Archive for the ‘Transmission’ Category

The Role of Retroviruses in Chronic Illness – A Clinician’s Perspective

https://klinghardtinstitute.com/wp-content/uploads/2018/05/IHCAN-Dr-K-article-HERV-05.1.pdf

The Role of Retroviruses in Chronic Illness- Dietrich Klinghardt, MD, PhD

The role of retroviruses in chronic illness is greatly disputed in academic circles. However, at the Sophia Health Institute Dr DIETRICH KLINGHARDT, MD, PhD, reports seeing significant improvement in treatment outcomes – in the most severely affected patients with chronic illness – when anti- retroviral strategies are included.

The results we are seeing at the Sophia Health Institute at our locations in Seattle and Marin County would not have been possible without the brilliant work of Judy Mikovits, PhD.

What is published and what illnesses are potentially caused by, or have as a contributing factor, activated retroviruses?

  • CNS-related illnesses: ME/CFS, Gulf War Syndrome, Autism, MS, Parkinson’s, ALS, Schizophrenia
  • Auto-immune diseases: Lupus, Crohn’s, Hashimoto’s Thyroiditis, Polymyositis, Sjogren’s syndrome, Bechet’s Disease, primary biliary cirrhosis
  • Cancer: prostate, breast, non-Hodgkin’s lymphoma, chronic lymphocytic leukaemia, mantle cell lymphoma, hairy cell leukaemia, bladder, colorectal, kidney, ovarian.

To that I am adding a list of other illnesses that have responded under my care to retroviral interventions: intractable Lyme disease, mold illness, insomnia, brain fog and all stages of a deteriorating brain, most childhood illnesses including ADHD and behavioural problems, asthma, breast cancer, lung cancer and many more.

Working backwards

What are retroviruses? The more familiar DNA viruses such as those from the “herpes family” – and many others – work their way from DNA over to RNA and from there to the manufacture of viral proteins. Retroviruses work their way backwards – from the RNA to the DNA – and then forward again from there.

Retroviruses are subdivided into different- lettered classes – Beta Retroviruses: HERV-K. Gamma Retroviruses: HERV-H and HERV-W.

The generally accepted key contributors to chronic illness are inflammation, oxidative stress and microbial infection. All of these are known triggers for retroviral activity, and in turn are also caused by retroviral activity.

Both human and animal retroviruses can infect the central nervous system (CNS). These are associated with many diseases of the CNS and cause neurological disease by several mechanisms:

1. Directly through infection of immune cells which traffic to the brain;

2. Indirectly through increases in proinflammatory cytokines and chemokines, or

3. In the absence of detectable brain inflammation indirect effects known as “bystander effects”- causing chronic retroviral replication of immune cells.

A retrovirus works via the enzyme “reverse transcriptase”. Once inside the cell, it uses the enzyme to force the cell to create viral DNA. This viral DNA becomes integrated into the host cell DNA. A retrovirus integrated into our genome may be passed from mother to child during pregnancy (Sakuma et al, 2012).

Only 2% of our DNA is protein-coding, but 6-8% of our DNA is retroviral DNA – passed down to us from our ancestors as scars from our constant encounter with an often hostile microbial and virus-rich environment (Stoyle, 2006, Mayer et al, 2011; Li et al, 2001). These viruses are referred to as Human Endogenous Retroviruses or HERVs.

However, not all embedded retroviral DNA is bad. Some sections have become a functional part of our genome because they have given us an evolutionary advantage, such as the formation of the p53 gene regulatory network (Shin et al, 2013; Barbusecu et al, 2001). Other retroviruses have to be silenced throughout life, mainly through DNA methylation and acetylation.

The transcription of retroviral DNA makes the infected person susceptible to numerous de-novo genetic mutations, including MTHFR, DNMT and other genes which control methylation. Many other illness-producing effects are known, implicating HERV-K in the pathogenesis of neuroinflammatory and autoimmune illnesses. For a patient to get well today, it is rarely enough to just interpret the genomic testing and to substitute accordingly.

Acquiring infection

How do we become infected? Retroviruses can be acquired (inhalation, blood-based products, physical contact) or the viruses already present in our DNA can be activated through influences such as a viral infection or chronic inflammation (Manghera and Douville, 2013).

For example, the Epstein Barr virus induces expression of the HERV-K envelope gene and the transactivation of MSRV, the Multiple Sclerosis retrovirus (Mameli et al, 2007; Sutkowski et al, 2001). Herpes simplex type-2 activates members of the HERV-W family. These and other mechanisms are likely responsible for the activation of HERVs seen in rheumatoid arthritis, SLE, Sjorgens disease, schizophrenia, autism, MS and cancer. Cell phone radiation has disabled many of our protective proteins (Fragopoulou et al, 2012) and so have many of the food-based toxins such as glyphosate (Seneff et al, 2017) and air-based inhalants (aluminium etc).  An unintended source of retroviruses are some vaccines as reported in Frontiers in Microbiology in January 2011).

Diagnosis

Currently PCR testing is only available to
the research community. We have to rely on indirect parameters:

  • decrease of CD56 NK cells (CD56 is involved in adhesion, migration, growth, differentiation and other cellular functions); down regulation of IL-13, IL-2, IFN gamma, TH-1 cytokines (J. Mikovits et al, 1998)
  • upregulated levels of TH-2 cytokines: IL-4, IL-10 and pro-inflammatory cytokines: IL-1, IL-6, IL-8 and TNF-alpha.
  • elevated levels of TGF beta-1: has profound effects on innate and adaptive immunity through stimulation of mast cells (often mistaken as mould-related). This may be the true cause of mastocytosis.

Other practical markers from my experience: low wbc (white blood count below 4500), low CD 56. I always include the CD 57 to rule out an active Borrelia burgdorferi infection as compounding factor.

Treatment

When the retroviruses are effectively addressed early in the treatment of chronic illness, other issues such as bacterial infections (Borrelia, Mycoplasma, Bartonella etc), mould illness, EBV, CMV, HHV-6, silent inflammation, parasites, heavy metal toxicity and many other problems become less symptomatic and often undetectable – and respond much better to treatment, even to interventions that have failed before.

Plants have been exposed to the same retroviruses as us, but for 300 million years longer – and many have developed potent adaptogens. Even though drugs like Truvada and AZT can be successfully used, I prefer the use of plant-based products that have unique anti-retroviral properties. A few examples with the key references:

  • Scutalaria root (Ruscetti et al: “Inhibition of HIV infection by baicalin – a flavonoid compound purified from Chinese herbal medicine”, Cellular & Molecular Biology Research 39, 2 (1993): 119-124).
  • Cistus incanus (Rebensburg et al: “Potent in vitro antiviral activity of Cistus incanus extract against HIV and Filoviruses targets viral envelope proteins”. Scientific Reports 6 (2016): 20394).
  • Broccoli sprouts (Furuya et al: “Sulforaphane inhibits HIV infection of macrophages through Nrf2.” PLoS Pathogens, 12.4 (2016): e1005581)
  • St John’s Wort (Meruelo, Lavie and Lavie: “Therapeutic agents with dramatic anti- retroviral activity and little toxicity at effective doses: aromatic polycyclic diones hypericin and pseudohypericin.” Proc Nal Acad Sci 85.14 (1988): 5230-5234).

In addition, I like to put my patients on a high dose of seleno-cysteine (commonly 800mcg, a dose that has been established as safe (Yang, G.; Zhou, R. (1994) “Further Observations on the Human Maximum Safe Dietary Selenium Intake in a Seleniferous Area of China”. Journal of Trace Elements and Electrolytes in Health and Disease. 8 (3–4): 159–165. Baum et al. “High risk of HIV- related mortality is associated with selenium deficiency.” JAIDS 15.5 (1997): 370-374).

Suramin, an old anti-parasitic, has turned out to be one of the most effective anti- retroviral agents. Retroviruses activate the “cell danger response” and the P2 purinergic receptor on each cell. Suramin downregulates this receptor and inhibits the binding of growth factors TGF-beta, EGF, PDGF to their receptors and thus antagonises the ability of these factors to stimulate growth of tumour cells. It can be given iv every six weeks.

I prefer giving daily homeopathic doses (Mitsuya et al: “Suramin protection of T cells in vitro against infectivity and cytopathic effect of HTLV-III.” Science 226.4671 (1984): 172-174).

When we use suitable liposomal extracts of plants in proper dose and frequency, together with selenium and “energetic copies” of immune modulators like suramin, olmetarsan (vitamin D receptor), rapamycin (mTOR), significant results can be achieved in the treatment of chronic illness that were not possible before. This new therapeutic approach should always be combined with the synergistic use of EMR protection, treatment of Lyme and co-infections, mould and metal detox.

• On June 10, Dr Klinghardt will present a one-day seminar on the correct and effective use of anti-retroviral interventions in chronic illness. For more information and to book see news story on page 9 and visit www. Klinghardtinstitute.com.

About the author

Dr DIETRICH KLINGHARDT studied medicine and psychology in Freiburg, Germany, completing his PhD on the involvement of the autonomic nervous system in autoimmune disorders. Early in his career he became interested in the sequelae of chronic toxicity (especially lead, mercury, environmental pollutants & electromagnetic fields) in the course of illness.

While working in India he encountered Eastern concepts of disease aetiology and blended them with his Western training. This laid the foundation for his 5-level system of Integrative Medicine. In the US he spent three years as a full-time emergency physician before becoming Medical Director of the Santa Fe Pain Centre.

Increasingly aware of the limitations of conventional medicine when dealing with chronic conditions, he trained in Ericksonian hypnotherapy and began to include body-oriented psychotherapeutic and counselling approaches in his work, along with neural therapy, mesotherapy injection techniques and applied psychoneurobiology. Dr Klinghardt has contributed significantly to the understanding of metal toxicity and its connection with chronic infections, illness and pain. He has been instrumental in advancing various fields within biological medicine – non-invasive pain management, injection techniques for pain and orthopaedic dysfunction, anti-ageing medicine, toxicology, paediatrics (neuro-developmental disorders), energy psychology, biological dentistry and others. He has also developed Autonomic Response Testing, a comprehensive diagnostic system that has helped many practitioners to become accomplished holistic physicians. He founded Sophia Health Institute in 2012, and is actively involved in patient care at his clinic.

______________

**Comment**

For more on Mikovitz’s work:  https://madisonarealymesupportgroup.com/2017/10/15/vaccines-and-retroviruses-a-whistleblower-reveals-what-the-government-is-hiding/

https://madisonarealymesupportgroup.com/2018/03/01/vaccines-could-contribute-to-disease-epidemics-due-to-retrovirus-contamination/

To hear the audio of the talk & slides, go here:  http://simplymimi.net/archives/1151


Northern & Southern CA Cats have Bartonella and Rickettsia – Proven by 16S rRNA Next Gen Sequencing

https://www.ncbi.nlm.nih.gov/m/pubmed/29893631/

Assessing Cat Flea Microbiomes in Northern and Southern California by 16S rRNA Next-Generation Sequencing.

Vasconcelos EJR, et al. Vector Borne Zoonotic Dis. 2018.

Abstract
Flea-borne diseases (FBDs) impact both human and animal health worldwide. Because adult fleas are obligately hematophagous and can harbor potential pathogens, fleas act as ectoparasites of vertebrates, as well as zoonotic disease vectors. Cat fleas (Ctenocephalides felis) are important vectors of two zoonotic bacterial genera listed as priority pathogens by the National Institute of Allergy and Infectious Diseases (NIAID-USA): Bartonella spp. and Rickettsia spp., causative agents of bartonelloses and rickettsioses, respectively.

In this study, we introduce the first microbiome analysis of C. felis samples from California, determining the presence and abundance of relevant pathogenic genera by characterizing the cat flea microbiome through 16S rRNA next-generation sequencing (16S-NGS). Samples from both northern (NoCal) and southern (SoCal) California were assessed to expand current knowledge regarding FBDs in the state. We identified Rickettsia and Bartonella, as well as the endosymbiont Wolbachia, as the most abundant genera, followed by less abundant taxa. In comparison to our previous study screening Californian cat fleas for rickettsiae using PCR/digestion/sequencing of the ompB gene, the 16S-NGS approach applied herein showed a 95% level of agreement in detecting Rickettsia spp. There was no overall difference in microbiome diversity between NoCal and SoCal samples. Bacterial taxa identified by 16S-NGS in this study may help to improve epidemiological investigations, pathogen surveillance efforts, and clinical diagnostics of FBDs in California and elsewhere.

_____________

**Comment**

Bartonella and Rickettsia spp. are also diseases Lyme/MSIDS patients have to contend with.  There is no good, solid research studying the ability of ticks to transmit Bartonella, yet most of us out here in Lyme land have it.  Rickettsia’s out here too in plenty.  I would think this important issue would be dealt with.  Somehow patients are getting these diseases and its either happening by direct transmission or by being activated once they get Lyme and their immune systems become compromised.

Either way, this issue MUST be studied, resolved, and appropriately death with.

Mainstream medicine is completely lost when it comes to tick borne illnesses such as these.  Lyme is finally getting acknowledged due to shear numbers, but don’t kid yourself, thousands upon thousands have Bartonella and Rickettsia as well.  The one drug, one pathogen paradigm needs to be forgotten like a bad dream and researchers and doctors need to become educated on this complex 21st Century plague.

BTW:  Wolbachia is being widely used as a biocontrol.  Here’s why that may not be such a great idea:  https://madisonarealymesupportgroup.com/2017/07/10/wolbachia-the-next-frankenstein/

https://madisonarealymesupportgroup.com/2018/02/12/wolbachia-laced-mosquitoes-being-released-why-lyme-msids-patients-might-be-negatively-affected/

https://madisonarealymesupportgroup.com/2018/05/22/mosquito-spit-alone-may-significantly-alter-your-immune-system-for-days-after-a-bite/

https://madisonarealymesupportgroup.com/2018/05/02/tick-mosquito-and-flea-diseases-more-than-tripled-since-2004/

It is my strong opinion that ALL of these factors are a perfect storm of events causing human suffering and disease.  Researchers need to zoom out and look at the big picture and the interconnection of things or we are doomed.

Counterpoint: We Don’t Take Lyme Seriously Enough

http://thechronicleherald.ca/opinion/1577953-counterpoint-we-don’t-take-lyme-seriously-enough#.WybeW46-8U4.linkedin

COUNTERPOINT: We don’t take Lyme seriously enough

by JIM WILSON

Published June 16, 2018

Diagnosis, treatment is still lacking in Nova Scotia
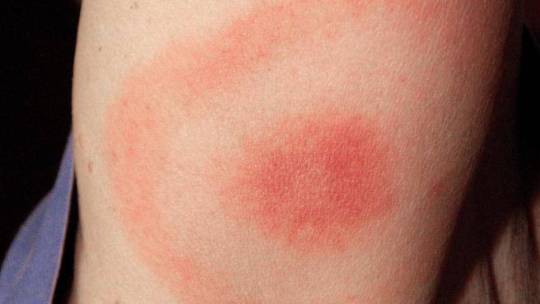
B97808243Z.120180615163154000GK8L2CS6.11The bullseye rash, like the one pictured on a woman’s arm above, is often associated with the early stages of Lyme disease. (JAMES GATHANY)

Re: your June 9 Letter of the Week: “Stop pushing the Lyme disease panic button.” I think it is time for a different take than what’s offered in this letter and the June 3 news article it stemmed from, “Public health failing to address Lyme disease crisis, says author.”

Born in Nova Scotia, I contracted Lyme disease in Dartmouth in 1991.

Little has improved since then, except for awareness.

Diagnosis and treatment are still very poor. Testing for Lyme disease is not even recommended until at least two to three weeks after infection because the current testing protocols used Canada-wide are indirect tests — checking to see if the patient has developed detectable levels of antibodies to the bacterium that causes Lyme disease (borreliosis), and it takes that long for us to develop the antibodies. By then, the disease has moved into deep tissue.

Lyme disease is not easily preventable; it requires daily due diligence and even then you can still become infected.

It may require landscaping redesign of your property, separating tick habitat from your living space.

Ticks, especially those that transmit Lyme disease, are tiny and not easily seen. Frequently, if you see one tick on you, you may miss other ticks that are in areas of the body not easily observed, including under the hair and in private parts.

Also, Canada says it is keen on prevention. Yet a majority of countries have approved products for sale designed to prevent ticks from attaching, such as permethrin-soaked clothing and eucalyptus oil with icaridin. Only after years of asking, Health Canada finally approved permethrin-soaked clothing to be sold here, but strangely only to prevent insect bites, not tick attachments (unlike 45 other countries).

Also, the eucalyptus-oil-based products containing icaridin (also called picaridin) that have been shown to be very effective have not been approved for sale in Canada either. So is Canada truly concerned about prevention? It appears not.

Rhode Island, a tiny U.S. state, has 9,000-plus cases per year, using the United States Center for Disease Control model of 10 times the confirmed cases (due in large part to poor tests, poor medical education and other reasons).

It is illogical to blame the individual for not taking precautions, which is the implication in the article and in this letter.

The fact is, even with the best of precautions and awareness, people are still becoming infected in record numbers, as there is a large amount of under-reporting.

The article and the letter also fail to point out that ticks do not only transmit Lyme disease.

Our motto at the Canadian Lyme Disease Foundation (CanLyme.org) is No Tick Is A Good Tick.

That’s because we must be concerned about all species of ticks that will attach to humans. They are all capable of transmitting various diseases (ehrlichiosis, babesiosis, rocky mountain spotted fever, etc.) — some requiring only a short period of attachment — and they can deliver serious neurotoxins such as tick paralysis (from the Dermacentor ticks commonly known in the west as the wood tick and in eastern and central Canada, the dog tick).

According to the original article, “Heather Fairbairn, a spokeswoman with the province’s public health department, states Lyme disease is easily curable both in the early and later states of the disease.”

That is simply an irresponsible statement that flies in the face of all credible evidence-based, grade-level science.

If caught very early, it can usually be cured with antibiotics. Sadly though, most cases are not diagnosed early — and typically it is only those who present with a nicely defined bull’s-eye rash who are.

But most people do not get that rash.

You can easily apply the “10 times of reported confirmed cases” estimate to Nova Scotia as well, putting the likely number of cases at around 4,000 per year — not around 400 — showing clearly that it is not easily prevented.

Later-stage Lyme disease is very difficult to treat in many cases — again a well-known fact supported by all studies done on animals and thousands of individuals’ testimony (similar to the 100 people who testified on camera at the 2016 Lyme disease conference sponsored by the Public Health Agency of Canada as required by federal legislation enacted with all-party, unanimous support).

The legislation came about due to misinformation by government and medical authorities over decades.

Physicians are improperly educated and not given the true picture of Lyme borreliosis and other tick-borne diseases. People do not have access to adequate diagnosis and treatment.

Jim Wilson is president of the Canadian Lyme Disease Foundation.

_____________

**Comment**

Bravo, Jim.  You are spot on.

33 Years of Documentation of Maternal-Child Transmission of Lyme Disease and Congenital Lyme Borreliosis – A Review

https://www.lymehope.ca/news-and-updates/33-years-of-documentation-of-maternal-child-transmission-of-lyme-disease-and-congenital-lyme-borreliosis-a-review-by-sue-faber-rn-bscn

33 Years of Documentation of Maternal-Child Transmission of Lyme Disease and Congenital Lyme Borreliosis – A Review

by Sue Faber, RN, BScN

6/16/2018

‘Transplacental transmission, adverse outcomes and reports of congenital infection of Borrelia Burgdorferi have been clearly documented over the last 33 years (1985 to 2018) by multiple international physicians, researchers, scientists and other experts. As entire families worldwide are affected by Lyme borreliosis resulting in serious debilitating illness and complex multi-systemic chronic infection, we must take this alternate mode of transmission – from mother to child in pregnancy, seriously.

For Lyme disease to be passed from mother to child in pregnancy drastically changes the narrative, we know that, it opens up new issues and challenges – however, recognizing it for what it is, is the right thing to do. It means upheaval and reordering and re-prioritizing in what has been taught and rethinking many areas of concern which perhaps have been looked over – but we must remember – we have no choice but to act with the highest integrity and honesty.

We have no option but to constructively engage, discuss and determine solutions and a clear path forward which will be a light for those who suffer, a beacon of Hope and healing. We need to prevent more miscarriages, stillbirths and babies from being born with Lyme and tick-borne illnesses – potentially leading to chronic pervasive, persistent and often disabling illness’. Sue Faber, RN.

https://www.lymehope.ca/uploads/8/4/2/8/84284900/updated_june_16_2018_-_32_years_of_literature_review_march_18_2018.pdf  (Excerpt below.  Please see link for more studies)

“Now we have found a spirochete capable of spreading transplacentally to the organs of the fetus, causing congenital heart disease and possible death of the infant.”

Dr. Willy Burgdorfer – The Enlarging Spectrum of Tick-Borne Spirochetoses: R. R. Parker Memorial Address, Reviews of Infectious Diseases. Vol 8, No 6. November-December 1986.

“It is clear that B. Burgdorferi can be transmitted in the blood of infected pregnant women across the placenta into the fetus. This has now been documented with resultant congenital infections and fetal demise. Spirochetes can be recovered or seen in infant’s tissues including the brain, spleen and kidney. The chronic villi of the placenta show and increase in Hofbauer cells as in luetic placentitis. Inflammatory changes of fetal or neonatal changes are not as pronounced as in the adult, but cardiac abnormalities, including intracardiac septal defects, have been seen. It is not known why inflammatory cells are so sparse from maternal transmission, but it is possible that an immature immune system plays a role.”

Dr Paul Duray and Dr Allen Steere – Clinical Pathologic Correlations of Lyme Disease by Stage. 1988.

“It is anticipated that more infants and fetuses with complications related to gestational Lyme borreliosis will be diagnosed in the future as the diagnosis is more frequently considered; it eventually will be possible to better describe the various clinical manifestations of congenital Lyme borreliosis.

“..in order for infants with congenital Lyme borreliosis and therefore initiation of prompt antibiotic therapy of the congenitally infected infant usually depend on suspicion or confirmation of Lyme borreliosis in the mother. Therefore, in order for infants with congenital Lyme borreliosis to be recognized, it is essential for clinicians caring for newborns and infants to become familiar with the various manifestations of Lyme borreliosis in the adult, as well as in the congenitally infected infant.”

“(serology) does not appear to be a sensitive method of diagnosis and reliance on sero-positivity leads to misdiagnosis of the majority of congenitally infected infants.”

“Large-scale, prospective studies of sufficient numbers of patients with Lyme borreliosis with follow-up to determine the pregnancy outcome of each enrolled patient; B burgdorferi-specific evaluation of any fetal or neonatal demise; and long-term follow-up of each infant born to determine the occurrence of possible early and late sequelae are needed.”

Dr. Tessa Gardner, Pediatric Infectious Disease MD, trained at Harvard University, 2001. Gardner, T. Lyme disease. In: Remington JK, J. editor. Infectious Diseases of the Fetus and Newborn. 5th ed: Saunders; 2001

“Transmission of Borrelia infection occurs via both zoonotic vectors and other humans. Congenital transfer is an established fact. Maternal to fetal transfer of Borrelia, can furthermore be clinically silent or unrecognized, and if not successfully treated, infection can be life long and latency, late activation and reactivation can occur.”

O’Brien J, Hamidi O. Lyme Disease (www.smgebooks.com). Infection with Borrelia: Implications for Pregnancy, Nov. 2017.

“Intra-human transfer of Borrelia can be initially silent or unrecognized’

‘The similarities of the clinical presentation of congenital syphilis to pregnancies with acute Lyme disease helps guide ante partum management. Due to the severity of previously documented cases, there should be a low threshold of suspicion to diagnose cases of Lyme disease in pregnancy.”

O’Brien J, Hamidi O. ‘Borreliosis Infection during Pregnancy’. Ann Clin Cytol Pathol 3(8). Oct. 2017.

“Pregnant women who are acutely infected with Borrelia burgdorferi (the primary cause of Lyme disease) and do not receive treatment have experienced multiple adverse pregnancy outcomes including preterm delivery, infants born with rash and stillbirth.”

“In obstetric patients acutely infected during the first trimester, a fetal echocardiogram is reasonable, given the demonstrated high potential of fetal cardiac abnormalities.’

O’Brien J, Baum, J. Case Report. The Journal of Family Practice. Vol 66, No 8, Aug, 2017.

“It was stated and proved transplacental transfer of borrelia”

“We need serious studies among pregnant women and newborn children in endemic regions…and in the future such patients should be monitored throughout pregnancy and after childbirth. Children born to these women should be examined for tick-borne infections at least during the first two years of life.”

Utenkova EO. Lyme disease and Pregnancy. Kirov State Medical Academy, Kirov Russia. Journal of Infectology, Volume 8, Number 2, 2016. *translated from Russian

“a new acronym is needed to include other, well-described cause of in utero infection: syphilis, enteroviruses, varicella zoster virus, HIV, Lyme disease (Borrelia burgdorferi) and parvovirus.”

“In utero infection and intrapartum infections may lead to late-onset disease. Such infections may not be apparent at birth but may manifest with signs and symptoms weeks, months or years later.”

Maldonado Y, Nizet V, Klein J et al. Current Concepts of Infections of the Fetus and Newborn Infant (Chapter 1). Found in Remington and Klein’s Infectious Diseases of the Fetus and Newborn Infant, 8th ed., 2016.

“Histological observations have confirmed the presence of Bb in children with congenital Lyme disease. It is interesting that spirochetes may exist in the spleen, kidney, bone marrow and nervous system.”

“The ability of long term survival of Bb sl in tissues and spreading of spirochetes in the body despite antibiotic treatment can contribute to intergenerational infection with Lyme disease.”

Jasik K, Okla H, Slodki J et al. Congenital Tick-Borne Diseases, is this an alternative route of transmission of tick- borne pathogens in mammals? Vector- Borne and Zoonotic Diseases, Volume 15, Number 11, 2015.

“these documented cases strongly suggest that transplacental transfer occurred via identification of Borrelia Burgdorferi in fetal tissues by culture, immunohistochemistry or indirect immunofluorescence.”

“the outcome of a pregnancy affected by Lyme disease remains relatively unknown and unstudied. However, it is still important to equip obstetrical patients with information that will help protect them against Lyme disease and provide treatment options if a suspected case of Lyme disease occurs during pregnancy.”

O’Brien JM, Martens MG. Lyme disease in Pregnancy, a New Jersey Medical Advisory. MD Advisor, 2014;7:24- 27.

“Borrelia Burgdorferi does appear to cross the placenta and infect the fetus. There are data to suggest an increased incidence of spontaneous abortion, stillbirth and congenital malformations associated with Lyme disease.”

“Adverse pregnancy outcomes are also more likely in women with untreated Lyme disease.”

Dotters-Katz S, Kuller J, Heine P. Arthropod-Borne Bacterial Diseases in Pregnancy. Obstetrical and Gynecological Survey, Vol 68(9). 2013.

“The parents of the five children in the study could not pinpoint an exact date of infection, but their treating physician suggested that the Bb bacteria could have been transmitted congenitally since all five of their mothers were diagnosed with Lyme disease and Bb has been shown to be transmitted congenitally in infected mothers. If the Bb bacteria were transmitted congenitally and this latency period presented itself in the infected children it could lead to an explanation of their late onset autistic symptomology.”

Kuhn M, Grave S, Bransfield R, Harris S. Long term antibiotics therapy may be an effective treatment for children co-morbid with Lyme Disease and Autism Spectrum Disorder. Medical Hypothesis (2012)

“The clinical picture of a fetus infected by B Burgdorferi is similar to that seen in the course of a syphilis infection. Most frequently they are: premature birth, intrauterine foetus death and malformation

“In the second stage of the illness, B. Burgdorferi traverses the placental barrier. Apart from foetal death, the following occur most frequently: syndactyly, sight loss, premature birth, neonatal rash, heart, liver, kidney damage or damage to the central nervous system.”

Relic, M, Relic, G. Lyme borreliosis and pregnancy. Vojnosanit Pregl 2012; 69(1):994-998. *translated from Polish

For more:  https://madisonarealymesupportgroup.com/2018/02/26/transplacental-transmission-fetal-damage-with-lyme-disease/

https://madisonarealymesupportgroup.com/2018/05/24/new-berlin-mom-given-life-altering-lyme-disease-diagnoses-after-pregnancy/

https://madisonarealymesupportgroup.com/2017/10/15/pregnancy-in-lyme-dr-ann-corson/


Tick-Borne Disease Working Group Subcommittee Reports – Comments due by June 18

https://www.hhs.gov/ash/advisory-committees/tickbornedisease/reports/index.html

Reports

The Tick-Borne Disease Working Group (Working Group) is required to submit a report on its activities and any recommendations to the HHS Secretary and Congress every two years. The first report is due December 2018.

The six subcommittees of the Working Group prepared reports to inform the Working Group and its 14 voting members. These reports offer insights into gaps, opportunities and potentials actions to be considered by the Working Group for the report to Congress and HHS Secretary. 

Report of the Access to Care Services and Support to Patients Subcommittee

Report of the Disease Vectors, Surveillance, and Prevention Subcommittee

Report of the Other Tick-Borne Diseases and Co-Infections Subcommittee

Report of the Pathogenesis, Transmission and Treatment Subcommittee

Report of the Testing and Diagnostics Subcommittee

Report of the Vaccine and Therapeutics Subcommittee


You may make comment either by writing or verbally by June 18th, for the next meeting on June 21st.

Go here for the June 21st meeting.
https://www.hhs.gov/ash/advisorycommittees/tickbornedisease/meetings/index.html