One thousand patients with tick bites were treated with a 10% Azithromycin antibiotic gel within 72 hours of attachment. None developed Lyme borreliosis. Of the control group, receiving a placebo, 7 contracted LD.
The gel has to be applied every 12 hours over three days to be effective.
While this is certainly a wonderful tool for our toolbox, consider the story of the little girl who in under six hours developed a facial palsy and the inability to walk or talk after a tick bite. https://madisonarealymesupportgroup.com/2016/12/07/igenex-presentation/ If it were not for the fast actions of an experienced Lyme literate doctor giving her injectable antibiotics, the outcome could have been devastating and life changing.
This demonstrates that infection can enter the central nervous system quickly and cause neurological symptoms, which if left untreated can cause damage. I wish the study followed the people for a year, minimum. Symptoms with Lyme (borrelia) tend to wax, wane, and migrate, often fooling people into thinking their symptoms are age-related.
Multi-Organ Involvement Confounding the Diagnosis of Bartonella henselae Infective Endocarditis in Children with Congenital Heart Disease.
Ouellette CP, Joshi S, Texter K, Jaggi P.
Abstract
Two children with congenital heart disease status-post surgical correction presented with prolonged constitutional symptoms, hepatosplenomegaly and pancytopenia. Concern for malignancy prompted bone marrow biopsies that were without evidence thereof. In case #1, echocardiography identified a multilobulated vegetation on the conduit valve. In case #2, transthoracic, transesophageal and intracardiac echocardiography were performed and were without evidence of cardiac vegetations, however pulmonic emboli raised concern for infective endocarditis. Both patients underwent surgical resection of the infected material and had histopathologic evidence of infective endocarditis. Further diagnostics identified elevated cytoplasmic anti-neutrophil cytoplasmic antibodies and anti-proteinase 3 antibodies in addition to acute kidney injury with crescentic glomerulonephritis on renal biopsy. Serologic evidence of infection with B. henselae was observed in both patients.These two cases highlight the potential multi-organ involvement that may confound the diagnosis of culture negative infective endocarditis due to B. henselae.
PMID: 28027277 DOI: 10.1097/INF.0000000000001510
He also states that those with familial Alzheimer’s have some of the highest levels ever measured that are similar to fatal cases of aluminum-induced encephalopathy in patients also undergoing renal dialysis.
Published on Jun 9, 2016
Dr. Marc Siegel explains on ‘Fox & Friends’ how Kris Kristofferson was diagnosed with Alzheimer’s but actually had Lyme Disease. (Warning: the news reporter propagates a myth that “One antibiotic,” prophylactically will cure LD if used early.
The Take Home: One or two pills of doxycycline will not cure LD.
What is aluminum in and how can we avoid it?
Most Vaccines:(Hepatitis A, B, Hib, DTaP, pneumococcal, Gardasil, and others.) Aluminum is added as an adjuvant that when mixed with a viral or bacterial antigen creates a greater inflammatory immune response which theoretically elicits a higher response of protective antibodies. The problem with this, according to Dr. Mercola, is that vaccines containing inactivated microbes promote antibody-mediated (Th2) immunity which means your body is less prepared to fight infections and more apt to acquire allergies.http://www.thevaccinereaction.org/2016/06/how-aluminum-in-vaccines-affects-your-health/ (Read this well written article about how vaccines work)
According to Dr. Mercola, aluminum injected into a muscle is 100% absorbed by the body, whereas, when ingested it 2-1.5% is absorbed. Also, there seems to be no upper limit in the vaccine program, with the number of aluminum containing vaccines quadrupling over the past 30 years.
The truly frightening aspect of vaccines is that studies have shown that immediately after vaccine injection, macrophages race to eat up the aluminum and the antigen and have the ability to go right through the blood brain barrier into the brain like a Trojan horse – delivering aluminum directly to the brain. This, if you remember, is what Exley warns about – an accumulation of aluminum in the brain – which is a part of the perfect storm of Alzheimer’s. Adding to the perfect storm are infections such as tick borne infections, inflammation (which TBI’s also cause), mitochondrial problems (TBI’s can cause), dysbiosis (think “leaky gut” which TBI’s can cause as well as yeast/fungus due to antibiotic use), premature birth, irradiation, infant formulas, and methamphetamines.
Antiperspirants: Aluminum (chloride, chlorohydrate, zirconium) salts can make up 25% of some antiperspirants, and after a single application about .012% of aluminum may be absorbed. The tally over a life-time of use is huge. http://articles.mercola.com/sites/articles/archive/2010/02/16/aluminum-lurks-in-crystal-deodorants.aspx Look in your health food store for alternatives or take a pinch of baking soda mixed into water and apply to underarms.
Food supply: http://articles.mercola.com/sites/articles/archive/2014/03/22/aluminum-toxicity-alzheimers.aspx Aluminum compounds are often added into foodstuffs as well as by contamination with aluminum equipment. Baking powder, self rising flour, salt, baby formula, coffee creamers, baked goods and processed foods, coloring and caking agents often have aluminum.Read labels. Cooking in aluminum foil increases concentration. Avoid aluminum laminated pouch drinks.
Drugs: antacids, analgesics, anti-diarrheals and additives like magnesium stearate.
Toothpaste: read labels and avoid aluminum oxyhydroxide.
• Silica-rich water, such as Fiji water,17 which contains 83 Mg of silica per liter. Research published in 2013 showed that drinking up to one liter of a silicon-rich mineral water daily for 12 weeks effectively excreted aluminum via the urine, without detrimental effects on essential metals such as iron and copper. According to the authors: “We have provided preliminary evidence that over 12 weeks of silicon-rich mineral water therapy the body burden of aluminum fell in individuals with Alzheimer’s disease and, concomitantly, cognitive performance showed clinically relevant improvements in at least 3 out of 15 individuals.” • Melatonin: Research shows that melatonin has a metal binding role and is a useful supplement in the treatment of neurological disorders in which oxidative stress is involved, which includes Alzheimer’s. Melatonin can travel freely across all cellular barriers, facilitating the removal of toxic metals such as aluminum. It also appears to suppress the oxidative activity of aluminum in your brain. • Anything that raises your glutathione. Your body synthesizes glutathione from three amino acids: cysteine, glutamate, and glycine. Raw fruits and vegetables, particularly avocado, asparagus, grapefruit, strawberries, orange, tomato, cantaloupe, broccoli, okra, peach, zucchini, and spinach are rich in the precursors glutamate and glycine. Dietary sources of cysteine include eggs, meat, red peppers, garlic, onions, Brussels sprouts, whey protein, and wheat germ. Other helpful treatments for improved glutathione metabolism include: ◦ Exercise: Exercise affects your adenosine triphosphate (ATP) levels needed to help produce glutathione ◦ Optimizing your vitamin D levels through sun exposure: There’s some evidence vitamin D increases intracellular glutathione levels ◦ Epsom salt baths ◦ MSM supplementation ◦ The supplement N-acetyl L-cysteine (NAC) may also be useful. NAC is the rate-limiting nutrient for the formation of the intracellular antioxidant glutathione • Curcumin: Research suggests that curcumin has a protective effect against aluminum-induced damage by modulating the extent of oxidative stress. It also decreases beta-amyloid plaques associated with Alzheimer’s, delays neuron degradation, chelates metals, decreases microglia formation, and has an overall anti-inflammatory, antioxidant effect. Studies have shown that curcumin can help improve memory in Alzheimer’s patients. There are some contraindications that curcumin is not recommended if you have biliary tract obstruction (as it stimulates bile secretion), gallstones, obstructive jaundice, or acute biliary colic.
Tick-borne pathogens transmitted byIxodes scapularis Say (Acari: Ixodidae), also known as the deer tick or blacklegged tick, are increasing in incidence and geographic distribution in the United States. We examined the risk of tick-borne disease exposure in 9 national parks across six Northeastern and Mid-Atlantic States and the District of Columbia in 2014 and 2015. To assess the recreational risk to park visitors, we sampled for ticks along frequently used trails and calculated the density of I. scapularisnymphs (DON) and the density of infected nymphs (DIN). We determined the nymphal infection prevalence of I. scapularis with a suite of tick-borne pathogens including Borrelia burgdorferi, Borrelia miyamotoi, Anaplasma phagocytophilum,and Babesia microti. Ixodes scapularisnymphs were found in all national park units; DON ranged from 0.40 to 13.73 nymphs per 100 m2. Borrelia burgdorferi, the causative agent of Lyme disease, was found at all sites where I. scapularis was documented; DIN with B. burgdorferi ranged from 0.06 to 5.71 nymphs per 100 m2. Borrelia miyamotoi and A. phagocytophilum were documented at 60% and 70% of the parks, respectively, while Ba. microti occurred at just 20% of the parks.Ixodes scapularis is well established across much of the Northeastern and Mid-Atlantic States, and our results are generally consistent with previous studies conducted near the areas we sampled. Newly established I. scapularis populations were documented in two locations: Washington, D.C. (Rock Creek Park) and Greene County, Virginia (Shenandoah National Park).This research demonstrates the potential risk of tick-borne pathogen exposure in national parks and can be used to educate park visitors about the importance of preventative actions to minimize tick exposure.
In the eastern United States, the blacklegged tick, Ixodes scapularis Say, is the primary vector of Borrelia burgdorferi, the causative agent of Lyme disease, which is the most commonly reported vector-borne disease in the United States (Mead 2015). Ixodes scapularis also vectors other pathogens that can cause potentially serious disease, including Borrelia miyamotoi, Anaplasma phagocytophilum, and Babesia microti (Barbour and Fish 1993, Homer et al. 2000, Jin et al. 2012, Krause et al. 2015). Established blacklegged tick populations are nearly continuous across counties in the Northeastern and North-Central United States where the majority of I. scapularis-borne disease cases are reported (Mead 2015, Eisen et al. 2016). The risk of acquiring Lyme disease is influenced by spatio-temporal variation in the density of host-seeking infected nymphs (Diuk-Wasser et al. 2012). This metric often correlates with Lyme disease incidence, though to varying degrees (Mather et al. 1996, Stafford et al. 1998, Falco et al. 1999, Pepin et al. 2012). Human behavior, including time spent in tick-infested areas or engaged in behaviors that enhance or reduce the likelihood of encounters with ticks (Orloski et al. 2000, Connally et al. 2009), also influences the likelihood of acquiring Lyme disease and may explain some of the lack of concordance between measures of density of infected host-seeking nymphs and Lyme disease incidence (Pepin et al. 2012).
Understanding where people may come into contact with infected vector-competent ticks is central to mitigating tick-borne disease risk. For example, in the Mid-Atlantic and Northeastern United States, peridomestic exposure to I. scapularis likely occurs frequently (Falco and Fish 1988, Maupin et al. 1991, Klein et al. 1996, Connally et al. 2006, Feldman et al. 2015), whereas in the North-Central United States, recreational exposures are believed to be more common than peridomestic exposures (Kitron and Kazmierczak 1997, Paskewitz et al. 2001). Regardless of geographic region, previous studies have demonstrated a risk of human exposure to infected host-seeking I. scapularis nymphs in recreational settings (Falco and Fish 1989, Schulze et al. 1992, Oliver and Howard 1998, Paskewitz et al. 2001, Han et al. 2014, Prusinski et al. 2014, Ford et al. 2015). National parks are popular recreation destinations and may represent areas of elevated acarological risk, yet one cannot adequately infer the risk of tick-borne disease for park visitors or employees from the epidemiological surveillance conducted at the county spatial scale (Eisen et al. 2013). National parks often vary ecologically from surrounding areas, and thus the density of infected ticks may differ between settings; further, human behavior within the parks may differ from behavior in surrounding communities.
In this study, we sought to characterize the acarological risk, that is, the risk of human exposure to tick-borne pathogens, in national parks in the Eastern United States. We surveyed frequently used trails in national park units across six Northeastern and Mid-Atlantic States and the District of Columbia, ranging from Maine in the north to Virginia in the south. Our collection efforts focused on the nymphal stage of I. scapularis. This stage likely poses the greatest threat of transmission of B. burgdorferi and other pathogens to humans, as peak activity of questing nymphs occurs in late spring and early summer which coincides with peak onset of human disease (Piesman 1989, Fish 1993, Falco et al. 1999, Mead 2015). Here, we describe the diversity of ticks collected by drag sampling during summer months, density of host-seeking I. scapularis nymphs, and diversity and prevalence of B. burgdorferi, B. miyamotoi, A. phagocytophilum, and Ba. microti infection in I. scapularis nymphs.
“North Carolina cat owners who have a child between 5 and 9 are among groups with the highest national household risk of cat scratch disease.
CDC guidelines recommend that owners keep cats inside at all times as part of guidelines to reduce incidence of cat scratch disease.
That was among the takeaways from a talk by Centers for Disease Control epidemiologist Christina Nelson, who presented results from the paper, “Cat Scratch Disease in the United States: Sinking Our Claws into the Data,” at the One Medicine conference this month at Research Triangle Park.
‘Efforts should target cat owners in the South, with children in the household, and/or people with immunocompromised conditions,’ Nelson said when talking about ways to combat the disease.
Cat scratch fever, or bartonella, as it’s known to scientists, attracts a lot of attention, perhaps because three of 10 American households have cats, perhaps because of its mention in a risque 1970s rock song, Nelson said. No matter the reason, an edition of Emerging Infectious Diseases in which the Nelson’s article on the disease ran attracted the largest number of online visits in the academic journal’s history.
Cat scratch disease often runs its course within two to four months, but related disorders can require antibiotics or other treatment.
The disease is caused by the spread of the bacterium Bartonella henselae through cat fleas, then to humans via animals’ scratches and sometimes bites. Primary symptoms include fever and enlargement of lymph nodes near the scratch site, but other manifestations can include swelling of the retina or Parinaud oculoglandular syndrome (swollen eye accompanying swollen nodes) as well as bone, brain or heart infections, according to the paper.
Because physicians are not required to report cat scratch disease to public health authorities, Nelson and colleagues examined diagnoses based on an insurance industry resource, Truven Health MarketScan. The database details diagnoses of company-insured employees and their families. That meant people over 65, insured by Medicare, were not included.
‘There were about 35 million people involved,’ Nelson said. ‘It’s an enormous database.’
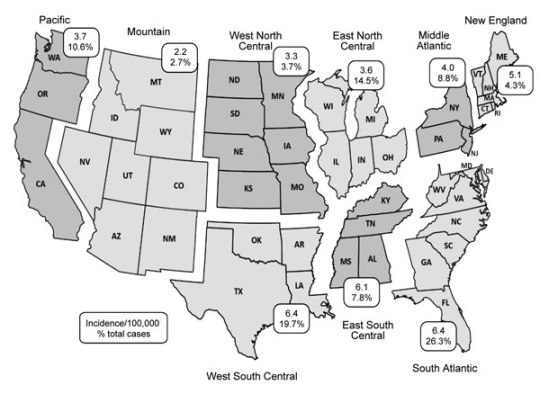
They found more than 500 inpatients and more than 12,500 outpatients are treated for cat scratch disease annually.
Among the findings of the study:
With an incidence of 6.1-6.4 per 100,000 population, North Carolina lies in the geographic region, the South Atlantic, with the highest U.S. incidence of cat scratch disease. More than one in four U.S. cases occurs in this region. An average of 4.5 patients out of 100,000 received outpatient treatment for the disease; 19 patients out of 100,000 required inpatient treatment, for an average of three days. Children age 5 to 9 accounted for the highest incidence of cat scratch fever cases — 9 outpatient cases and .4 inpatient cases per 100,000. Females made up more than six in 10 outpatients and 55.6 percent of inpatients. Mean cost of care per inpatient was $244, with inpatient treatment and followup costing $13,663. Overall disease costs nationally were nearly $10 million. Nelson noted that researchers were puzzled by an increase in cat scratch disease cases in January. Attendees at the RTP conference immediately suggested an answer.
“Christmas kittens!” they chorused.
Among the things the study did not say: That people can get the disease from kissing cats.
Nonetheless, news outlets took the CDC study and ran with it, in some cases, a bit too far. NPR had to run a correction: noting that people cannot get the disease from kissing cats.
‘This is incorrect. People can get the disease if an infected cat licks a scratch or wound,’ the correction read.
How to keep incidence down
Speakers at the conference suggested using the Healthy Pets Healthy People site as a resource for dealing with cat scratch disease.
The CDC suggested these means to reduce incidence:
People bitten by cats should Immediately clean the bite with soap and water People, especially those with weakened immune systems, should wash their hands with soap and water after playing with cats. Because kittens less than a year old are more likely to harbor the bacterium, people who have weakened immune systems should adopt cats older than one year. People shouldn’t play with or pet feral cats. Cats shouldn’t be allowed to lick open wounds. Cats should have nails trimmed, use vet-approved flea products, and be checked regularly with a flea comb. Cats should stay indoors to reduce exposure to fleas and to avoid fights with flea-infected animals. ‘Some shelters will not adopt a cat out unless the owners pledge never to let the cat outside,’ audience member Marcia Herman-Giddens, a Triangle area teacher and researcher, noted during a discussion period.
CSD belongs to the disease group Bartonellosis ‘Bartonellosis is a group of emerging infectious diseases caused by bacteria belonging to the Bartonella genus. Bartonella includes at least 22 named species of bacteria that are mainly transmitted by carriers (vectors), including fleas, lice, or sandflies. Both domestic and wild animals can be infected with Bartonella species by these vectors. Among the Bartonella species, at least 14 have been implicated in diseases that can be transmitted from animals to people (zoonotic disease). Of these zoonotic species, several may be transmitted to humans by companion animals (dogs and cats), typically through a bite or scratch.’ Source: National Organization for Rare Disorders
http://www.columbia-lyme.org/patients/tbd_bartonella.html “Bartonella are also found in numerous arthropods, biting flies, and ticks. The evidence for ticks as vectors is circumstantial but fairly strong. Recent studies in both the United States and Europe have found that Ixodes ticks harbor B. henselae in addition to Borrelia, Babesia and Anaplasma organisms; in fact, a 2004 PCR analysis of I. Scapularis ticks in New Jersey discovered that a higher percentage of ticks were infected with B. henselae than any of these other pathogens. In addition, B. henselae has been detected in the spinal fluid of patients co-infected with Borrelia burgdorferi, the agent of Lyme disease.”