Columbia University Needs Volunteers for a Chronic Lyme Study


https://www.linkedin.com/pulse/cdcs-profile-plummets-while-15-government-authorities-luche-thayer by Jenna Luche-Thayer July 4, 2017
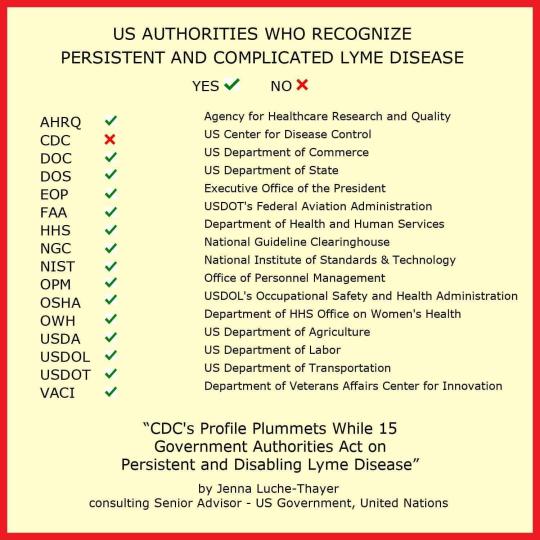
How is it that 15 government authorities have adopted policies recognizing Lyme disease as a serious illness, easily incurred through common outdoor activity, that may have systemic and chronic disabling complications? These authorities acknowledge that delayed treatment may be ineffective once the disease is systemic, that a delay in diagnosis may result in severe and chronic complications and prolonged antimicrobial treatments may be required. They acknowledge it may result in loss of livelihood and severe financial hardship.
When did other federal agencies decide that CDC Lyme information was insufficient? Was it due to some failing rationale created to tamp down public fears of the epidemic for which the CDC has no clear strategy to control or cure?
Why are CDC views regarding Lyme now the minority among federal authorities and yet still ‘the rule’ for insurance reimbursements and treatment protocols? Is it because many of the CDC officials who are decisions-makers for Lyme disease policies are members of the Infectious Diseases Society of America (IDSA)? Is there is a connection to the fact that some IDSA members who wrote the 2006 Lyme treatments guidelines Lyme also support health and disability insurers against claims made by Lyme patients?
Are there wrongful financial motives related to IDSA/CDC pending patented vaccines driving this behavior?
Is it tied to the CDC performance metrics regarding global vector borne diseases? Borreliosis infections are pandemic and include Lyme and relapsing fever borreliosis. These metrics do not measure the reduction in vector infections or deaths, nor does it track improvements in treatments. It only measures how many CDC reagents (CDC patented products $$) are used on a global scale.
Whatever the reasons, the CDC’s Lyme policy stands in baffling contrast to the following 15 government authorities, including : the United States Department of Health and Human Services, Office on Women’s Health, Agency for Healthcare Research and Quality, National Guideline Clearinghouse, Office of Personnel Management, Executive Office of the President, US Department of Veterans Affairs Center for Innovation, US Department of Agriculture, US Department of Commerce, National Institute of Standards and Technology, US Department of Labor, Occupational Safety and Health Administration, US Department of State, US Department of Transportation and Federal Aviation Administration.
Most importantly, when will the CDC adopt the updated science that informs these other federal agencies? Details now follow:
(1) United States Department of Health and Human Services (HHS) YES, recognizes persistent and complicated Lyme disease – see Nos. 2 – 4
(2) HHS’s Office on Women’s Health YES, recognizes persistent and complicated Lyme disease
Nicole Greene serves as Deputy Director for the United States (US) Department of Health and Human Services’ Office on Women’s Health (OWH) and acts as the primary advisor to the Deputy Assistant Secretary for Health — Women’s Health. She oversees all administrative, financial and strategic planning as well as program and management operations, including the Office’s annual $33 million budget and related Congressional Justifications.
Ms. Greene also serves as an OWH spokesperson and raises awareness of Lyme disease and related illnesses by sharing her own experiences with Lyme.
[excerpted from her blog ] “On Easter Sunday 2007, I woke up unable to move from the neck down. My doctor tested me for all sorts of things: lupus, fibromyalgia, chronic fatigue syndrome, multiple sclerosis, sickle cell disease. But only one test came back positive: Lyme disease.
After my diagnosis, I thought through my entire medical history. I realized that I had actually had a lot of symptoms — I just didn’t know they were symptoms. I was sick all the time. None of my doctors ever put all of my symptoms together. But once I was diagnosed with Lyme disease, it all made much more sense.
I immediately went on antibiotics, which wiped me out so much that I couldn’t go into the office, or even the grocery store. I was lucky to be able to work from home, but many people don’t have that option. For almost a year, I missed a lot of things — my friends, family, birthday parties, celebrations, saying goodbye to loved ones who passed away. That first year was really hard.
Even after I started feeling better, my body wasn’t completely well… I’ve dealt with sciatica, a spinal lesion, neuropathy, temporary hair loss, cognitive issues, stress fractures in both knees … Lyme has affected my body, my work, and my relationships.
… I had no idea there even were Lyme specialists! Through him, I’ve learned about chronic Lyme disease, its co-infections, and new options for treatment… A lot of Lyme-literate doctors don’t take insurance, and all of the appointments, blood work, and treatments are out of pocket and very expensive. …my family and I have made sacrifices to ensure that I have the resources to make those choices… It’s been 15 years now, but I’m finally living with my Lyme disease.”
(3) HHS Agency for Healthcare Research and Quality (AHRQ) YES, recognizes persistent and complicated Lyme disease
AHRQ is the lead Federal agency charged with improving the quality, safety, efficiency, and effectiveness of health care for all Americans. AHRQ promotes evidence-based decision-making.
The AHRQ’s Effective Health Care Program facilitates collaboration among individual researchers, research centers, and academic organizations to assist the AHRQ to produce effectiveness and comparative effectiveness research for clinicians, consumers, and policymakers.
In 2011, AHRQ adopted the updated and internationally accepted Guideline criteria developed by the Institute of Medicine (IOM). On March 21, 2012, a series of questions were sent to the AHRQ’s Effective Health Care Program regarding treatment protocols for chronic Lyme.
The International Lyme and Associated Diseases Society (ILADS) then revised their Guidelines to meet these new evidence-based criteria. ILADS recognizes and treats chronic Lyme.
The Infectious Diseases Society of America (IDSA) recommends restricted treatments (two to four weeks) of antibiotics for Lyme infection and does not recognize chronic Lyme. The IDSA Lyme treatment guidelines have been delisted by the AHRQ because they are outdated and do not meet the international standards set by the IOM. The CDC solely promotes the 2006 IDSA Lyme treatment guidelines.
(4) National Guideline Clearinghouse (NGC) YES, recognizes persistent and complicated Lyme disease
[from the AHRQ website] The National Guideline Clearinghouse™ (NGC) is a publicly available database of evidence-based clinical practice guidelines and related documents. It provides Internet users with free online access to guidelines at http://www.guideline.gov. Updated weekly with new content, the NGC is produced by the AHRQ in partnership with the American Medical Association (AMA) and the American Association of Health Plans (AAHP) Foundation.
ILADS revised their guidelines September 2014 and the updated clinical practice guidelines are officially posted on NGC Evidence assessments and guideline recommendations in Lyme disease: the clinical management of known tick bites, erythema migrans rashes and persistent disease.
As of July 4th, 2017, the NGC is currently working on 65 guidelines that have met the NGC Inclusion Criteria. The IDSA has had since 2011 to update their 2006 guidelines for treating Lyme and have yet to meet the inclusion criteria.
(5) Office of Personnel Management (OPM) YES, recognizes persistent and complicated Lyme disease
The United States OPM is an independent agency of the United States government that manages the civil service of the federal government. Currently, the OPM has ‘enforcement responsibility’ for key health care laws – such as protection of access to evidence-based care for those with chronic illnesses.
From the OPM website, “National Healthcare Operations (NHO) is the OPM component responsible for implementing and overseeing the Multi-State Plan (MSP) Program, which was established under the Affordable Care Act (ACA). In this role, NHO reviews potential MSP issuer applications and certifies MSP options, which are then made available for sale on the Health Insurance Marketplace. MSP options are among the health insurance choices for individuals and small employers on HealthCare.gov. NHO is responsible for all functions related to the MSP Program: outreach and communications, engagement with State regulators, MSP issuer support and evaluation, policy analysis, contracting, and external review (appeals).”
In this manner, OPM reviewed insurers for acceptance in the ACA ‘healthcare marketplace’. As defined in the ACA, a Qualified Health Plan (QHP) is an insurance plan that is certified by the Health Insurance Marketplace, provides essential health benefits (EHBs), follows established limits on cost sharing, and meets other requirements outlined within the application process.
Every state that formed a Health Insurance Exchanges provided an example of an insurance company and plan that they wanted to have as the standard or “benchmark plan” that set the criteria for all other QHPs in the Health Insurance Marketplace.
By September 2012, an insurer known as ConnectiCare, was reviewed and sanctioned by OPM via QHP EHB and all other necessary criteria as a benchmark plan. ConnectiCare specifically recognizes ‘chronic Lyme’. Acceptance of the ConnectiCare insurer into the ‘healthcare marketplace’ by OPM/NHO also means that ‘chronic Lyme’ is acknowledged as a chronic disease, and as such, meets the specific protections under the ACA.
(6) Executive Office of the President (EOP) YES, recognizes persistent and complicated Lyme disease
The EOP was created in 1939 by President Franklin D. Roosevelt to provide the President with the support needed to govern effectively. The EOP has responsibility for tasks ranging from communicating the President’s message to the American people to promoting our trade interests abroad. Overseen by the White House Chief of Staff, the EOP has traditionally been home to many of the President’s closest advisors including: Council of Economic Advisers, Council on Environmental Quality, Office of Management and Budget, Office of National Drug Control Policy, Office of Science and Technology Policy , Executive Residence, National Security Council, Office of Administration, Office of the Vice President, etc..
The previous Obama administration acknowledged persistent and complicated Lyme. For example, Kristen T. Honey, PhD, PMP, former Policy Advisor to the White House Office of Science and Technology Policy and spokesperson for Lyme, including persistent and complicated Lyme cases and Mentor of the Lyme Innovation 2016 Hackathon.
(7) US Department of Veterans Affairs Center for Innovation (VACI) YES, recognizes persistent and complicated Lyme disease
The VACI identifies, tests, and evaluates new approaches to efficiently and effectively meet the current and future needs of Veterans through innovations rooted in data, design-thinking, and agile development.
VACI supported the Lyme Innovation 2016 Hackathon . The Lyme Innovation 2016 Hackathon gave awards to address chronic Lyme. For example, the Finalists and Recognition Awards on June 16, 2017 in Cambridge, MA. Finalists included: Utilize the University of Massachusetts Plant Cell Culture Library to screen for plant extracts that can eliminate Borrelia persister cells (chronic or persistent Lyme infection).
(8) US Department of Agriculture (USDA) YES, recognizes persistent and complicated Lyme disease
The USDA is the federal executive department responsible for developing and executing federal laws related to farming, agriculture, forestry, and food. The USDA webpage for Lyme infection details possible tests – beyond the CDC recommended Elisa and Western blot – that may validate a clinical diagnosis for Lyme infection. It also describes an illness that may have debilitating, serious and persistent symptoms that are difficult to treat. It does not say these symptoms should not be treated.
“Clinical disease in humans: Lyme disease is a multisystem illness involving the skin, nervous system, heart, and joints. Initially, symptoms resemble the onset of influenza, including severe headache, fatigue, joint and muscle pain, fever and possibly swollen lymph glands. … Later stage symptoms may occur weeks after a tick bite and are more severe, including neurological complications such as facial palsy, irritability … poor motor coordination … cardiac problems including irregular heart beat and varying degrees of heart blockage… Third stage Lyme disease … may involve chronic arthritis or chronic neurological effects … later stages are more difficult to treat.”
(9) US Department of Commerce YES, recognizes persistent and complicated Lyme disease – see No. 10
(10) National Institute of Standards & Technology (NIST) YES, recognizes persistent and complicated Lyme disease
The US Department of Commerce’s NIST have prioritized the need to improve diagnostic technology for Lyme disease and recognizes it may be a complex and chronic condition.
Taken from the February 11, 2016 article New Experimental Test Detects Signs of Lyme Disease Near Time of Infection … The collaborators—from the National Institute of Standards and Technology (NIST), Institute for Bioscience and Biotechnology Research, and Johns Hopkins School of Medicine—recently reported the successful first trial of their new method. “The complexity of Lyme disease, combined with lack of biomarkers to measure infection, has slowed progress,” study collaborator John Aucott, head of the Johns Hopkins Lyme Disease Clinical Research Center … The current standard blood test for Lyme disease exposes the infection only after antibodies have accumulated to detectable levels, which can take up to 4 to 6 weeks.
From the February 13, 2016 article Precision Medicine, Global Reach: Health Solutions From the Big Data Revolution. “This symposium examines the ways that big, open … data and technology are transforming society, science, and medicine and giving new hope for solutions to complex health conditions. As Albert Einstein said, “We cannot solve our problems with the same thinking we used when we created them.” … Yesterday’s science fiction concepts may become today’s solutions, shining light on complex, chronic conditions from cancer to Lyme disease.”
(11) US Department of Labor (USDOL) YES, recognizes persistent and complicated Lyme disease – see No.12
(12) USDOL’s Occupational Safety and Health Administration (OSHA) YES, recognizes persistent and complicated Lyme disease
[from webpage]” With the Occupational Safety and Health Act of 1970, Congress created the Occupational Safety and Health Administration (OSHA) to assure safe and healthful working conditions for working men and women by setting and enforcing standards and by providing training, outreach, education and assistance. The OSH Act covers most private sector employers and their workers, in addition to some public sector employers and workers in the 50 states and certain territories and jurisdictions under federal authority. Those jurisdictions include the District of Columbia, Puerto Rico, the Virgin Islands, American Samoa, Guam, Northern Mariana Islands, Wake Island, Johnston Island, and the Outer Continental Shelf Lands as defined in the Outer Continental Shelf Lands Act.”
The Directorate of Technical Support issues Hazard Information Bulletins (HIBs) in accordance with OSHA instruction CPL 2.65 to provide relevant information regarding unrecognized or misunderstood health hazards … HIBs are initiated based on information provided by the field staff, studies, reports and concerns expressed by safety and health professionals, employers and the public. Bulletins are developed based on thorough evaluation of available facts in coordination with appropriate parties.
The USDOL’s Occupational Safety and Health Administration has issued a Hazard Information Bulletin for Lyme disease that details circumstances surrounding the vaccine LYMErix. “Communications with the Vaccine Adverse Events Reporting System (VAERS) Hotline during September 1999 indicated that some reports of adverse events relating to LYMErix have been made… Lyme disease vaccine does not protect all recipients against infection with B. burgdorferi … Consequently, vaccinated persons, as well as the unvaccinated, should continue to practice good prevention and personal protective measures to prevent tick bites, and they should seek medical attention for early diagnosis and treatment of suspected tickborne infections. The duration of protection with LYMErix is not known … LYMErix is not recommended for certain groups of people [including ] Pregnant Women, Persons with Immunodeficiency and Persons with Musculoskeletal Disease [such as] persons with diseases associated with joint swelling (including rheumatoid arthritis) or diffuse musculoskeletal pain … Safety and efficacy are unknown for persons with chronic joint or neurological illness related to Lyme disease and for persons with second-or third-degree atrioventricular block.”
In a memorandum for Regional Administrator from Director Ruth McCully, of OSHA’s Directorate of Science, Technology and Medicine, “Workers should be advised of the signs and symptoms of Lyme disease, as well as the primary and secondary preventive measures for decreasing the risk of Lyme disease transmission, acute illness, and chronic health effects. If recognized early, Lyme disease can be easily treated with antibiotic medication. However, if the disease goes unrecognized and untreated, chronic conditions may ensue, including varying degrees of permanent damage to the joints or the nervous system … If recognized early, Lyme disease can be easily treated with antibiotic medication.
… In fact, the majority of infected persons do not recall being bitten by a tick … It is very important that the infection be diagnosed and treated with appropriate antimicrobial medication as early as possible because untreated Lyme disease may result in symptoms that are severe, chronic, and disabling. These disorders include chronic inflammatory arthritis, chronic muscle pain, heart disease, and/or neurological (brain and peripheral nerves) disorders. In addition, Lyme disease in a later stage is more difficult to diagnose, and treatment may be more prolonged and costly.”
(13) US Department of State YES, recognizes persistent and complicated Lyme disease
[from webpage] The primary goal of the Secretary of State and the U.S. Department of State is to shape a freer, more secure, and more prosperous world through formulating and implementing the President’s foreign policy, while supporting and protecting American interests abroad. The Department is responsible for promoting peace and stability in areas of vital interest to America
December 9, 2015 Fact Sheet from the Office of the Spokesperson, Washington, DC, “Climate change is a global threat that requires a global solution. Yet, many of the countries that have contributed little to global emissions are impacted the most … Climate change enhances the spread of pests that cause life threatening diseases like dengue, malaria, and Lyme disease.”
(14) US Department of Transportation (USDOT) YES, recognizes persistent and complicated Lyme disease -see No.15
(15) USDOT’s Federal Aviation Administration (FAA) YES, recognizes persistent and complicated Lyme disease
The FAA is responsible for regulating civil aviation to promote safety; encouraging and developing civil aeronautics, including new aviation technology; developing and operating a system of air traffic control and navigation for both civil and military aircraft; and researching and developing the National Airspace System and civil aeronautics.
The FAA takes Lyme disease very seriously. There is a 158 page Occupational Safety and Health Order that was prepared in an effort to prevent injuries, illnesses, and death from work related causes and to minimize losses of material resources and interruptions due to accidental occurrences. According to this guide, “Employees who have definitely been bitten by a tick at work must file a FAA Mishap Report (Form 3900-6) with their supervisor and the Safety Office.”
Furthermore, the guide notes that “while medical sources acknowledge that it takes several hours for a tick to infect you with Lyme disease, this process may be facilitated by squeezing the tick’s fluids into the bite. If bitten by a tick, do not wait for the symptoms of Lyme disease to appear; consult your doctor immediately, as early warning signs are not always present.”
There are bulletins that inform FAA staff about potential dangers of Lyme. For example, the Federal Air Surgeon’s Medical Bulletin Vol. 50, No. 3 2012-3 contains an article Etiology of Transverse Myelitis. According to Jonathan F. Stinson, MD, MPH, “This case report evaluates an airline pilot with [Transverse Myelitis] this disorder and the requirements necessary to return the airman to flying … Transverse myelitis is a relatively rare neurological disorder caused by inflammation of the spinal cord, creating a demyelinating lesion, typically involving both sides of the cord, hence its transverse or bilateral nature … The resulting inflammation damages or destroys myelin, compromising conduction between the brain and muscles or sensory organs distal to the lesion.
Symptoms of transverse myelitis can evolve over several hours to as long as several weeks. It often begins as a sudden onset of lower back pain, muscle weakness, or abnormal sensations in the toes and feet. However, it can rapidly progress to more severe symptoms, including paralysis, urinary retention, and loss of bowel control. Diagnosis is made by clinical history, physical findings, and a spinal cord lesion seen on MRI. Some patients may recover from transverse myelitis with minor or no residual problems, while others suffer permanent impairments that affect their ability to work or even carry out activities of daily living.
It is estimated that about 1,400 new cases of transverse myelitis are diagnosed each year in the United States, and approximately 33,000 Americans have some type of disability resulting from the disorder … There appear to be no inherited, ethnic, or gender differences in incidence. One study estimated the incidence to be about 4.6 cases per million per year … Transverse myelitis can have many different etiologies. It is thought that about 45% are parainfectious or related to infections. Infectious agents suspected of causing transverse myelitis include … Lyme disease.”
Cardiac complications from Lyme disease grounded this pilot for more than ten months. The Federal Air Surgeon’s Medical Bulletin Vol. 48, No. 2 Lyme Carditis and Atrial Fibrillation Case Report, by Joseph T. LaVan, MD discusses the aeromedical concerns and the issuance requirements to regain an active pilot licence for a pilot with Lyme-related cardiac complications.
“Of aeromedical significance, [Lyme] patients can develop cardiovascular compromise (either from conduction disturbances due to carditis or cardiac tamponade due to pericarditis), neurological deficits, and debilitating arthritis. This airman developed transient complete heart block and pericarditis with effusion, both of which resolved with treatment, so he is at low risk for recurrence of these cardiac problems. Pericarditis may recur in up to 20% of patients after an acute attack, which may lead to cardiac tamponade and significant hemodynamic instability … This airman remains in atrial fibrillation, requiring periodic re-evaluation for special issuance. This ongoing surveillance is likely to detect any complications of the Lyme carditis … The airman applied for renewal of his third-class airman medical certificate 10 months after the onset of acute pericarditis and atrial fibrillation and six months after the second failed cardioversion attempt.”
Jenna Luché-Thayer, Ad Hoc Committee for Health Equity in ICD11 Borreliosis Codes and Global RBCC
______________
**Comment**
I must add that although the Obama Administration might have acknowledged persistent Lyme (I never heard about it), it did absolutely nothing about it – nor any of these other agencies listed. Lyme/MSIDS is a huge problem – that transcends politics. It has been improperly handled from the get-go and the seemingly endless juggernaut has not let up one iota, no matter who is in the White House. I believe this is because our government is captured and is full of corruption at every single level. This is particularly true with public health, as has been so poignantly pointed out during the time of COVID. But, this is not new. This same corruption has been at play for decades but has only become more prominent for all whom are looking to see.
http://www.newsday.com/opinion/commentary/the-peril-of-chronic-lyme-disease-1.13775806 by Mary Beth Pfeiffer July 4, 2017
Nev Zubcevik is a rare doctor: She runs a clinic that treats late-stage Lyme disease. It has 100 patients waiting to get in and no openings until March of 2018.
“Between yesterday and today,” she told me recently, “I got six texts about children who are in need of immediate attention.”
The plight of Zubcevik’s clinic at Spaulding Hospital in Boston is played out around the nation and in other countries, where physicians who specialize in Lyme disease are overwhelmed. Why? Because infectious disease doctors will not care for a condition that is spurned by mainstream medicine: chronic Lyme disease. We cannot help you, patients are told. See someone else.
New York has the highest number of Lyme disease cases nationwide, and scientists forecast a record year for ticks in the Northeast. Of more than 300,000 Americans who contract Lyme disease every year, some 10 to 20 percent remain ill for months and sometimes years. The U.S. Centers for Disease Control and Prevention calls this a “post-treatment syndrome,” rather than a condition involving live pathogens, in part because there is no approved test to determine active infection.
Whatever is causing these patients’ pain — syndrome or infection — the shortage of care is destined to get much worse. That is courtesy of the CDC itself, which recently reported the unfortunate and unrepresentative outcomes of five patients who received intravenous antibiotic and immune-therapy treatment for Lyme disease. https://www.cdc.gov/mmwr/volumes/66/wr/mm6623a3.htm?s_cid=mm6623a3_e The agency warned doctors not to provide the only treatment that works for many patients, while offering them nothing better.
The CDC, relying on principles developed by the Infectious Diseases Society of America, maintains that short courses of antibiotics, generally two to four weeks, eradicate the disease. But at the same time, it ignores science from American universities that documents re-emergence and persistence of Lyme spirochetes after treatment with antibiotics — suggesting it can be chronic. Some research suggests that common front-line antibiotics ought to be abandoned for stronger ones.
The CDC reported the cases of five patients who had received long-term treatment and suffered infections from intravenous lines. They included a woman in her 30s who died from septic shock and an adolescent girl who suffered a serious infection, normally acquired in hospitals. Two patients developed spinal infections, and a third had abdominal cramping and diarrhea from a debilitating Clostridium difficile infection.
In all, there were five serious infections over three years, indicating real but small risk. A 2010 study of 200 Lyme patients on long-term IV antibiotics — on average 118 days — found just one confirmed infection and six suspected. The CDC provides scant evidence of risk of long-term IV antibiotic treatment on its website, citing six scientific articles in 21 years, including four that cover single cases.
When I asked the CDC about the new reports, which were solicited from doctors, it said in a statement it had “heard of additional cases” beyond the five but did not include them; that “anecdotal reports” were “unfortunately common”; and that “no systematic efforts” had heretofore been made to collect them. This effort was hardly systematic. The question that the CDC cannot answer is how common bad outcomes are, or more important, good ones, either. On that side, no one is looking.
Scientific evidence is mounting that the Lyme spirochete can survive short-course antibiotic treatment in animals and sometimes people. Some 20 scientific papers since 2012 have pointed in a similar direction.
CDC’s unwillingness to re-evaluate Lyme disease care leaves patients with few options in the United States and other countries that follow the American model of care.
It’s time to stop asking what Lyme doctors are doing wrong, and, just maybe, ask what they are doing right.
Mary Beth Pfeiffer, an investigative journalist, is writing a book on the global spread of tick-borne disease.
Rebuttals to the CDC MMWR article keeping mounting:
Stricker & Johnson: https://madisonarealymesupportgroup.com/2017/06/19/stricker-johnson-rebuttal-to-article-in-mmwr/
Lorraine Johnson Interview: https://madisonarealymesupportgroup.com/2017/06/26/lorraine-johnson-interview-on-cdc-mmwr-article/
Lyme Disease Association: https://madisonarealymesupportgroup.com/2017/06/16/who-controls-the-fake-lyme-disease-news/
Lee: https://madisonarealymesupportgroup.com/2017/06/19/lees-rebuttal-to-cdc-article-in-mmwr/
Dr. Shor: https://madisonarealymesupportgroup.com/2017/07/01/dr-shor-on-mmwr-article/
Dr. Maloney: https://madisonarealymesupportgroup.com/2017/07/01/dr-maloney-comments-on-mmwr-article/
Conner’s letter to the Washington Post on their lack of ethics by printing the CDC article word for word without even looking at the controversy: https://madisonarealymesupportgroup.com/2017/06/19/conners-letter-to-washington-post-on-ethics-and-integrity/ Conner states, “The Washington Post health editor Laura Helmuth has in the past disclosed during her post as health editor at Slate that she does not believe in persisting Lyme disease because an acquaintance of hers committed suicide while undergoing treatment, and she believes the treatment is what drove her friend to suicide.”
Helmuth obviously hasn’t read this: https://madisonarealymesupportgroup.com/2017/06/20/suicide-lyme-and-associated-diseases/
https://www.lymedisease.org/jesse-ruben-lyme-song/
Click on link to hear a beautiful & heartfelt song about suffering with Lyme/MSIDS from Jesse Ruben.
The reason I write about vaccines in relation to Lyme/MSIDS is that our bodies are in a war of epic proportions, often fighting against numerous bacteria, viruses, funguses, parasites, and stuff not even named yet. To say our immune systems were off would be an under statement. Even the CDC admits on its website that those in active infection should postpone any vaccinations until healthy. For another way of thinking about health, read: https://madisonarealymesupportgroup.com/2015/06/19/a-word-on-vaccines/
Thank you Dr. Lapenta for the following insightful article. ____________________________________________________________________________________________
http://dermagicexpress.blogspot.com/2017/07/stop-gardasil-and-cervarix-hpv-human.html by Dr. José Lapenta
HPV (Human Papilloma Virus) has spread throughout the world since it was discovered and continues its dissemination process in spite of social preventive campaigns and the INVESTIGATION OF VACCINES to avoid contagion.
That is the topic today, but first I will tell you that it was in year 1978 when the HPV 5 subtype associated with SKIN CANCER was discovered for the first time, later in 1981 and 1984 the association of HPV subtypes 16 and 18 was discovered To CERVICAL CANCER in women.
Despite these discoveries, HPV continued to spread throughout the world and that is when scientists INVENTED 3 VACCINES: CERVARIX AND GARDASIL 4 AND 9 to prevent infection … and here I will tell you objectively what happened with these VACCINES and subsequently, I will give my opinion as a medical dermatologist with more than 20 years in this world of research on DERMATOLOGICAL AND NON-DERMATOLOGICAL MEDICINES.
But first let’s talk a little about these VACCINES:
GARDASIL (QUADRIVALENT, HPV4), ALSO KNOWN AS SILGARD:
========================================================1.) WAS THE FIRST FDA APPROVED VACCINE TO PREVENT HPV IN JUNE 8, 2006, AGAINST 4 TYPES OF HPV.
2.) PROTECTS AGAINST TYPES: 16, 18, (ONCOGENIC), 6 AND 11 (LOW RISK).
3.) TO BE USED IN MEN AND WOMEN BETWEEN 9 AND 26 YEARS.
4.) COMPOSED BY L1 PROTEINS OF THE DESCRIBED HPV.
5.) ADJUVANTS: ALUMBER, POLYSORBATE 80, SODIUM BORATE, L HISTIDINE AND SODIUM CHLORIDE.
6.) ADMINISTRATION: INTRAMUSCULAR: 3 DOSES, TO 0, 2 AND 6 MONTHS.
7.) LABORATORY: MERCK SAHRP & DOHME (MSD)CERVARIC (BIVALENT HPV2):
=========================1.) APPROVED BY THE FDA IN OCTOBER 2.009, BECOMING THE SECOND APPROVED VACCINE TO PREVENT HPV.
2.) PROTECTS AGAINST TYPES OF HPV: 16 AND 18 (ONCOGENIC).
3.) TO BE USED IN WOMEN BETWEEN 9 AND 25 YEARS.
4.) NOT APPROVED FOR USE IN MEN.
5.) COMPOSED BY L1 PROTEINS OF THE DESCRIBED HPV.
6.) ADJUVANTS: SODIUM CHLORIDE (NACl), DIHYDROGEN SODIUM DIHYDRATE PHOSPHATE(NaH2PO4.2 H2O), DISTILLED WATER.
7.) ADMINISTRATION: INTRAMUSCULAR: 3 DOSES OF 0.5 ML, AT 0, 1 AND 6 MONTHS.
8.) LABORATORY: GLAXOSMITHKLINE (GSK)GARDASIL 9 (VALENTE):
=====================1.) APPROVED BY THE FDA ON DECEMBER 10, 2014 TO PREVENt AGAINST 9 TYPES OF HPV.
2.) PROTECTS AGAINST HPV TYPES: 16, 18, 31, 33, 45, 52, and 58 (ONCOGENICS), 6 AND 11 (LOW RISK).
3.) TO BE USED IN WOMEN BETWEEN 9 AND 26 YEARS AND MEN BETWEEN 9 AND 15 YEARS.
4.) PREVENTS 90% OF THE CANCER OF THE UTERINE NECK.
5.) EXCEED THE PREVIOUS VERSION GARDASIL 4, WHICH PROTECTS ONLY AGAINST 4 TYPES OF HPV.
6.) COMPONENTS: L1 PROTEINS OF THE HPV VIRUS BEFORE DESCRIBED.
7.) ADJUVANT: ASO4: AMORF ALUMINUM SULPHATE HYDROXYPHOSPHATE.
8.) ADMINISTRATION: INTRAMUSCULAR: 3 DOSES OF 0.5 ML, TO 0, 2-6, 6-12 MONTHS.
9.) LABORATORY: MERCK SHARP & DOHME. (MSD) and SANOFI PASTEURObviously there are more LABORATORIES INVOLVED, which commercialized the VACCINES. But the ORIGINAL authors were: GARDASIL: MERCK SHARP & DOHME (MS), AND CERVARIX: GLAXOSMITHLINE (GSK)
As you will be able to observe APARENTLY, they were WONDERFUL inventions, the population thought that, soon they would be free of the dreaded HPV, mainly the ONCOGENICS, and in addition you could have SEX WITHOUT PROTECTION and you would not be contagious by those HPV STRAINS described in these vaccines, BUT THE REALITY WAS ANOTHER. !!
SUMMARIZING:
=============PROTECTION OF VACCINES COVERS HPV TYPES: 16, 18, 31, 33, 45, 52, 58 (ONCOGENIC), AND 6 AND 11 LOW RISK (GENITAL WARTS), IN TOTAL 9 TYPES, as the original GARDASIL and The CERVARIX include types 16, 18 and 6, 11 INCLUDED in the GARDASIL 9.
Before proceeding, let us make the following reflection: HOW MANY TYPES OF HPV exist that infect the genital mucosa? Let’s take a look at the PRE-EDITION OF DERMAGIC EXPRESS: HPV, HUMAN PAPILLOMA VIRUS, BEFORE VACCINES
“… For today, 2017 there are approximately 120 types of HPV, of which 51 species affect the genital mucosa being the most carcinogenic types: 16, 18, 31, 33, 35, 39, 45, 51, 52, 56 , 58, 59, 68, 73 and 82. Of probable high risk : 26, 53, and 66, and of low carcinogenic risk: 6, 11, 40, 42, 43, 44, 54, 61, 70, 72, 81, and 108 …. “
CARCINOGENICS ARE 15 TYPES OF HPV, THOSE THAT ARE PROBABLE HIGH RISK 3, AND THOSE OF LOW RISK: 12,
============================================================================THE VACCINES DESCRIBED: PROTECT AGAINST:
1.) ONLY 7 TYPES OF HPV OF THE 15 DESCRIBED AS ONCOGENICS. LESS THAN 50%.
2.) DO NOT PROTECT FROM PROBABLE HPV HIGH RISK: 0%.
3.) PROTECT ONLY 2 TYPES OF LOW-RISK HPV FROM THE 12 DESCRIBED: 16%However the FDA approved these VACCINES and were sold AS “MAIZE GRAINS” being implemented in more than 120 countries. Big profits for the laboratories described above.
The majority of the studies said that they were SAFE and that they only great adverse effect it was PAIN IN THE SITE OF INJECTION and in rare occasions SINCOPE. Did you read well ?
But the reality was another, SEVERE ADVERSE EFFECTS AND EVEN DEATHS after the VACCINATION began. Becoming a TRAGEDY for parents and relatives of GIRLS and CHILDREN who died or developed SEVERE ADEVERSE EFFECTS. At the level of all the WORLD were presented these cases, being the most affected JAPAN, DENMARK, IRELAND, COLOMBIA, SWEDEN, NEW ZEALAND, SPAIN, INDIA, CANADA, and UNITED STATES. Did you read well? WORLDWIDE.
In European countries (SWEDEN) began to call the set of signs and symptoms produced post vaccination of GARDSIL, with the name POST GARDSASIL SYNDROME (PGS), in other countries began to call them THE “MURDER’S” VACCINES (CHILE) in other PARALYZING DISEASE ( NEW ZEALAND).
“… In SPAIN, the situation became hotter and Merck-Sanofi Pasteur received from the national and regional sanitary authorities (La Rioja) of Spain, charges or penalty for:
“… Fraudulent marketing and / or administration of an inadequately proven vaccine. Do not inform the public about the potential risks of the use of Gardasil … and others, being the most EMBLEMATIC case a GIRL called ZURIÑE of 18 years of age who suffered DEMINERALIZATION of its body putting her in a state of a person OF 60 YEARS…”
IN JAPAN: “… A total of 98 girls who developed health problems requested assistance from 2011 to 2014. Of the 90% vaccinated, 186 of the girls did not recover from these events ….
A Japanese EXPERT asked that the VACCINE BE REMOVED FROM THE MARKET because of its HARMFUL effects … and a DEMAND was raised for 140 million DOLLARS for the damages caused to the population by the vaccines against HPV “In COLOMBIA, many teenagers fainted within a few hours of VACCINATION. And there are girls who DO NOT RECOVER of the ADVERSE EFFECTS, being the first victim publicly known the girl MARIA PAULA MEJIA. MAY 6, 2014, AND CARMEN BOLIVAR.
IN IRELAND, 130 GIRLS became ill after the VACCINATION against HPV … which caused a scandal.
IN INDIA … THE FIRST GARDASIL VACCINE caused several DEATHS at the beginning of 2009 and the GOVERNMENT ordered the suspension of all HPV VACCINE TRIALS, which is still in effect today. In 2013 the Supreme Court admitted the petition and accused Merck and GlaxoSmithKline of “CHILD ABUSE” for creating marketing with these VACCINES.
IN CANADA, an article was published WHERE THE ADJUVANT ALUMINUM AND ANTIGENS OF HPV HAVE THE ABILITY TO RELEASE NEUROINFLAMATION AND AUTOIMMUNE REACTIONS, leading to future changes in behavior in susceptible people.
IN THE UNITED STATES, up to January 31, 2010, 49 unexplained deaths were reported after GARDASIL injections by CDC (Centers for Disease Control and Prevention) and VAERS (Vaccine Adverse Event Reporting System ).
For July of 2,015 the EMA (EUROPEAN AGENCY OF MEDICINS) reports 311 deaths BY GARDASIL and 41 by CERVARIX …
Even after ALL this data: THE VACCINES ARE STILL IN THE MARKET.
LIST OF ADVERSE EFFECTS ASSOCIATED WITH THESE VACCINES:
==========================================================================1.) SUDDEN DEATH , IN SOME CASES HOURS AFTER THE INJECTION.
2.) ASIA SYNDROME: AUTOINMUNE AND INFLAMMATORY SYNDROME INDUCED BY THE ADJUVANTS OF VACCINES FOR HPV. THE CHARACTERISTICS OF THIS SYNDROME ARE:
A-) PYREXIA (58%).
B-) MYALGIA (27%)
C-) ARTHRITIS OR ARTHRALGIA (19%)3.) OPTICAL NEURITIS. (Some consider this inconclusive).
4.) VENOUS THROMBOEMBOLISM (VTE)
5.) PAIN IN THE ARM (SITE OF THE INJECTION).
6.) CHRONIC FATIGUE SYNDROME. (CFS).
7.) POSTURAL ORTHOSTATIC TACHYCARDIA SYNDROME (POTS).
8.) CHRONIC REGIONAL PAIN SYNDROME (CRPS).
9.) DIZZINESS.
10.) PSYCHOSOMATIC REACTION.
11.) MUSCLE WEAKNES.
12.) BLEEDING FROM NOSE AND GUMS.
13.) PAIN IN THE KNESS AND ANKLE.
14.) VOMITING.
15.) DIARRHEA.
16.) BONE PAIN.
17.) MIGRAINES.
18.) NECK PAIN.
19.) TINGLING.
20.) ELECTRICAL “ZAPS” HIPS AND BACK.
21.) INSOMNIA.
22.) WRIST PAIN.
23.) FAINTING
24.) LOST CONSCIOUSNESS.
25.) CONVULSIONS
26.) PALE.
27.) HANDS AND FEETS FEEL COLD.
28.) FATIGUE.
29.) PALPITATIONS.
30.) SWEATING
31.) STIMULATION OF AUTO-IMMUNITY BY THE ALUMINUM CONTENT OF THE VACCINE, (GARDASIL) WHICH CAN TRIGGER: MUSCLE SPASM, PAIN, IRRITABILITY, ARRHYTMIAS, HEADACHES, BRITTLE BONES, INFLAMMATION, AUTO-INMMUNE REACTIONS AND MORE.I guess you’re waiting for MY OPINION on this … and I’ll give it to you STEP BY STEP:
================================================================1.) INVENTED VACCINES ONLY PROTECT AGAINST LESS THAN 50% OF THE ONCOGENIC TYPES OF HPV DESCRIBED. THEREFORE, THEY DO NOT HAVE SCIENTIFIC JUSTIFICATION FROM THE POINT OF VIEW OF THE PREVENTION.
2.) THE FACT THAT THE HPV TYPES 16, 18, 31, 33, 45, 52, AND 58, THE MOST COMMON AND ONCOGENIC, ARE INCLUDED IN THE VACCINES, DOES NOT RELEASE YOU OF THE CERVICAL CANCER, FOR THE PREVIOUSLY MENTIONED.
2.) THE INVENTION IS BADLY IMPLEMENTED, SINCE PROTEINS ARE USED FOR EVERY TYPE OF HPV, THE IDEAL HAVE BEEN A PROTEIN OR “ANTIGEN” COMMON TO ALL TYPES OF HPV.
3.) MIXING THESE ANTIGENS OF EACH TYPE OF HPV IN A SINGLE SOLUTION, SEEMS TO ME LIKE A BIOLOGICAL “BOMB”, WHICH HAS PROVOKED DEATH AND THOUSANDS OF AFFECTED EVERYWHERE ON THE PLANET, MANY OF THOSE THAT WERE NOT RECOVERED YET.
4.) USING ALUMINUM AS ADJUVANT IT WAS ANOTHER ERROR, AS IT IS KNOWN THAT THE SAME IS INVOLVED IN INFLAMMATORY AND AUTO-IMMUNE REACTIONS.
5.) THE SEVERE SIDE EFFECTS: CHRONIC FATIGUE SYNDROME. (CSF), ORTOSTATIC POSTURAL TACHYCARDIA SYNDROME. (POTS), CHRONIC SYNDROME OF REGIONAL PAIN … AND OF COURSE SUDDEN DEATH … BUT NOT DISCARD ANY OF THE DESCRIBED.
6.) THE VACCINATION CAMPAIGNS WERE BADLY DIRECTED: THE IDEA WAS TO TELL THAT THESE VACCINES ARE THE “SALVATION OF HUMANITY AGAINST HPV.”
7.) SERIOUSLY THOUGHT THAT THEY WERE NOT WELL “TESTED” BECAUSE IN MOST OF THE STUDIES THAT YOU FOUND IN THE DATABASES, ALMOST EVERYONE CONCLUDES THAT: THEY ARE SAFE, NOTHING BUT FALSE.
To conclude once again I want to say very responsibly that I HAVE NOTHING ABOUT THE SCIENTIFIC LABORATORIES, who invented these vaccines, for that they are, to create solutions for our diseases. But in this case of VACCINES AGAINST HPV, I also very responsibly say that:
WERE A BIG FAILURE AND WILL CONTINUE TO KILL AND DAMAGING THE HEALTH OF THE POPULATION THAT ACCESSES THESE VACCINES … so that:
“… IF YOU READ THIS ARTICLE, YOU ARE GIRL OR MAN AND YOU ARE IN THE AGE COMPREHENDED TO ACCESS THESE VACCINES … DO NOT DO IT … YOU CAN DIE IN THE ATTEMPT … OR BE SICK FOR LIFE …”
And I remember what I said in the PREVIOUS EDITION OF DERMAGIC EXPRESS on HPV BEFORE VACCINES: http://dermagicexpress.blogspot.com/2017/06/hpv-human-papilloma-virus-before.html “… By that time, BEFORE THE VACCINES against this disease, HPV DEATH was produced by CANCER, today, AFTER VACCINES for HPV, death is not only by CANCER … BUT ALSO THE VACCINES … “
____________________________________________________________________________________________
For more on Gardasil and HPV Vaccines:
https://madisonarealymesupportgroup.com/2016/04/24/gardasil-and-bartonella/
https://madisonarealymesupportgroup.com/2017/02/16/gardasil-vasculitis-msids/
https://madisonarealymesupportgroup.com/2017/04/14/gardasil-and-female-reproduction/


Written
on July 7, 2017