Archive for the ‘Activism’ Category

The Role of Retroviruses in Chronic Illness – A Clinician’s Perspective

https://klinghardtinstitute.com/wp-content/uploads/2018/05/IHCAN-Dr-K-article-HERV-05.1.pdf

The Role of Retroviruses in Chronic Illness- Dietrich Klinghardt, MD, PhD

The role of retroviruses in chronic illness is greatly disputed in academic circles. However, at the Sophia Health Institute Dr DIETRICH KLINGHARDT, MD, PhD, reports seeing significant improvement in treatment outcomes – in the most severely affected patients with chronic illness – when anti- retroviral strategies are included.

The results we are seeing at the Sophia Health Institute at our locations in Seattle and Marin County would not have been possible without the brilliant work of Judy Mikovits, PhD.

What is published and what illnesses are potentially caused by, or have as a contributing factor, activated retroviruses?

  • CNS-related illnesses: ME/CFS, Gulf War Syndrome, Autism, MS, Parkinson’s, ALS, Schizophrenia
  • Auto-immune diseases: Lupus, Crohn’s, Hashimoto’s Thyroiditis, Polymyositis, Sjogren’s syndrome, Bechet’s Disease, primary biliary cirrhosis
  • Cancer: prostate, breast, non-Hodgkin’s lymphoma, chronic lymphocytic leukaemia, mantle cell lymphoma, hairy cell leukaemia, bladder, colorectal, kidney, ovarian.

To that I am adding a list of other illnesses that have responded under my care to retroviral interventions: intractable Lyme disease, mold illness, insomnia, brain fog and all stages of a deteriorating brain, most childhood illnesses including ADHD and behavioural problems, asthma, breast cancer, lung cancer and many more.

Working backwards

What are retroviruses? The more familiar DNA viruses such as those from the “herpes family” – and many others – work their way from DNA over to RNA and from there to the manufacture of viral proteins. Retroviruses work their way backwards – from the RNA to the DNA – and then forward again from there.

Retroviruses are subdivided into different- lettered classes – Beta Retroviruses: HERV-K. Gamma Retroviruses: HERV-H and HERV-W.

The generally accepted key contributors to chronic illness are inflammation, oxidative stress and microbial infection. All of these are known triggers for retroviral activity, and in turn are also caused by retroviral activity.

Both human and animal retroviruses can infect the central nervous system (CNS). These are associated with many diseases of the CNS and cause neurological disease by several mechanisms:

1. Directly through infection of immune cells which traffic to the brain;

2. Indirectly through increases in proinflammatory cytokines and chemokines, or

3. In the absence of detectable brain inflammation indirect effects known as “bystander effects”- causing chronic retroviral replication of immune cells.

A retrovirus works via the enzyme “reverse transcriptase”. Once inside the cell, it uses the enzyme to force the cell to create viral DNA. This viral DNA becomes integrated into the host cell DNA. A retrovirus integrated into our genome may be passed from mother to child during pregnancy (Sakuma et al, 2012).

Only 2% of our DNA is protein-coding, but 6-8% of our DNA is retroviral DNA – passed down to us from our ancestors as scars from our constant encounter with an often hostile microbial and virus-rich environment (Stoyle, 2006, Mayer et al, 2011; Li et al, 2001). These viruses are referred to as Human Endogenous Retroviruses or HERVs.

However, not all embedded retroviral DNA is bad. Some sections have become a functional part of our genome because they have given us an evolutionary advantage, such as the formation of the p53 gene regulatory network (Shin et al, 2013; Barbusecu et al, 2001). Other retroviruses have to be silenced throughout life, mainly through DNA methylation and acetylation.

The transcription of retroviral DNA makes the infected person susceptible to numerous de-novo genetic mutations, including MTHFR, DNMT and other genes which control methylation. Many other illness-producing effects are known, implicating HERV-K in the pathogenesis of neuroinflammatory and autoimmune illnesses. For a patient to get well today, it is rarely enough to just interpret the genomic testing and to substitute accordingly.

Acquiring infection

How do we become infected? Retroviruses can be acquired (inhalation, blood-based products, physical contact) or the viruses already present in our DNA can be activated through influences such as a viral infection or chronic inflammation (Manghera and Douville, 2013).

For example, the Epstein Barr virus induces expression of the HERV-K envelope gene and the transactivation of MSRV, the Multiple Sclerosis retrovirus (Mameli et al, 2007; Sutkowski et al, 2001). Herpes simplex type-2 activates members of the HERV-W family. These and other mechanisms are likely responsible for the activation of HERVs seen in rheumatoid arthritis, SLE, Sjorgens disease, schizophrenia, autism, MS and cancer. Cell phone radiation has disabled many of our protective proteins (Fragopoulou et al, 2012) and so have many of the food-based toxins such as glyphosate (Seneff et al, 2017) and air-based inhalants (aluminium etc).  An unintended source of retroviruses are some vaccines as reported in Frontiers in Microbiology in January 2011).

Diagnosis

Currently PCR testing is only available to
the research community. We have to rely on indirect parameters:

  • decrease of CD56 NK cells (CD56 is involved in adhesion, migration, growth, differentiation and other cellular functions); down regulation of IL-13, IL-2, IFN gamma, TH-1 cytokines (J. Mikovits et al, 1998)
  • upregulated levels of TH-2 cytokines: IL-4, IL-10 and pro-inflammatory cytokines: IL-1, IL-6, IL-8 and TNF-alpha.
  • elevated levels of TGF beta-1: has profound effects on innate and adaptive immunity through stimulation of mast cells (often mistaken as mould-related). This may be the true cause of mastocytosis.

Other practical markers from my experience: low wbc (white blood count below 4500), low CD 56. I always include the CD 57 to rule out an active Borrelia burgdorferi infection as compounding factor.

Treatment

When the retroviruses are effectively addressed early in the treatment of chronic illness, other issues such as bacterial infections (Borrelia, Mycoplasma, Bartonella etc), mould illness, EBV, CMV, HHV-6, silent inflammation, parasites, heavy metal toxicity and many other problems become less symptomatic and often undetectable – and respond much better to treatment, even to interventions that have failed before.

Plants have been exposed to the same retroviruses as us, but for 300 million years longer – and many have developed potent adaptogens. Even though drugs like Truvada and AZT can be successfully used, I prefer the use of plant-based products that have unique anti-retroviral properties. A few examples with the key references:

  • Scutalaria root (Ruscetti et al: “Inhibition of HIV infection by baicalin – a flavonoid compound purified from Chinese herbal medicine”, Cellular & Molecular Biology Research 39, 2 (1993): 119-124).
  • Cistus incanus (Rebensburg et al: “Potent in vitro antiviral activity of Cistus incanus extract against HIV and Filoviruses targets viral envelope proteins”. Scientific Reports 6 (2016): 20394).
  • Broccoli sprouts (Furuya et al: “Sulforaphane inhibits HIV infection of macrophages through Nrf2.” PLoS Pathogens, 12.4 (2016): e1005581)
  • St John’s Wort (Meruelo, Lavie and Lavie: “Therapeutic agents with dramatic anti- retroviral activity and little toxicity at effective doses: aromatic polycyclic diones hypericin and pseudohypericin.” Proc Nal Acad Sci 85.14 (1988): 5230-5234).

In addition, I like to put my patients on a high dose of seleno-cysteine (commonly 800mcg, a dose that has been established as safe (Yang, G.; Zhou, R. (1994) “Further Observations on the Human Maximum Safe Dietary Selenium Intake in a Seleniferous Area of China”. Journal of Trace Elements and Electrolytes in Health and Disease. 8 (3–4): 159–165. Baum et al. “High risk of HIV- related mortality is associated with selenium deficiency.” JAIDS 15.5 (1997): 370-374).

Suramin, an old anti-parasitic, has turned out to be one of the most effective anti- retroviral agents. Retroviruses activate the “cell danger response” and the P2 purinergic receptor on each cell. Suramin downregulates this receptor and inhibits the binding of growth factors TGF-beta, EGF, PDGF to their receptors and thus antagonises the ability of these factors to stimulate growth of tumour cells. It can be given iv every six weeks.

I prefer giving daily homeopathic doses (Mitsuya et al: “Suramin protection of T cells in vitro against infectivity and cytopathic effect of HTLV-III.” Science 226.4671 (1984): 172-174).

When we use suitable liposomal extracts of plants in proper dose and frequency, together with selenium and “energetic copies” of immune modulators like suramin, olmetarsan (vitamin D receptor), rapamycin (mTOR), significant results can be achieved in the treatment of chronic illness that were not possible before. This new therapeutic approach should always be combined with the synergistic use of EMR protection, treatment of Lyme and co-infections, mould and metal detox.

• On June 10, Dr Klinghardt will present a one-day seminar on the correct and effective use of anti-retroviral interventions in chronic illness. For more information and to book see news story on page 9 and visit www. Klinghardtinstitute.com.

About the author

Dr DIETRICH KLINGHARDT studied medicine and psychology in Freiburg, Germany, completing his PhD on the involvement of the autonomic nervous system in autoimmune disorders. Early in his career he became interested in the sequelae of chronic toxicity (especially lead, mercury, environmental pollutants & electromagnetic fields) in the course of illness.

While working in India he encountered Eastern concepts of disease aetiology and blended them with his Western training. This laid the foundation for his 5-level system of Integrative Medicine. In the US he spent three years as a full-time emergency physician before becoming Medical Director of the Santa Fe Pain Centre.

Increasingly aware of the limitations of conventional medicine when dealing with chronic conditions, he trained in Ericksonian hypnotherapy and began to include body-oriented psychotherapeutic and counselling approaches in his work, along with neural therapy, mesotherapy injection techniques and applied psychoneurobiology. Dr Klinghardt has contributed significantly to the understanding of metal toxicity and its connection with chronic infections, illness and pain. He has been instrumental in advancing various fields within biological medicine – non-invasive pain management, injection techniques for pain and orthopaedic dysfunction, anti-ageing medicine, toxicology, paediatrics (neuro-developmental disorders), energy psychology, biological dentistry and others. He has also developed Autonomic Response Testing, a comprehensive diagnostic system that has helped many practitioners to become accomplished holistic physicians. He founded Sophia Health Institute in 2012, and is actively involved in patient care at his clinic.

______________

**Comment**

For more on Mikovitz’s work:  https://madisonarealymesupportgroup.com/2017/10/15/vaccines-and-retroviruses-a-whistleblower-reveals-what-the-government-is-hiding/

https://madisonarealymesupportgroup.com/2018/03/01/vaccines-could-contribute-to-disease-epidemics-due-to-retrovirus-contamination/

To hear the audio of the talk & slides, go here:  http://simplymimi.net/archives/1151


A New Weapon in the Fight Against Superbugs – TED Talk with David Brenner

https://embed.ted.com/talks/lang/en/david_brenner_a_new_weapon_in_the_fight_against_superbugs”

Since the widespread use of antibiotics began in the 1940s, we’ve tried to develop new drugs faster than bacteria can evolve — but this strategy isn’t working. Drug-resistant bacteria known as superbugs killed nearly 700,000 people last year, and by 2050 that number could be 10 million — more than cancer kills each year. Can physics help? In a talk from the frontiers of science, radiation scientist David Brenner shares his work studying a potentially life-saving weapon: a wavelength of ultraviolet light known as far-UVC, which can kill superbugs safely, without penetrating our skin. Followed by a Q&A with TED Curator Chris Anderson.

This talk was presented at an official TED conference, and was featured by our editors on the home page.

https://www.ted.com/speakers/david_brenner?language=en


The Corruption of Evidence Based Medicine – Killing For Profit

http://www.greenmedinfo.com/blog/corruption-evidence-based-medicine-killing-profit

The Corruption of Evidence Based Medicine — Killing for Profit

Tuesday, June 19th 2018
Written By: Dr. Jason Fung
This article is copyrighted by GreenMedInfo LLC, 2018

The idea of Evidence Based Medicine (EBM) is great. The reality, though, not so much. Human perception is often flawed, so the premise of EBM is to formally study medical treatments and there have certainly been some successes.

Consider the procedure of angioplasty. Doctors insert a catheter into the blood vessels of the heart and use a balloon like device to open up the artery and restore blood flow. In acute heart attacks studies confirm that this is an effective procedure. In chronic heart disease the COURAGE study and more recently the ORBITA study showed that angioplasty is largely useless. EBM helped distinguish the best use of an invasive procedure.

So, why do prominent physicians call EBM mostly useless? The 2 most prestigious journals of medicine in the world are The Lancet and The New England Journal of Medicine. Richard Horton, editor in chief of The Lancet said this in 2015 https://www.thelancet.com/journals/lancet/article/PIIS0140-6736%2815%2960696-1/fulltext

The case against science is straightforward: much of the scientific literature, perhaps half, may simply be untrue

Dr. Marcia Angell, former editor in chief of NEJM wrote in 2009 that http://www.nybooks.com/articles/2009/01/15/drug-companies-doctorsa-story-of-corruption/

It is simply no longer possible to believe much of the clinical research that is published, or to rely on the judgment of trusted physicians or authoritative medical guidelines. I take no pleasure in this conclusion, which I reached slowly and reluctantly over my two decades as an editor

This has huge implications. Evidence based medicine is completely worthless if the evidence base is false or corrupted. It’s like building a wooden house knowing the wood is termite infested. What caused this sorry state of affairs? Well, Dr. Relman another former editor in chief of the NEJM said this in 2002  https://www.ncbi.nlm.nih.gov/pubmed/12561803

The medical profession is being bought by the pharmaceutical industry, not only in terms of the practice of medicine, but also in terms of teaching and research. The academic institutions of this country are allowing themselves to be the paid agents of the pharmaceutical industry. I think it’s disgraceful

The people in charge of the system — the editors of the most important medical journals in the world, gradually learn over a few decades that their life’s work is being slowly and steadily corrupted. Physicians and universities have allowed themselves to be bribed.

The examples in medicine are everywhere. Research is almost always paid for by pharmaceutical companies. But studies done by industry are well known to have positive results far more frequently https://www.ncbi.nlm.nih.gov/pubmed/20679560.  Trials run by industry are 70% more likely than government funded trials to show a positive result. Think about that for a second. If EBM says that 2+2 = 5 is correct 70% of the time, would you trust this sort of ‘science’?

Selective Publication — Negative trials (those that show no benefit for the drugs) are likely to be suppressed. For example, in the case of antidepressants, 36/37 https://www.nejm.org/doi/full/10.1056/NEJMsa065779 studies that were favourable to drugs were published. But of the studies not favorable to drugs, a paltry 3/36 were published. Selective publication of positive (for the drug company) results means that a review of the literature would suggest that 94% of studies favor drugs where in truth, only 51% were actually positive. Suppose you know that your stockbroker publishes all his winning trades, but suppresses all his losing trades. Would you trust him with your money? But yet, we trust EBM with our lives, even though the same thing is happening.

KillingForProfitGraph

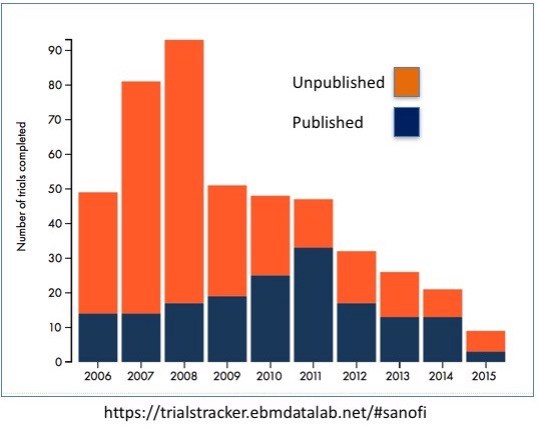
Let’s look at the following graph of the number of trials completed versus those that were published. In 2008, the company Sanofi completed 92 studies but only a piddly 14 were published. Who gets to decide which gets published and which does not? Right. Sanofi. Which ones do you think will be published? The ones that favor its drugs, or the ones that prove their drugs do not work? Right. Keep in mind that this is the only rational course of action for Sanofi, or any other company to pursue. It’s idiotic to publish data that harms yourself. It’s financial suicide. So this sort of rational behavior will happen now, and it will not stop in the future. But knowing this, why do we still believe the evidence based medicine, when the evidence base is completely biased? An outside observer, only looking at all published data, will conclude that the drugs are far, far more effective than they are in reality. Yet, if you point this out in academic circles, people label you a quack, who does not ‘believe the evidence’.

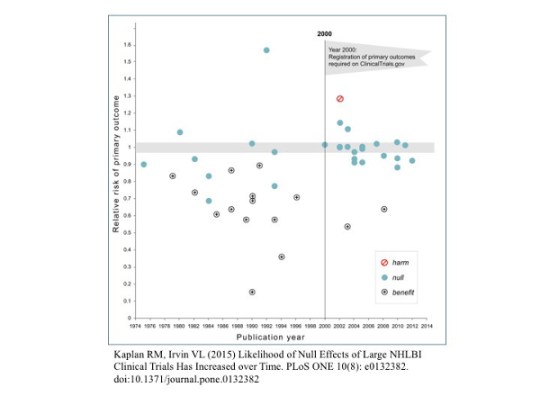
KillingForProfitGraph2Rigging of Outcomes — Or consider the example of registration of primary outcomes. Prior to year 2000, companies doing trials did not need to declare what end points they measured. So they measure many different endpoints and simply figured out which one looked best and then declared the trial a success. Kind of like tossing a coin, looking at which one come up more, and saying that they were backing the winning side. If you measured enough outcomes, something was bound to come up positive.

In 2000, the government moved to stop these shenanigans. They required companies to register what they were measuring ahead of time. Prior to 2000, 57% of trials showed a positive result. After 2000, a paltry 8% showed good results. More evidence of the evidence base being completely corrupted by commercial interest, and the academic physicians who were getting rich on it tacitly allowing corruption because they know that you don’t bite the hand that feeds you

KillingForProfitExcerpt

‘Advertorials’ — Or this example of a review paper in the NEJM https://www.nejm.org/doi/pdf/10.1056/NEJMoa1001086 that fracture rates caused by the lucrative bisphosphonate drugs were “very rare”. Not only did the drug companies pay lots of consulting fees to the doctors, three of the authors of this review were full time employees! To allow an advertorial to be published as the best scientific fact is scandalous. Doctors, trusting the NEJM to publish quality, unbiased advice have no idea that this review article is pure advertising. Yet, we still consider the NEJM to be the very pinnacle of evidence based medicine. Instead, as all the editors of the journals sadly recognize, it has become lucre-based publishing. Mo money = better results.

Money from Reprints — The reasons for this problem is obvious to all  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2964337/ — it’s insanely profitable for journals to take money from Big Pharma. Journals want to be read. So they all try to get a high Impact Factor (IF). To do this, you need to get cited by other authors. And nothing boosts ratings like a blockbuster produced by Big Pharma. They have the contacts and the sales force to make any study a landmark. A less obvious benefit is the fees that are generated by Big Pharma purchasing articles for reprint. If a company publishes an article in the NEJM, they may order several hundred thousand copies of the article to be distributed to unsuspecting doctors everywhere. These fees are not trivial. The NEJM publisher Massachusetts Medical Society gets 23% of its income from reprints. The Lancet — 41%. The American Medical Association — a gut busting 53%. No wonder these journals are ready to sell their readers (ordinary physicians) down the river. It pays. Who needs journalistic ethics when there’s a Mercedes in the driveway? Mo money, baby. Mo money.

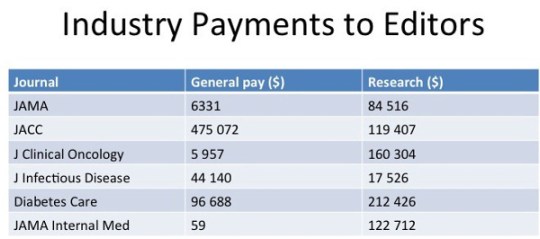
Bribery of Journal Editors — A recent study by Liu et al in the BMJ https://www.bmj.com/content/359/bmj.j4619 shed more light on the problem of crooked journals. Crooked journal editors. Editors play a crucial role in determining the scientific dialogue by deciding which manuscripts are published. They determine who the peer reviewers are. Using the Open Payments database, they looked at how much money the editors of the most influential journals in the world were taking from industry sources. This includes ‘research’ payments, which are largely unregulated. As mention previously, much ‘research’ consists of going to meetings in exotic locale. It funny how many conferences are held in beautiful European cities like Barcelona, and how few are done in brutally cold Quebec City.

Of all journal editors that could be assessed, 50.6% were on the take. The average payment in 2014 was $27,564. Each. This does not include an average $37, 330 given for ‘research’ payments. Other particularly corrupt journals include:

KillingForProfitPayToEditors

This is slightly horrifying. Each editor of the Journal of the American College of Cardiology received, on average $475 072 personally and another $119 407 for ‘research’. With 35 editors, that’s about $15 million in bribes to doctors. No wonder the JACC loves drugs and devices. It pays the private school bills. Mo money = we’ll publish your crooked studies for you. Mo money, baby, mo money.

Publication Bias — The evidence base that EBM depends upon is completely biased. Some people think I’m really anti-Pharma, but this is not really true. Big Pharma companies have a duty to their shareholders to make money. They have no duty to patients. On the other hand, doctors have a duty to patients. Universities have a duty to remain unbiased.

It is the failure of doctors and universities to keep their greedy paws out of the corrupting influence of Big Pharma money that is the problem. If Big Pharma is allowed to spend lots of $$$ paying off doctors and universities and professors, then it should do so to maximize profits. That is their mission statement. Doctors love to blame Big Pharma companies because it takes peoples gaze off the real problem — lots of doctors taking $$$ from anybody who will pay. The pharma industry is not the problem. Bribery of university doctors is the problem — one that is easily fixed if the political will exists.

Consider this study:  https://onlinelibrary.wiley.com/doi/pdf/10.1111/ene.13336  Looking at studies in the field of neurodegenerative disease, researchers looked at all the studies that were started but never finished or never published. Approximately 28% of studies never made it to the finish line. That’s a problem. If all the studies that don’t look promising for drug candidates are not published, then it appears that the drugs are way way more effective than they really are. But the published ‘evidence base’ would falsely support the drug. Indeed, Pharma sponsored trials were 5 times more likely to be unpublished.

Imagine you have a coin flipping contest. Suppose a player call ‘Big Pharma” chooses heads, and also pays the coin flipper. Every time the coin flipper pulls up tails, the results don’t count. Every time it comes up heads, it counts. This happens 28% of the time. Now, instead of a 50/50 split of heads and tails, it’s more like a 66/34 split of heads/tails. So the ‘evidence based medicine’ lover claims that heads is far more likely to come up than tails, and castigates people who don’t believe the results as ‘anti-science’.

Evidence based medicine depends entirely upon having a reliable base of evidence (studies). If the evidence base is tampered with, and paid for, then EBM as a science is completely useless. Indeed, the very editors whose entire careers have been EBM have now discovered it to be worthless. Does the CEO of Phillip Morris (maker of Marlboro cigarettes http://www.greenmedinfo.com/disease/tobacco-toxicity) smoke? That tells you all you need to know about the health risks. Do the editors of the NEJM and the Lancet believe EBM anymore? Not at all. So neither should we. We can’t believe evidence based medicine until the evidence has been cleaned up from the corrupting influence of commercial interests.

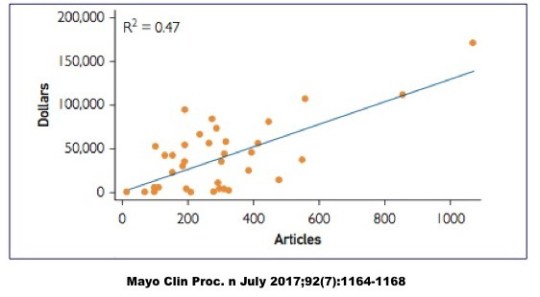
Financial conflicts of interest (COI), also known as gifts to doctors, is a well accepted practice. A national survey in the New England Journal of Medicine in 2007 https://www.nejm.org/doi/pdf/10.1056/NEJMsa064508 shows that 94% of physicians had ties to the pharmaceutical industry. This gravy train only rides in one direction. From Big Pharma to the wallets of doctors. Sure Big Pharma can simply pay doctors directly, and it does plenty of that. It’s no surprise that medical students with more exposure to pharmaceutical reps develop a more positive attitude towards them https://www.ncbi.nlm.nih.gov/pubmed/20672554. Many medical schools have limited exposure of medical students in response, but declined to get off the gravy train themselves. There is a simple relationship between how prominent a physician is (more articles published — almost always academic doctors and professors) and how much money they take from Big Pharma. Mo prominent = mo money. Further, there is a ‘clear and strong link’ between taking industry money and minimizing the risk of side effects of medications https://www.ncbi.nlm.nih.gov/pubmed/20299696.  What, you thought people teach at prestigious institutions like universities for the good of mankind? Maybe that’s why they went there, but that’s not why they stay. They came for the science. They stayed for the money.

KillingForProfitGraph3

So here’s a damning list of all the problems of EBM

  1. Selective Publication
  2. Rigged outcomes
  3. Advertorials
  4. Reprint Revenues
  5. Bribery of Journal Editors
  6. Publication Bias
  7. Financial Conflicts of Interests

When the evidence base of medicine is bought and paid for, people die. That is how doctors have created this opioid crisis that kills thousands of people. Pharmaceutical companies want to pay off doctors, just as drug lord want to pay off judges and police officers. Doctors, being human, should put safeguards against this temptation. Unfortunately, doctors and universities have been willing participants in this game of killing for profit https://www.facebook.com/NathanGillOfficial/videos/2134121280141545/.   We need to end it now. End the corruption of the universities. Stop the bribery of doctors.

Dr. Aseem Malhotra will be speaking about this very issue to the European Parliament this Thursday:  https://www.dietdoctor.com/live-stream-big-food-big-pharma-killing-profit

Nephrologist. Special interest in type 2 diabetes reversal and intermittent fasting. Founder of Intensive Dietary Management Program.

Disclaimer: This article is not intended to provide medical advice, diagnosis or treatment. Views expressed here do not necessarily reflect those of GreenMedInfo or its staff.

“© [Article Date] GreenMedInfo LLC. This work is reproduced and distributed with the permission of GreenMedInfo LLC. Want to learn more from GreenMedInfo? Sign up for the newsletter here http://www.greenmedinfo.com/greenmed/newsletter.”

______________

**Comment**

I am so thankful people are speaking out about what’s happening to Science.  This is being seen across the board, but particularly with tick borne illness.  This complex illness has been riddled with fraud, collusion, and conflicts of interest from the get-go and hasn’t changed in over 40 years.

For more:  https://madisonarealymesupportgroup.com/2017/01/13/lyme-science-owned-by-good-ol-boys/

https://madisonarealymesupportgroup.com/2018/06/14/corruption-human-rights-violations-against-lyme-doctors-scientists-and-parents-now-on-united-nations-record/

https://madisonarealymesupportgroup.com/2017/08/19/dr-liegner-guidelines-used-by-managed-care-causing-lyme-deaths/

https://madisonarealymesupportgroup.com/2017/01/02/fake-science/

https://madisonarealymesupportgroup.com/2017/09/25/trump-should-eliminate-fake-science/

https://madisonarealymesupportgroup.com/2017/01/28/sit-down-science/

https://madisonarealymesupportgroup.com/2017/12/05/bought-documentary-on-pharma-vaccines-gmos/


NY Senate Approves $1 Million to Combat Lyme

https://www.nysenate.gov/newsroom/press-releases/senate-approves-1-million-investment-combat-lyme-across-new-york-state

Senate Approves $1 Million Investment to Combat Lyme Across New York State

June 19, 2018 ISSUE: LYME AND TICK-BORNE DISEASES

Historic Levels of Funding Build Upon the Senate’s Commitment to Increasing Public Awareness, Treatment, and Prevention of Lyme and Other Tick-Borne Illnesses
The New York State Senate today approved a resolution to provide a record $1 million to help fight the scourge of Lyme and other tick-borne diseases (TBDs) throughout the state. The new funding will help support a wide variety of local investments identified by the Senate’s Task Force on Lyme and Tick-Borne Diseases to increase education, research, prevention, and treatment options, and combat the ongoing increase in TBDs throughout New York.

The Senate Majority – and specifically the Task Force – led the charge in securing this historic level of funding in the 2018-19 state budget. Based on the Task Force’s recommendations, the final budget restores $400,000 in Executive Budget cuts and includes $600,000 in new funding for a total of $1 million.

Senator Sue Serino, Chair of the Task Force on Lyme and Tick-Borne Diseases, said,

“With the State Senate successfully securing an unprecedented $1 million in this year’s budget to bolster awareness, prevention and research initiatives, we are sending a strong message to New Yorkers who have spent years grappling with the devastating impacts of Lyme and tick-borne diseases. This critical funding will play a direct role in helping us to combat the spread of Lyme and TBDs in the state, and with the Hudson Valley sitting at the epicenter of this epidemic, I am especially proud to have secured funding that will go directly to our local community. I thank Senator Kemp Hannon, Chair of the Senate’s Health Committee, who has partnered with me to continue building momentum on this important issue. Working together with partners at all levels, we can ensure that New York has an effective statewide action plan in place to empower patients and better protect residents against the scourge of Lyme and TBDs.”

Senator Kenneth P. LaValle (R-C-I, Port Jefferson) said,

“I am pleased that the Senate was able to secure $1 million for Lyme and Tick Borne Disease (TBD) funding. My colleagues and I fought hard to secure this funding, recognizing the importance of fighting the spread of Lyme and TBD’s throughout the state. My district is particularly hard hit, especially on the East End of Long Island. This money will allow for the continuation of the highly successful Tick Borne Disease Center at Southampton Hospital, a four poster program on Shelter Island directly targeting the spread of ticks from the deer population, and the creation of a new state-of-the-art infectious disease lab at Stony Brook University.”

Senator Betty Little (R-C-I, Queensbury) said,

“I represent a beautiful region of New York State and we want people outdoors, enjoying nature. But the fear of contracting Lyme Disease is increasingly a deterrent and that’s a shame. My experience is that the statistics of reported cases fall short of what is actually happening. A mere mention of Lyme disease among a group of people and you immediately hear horror stories of misdiagnosis and costly long-term treatments. The good news is we are making progress and the Senate task force is playing a major role. We’ve secured funding and spearheaded legislation. We have taken our direction from the public we serve, from those leading the effort to improve diagnosis and treatment and from the incredible insight of patients themselves. This additional funding will make an impact in the North Country and I am very grateful to have helped secure it as part of this year’s budget.”

Highlights of the resolution passed today include:
  • Cary Institute of Ecosystem Studies, Inc. – $192,000 to research community-based prevention methods by continuing and expanding “The Tick Project,” a five-year research project. The funding will help determine whether neighborhood-based prevention can reduce human cases of Lyme and other TBDs.
  • Stony Brook University – $175,000 to open a state-of-the art infectious disease laboratory, which will have an insectary dedicated solely for work on ticks. The laboratory will be open to Stony Brook scientists and others as a regional facility with unique research capabilities. The funds will be used to support activities in the laboratory and new research on TBDs.
  • Cornell University – $130,000 to study the distribution of ticks and the diseases they carry in various parts of the state through the Tick Outreach and Surveillance Project for New York. Run through the New York State Integrated Pest Management (IPM) Program at Cornell University, the research will primarily focus on the spread of ticks by species within certain counties. Other areas of study include ways to reduce human exposure to TBDs, tick management workshops, and best practices in schools, camps, parks, and places where people gather outdoors.
  • New York State Association of County Health Officials (NYSACHO) – $112,000 to increase public awareness throughout New York through eight to 10 regional educational lectures. The informational seminars will focus on community awareness, best practices for TBD investigation, tick surveillance, and disease prevention to local parts of the state heavily impacted by the effects of Lyme and TBDs.
  • SUNY Adirondack – $100,000 for laboratory research on lesser-known TBDs, including infectious diseases known to be comorbid with Lyme disease, such as Babesia, Bartonella, Ehrlichia, Anaplasma, and Powassen virus. The work would help provide much needed information about the rates of these coinfections in people with Lyme disease in New York.
  • Southampton Hospital – $75,000 to fund the Tick-Borne Disease Resource Center, which helps doctors in multiple disciplines collaborate with researchers and community outreach experts to inform and treat individuals from across the region.
  • New York State Department of Health – $60,000 to increase the number of tick collection sites in New York, and the number of ticks tested for pathogens statewide. The funding will also be used to hire temporary staff to assist with sampling and testing, as well as targeting of educational messages in a more efficient manner.
  • SUNY College of Environmental Science and Forestry – $50,000 to monitor seasonal variations of ticks in Western and Central New York to help provide a better understanding of how disease transmission risks are changing. The study will also provide public information to better explain the risks of tick exposure.
  • Paul Smith’s College – $30,000 to study the emergence of TBDs in the North Country by continuing and expanding academic studies that monitor ticks and TBDs.
  • Cornell Cooperative Extension – $26,000 for a series of regional Lyme and TBD forums to be hosted throughout the state. The forums will help provide the public with information on tick identification, tick bite prevention, Lyme disease and co-infection awareness, impact on pets and livestock, and health resources that are available for individuals who have been bitten by a tick.
  • New York State Department of Health – $25,000 to continue database mining, which would include various projects associated with Lyme carditis, as well as deaths associated with Lyme and other TBDs.
  • Town of Shelter Island – $25,000 to help combat the spread of ticks on Shelter Island, which is one of the worst hit areas of the public health crisis. The town has developed a four-poster program to stem the spread of ticks associated with the deer population. The town has built and installed four-poster stations, to remove ticks from deer across the Island, and this funding would maintain and expand the efforts of this critical initiative.

In addition to the $1 million announced today, the Senate was instrumental earlier this year in passing apackage of bills aimed at combating Lyme and TBDs, based on the recommendations of the Senate’s Task Force on Lyme and Tick-Borne Diseases.

________________

Also see:  https://madisonarealymesupportgroup.com/2018/06/20/ny-governor-cuomo-announces-public-private-research-collaboration-to-advance-diagnosis-and-treatment-of-tick-borne-diseases/

U.S. Government Continues to Pay Millions in Vaccine Injuries & Death Settlements

http://vaccineimpact.com/2018/u-s-government-continues-to-pay-millions-in-vaccine-injuries-and-death-settlements/

U.S. Government Continues to Pay Millions in Vaccine Injuries and Death Settlements

by Brian Shilhavy
Editor, Health Impact News

The federal government Advisory Commission on Childhood Vaccines (ACCV) under the U.S. Department of Health and Human Services just concluded their second meeting of 2018 on June 15th.

These quarterly meetings include a report from the Department of Justice (DOJ) on cases settled for vaccine injuries and deaths as mandated by the National Vaccine Injury Compensation Program (NVICP).

The NVICP was started as a result of a law passed in 1986 that gave pharmaceutical companies total legal immunity from being sued due to injuries and deaths resulting from vaccines.

Drug manufacturers in the vaccine market can now create as many new vaccines as they desire, with no risk of being sued if their product causes injury or death.

This has resulted in a huge increase of vaccines entering the market, and the U.S. government, through the Centers for Disease Control (CDC), is the largest purchaser of these vaccines, spending in excess of $4 billion taxpayer dollars each year to purchase these vaccines.

If you or a family member is injured or dies from vaccines, you must sue the federal government in this special vaccine court. Many cases are litigated for years before a settlement is reached.

As far as we know, Health Impact News is the only media source that publishes these reports each quarter. Past reports can be found here:  http://vaccineimpact.com/vaccine-injuries-and-deaths-compensated-through-vaccine-court/

The June 15, 2018 report states that 263 petitions were filed during the 3-month time period between 2/16/18 – 5/15/18, with 147 cases being adjudicated and 113 cases compensated.

But for some reason, the DOJ report only lists 68 of the settlements, leading one to wonder why only these particular cases were listed.

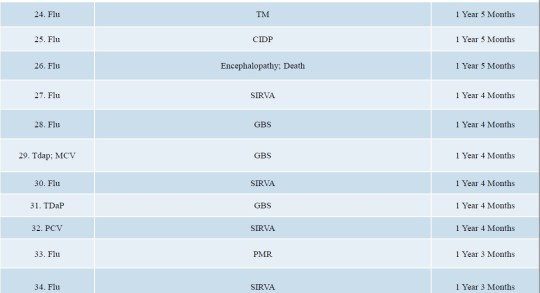
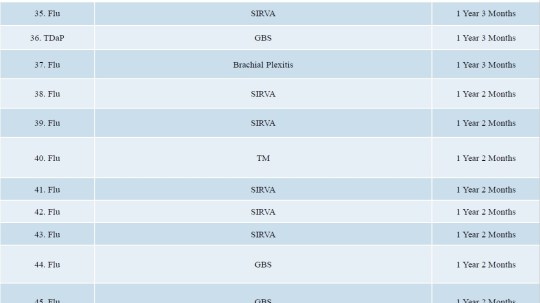
These 68 cases (see below), specify the vaccine, the injury, and the amount of time the case was pending before settlement.

53 of the 68 cases were for injuries (and one death) due to the flu vaccine, making the annual flu shot the most dangerous vaccine in the U.S., by far.

The most common flu vaccine injuries are SIRVA (“Shoulder Injury Related to Vaccine Administration”) and GBS (“Guillain-Barré Syndrome“), which leads to paralysis.

While “shoulder injury related to vaccine administration” may not sound serious, it can lead to very serious complications, including chronic pain.

SIRVA can lead to intense, prolonged pain, limited range of motion, and shoulder-related injuries such as Adhesive Capsulitis or Frozen Shoulder Syndrome. https://www.mctlawyers.com/vaccine-injury/sirva/  Read the story of how one man entered a hospital because of shoulder pain, and was dead six weeks later:  http://medicalkidnap.com/2017/12/17/56-year-old-man-enters-hospital-with-shoulder-pain-dies-6-weeks-later-after-developing-infection-in-hospital/

doj-vaccine-injuries-deaths-litigated-june-2018-page-1

doj-vaccine-injuries-deaths-litigated-june-2018-page-2

doj-vaccine-injuries-deaths-litigated-june-2018-page-3

doj-vaccine-injuries-deaths-litigated-june-2018-page-4

doj-vaccine-injuries-deaths-litigated-june-2018-page-5

doj-vaccine-injuries-deaths-litigated-june-2018-page-6

doj-vaccine-injuries-deaths-litigated-june-2018-page-7

Read the full report:  http://vaccineimpact.com/wp-content/uploads/sites/5/2018/06/DOJ-June-2018.pdf

Vaccine Injuries are Seldom Reported

In November of 2014, the Government Accounting Office (GAO) issued the first report on America’s “Vaccine Court,” known as the National Vaccine Injury Compensation Program (NVICP), in almost 15 years:  https://www.gao.gov/products/GAO-15-142

As I noted above, Congress gave the pharmaceutical companies immunity against lawsuits for injuries or deaths resulting in vaccines in 1986. Prior to this time, there were so many lawsuits pending against pharmaceutical companies for injuries and deaths due to vaccines, that the pharmaceutical industry basically blackmailed congress and told them that if they did not grant them legal immunity against the liabilities of vaccines, that they would quit making them. These vaccine products cannot survive in a free market, they are so bad.

The November 2014 GAO report criticized the government for not making the public more aware that the National Vaccine Injury Compensation Program exists, and that there are funds available for vaccine injuries. Therefore, the settlements represented by vaccine injuries and deaths included in the DOJ report probably represent a small fraction of the actual vaccine injuries and deaths occurring in America today.

The U.S. government keeps a database of reports documenting vaccine injuries and deaths called The Vaccine Adverse Event Reporting System (VAERS). The problem is that very few medical officials ever report vaccine injuries or deaths, either because they are not trained to recognize them, or due to pressure within their profession to not report them. To admit that vaccines do cause harm is professional suicide for most doctors and medical professionals.

Hence, the quarterly DOJ report on vaccine cases only represents a tiny fraction of the actual cases that exist.

One place we can get a glimpse of the amount of vaccine harm that is being caused in the U.S. today is to look at emergency room visits. As one can see in the report above, with most of the settlements being cases of harm caused by the flu vaccine, Guillain-Barré Syndrome (GBS) is the most common injury suffered from the flu shot. GBS is a debilitating disease that attacks a person’s own immune system and damages their nerve cells, causing muscle weakness and sometimes paralysis. It is very similar to the symptoms one may see with polio.

If you are taken to the emergency room with signs of GBS during flu season, chances are one of the first questions the doctors will ask you is if you have received the flu shot recently. GBS is also listed as a side effect of the flu shot in the package insert.

An emergency room nurse published his experience in dealing with the volume of vaccine injuries he was seeing, and how reluctant other medical personnel were in reporting these injuries:

As an E.R. nurse, I have seen the cover up. Where do you think kids go when they have a vaccine reaction?

They go to the E.R.

They come to me.

I cannot even begin to guess how many times over the years I have seen vaccine reactions come through my E.R. Without any exaggeration, it has to be counted in the hundreds.

Sometimes it seemed like it was one or two cases in a single shift, every shift, for weeks. Then I would get a lull, and I wouldn’t catch one for a week or two, then I’d catch another case per night for a couple weeks. This was common.

Once, I was training a nursing student, about to graduate, on their E.R. experience rotation in nursing school. This student and I floated up to triage to cover the triage nurse for a break. I was quizzing them on what to ask and look for as a triage nurse on pediatric kids that came through. I made a point about asking about immunizations right out the gates. The student was puzzled, and asked why, and I told the student because we see vaccine reactions every day and it’s their job to catch it, alert the doctor and the parents, and report it to VAERS.

Some higher power apparently smiled on my attempt to open the eyes of another nurse I guess, because not even ten minutes later, a woman brought her child up to the counter. Sudden onset super high fever and lethargy. I asked if the child was up to date on vaccination.

The mother replied he had them just a few hours ago.

I glanced at the student, who looked shocked and looked back at me in disbelief. I nodded, told them to remember this, and then took the mom and her child to finish the triage in back. When I was done I came back and sat down with the student, and asked what he learned that night so far.

The first response: “What I was told about vaccines wasn’t true”.

I couldn’t have said it better. That student is going to go on to be like me, advocating for his patients with his eyes wide open.

The cases almost always presented similarly, and often no one else connected it. The child comes in with either a fever approaching 105, or seizures, or lethargy/can’t wake up, or sudden overwhelming sickness, screaming that won’t stop, spasms, GI inclusion, etc.

And one of the first questions I would ask as triage nurse, was, are they current on their vaccinations? It’s a safe question that nobody sees coming, and nobody understands the true impact of. Parents (and co-workers) usually just think I’m trying to rule out the vaccine preventable diseases, when in fact, I am looking to see how recently they were vaccinated to determine if this is a vaccine reaction.

Too often I heard a parent say something akin to “Yes they are current, the pediatrician caught up their vaccines this morning during their check up, and the pediatrician said they were in perfect health!”

If I had a dollar for every time I’d heard that, I could fly to Europe for free.

But here’s the more disturbing part.

For all the cases I’ve seen, I have NEVER seen any medical provider report them to VAERS. I have filed VAERS reports. But I am the ONLY nurse I have EVER met that files VAERS reports.

Mind you, I have served in multiple hospitals across multiple states, alongside probably well over a hundred doctors and probably 300-400+ nurses.

I’ve worked in big hospitals (San Francisco Bay Area Metro 40 bed ER, Las Vegas NV Metro 44 bed ER) and small hospitals (Rural access 2 bed ER, remote community 4 bed ER) and everything in between.

When I say NEVER, I mean NEVER.

I have even made a point of sitting in the most prominent spot at the nurses station filling out a VAERS report to make sure as many people saw me doing it as possible to generate the expected “what are you doing” responses to get that dialog going with people.

And in every case, if a nurse approached me, their response was “I’ve never done that” or “I didn’t know we could do that” or, worse “What is VAERS?” which was actually the most common response.

The response from doctors? Silence. Absolute total refusal to engage in discussion or to even acknowledge what I was doing or what VAERS was.

The big take away from that?

VAERS is WOEFULLY under reported.

I am PROOF of that. Read the full blog post here:  https://www.healthyfamiliesforgod.com/blog/2015/11/er-nurse-shares-experiences-vaccine-reactions

Autism Vaccine Injuries Not Allowed: Too Many

One indication that the problem is more widespread than what the public is being told is the increasing rate of autism among children.

The U.S. government vaccine court will no longer hear cases of vaccines causing autism. When the Vaccine Injury Compensation Trust Fund was set up in 1988, autism was the most prevalent vaccine injury brought before the vaccine court, mostly from the MMR (measles, mumps, rubella) vaccine.

It soon became apparent that the trust fund, funded through taxes the public pays on vaccines, would not be sufficient to litigate all the claims for autism as a vaccine injury. By March 1, 2010, 13,330 cases had been filed in the special vaccine court, with 5,617 representing autism cases. Of those 13,330 cases filed up to March 1, 2010, only 2,409 were compensated. The rest were dismissed, but there were 5,933 cases still pending, and most of those were claims for vaccine-induced autism, mostly due to either the MMR vaccine, or vaccines containing thimerosal (mercury).

So how did the federal government and the vaccine court handle this?

Simple. They took 3 “test cases” that they said represented all of them and litigated against those claims. Their own appointed judges then ruled in each case that vaccines were not the cause of their autism. Then they told everyone else that their autism could not have been caused by vaccines, and that they would pay no damages for all those hundreds of thousands of children suffering with autism.

This was all part of what is called The Omnibus Autism Proceeding.

So if you have a child today injured by vaccines and suffering with autism, you cannot sue the federal government in vaccine court, as their official position is that vaccines do not cause autism.

One of the biggest myths being propagated in the compliant mainstream media today is that doctors are either pro-vaccine or anti-vaccine, and that the anti-vaccine doctors are all “quacks.”

However, nothing could be further from the truth in the vaccine debate. Doctors are not unified at all on their positions regarding “the science” of vaccines, nor are they unified in the position of removing informed consent to a medical procedure like vaccines.

The two most extreme positions are those doctors who are 100% against vaccines and do not administer them at all, and those doctors that believe that ALL vaccines are safe and effective for ALL people, ALL the time, by force if necessary.

Very few doctors fall into either of these two extremist positions, and yet it is the extreme pro-vaccine position that is presented by the U.S. Government and mainstream media as being the dominant position of the medical field.

In between these two extreme views, however, is where the vast majority of doctors practicing today would probably categorize their position. Many doctors who consider themselves “pro-vaccine,” for example, do not believe that every single vaccine is appropriate for every single individual.

Many doctors recommend a “delayed” vaccine schedule for some patients, and not always the recommended one-size-fits-all CDC childhood schedule. Other doctors choose to recommend vaccines based on the actual science and merit of each vaccine, recommending some, while determining that others are not worth the risk for children, such as the suspect seasonal flu shot.

These doctors who do not hold extreme positions would be opposed to government-mandated vaccinations and the removal of all parental exemptions.

In this eBook, I am going to summarize the many doctors today who do not take the most extremist pro-vaccine position, which is probably not held by very many doctors at all, in spite of what the pharmaceutical industry, the federal government, and the mainstream media would like the public to believe.

Canadian physician Dr. Andrew Moulden provided clear scientific evidence to prove that every dose of vaccine given to a child or an adult produces harm. The truth that he uncovered was rejected by the conventional medical system and the pharmaceutical industry. Nevertheless, his warning and his message to America remains as a solid legacy of the man who stood up against big pharma and their program to vaccinate every person on the Earth.

Dr. Moulden died unexpectedly in November of 2013 at age 49.

Because of the strong opposition from big pharma concerning Dr. Moulden’s research, we became concerned that the name of this brilliant researcher and his life’s work had nearly been deleted from the internet. His reputation was being disparaged, and his message of warning and hope was being distorted and buried without a tombstone. This book summarizes his teaching and is a must-read for everyone who wants to learn the “other-side” of the vaccine debate that the mainstream media routinely censors.

(Please go to link at top of page to access the ebook)