Archive for the ‘Activism’ Category

COVID-19 And The Elephant in The Room

https://www.europeanscientist.com/en/article-of-the-week/covid-19-and-the-elephant-in-the-room/

April 16, 2020

Covid 19 and the elephant in the room

Covid 19 and the elephant in the room
Obesity and chronic metabolic disease is killing COVID -19 patients: now is the time to eat real food, protect the NHS and save lives. 
(See link for article)
____________________
**Comment**
Important quote: 
It is well known in the medical literature that excess body fat induces immune dysregulation and chronic inflammation which is directly linked to the cytokine storm that is responsible for Acute Respiratory Distress Syndrome seen in influenza and other respiratory viruses. (4)
The article also admits that it’s highly likely another international viral pandemic will occur in the future.  By addressing the underlying factors we would have a healthier population. It goes on to say:

“Hopefully if and when that occurs a lockdown will not be required.”

Don’t hold your breath.  From where I sit and from what I’m reading, future lockdowns with decreasing civil liberties are the wave of the future unless we speak up now.

CDC Playbook: Learning From Lyme

April 25, 2020

By Alicia Cashman MS, Lyme patient and advocate

While most of the world is staggering with newly imposed social distancing measures, worrying about viruses and how to bolster the immune system, chronic Lyme patients simply carry on doing these things daily. They’ve been isolated for some time – either to avoid illness due to being immunocompromised or because they were forced into exile by authorities who tell them the illness they are struggling with simply doesn’t exist. In time, family and friends become more and more distant because they tend to believe the authorities. Authorities, after all, are honest and are looking after public health – aren’t they?

They say history repeats itself, which appears to be the case regarding COVID-19 when you study the sordid history of how Lyme disease has been and continues to be handled.
The CDC Insists Upon Using Its Own Tests

Due to decisions made at a conference in Michigan, serology testing criteria for Lyme Disease were purposely manipulated for vaccine development. To this day the CDC insists upon its own two-tiered testing which research has proven is abysmal and misses a vast majority of cases. It can’t distinguish between active, past, or reinfection.  It has now been removed, but the CDC website used to call specialized CLIA certified labs testing for tick-borne illness, “home-brewed.” I personally heard a pediatrician use those exact words at the Wisconsin State Capital in his effort of delegitimatizing patients who are forced to go to specially trained doctors using these labs to get diagnosed and proper treatment. This history is disturbing in and of itself but should particularly concern us in light of current events.

The CDC also insisted upon their own COVID-19 tests.  It was just discovered that CDC COVID-19 tests were initially contaminated with COVID-19 – making ALL numbers based upon those tests absolutely worthless. COVID-19 laced tests were also found in the UK.  Due to contamination, which they state on their website is a “problem with a reagent,” the entire United States is in lockdown. Had accurate testing been accepted by the CDC from the WHO from the start, authorities would have had accurate data to base decisions upon. This article states there are only 12 labs outside the CDC with the capability to test for the virus; however, as of the beginning of March, they hadn’t received FDA authorization to do their own testing. The CDC website states the following:

“This message is to remind clinical laboratories that this is currently the only EUA assay for severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), the virus that causes COVID-19. Any laboratory that is not designated by CDC as a qualified laboratory and is implementing a COVID-19 diagnostic test other than the CDC EUA assay must contact the FDA to obtain an EUA before any COVID-19 diagnostic testing may be performed in their facilities.”

Compare that statement with the following:

“The conference proceedings recommended a two-test methodology using a sensitive enzyme immunoassay (EIA) or immunofluorescence assay as a first test, followed by a western immunoblot assay for specimens yielding positive or equivocal results (1,2).

On July 29, 2019, FDA cleared several Lyme disease serologic assays with new indications for use based on a modified two-test methodology (4). The modified methodology uses a second EIA in place of a western immunoblot assay. Clearance by FDA of the new Lyme disease assays indicates that test performance has been evaluated and is ‘substantially equivalent to or better than’ a legally marketed predicate test.“

In other words, you better use our tests. If you think that FDA cleared tests are effective, think again. The CDC has monopolized Lyme testing since the beginning of time, dooming patients to a life-time of suffering.

This article states that only two government agencies are required by law to be “patient-centered,” the FDA and the Patient Centered Outcomes Research Institute (PCORI), yet Lyme patients continue to experience false negative results on CDC 2-tiered testing. Negative results means no diagnosis and no treatment. Patients and advocates have complained profusely with no change in testing.

The reason for insisting upon their own tests become clear when you go down rabbit-holes to discover they own patents on nearly everything surrounding the diseases they have tests for.  Please also see ConflictReport.  Dr. Fauci, director of NIAID, and a leader in the Corona Task Force has numerous patents, and a long list of conflicts of interest.

  • Journalist Mary Beth Pfeiffer summarizes CDC testing incompetence.
  • James Lyons Weiler, Phd also reveals the CDC’s testing fiasco. He knows that of which he speaks as he attempted to have the CDC test his own test for Ebola. Let’s just say he was promptly rebuffed.
  • Currently, a pathologist is suing the CDC for their willful suppression of direct detecting methods.
  • Professor Lane hit the same brick wall regarding testing.
  • Regarding COVID testing, the president of Tanzania (PhD Chemistry) punked the WHO by sending in goat, fruit, and motor-oil samples to be tested for COVID-19.  Half came back positive! 
  • The creator of the PCR states it was never created to diagnose patients but for research and manufacturing purposes.
  • Dr. David Rasnick, bio-chemist, protease developer, and former founder of an EM lab called Viral Forensics states,“I’m skeptical that a PRC test is ever true.” When asked his advice for people wanting to be tested for COVID-19, he said:
“DON’T DO IT…NO HEALTHY PERSON SHOULD BE TESTED. IT MEANS NOTHING BUT IT CAN DESTROY YOUR LIFE, MAKE YOU ABSOLUTELY MISERABLE.”
  • According to David Crowe, Canadian researcher with degrees in biology and mathematics, host of The Infectious Myth podcast, and President of the think-tank Rethinking AIDS:

“The first thing to know is that the test is not binary,” he said. “In fact, I don’t think there are any tests for infectious disease that are positive or negative. What they do is they take some kind of a continuum and they arbitrarily say this point is the difference between positive and negative.”

Further, and more importantly, COVID testing does not detect SARS-COV-2 due to the fact the virus has not been isolated/purified from all else. You can’t test for something specific if you don’t have that information.  COVID testing is not specific to a particular virus people have tested positive, then negative, then positive within hours or days.  The test simply picks up viral fragments – some of which are completely dead and benign – not causing illness at all, and some are from other strains of coronaviruses such as the common cold, but it’s all being falsely labeled COVID-19 – further inflating case numbers and fear.

Lastly, there’s the very important issue of PCR cycle threshold, which was set at 40 (although this varied from lab to lab.  Experts have weighed in stating a PCR cycle of 40 is far too sensitive and that it should be set much lower – around 30.  Cases plummeted when the cycle threshold was lowered proving this fact.  What is frightening about this is health ‘authorities’ can manipulate this cycle threshold for their own nefarious reasons.

This exact same fact is true with Lyme/MSIDS testing as well and is why research shows a majority do not test positive.

The CDC wants their own tests & patents so they can create their own vaccines and drugs they will profit from.

A vaccine called Lymerix caused Lyme-like symptoms in many. In fact, it can be directly linked to 222 deaths and hundreds of adverse reactions, and these are only the ones that were recorded.

The CDC to-date hasn’t even attempted to address the immune issues caused by Lymerix. They just deny it ever happened. In fact, another Lyme vaccine is in the works which still uses the same OspA component which is attributed with problems in the first human vaccine.

Fool me once, shame on you – fool me twice, shame on me.

COVID-19 vaccines have been fast-tracked thereby bypassing important safety studies. Dr. Hotez, a vaccine researcher, is on record stating previous respiratory vaccines caused “paradoxical immune enhancement“:

James Lyons Weiler, PhD also gives the following chilling prediction:

When Phase I trials become Phase II trials people will start getting infected w/SARS-CoV-2 following vaccination and start dying at even higher rates due to disease enhancement caused by Pathogenic Priming from SARS-CoV-2 vaccination – something the vaccine developers SHOULD have tested for in animal studies, but skipped.

Even the FDA is worried about potential risks of the PER C6 Ad5 technology (aborted fetal cells) within many COVID-19 vaccines, which not only has moral implications but oncogenicity and infectivity concerns. The vaccine also uses electricity to drive DNA into your cells.  

A group of doctors recently wrote a paper about the emergency use authorized, fast-tracked COVID “vaccines” and state they are needless, ineffective and dangerous. 

  • needless because there are effective treatments  (Scroll to comment section)
  • ineffective because they don’t stop transmission or keep you from becoming ill
  • dangerous due to causing: viral immune escape, an inevitable steep incline in future severe COVID cases, antibody-immune enhancement, a condition where the “vaccinated” suffer with more severe illness when exposed to the wild virus, but also any infection.  There are also  unsafe epitopes within the injections, and mounting reports of adverse reactions and deaths after these injections, which aren’t “vaccines.”

Faulty testing issues and the subsequent push for vaccines are uncannily similar between Lyme and COVID-19 and should strongly remind us that the CDC is a vaccine manufacturing company first and foremost – to the detriment of severely ill and desperate patients.

Why Should We Trust the CDC?

The question begging to be asked is why should anyone trust the CDC? Their track record speaks for itself. Even CDC scientists have formed a group exposing the corruption from within. They’ve also lied about flu figures for decades. The ACIP, a group within the CDC, votes “Yes” for new vaccines despite having no safety data. And let us never forget the CDC whistleblower who exposed that scientists were ordered to purposely destroy data showing that African-American males who got the MMR vaccine before 36 months had a 250% increase in autism diagnoses.

Recently, microbiologist Judy Mikovitz spoke out on the unethical behavior of Dr. Fauci, Director of the NIAID since 1984 and one of the lead members of the White House Coronavirus Task Force (NIAID and CDC are both under the HHS umbrella). Excerpt:

Dr Fauci ordered Mikovits to keep her mouth shut. When she refused, he illegally confiscated her work books and hard drives, drove her from government work + blackballed her from receiving NIH grants ending her science career.

For those of you who are unaware, Mikovits discovered that a mouse virus (XMRV) has contaminated vaccines all the way back to the 30’s. She believes the virus can be linked to diseases like chronic fatigue (CFS/ME), autism, Alzheimer’s, cancer, autoimmune, neuroimmune, central nervous system diseases, and even chronic Lyme disease. While retroviruses do not directly cause diseases by themselves they help to create acquired immune system deficiency (non-HIV AIDS) which in turn causes unrelenting inflammatory processes.  Call it a trigger, in a perfect storm of events within the body allowing disease to occur.

You may ask why you’ve never heard of XMRV before. That’s because the CDC, NIH, FDA, and other government agencies covered it up. They didn’t want to worry you, and they certainly don’t want you to question their lucrative vaccines.

XMRV remains in American vaccines.

There is much evidence showing both COVID-19 and Lyme/MSIDS have been manipulated in a lab.

Ian Lipkin, aka The Virus Hunter, has been involved with both issues due to the urging of Dr. Fauci. He denies XMRV involvement in human disease, despite Mikovitz’s group being able to transmit it from patients’ T-cells to uninfected T-cells in the laboratory. He also denies COVID-19 is a lab-made, manipulated virus.

Despite his denial, the origin of COVID-19, after boomeranging around the globe, has returned to show strong evidence that it is most likely a manipulated virus for biowarfare purposes after all.

Excerpt:

After creating the synthetic virus, which they call SHC014, Zhengli and her coauthors write that they “next synthesized a full-length SHC014-CoV infectious clone based on the approach used for SARS-CoV.”24 Other papers Zhengli co-wrote focus on the transmission of coronaviruses from one species to another, according to the documentary.

Zhengli and her fellow researchers admit they used a “reverse genetics system” to generate “a chimeric virus expressing the spike of bat coronavirus,” raising legitimate fears that COVID-19 is also reverse-engineered, according to “Tracking Down the Origin of the Wuhan Virus.”

And the real clincher:

According to Mikovits, the S proteins seen on COVID-19 that make it so transmittable to humans come from “cutting and pasting of two different viruses” and the apparent insertion of four new genes could not have been generated from a natural “zoonotic transmission.”

They had to come from a medical, bioweapons or lab setting, says Mikovits. Other scientists in the film agree that COVID-19 is a re-engineered, laboratory-driven virus.

But we were warned about this months ago, and then again recently with even more damning details.

Lyme patients are also familiar with bioweaponization. Recently, Congressman Smith announced a DOD investigation on the bioweaponization of ticks. Tick researchers have gone on record admitting to experimenting on ticks and dropping them out of airplanes.  And Kris Newby in her book “Bitten”, describes how a CIA operative dumped boxes full of crawling ticks over Cuba, returned home, and unwittingly infected his own newborn baby.  Dr. William Burgdorfer, the discoverer of the causative agent of Lyme disease worked as a bioweapons researcher for the US military and worked in programs tasked with breeding ticks and infecting them with pathogens that cause human diseases.

Besides faulty testing, a thrust to create a vaccine at all costs, a tightly controlled narrative, and bioweaponization, there is also a similar smear campaign on successful clinical treatments in both Lyme disease and COVID-19.

The CDC Slanders Competing Treatments

Authorities have purposely thwarted IV therapy for Lyme patients in a recent MMWR paper. The short recap is that the CDC cherry-picked 5 cases that had poor outcomes using IV therapy and then wrote a paper scaring the bejesus out of doctors. 

What’s interesting about the MMWR paper is that one of the authors, a CDC epidemiologist, allegedly solicited IDSA doctors for evidence of harm from IV antibiotic treatments, essentially bribing them by offering co-authorship of the report if anecdotes were used. No such solicitation was made for IV treatment success stories.  The dangling carrot has been blatantly observed with COVID treatment. There has been hot debate on Lyme treatments for decades. The MMWR paper is only one example of bias which is embedded within the CDC. There are many success stories using IV therapy by a Wisconsin Doctor and IDSA founder who disagreed with his colleagues on how to treat Lyme disease.

Meanwhile, doctors are reporting in on the success of treatments for COVID-19, but the CDC, true to form, bad-mouths any treatment or tests, other than ones they orchestrate. Based upon the CDC’s casting a dark shadow upon treatments that even patients attribute to saving their lives, numerous states (MI, NV, NY) as well as France have banned their usage for COVID-19.  It’s gotten so bad that judges are ordering hospitals to administer life-saving COVID treatment to dying patients because medical doctors kowtow to corrupt health ‘authorities’.

This tactic of politicizing clinically successful treatments is what the CDC/IDSA/NIH does. This article clearly shows the bantering common in mainstream media regarding COVID-19 treatment. The bi-partisan squabbling is tangible, and similar hit-pieces have been written about Lyme treatment for years. Lyme patients have had to straddle this polarized fence for over 40 years and this polarization continues unabated.

I was told by a front-line European doctor treating severely ill COVID-19 patients that hydroxychloroquine, commonly known as plaquenil, was used for over 70 years over the counter and was frequently given to travelers. Then, all of a sudden it became a prescription drug overnight, and now it’s being banned for use for COVID-19. This means doctors using it for COVID-19 will have their licenses revoked.

Scaring doctors and revoking their licenses is a common refrain for doctors treating Lyme disease.  My own doctor had to pay over $50,000 in legal fees fighting this battle and it’s happening not only in the U.S. but around the world due to the Iron Curtain of the CDC.

There is no question that IV therapies as well as extended antibiotics for Lyme and hydroxychlorquine for COVID-19 have side effects. No one is denying this. What’s unconscionable is that ‘authorities’ zoom in on particular treatments and microscopically nit-pick due to ulterior motives. It becomes crystal clear that the motivation is to control the narrative, and protect special interests – not to safe-guard patients.

Everyone wants double blind, placebo, randomized controlled trials (RCT); however, in the case of Lyme disease, those studies are controlled by a cabal who continue to study only the acute phase of the disease with faulty parameters for entrance into their studies. Again, testing is rigged for a predetermined outcome and they exclude a large subset of patients who don’t meet their stringent criteria.  Due to the complexity of Lyme/MSIDS, RTCs will never be done.

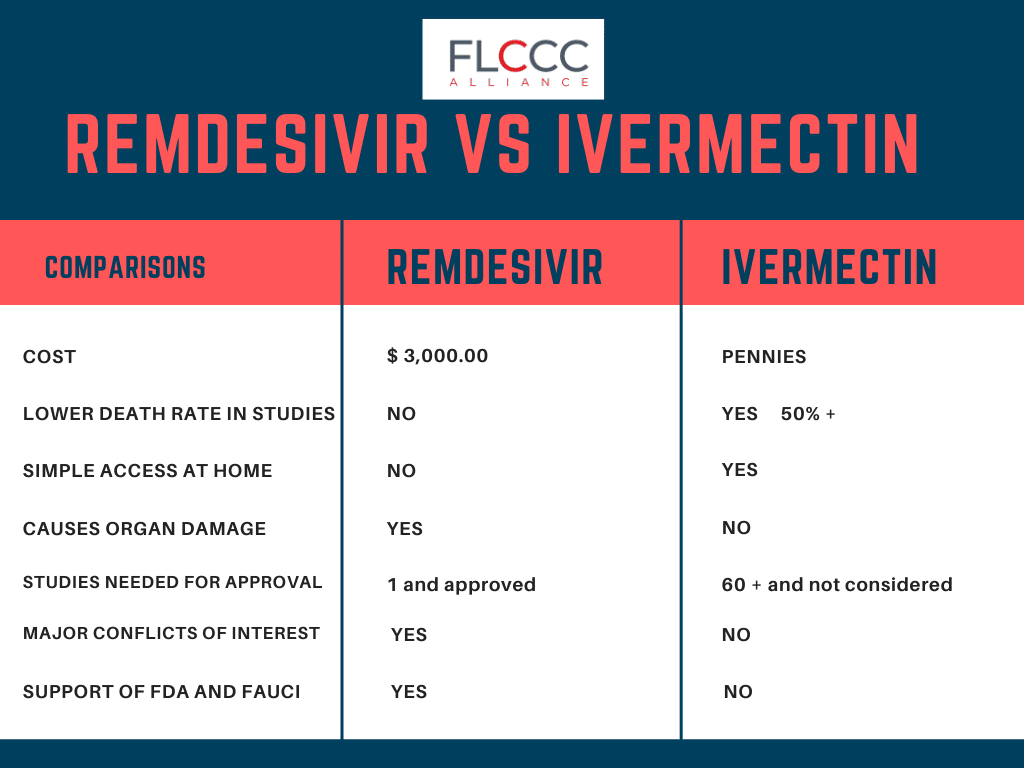
In the case of COVID-19, severe patients can quickly die, making those studies of little use in the present. Treatments are needed now, not in six months. Doctors and pharmacists go to school to learn about drugs and their interactions. How about authorities just let doctors do their jobs? I don’t see these authorities condemning cancer treatments which kill as many good cells as bad cells and cause horrific side-effects.  Why the focus on HCQ, ivermectin, and benign treatments like vitamin D, C, zinc, and quercetin?   This recent article explains why.  In essence, the CDC is in bed with Gilead Science as nine of the experts on the NIH COVID-19 Panel recommending treatment options have disclosed financial support from Gilead.  More dangling carrots.

Gilead Science created the anti-viral remdesivir which was unsuccessful for Ebola.  They are now digging it out of the drug graveyard and pushing it for COVID-19 to make up for lost profits. They did this exact same thing with AZT, a chemotherapy drug which failed for leukemia, and repurposed it for HIV patients who didn’t even have symptoms! HCQ, even though it’s clinically showing great success, stands in the way of their chosen profitable, albeit dangerous treatment. Remdesivir is not without side-effects and only showed modest benefits against COVID-19 but this is the CDC’s “golden” treatment, therefore, everything said about it is positive while they bad-mouth HCQ a direct competitor.

It’s also important to understand that the NIH owns half of the Moderna COVID vaccine. Many other conflicts of interest exist regarding this unique injection technology.

Where the handling of the two diseases drastically departs; however, is in how seriously the CDC is handling COVID-19 by enacting what most declare to be draconian measures, while continuing to downplay Lyme disease.  The learning curve for COVID-19 has been lightening fast in comparison to Lyme disease in that the conflicts of interest, the reliance upon faulty testing, and the polarization in the medical community on pretty much every aspect of the disease hasn’t budged in over 40 years.

What’s happening in the world today regarding COVID-19 is probably easier for Lyme patients to understand than the average person, but that doesn’t give them solace for the future. They will continue to wash their hands, do an entire laundry list of things to strengthen their immune systems, and will continue to be isolated. While the rest of the world returns to “normal” at some point, Lyme patients will continue living in a paradigm where the majority of doctors don’t even believe, test, or treat them, because the CDC has filled their heads with 40 year old unscientific, fraudulent dogma.


TBDWG Public Comment: Lyme Advocate Carl Tuttle

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/

TBDWG April 27, 2020 – Written Public Comment

APR 24, 2020 — 

The following comment was posted to the Tick-Borne Disease Working Group for the upcoming April 27th meeting.

If you want Dr. Ben Beard to answer the question below, cut and paste the comment into an email and respectfully demand an answer. Dr. Ben Beard’s public email address is: cbb0@cdc.gov

If Dr. Beard cannot answer that question as a representative of the CDC, what is he doing as a member of this Tick-Borne Disease Working Group?

TBDWG April 27, 2020 – Written Public Comment

https://www.hhs.gov/ash/advisory-committees/tickbornedisease/meetings/2020-4-27/written-public-comment/index.html

Carl Tuttle

Providing comments in support of the Change.org petition calling for a congressional investigation into the mishandling of Lyme disease.

Through recent events with Coronavirus we are witnessing what the Lyme community has endured for the past three decades:  Faulty/misleading antibody tests, inadequate treatment, no medical training and absolutely no disease control whatsoever; a public health disaster.

Our public health officials got away with mishandling Lyme disease because Lyme does not cause dead bodies piling up in the morgue in New York City but at the same time, no one is counting the number of lives ruined by Lyme disease.

So how will our public health officials find a way to maintain the status quo of a dysfunctional system in Lyme diagnosis after this massive tragedy is over?

What is the status of Direct Diagnostic Tests for Lyme Disease, Dr. Ben Beard of the CDC?

Persistent infection after extensive antibiotic treatment has been identified through the use of direct detection methods in academic centers [1] and autopsy findings yet the average patient cannot obtain these tests to justify how sick they are with their chronic active infection.

There has been a deliberate avoidance of direct detection methods in order to hide the truth that Lyme disease is a life-altering/life threatening infection capable of destroying lives, ending careers while leaving its victim in financial ruin.

So once again I ask the question Dr Ben Beard of the CDC; What is the status of Direct Diagnostic Tests for Lyme Disease?

Carl Tuttle
Lyme Endemic Hudson, NH

Reference

1. Seronegative Chronic Relapsing Neuroborreliosis. 

https://www.ncbi.nlm.nih.gov/pubmed/7796837

Coronavirus: Science, Policy, Politics, & 5G

CORONAVIRUS: SCIENCE, POLICY AND POLITICS

By Arthur Firstenberg

Many people are afraid of even asking whether 5G is playing a role in the COVID-19 disease that has shut down much of the world. It is similar to the fear that has prevented people from questioning the orders to stay home, wear masks, and keep six feet away from each other.

I am about truth, wherever I find it, wherever it may lead, because our world is at stake, and life itself — physical, mental, emotional and spiritual — is being dismantled. Conspiracies have no place in this effort. Neither does fear.

My opinions, based on my reading of the scientific and medical literature, as best as I can determine, are these:

  • Did 5G cause the coronavirus? No.
  • Does 5G cause disease similar to the coronavirus? Yes.
  • Did COVID-19 originate in bats? No.
  • Is COVID-19 a recombinant RNA virus, created in a laboratory, intentionally or unintentionally, as part of a research program whose purpose was to protect the population? Did it escape accidentally from a virology laboratory in Wuhan, China? Probably.

The measures that have been put in place, and accepted without question, are ineffective, destructive, and anti-life.

Masks do not protect the wearer. Medical masks are ineffective against viruses, and cloth masks provide breeding grounds for them. A 2015 study in the British Medical Journal found that:

  • Healthcare workers caught viruses from their patients 13 times more often if they wore a cloth mask than if they wore a medical mask.
  • a Chinese study found that a medical mask was no more protective against viruses than wearing no mask at all.
  • The World Health Organization warns that wearing a medical mask “may create a false sense of security” against COVID-19 and that “no evidence is available on its usefulness to protect non-sick persons.”
  • The N95 respirator, recommended for medical workers, requires training to use properly and “without training, the masks could not only expose workers to the virus but also lull them into thinking they are protected,” according to doctors at the Harvard School of Public Health. In practice, even the N95 mask has been found to be ineffective in preventing the transmission of viruses. A review of six clinical studies, published in the Canadian Medical Association Journal, found that medical workers caught viruses from their patients just as often when they used N95 respirators as when they used ordinary medical masks.

Masks are harmful to the wearer. COVID-19 kills by causing severe hypoxia (low levels of oxygen in the blood). People wearing masks rebreathe some of their exhaled air, lowering the amount of oxygen they are breathing.

“Wearing respirators come[s] with a host of physiological and psychological burdens. These can interfere with task performances and reduce work efficiency. These burdens can even be severe enough to cause life-threatening conditions if not ameliorated,” wrote the author of a 2016 article in the Journal of Biological Engineering. When the N95 respirator was tested in use in 2010, the “dead-space oxygen and carbon dioxide levels did not meet the Occupational Safety and Health Administration’s ambient workplace standards.”

Ventilators do not work and are harmful. Dr. Cameron Kyle-Sidell quit his job in the Intensive Care Unit at Maimonides Medical Center in Brooklyn because he was required to put his COVID-19 patients on ventilators that he felt were killing them because the air pressure was damaging their lungs. His coronavirus patients all had severe hypoxia but healthy respiratory muscles: they needed oxygen, he said, but not pressure.

“COVID-19 lung disease, as far as I can see, is not a pneumonia,” he said, but seems to be “some kind of viral-induced disease most resembling high altitude sickness… These patients are slowly being starved of oxygen … and while they look like patients absolutely on the brink of death, they do not look like patients dying of pneumonia.” Italian doctors agree: “Patients on ventilators deteriorate anyway, in an unexplained way… Most of these patients are plainly hypoxic.”

PCR tests are not accurate.

A March 25, 2020 paper by Carver and Jones reported that it is not possible to assess the accuracy of PCR tests because:

“There are little public data on the false positive and false negative rates of the various RT-PCR based tests.”

A false positive test means that you are diagnosed with COVID-19 when you don’t actually have it. One of the only studies to date that has attempted to estimate the frequency of false positives is Zhuang et al., “Potential false-positive rate among the ‘asymptomatic infected individuals’ in close contacts of COVID-19 patients”, Chinese Journal of Epidemiology, 2020, 41(4): 485-488 (in Chinese).

They concluded that up to 80 percent of non-symptomatic people who test positive for the coronavirus may not actually have it.

Shutdowns do not have any effect.

  • Japan, which did not shut down until April 6 and then only with voluntary measures, has 2 COVID-19 deaths per million population.
  • China, which shut down in December, has 3 deaths per million population.
  • Belarus, which never shut down, has 4 per million.
  • South Korea, which has only voluntary measures, has 5 per million.
  • Iran, which shut down in early March, has 62 per million.
  • Sweden, which did not shut down, has 156 per million.
  • Switzerland, which did shut down, has 165 per million.
  • Belgium, which did shut down, has 503 deaths per million population.
  • Vietnam, Laos and Cambodia, all close to China, have no COVID-19 deaths at all. Vietnam shut down in early February, Laos shut down in late March, and Cambodia has never shut down at all.
  • In the U.S., South Dakota, which has not shut down at all, has four times as many cases, but fewer deaths, than neighboring Montana, which is completely locked down.

Death rates in the United States have been going down, not up, since the beginning of the year. If you pay attention to the news, you might assume that record numbers of people are dying. The opposite is true. Not only has overall mortality for the United States been going steadily downward since January, but mortality has been substantially lower this year than last year. These are weekly mortality statistics for the United States from the Centers for Disease Control:

Week                   Number of Deaths 2019           Number of Deaths 2020

1                                  58,291                                           59,087

2                                  58,351                                           59,151

3                                  58,194                                           57,616

4                                  57,837                                           57,000

5                                  58,128                                           56,426

6                                  58,492                                           56,962

7                                  57,917                                           55,981

8                                  57,858                                           55,494

9                                  57,920                                           54,834

10                                  58,490                                           54,157

11                                  57,872                                           52,198

12                                  57,087                                           51,602

13                                  56,672                                           52,285

14                                  56,595                                           49,292

15                                  55,477                                           47,574

TOTAL                         865,181                                         819,659

We are told that 37,308 people have died this year from COVID-19 through April 18, yet actually 45,522 fewer people have died this year than last year during the same period of time.

RF radiation and COVID-19 cause similar disease. In my last newsletter (“Is the Sky Really Falling?”), I noted some effects of COVID-19 that are similar to effects of radio waves. The list of effects in common has grown, and includes:

  • headaches
  • dizziness
  • nausea
  • digestive problems
  • muscle pain
  • tachycardia
  • hypotension
  • cardiac arrhythmias
  • strokes
  • seizures

As many as two-thirds of people who test positive for COVID-19 have lost their sense of smell, often without any other symptoms. Patients are presenting with mental confusion, without any respiratory symptoms at all. Patients are presenting with diarrhea, vomiting, and abdominal pain. When patients with any of these symptoms test positive for the coronavirus, their illnesses are being attributed to that virus. But these are all classic symptoms of radio wave sickness.

When both the virus and RF radiation are present, the disease should be attributed to both.

And RF radiation and COVID-19 both cause hypoxia. COVID-19 impairs oxygen absorption by the blood, and RF radiation impairs oxygen use by the cells. COVID-19 would not be so severe were it not for the radiation.

Recently, there is a new symptom that is being attributed to the virus that is exactly what one would expect to see from millimeter waves: a “fizzing” sensation throughout the body. It is being described as a “buzzing sensation,” “a burning feeling,” and “an electric sensation in the skin.” It is probably wrongly being attributed to the virus, and is due instead to 5G.

It is a fact that 5G was turned on in Wuhan, China on November 1, 2019, and that the first known COVID-19 patient became ill there on November 17.  It is a fact that there is a research virology lab in Wuhan, and that researchers there coauthored a paper in 2015 with American researchers from Chapel Hill, North Carolina describing a hybrid coronavirus that they had created by attaching a spike protein from bats to a SARS coronavirus. Zheng-Li Shi, the lead researcher from Wuhan, said in an interview in Scientific American that she had worried that COVID-19 was a virus that had escaped from her lab, but she reassured the world that she had checked and it did not resemble any of the viruses that she had collected in bat caves. Yet in the next sentence she justified her claim that COVID-19 came from bats by saying that it was almost identical to a virus that she had collected in a bat cave in Yunnan.

The SARS virus has escaped from high-level containment facilities in China multiple times. As revealed by the Washington Post on April 14, 2020, U.S. Embassy officials had warned in 2018 that sloppy safety protocols for handling contagious viruses in the Wuhan lab “represented a risk of a new SARS-like pandemic.”

It is also a fact that the animal market in Wuhan does not sell bats. A YouTube video that has been shared on social media that shows bats being sold for meat at a market was actually filmed in Langowan, Indonesia, and not in China at all.

In short, 5G is part of the coronavirus equation, and everything that we have been doing to address the pandemic has more to do with politics and fear than with reality. It is time to re-open society, to take off our masks, and to open our eyes to what is really happening to our world.

Arthur Firstenberg


P.O. Box 6216
Santa Fe, NM 87502
USA
phone: +1 505-471-0129
info@cellphonetaskforce.org
https://www.5gSpaceAppeal.org

A pdf version of this newsletter is available here:

https://www.cellphonetaskforce.org/wp-content/uploads/2020/04/Choosing-Life.pdf

For Firstenberg’s Curriculum Vitae:  https://madisonarealymesupportgroup.com/wp-content/uploads/2020/04/96e76-curriculumvitaeofarthurfirstenberg.pdf

To sign the international petition to halt 5G:  https://www.5gspaceappeal.org/sign-individual

For more on 5G:  

For an interesting read on the connection between COVID-19, COVID injections, 5G, and Chemtrails.  

A few important excerpts:

…globalist entities that are behind the military deployment of 5G worldwide needed a cover for the inevitable outbreaks of both 5G Flu and 5G Syndrome.  The coronavirus pandemic has provided just that, especially in light of the fact that many of the symptoms of both are quite similar. See: Is The “Coronavirus” Actually Microwave Illness from 4G and 5G Radiation?

There have been many telltale signs that are dead giveaways about the close coordination between the military deployment of 5G just before the first major COVID-19 outbreaks around the world.  For example, Wuhan was established as China’s first 5G “Demonstration Zone” in 2019. See: Wuhan City Was expected to have 10,000 5G base stations operating by the end of 2019

Another major clue concerns the highly suspicious work being conducted at Harvard University.  The activation of 5G energy grids amps up the manifestation and severity of Covid symptoms considerably which is why Harvard’s Charles M. Lieber holds the U.S. Patent for using 5G radiation to vibrate corona virus particles from preset nanotubule containers.  The Chair of the Chemistry Department was arrested and indicted in June of 2020.

….Just how many assaults can the human body take before it starts to break down, particularly for the elderly and those with serious comorbidities. See: CHEMTRAIL SYNDROME: A Global Pandemic Of Epic Proportions

The article also points out that the aerosolized and chemically mobile aluminum oxide is “particularly toxic to the brain when permitted to pass through the blood-brain barrier.” This was accomplished through the invasive nasal COVID-19 testing which punctured the brain lining, causing some to need surgery.

Dr. Oz Interviews Dr. Didier Raoult on Hydroxychloroquine Study for COVID-19

 Approx 33 Min. April 15, 2020

EXCLUSIVE: Dr. Oz Discusses The Hydroxychloroquine Study Outcome With Dr.Didier Raoult

Do not seek these medications without the guidance of a doctor.

_________________

**Comment**

I’ve posted on Hydroxychloroquine before:

Lyme/MSIDS patients know this drug as plaquenil and often use it for Babesia, a malarial-like organism that is considered a fairly common coinfection from a tick bite.  In fact, both my husband and I used this drug in our treatment regimen.

I’ve heard directly from European doctors that this drug is working miraculously for COVID-19.  Miraculously. We also heard recently from Michigan Representative Karen Whitsett, also a chronic Lyme sufferer, that this treatment saved her life:  https://madisonarealymesupportgroup.com/2020/04/16/trump-holds-meeting-with-recovered-covid-19-patients-first-one-has-chronic-lyme-disease/

Then there’s Dr. Zelenko, a New York doctor, who’s successfully treated 1,450 COVID-19 patients with a 99% success rate using a cocktail of hydroxychloroquine, Zinc Sulfate and Azithromycin:  https://techstartups.com/2020/04/21/dr-vladimir-zelenko-now-treated-1450-coronavirus-patients-2-deaths-using-hydroxychloroquine-99-99-success-rate-latest-video-interview/  Video with Zelenko in link.

Evidently, Lorraine Johnson of Lyme Disease Organization stated the following about the need for COVID-19 treatment now in a recent Forbes interview:

“It is important right now to take the gloves off clinicians and give them access to all available tools. Patients are dying and can’t wait for clinical trials.”  https://www.lymedisease.org/patients-cant-wait-covid-lyme/

She states her comment drew fire.

This is also what I’ve been noting.  But it doesn’t surprise me.  Why?  Because Lyme disease treatment that has proven to be successful clinically has also been targeted by “authorities”:  https://madisonarealymesupportgroup.com/2017/06/23/no-bias-in-mmwr-for-any-other-infectious-disease-requiring-iv-antibiotics-except-for-lyme/  The short recap is that the CDC cherry-picked 5 cases that had poor outcomes using IV therapy and then wrote a paper scaring the bejesus out of doctors. 

What’s interesting about the MMWR paper is that one of the authors, a CDC epidemiologist, allegedly solicited IDSA doctors for evidence of harm from IV antibiotic treatments, offering co-authorship of the report if anecdotes were used, according to a blog post by Lymedisease.org’s vice president. No such solicitation was made for IV treatment success stories.

I just happen to have success stories on IV therapy from an IDSA founder here:  https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/

The MMWR paper is a prime example of bias which frankly is embedded within the CDC.

“If you search the MMWR archives, there are no other examples of this sort of bias for ANY OTHER infectious disease requiring IV treatments,” Ahern wrote in an email. “None.”

To those that are worried about side-effects: nearly all drugs have side-effects. This is why doctors and pharmacists go to school. They are fully capable of discussing these side-effects with their patients and deciding if it’s worth the risk or not.
Did you know you can actually die from drinking too much water?  It’s true.
**Medpage recently came out with this article, which does have a disclaimer that it is a satirical piece; however, the picture of Dr. Oz with tape over his mouth is quite telling. The title is, ” CDC Recommends Dr. Oz Wear ‘Duct Tape Mask’**: https://www.medpagetoday.com/blogs/gomer/86071
I don’t think the message could be clearer.