https://www.mdpi.com/2673-6772/1/2/6/htm

First Report of Ixodes scapularis Ticks Parasitizing a North American Porcupine in Canada

by John D. Scott
 
 
Department of Medicine and Epidemiology, School of Veterinary Medicine, University of California, Davis, CA 95616, USA
Academic Editor: Theo De Waal
Parasitologia 2021, 1(2), 45-49; https://doi.org/10.3390/parasitologia1020006
Received: 16 February 2021 / Revised: 18 March 2021 / Accepted: 25 March 2021 / Published: 1 April 2021

Abstract

Adult females of the blacklegged tick, Ixodes scapularis (Acari: Ixodidae), were collected from a North American porcupine, Erethizon dorsatum, in eastern Ontario, Canada. This porcupine parasitism indicates that an established population of I. scapularis is present in the local vicinity. This tick species is known to parasitize more than 150 different vertebrate hosts, including the North American porcupine. The presence of I. scapularis ticks parasitizing a North American porcupine constitutes a new tick-host record in Canada.

1. Introduction

The North American porcupine, Erethizon dorsatum (Rodentia: Erethizontidae), also known as the Canadian porcupine, is a herbivore rodent. This meso-mammal is one of the largest members in the rodent family, and has wide distribution across continental North America. This woodland denizen is native to coniferous and mixed forests across southern Canada, and its distribution extends southward into northeastern, north-central, and western United States as far south as the northern fringe of Mexico. Ecologically, free-ranging porcupines have a home range of up to 28 ha. This arboreal herbivore is covered with a coat of quills that arm it from predators. Once a porcupine is threatened, it will hide its face, swat its tail at its assailant, and thrust an arsenal of quills in multiple directions to strike its attacker. The sharp, needle-like quills are painful, and prudent attackers retreat. In the spring and summer, porcupines feed on berries, seeds, grasses, leaves, roots, and stems. In the winter, North American porcupines feed on the inner bark of trees. As these herbivore rodents forage for food, they make direct contact with low-lying vegetation where ticks are questing.
Blacklegged ticks, Ixodes scapularis (Acari: Ixodidae), are indigenous across North America east of the Rocky Mountains [1]. Ixodidae, commonly referred to as hard ticks, are predominantly blood-feeding ectoparasites of mammals and birds although several species feed on reptiles [1]. Tiny ticks maintain a stealth presence in the natural environment, and covertly parasitize North American porcupines. These quill-laden rodents are primarily nocturnal, but will defend themselves at any time of day. In Wisconsin, wildlife rehabilitators collected I. scapularis adults from several North American porcupines [2].
 
The locality where the free-ranging porcupine was found is in the Great Lakes-St. Lawrence forest region which consists primarily of red pine, eastern white pine, eastern hemlock, yellow birch, sugar maple, and red oak [3]. In a tick-host study conducted across Ontario with veterinarians, wildlife rehabilitators, and the public, acarologists previously detected I. scapularis ticks on domestic dogs, cats, and humans in the same precambrian area (Canadian Shield) [4]. Although porcupines have feeding activities in trees, these spiny rodents will have direct contact with low-lying vegetation when they are feeding at ground level. If present, this is where I. scapularis ticks are questing. Depending on the time of year and their developmental life stage, I. scapularis ticks conduct host-seeking activities anytime through the day. Several blacklegged ticks collected within a single collection period (a single year) indicate that a reproducing population of I. scapularisis present [5,6].

2. Results

The North American porcupine was found on the side of the road north of Westport, Ontario on County Road 10 (44.687° N, 76.385° W), which is situated within the Canadian Shield (Figure 1). The injured porcupine was taken to Sandy Pines Wildlife Centre, Napanee, Ontario, and a wildlife rehabilitator examined it. Since the head had visible trauma, it is believed that the porcupine was struck by a passing vehicle. Based on a x-ray, veterinary technicians also found a diaphramatic hernia. Due to the severity of trauma, the North American porcupine was promptly euthanized upon arrival, and five partially engorged I. scapularisfemales were collected.

3. Discussion

The collection of five engorged I. scapularis females feeding on a North American porcupine is a novel discovery in Canada (Figure 2). Based on a literature search [2,7,8,9] and the Canadian National Collection, the author affirms that this mammalian parasitism is the first documentation of I. scapularis parasitizing a North American porcupine in Canada. (See link for full article)

ihttps://medicalxpress.com/news/2021-04-lyme-disease-distinguishes-early-late-stage

New Lyme disease test distinguishes between early and late-stage disease

April 7, 2021

Lyme disease

For those who live in an area blighted by ticks, the threat of Lyme disease can cast a shadow over the joy of spring and summer. These blood-sucking arachnids can transmit bacteria into the bloodstream of their unsuspecting host, causing the disease. Early treatment is essential, but current tests are not usually sensitive enough to detect the disease in early-stage patients. A recent study in open-access journal Frontiers in Microbiology reveals a new test for Lyme disease, which is the first to reliably distinguish between early- and late-stage patients. The test detects a genetic sequence left by a virus that resides in Lyme-causing bacteria, and can detect just one bacterial cell in a small blood sample.

As the most common tick-borne infection, Lyme affects nearly 500,000 people in the U.S. every year. Symptoms include fever, fatigue, joint pain, and a distinctive ‘bullseye’ rash, but if left untreated, the disease can cause paralysis and even death. As such, is important, but difficult.

“Early diagnosis of Lyme disease is absolutely vital in reducing suffering, because early Lyme can be treated, but late Lyme is very difficult to treat,” explained Dr. Jinyu Shan of the University of Leicester, lead author on the study. “Current tests cannot typically detect the low numbers of bacteria in early-stage patient blood samples. Our goal was to design a highly sensitive to help doctors to identify Lyme disease as early as possible.” (See link for article)

______________________

Study here: https://madisonarealymesupportgroup.com/2021/03/31/targeting-multicopy-prophage-genes-for-the-increased-detection-of-borrelia-burgdorferi-sensu-lato-the-causative-agents-of-lyme-disease-in-blood/

Evidently the test is unique in that it is based on prophages that have a genetic sequence inserted into the bacteria by a virus which can escape the bacteria, and is more likely to be picked up in the blood due to having multiple copies within cells.

They found the test is sensitive and can detect one bacterial cell in .3 mL of blood.  Infected patients have between 1-100 bacterial cells per mL of blood.

The test is the first to distinguish between healthy, early-stage, and late-stage samples.


I must admit that the debacle with PCR testing for COVID has made me extremely skeptical and wary.  I hope that this isn’t too good to be true.  Time will tell.

https://www.sciencedirect.com/science/article/abs/pii/S1877959X20304775

Tick-borne diseases and co-infection: Current considerations

Abstract

Over recent years, a multitude of pathogens have been reported to be tick-borne. Given this, it is unsurprising that these might co-exist within the same tick, however our understanding of the interactions of these agents both within the tick and vertebrate host remains poorly defined. Despite the rich diversity of ticks, relatively few regularly feed on humans, 12 belonging to argasid and 20 ixodid species, and literature on co-infection is only available for a few of these species. The interplay of various pathogen combinations upon the vertebrate host and tick vector represents a current knowledge gap. The impact of co-infection in humans further extends into diagnostic challenges arising when multiple pathogens are encountered and we have little current data upon which to make therapeutic recommendations for those with multiple infections. Despite these short-comings, there is now increasing recognition of co-infections and current research efforts are providing valuable insights into dynamics of pathogen interactions whether they facilitate or antagonise each other. Much of this existing data is focussed upon simultaneous infection, however the consequences of sequential infection also need to be addressed. To this end, it is timely to review current understanding and highlight those areas still to address.

https://www.theblaze.com/op-ed/horowitz-shocking-report-55-of-brits-have-antibodies-despite-12-months-of-restrictions

Originally, we were told that governments can assume unprecedented control over our lives, businesses, and even our own faces for the goal of not overrunning hospitals. A year later, as we come increasingly close to herd immunity, not only are hospitals in no danger of being overrun, but it turns out that people have likely contracted the virus at a rate that would have occurred without any of these restrictions – and their calamitous damage to society. Twelve months later, it’s all pain and no gain. (See link for article)

________________________

**Comment**

Excerpt:

img

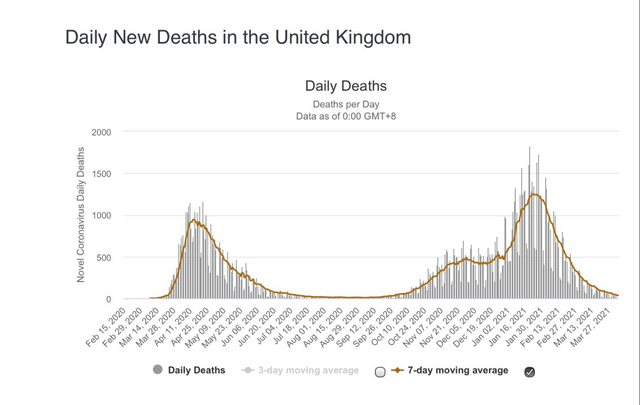
This data demonstrates that the entire 12-month premise of lockdowns and masks to slow the spread was a lie (after the original lie of flatten the curve), and even more so, any continuation of these policies after most people have immunity is built upon a dastardly lie. Even if the new goal has changed illogically from decreasing the burden on the hospitals to slowing the growth of cases, it’s quite evident that these measures don’t work. We have now achieved well over 50% immunity between infection and vaccines in most Western countries, built on 12 months of masochist public policy designed to preclude that immunity.

Horowitz points out that this intel comes at a time when public ‘authorities‘ are pushing the myth of super deadly and contagious variants, yet Britain has barely had any cases.

The intel also falls in line with what others are saying.

Yet, dissenting doctors continue to be censored and people are losing jobs for not forcing and adhering to these nonsensical measures that have been proven time and again not to work.  In this bizarre world of “make-believe,” you can now purchase a combination phone/mask.

Track coach Brad Keyes put it succinctly:

“I’ll come straight to the point,” he said. “I will not put kids on the track and tell them to run any races while wearing masks.”

Brutally honest in his message to Vezina, Keyes said the athletic directors and school boards that followed New Hampshire Interscholastic Athletic Association recommendations and agreed to outdoor mask-wearing were being dishonest to the athletes, by making decisions without wisdom or science.

“No, the real reason I won’t do it is because it’s senseless, irrational, cowardice b——t and I will not help cover that up,” Keyes wrote. “I will not stand up in front of the kids and lie to them and tell them that these masks are doing anything worthwhile out in an open field with wind blowing and the sun shining.”

“Fire me if you must,” was the title of his follow up message. On Monday, his school bosses did just that.  Source

Meanwhile, Fauci falters to explain the downward trend in Texas, where 80% have reached herd immunity without the COVID injection. Perhaps he’s waiting to include more cases after people getting the injection test positive for the virus.  It’s a win/win for continuing the fear-mongering.

Even mainstream media has to admit:

  • An official of the European Medicines Agency said he believes there is a link between the AstraZeneca COVID-19 vaccine and blood clots. (Barron’s)

  • Oxford University has stopped a trial of AstraZeneca’s COVID-19 vaccine in teenagers and children due to concerns over blood clotting. (Wall Street Journal)

  • 246 fully-vaccinated Michigan residents later tested positive for COVID-19; 11 required hospitalization and three of them died. (Detroit News)
  • The Baltimore manufacturing plant that recently had to discard 15 million doses of Johnson & Johnson’s coronavirus vaccine had a history of flouting the rules. (New York Times)
Before you agree to the jab, please read about the many adverse reactions and deaths.

Also, Please see 12 Vaccine Truths put out by the Disinformation Dozen.

A UK organization labeled as the “Center for Countering Digital Hate” produced a report that stated that 65% of all vaccine misinformation comes from a set of 12 people, and put forth a call to big tech platforms to censor their content and erase them completely from their platforms. They labeled this group the “Disinformation Dozen,” and the message has been pushed out to news sources around the world.

https://www.americasfrontlinedoctors.com/custom_videos/the-year-that-disappeared/  Forum Here

AFLDS Frontline Forum – The Year That Disappeared


An AFLDS Issue Brief for Citizens, Policymakers and Physicians


STATEMENT OF POSITION
Countering pervasive cancel culture is a national priority. From music to books to movies and now medicine, cancel culture is eroding constitutional free speech and destroying lives. Cancel culture imposes political and social consequences for attempting to speak truth to power. Among these consequences are professional sanction and social media bans, quasi-public platforms that can effectively silence individuals without due process. Americans across the political spectrum are fed up with the self-censorship and speech restrictions inherent to cancel culture.

The coronavirus pandemic has introduced the insidious sub-category of medical cancel culture into our political lexicon. For more than a year, doctors and healthcare professionals nationwide have faced censorship, termination, and intimidation from state medical and pharmacy boards, scientific journals, and providers like hospitals merely for relaying their patient experiences. Describing one’s job should not result in losing an occupation and source of income.

The purpose of this Issue Brief is to describe instances of medical cancel culture and explore what can be done to counter it. This is nothing less than a national emergency. At stake is the health and safety of every American, as well as their access to independent information free from official suppression or censor.

THE WAY WE LIVE NOW
The coronavirus pandemic has tested public health experts like no other event since the Spanish flu outbreak of more than a century ago. Unfortunately, it seems, truth was again the first casualty in the war on an infectious pathogen in 2020-21. How did we get here? Through a combination of establishment institutions and figures silencing dissent and the mainstream media playing the role of willing enforcer. Below are only a small selection of medical cancel culture examples in the last year:

  • Pierre Kory – Dr. Kory, who testified in front of the US Senate Homeland Security Committee in December 2020, noted the positive findings of a clinical study in Argentina which tested the effectiveness of ivermectin for the prevention and treatment of COVID-19. YouTube’s parent company Google responded by removing his testimony from its video-sharing platform, even though more than a dozen separate studies suggest that the antiparasitic drug, a widely available, cost-effective alternative for patients with mild to moderate disease, works when individuals are treated early after symptoms emerge.
  • Michael deBoisblanc – Dr. deBoisblanc was terminated from his position as a trauma medical director at John Muir Health in December 2020 after he and two other Bay Area doctors spoke out against California state government’s scientifically illiterate and economically devastating COVID-19 lockdown strategy. The doctors sent a letter to Contra Costa County health officials and legislators on December 10 asking them to justify a stay-at-home order set to expire the next month. Among other restrictions, the order banned outdoor dining and kept schoolchildren away from in-person instruction despite lack of CDC evidence for either prohibition.
  • Steven LaTulippe – Dr. LaTulippe had his medical license revoked by the Oregon Medical Board in December 2020 after he did not wear a mask at his clinic and “engaged in unprofessional conduct or dishonorable conduct,” according to the emergency suspension. LaTulippe told patients who believe they had COVID-19 or were showing symptoms of the virus to wear a facial covering, and saw these patients at the end of the day at his practice, according to published reports.
  • Scott Jensen – In April 2020, Dr. Jensen questioned CDC and Minnesota Department of Health guidelines related to death certificates for suspected COVID-19 patients. He soon found his medical license challenged by the state’s Board of Medical Practice and was threatened with cancellation in the mainstream media, simply for defending longstanding practices and medical ethics.
  • Dan Erickson and Artin Massihi – After questioning California’s punitive lockdown order in April, Bakersfield doctors Erickson and Massihi were subjected to endless media attacks and had their remarks censored by YouTube. The tech giant removed two of the urgent care physicians’ videos for violating its “community guidelines,” effectively preventing its more than 1 billion users from hearing a dissenting opinion from so-called public health “experts.” 

CONCLUSION
Restricting free speech for political ends is the glidepath to tyranny. Today, public and private interests alike attempt to “cancel” dissenting voices they find inconvenient or uncooperative. Lives and livelihoods are being lost. Americans should not have to live in fear that they might find themselves on the wrong side of a fashionable issue, or suffer professional sanction for disagreeing with conventional wisdom.

The answer for speech with which we disagree is not to eliminate it but to allow more voices into an open system of freely exchanged ideas. Trust everyday Americans to weigh the facts and decide for themselves. The stakes in this fight could not be greater. Medical cancel culture is a fast-spreading virus that threatens to infect all independent scientific information unless we push back.

________________________

**Comment**

Many in the medical field are now seeing what we in Lyme-land have been experiencing for decades: censorship, institution bias, flawed research, intimidation, and termination of employment.

If there’s ONE good thing that has come out of this ‘Plandemic,’ perhaps it’s an awakening in the medical field that ‘all is not as it seems.’

While public ‘authorities’ want you to believe Lyme is hard to catch and easy to treat, they desperately want you to believe COVID is the worst disease on the planet when data show it has nearly the same mortality rate as the seasonal flu and that serious cases are in the elderly with comorbidities.  Most are infected and recover. In fact, recently Dr. McCullough states Texas is at 80% natural herd immunity (without a vaccine), this immunity is complete AND durable, there are numerous effective treatments, and you can’t vaccinate on top of this and make it better.  He states there is no science or rationale behind vaccinating or testing a recovered COVID patient.

Yet, similarly to Lyme literate doctors, these dissenting doctors treating COVID continue to be censored and silenced.