URGENT: The Assembly Committee on Constitution and Ethics has scheduled a hearing on vaccine freedom bills AB 299, AB 303, AB 309, AB 316, and AB 347. The hearing is scheduled for Wednesday, June 2, at 10 am and will be held in the Wisconsin State Capitol at 417 North (GAR Hall). The John Birch Society encourages members to attend tomorrow’s hearing and testify in support of the bills listed above.

Members of the Wisconsin Legislature are seeking to pass legislation protecting citizens from forced vaccinations.

Several bills have been introduced and would robustly protect individual freedom with regard to vaccinations. One of these is SB 4, which prevents both local officials and the Department of Health Services (DHS) from requiring people to receive COVID-19 vaccines. Although Governor Tony Evers vetoed the Assembly companion, AB 23, the Senate bill can still pass.

Additionally, SB 5 and AB 25, prohibits employers from forcing their employees to receive any of the COVID-19 vaccines. Meanwhile, AB 299 would prohibit government and private entities from requiring a COVID vaccine in order to receive services, while AB 303 would prohibit businesses from discriminating against customers based on whether or not they have been vaccinated.

Similarly, AB 309 would prohibit multiple forms of discrimination based on one’s vaccination status, while AB 316 prevents government discrimination against those who refuse to take the coronavirus vaccine. Last, but not least, AB 347 ensures that students attending the University of Wisconsin System are not required to take the coronavirus vaccine in order to attend.

In addition to the general, and real, risk of the government mandating coronavirus vaccinations to increase the inoculation rate, some Wisconsin employers are already laying off staff for refusing to take the vaccine.

Multiple reasons exist for why it is important to oppose forced vaccinations. For one, individuals might have religious, conscientious, or other personal reasons for wishing not to be vaccinated, making forced vaccination a direct infringement on the U.S. Constitution’s First Amendment. Additionally, potential health risks of vaccines in general – and of a COVID-19 vaccine specifically, considering its rapid development – make it even more important to keep them voluntary. Mandatory vaccinations would be yet another step in the steady encroachment of government over every aspect of our daily lives.

Since the COVID-19 pandemic began, the federal, state, and local governments have exceeded their constitutional limitations in a variety of areas. It is imperative that citizens push back, rein in these government entities, and ensure they cease to violate our constitutional liberties.

Enacting SB 4, SB 5, AB 25, AB 299, AB 303, AB 309, AB 316, and AB 347 would be a positive start in Wisconsin.

Urge your state representative and senator to pass these vaccine freedom bills!

If you can’t attend in person, let your representatives here:

https://www.lifesitenews.com/news/vaccine-researcher-admits-big-mistake-says-spike-protein-is-dangerous-toxin

Vaccine researcher admits ‘big mistake,’ says spike protein is dangerous ‘toxin’

‘Terrifying’ new research finds vaccine spike protein unexpectedly in bloodstream. The protein is linked to blood clots, heart and brain damage, and potential risks to nursing babies and fertility.
Mon May 31, 2021 
Featured Image

May 31, 2021 (LifeSiteNews) — New research shows that the coronavirus spike protein from COVID-19 vaccination unexpectedly enters the bloodstream, which is a plausible explanation for thousands of reported side-effects from blood clots and heart disease to brain damage and reproductive issues, a Canadian cancer vaccine researcher said last week.

“We made a big mistake. We didn’t realize it until now,” said Byram Bridle, a viral immunologist and associate professor at University of Guelph, Ontario, in an interview with Alex Pierson last Thursday, in which he warned listeners that his message was “scary.”

“We thought the spike protein was a great target antigen, we never knew the spike protein itself was a toxin and was a pathogenic protein. So by vaccinating people we are inadvertently inoculating them with a toxin,” Bridle said on the show, which is not easily found in a Google search but went viral on the internet this weekend.

Bridle, a vaccine researcher who was awarded a $230,000 government grant last year for research on COVID vaccine development, said that he and a group of international scientists filed a request for information from the Japanese regulatory agency to get access to what’s called the “biodistribution study.”

“It’s the first time ever scientists have been privy to seeing where these messenger RNA [mRNA] vaccines go after vaccination,” said Bridle. “Is it a safe assumption that it stays in the shoulder muscle? The short answer is: absolutely not. It’s very disconcerting.”  (See link for article)

_____________________

**Comment**

Studies have shown that the spike protein, on its own, is what is causing the blood clotting, bleeding, and other cardiovascular effects of COVID-19, if it gets into the blood stream.  Now, they admit it gets into the blood stream – after millions have been injected with it. 

To listen to Bridle on the peer-reviewed research upon which this information is based:

Bidle admits:

The spike protein has been found circulating in the blood and is accumulating in ovaries, the liver, spleen, bone marrow, and adrenal glands.  It can bind to receptors that are on our platelets & the cells that line our blood vessels.  This can cause platelets to clump, leading to clotting, or bleeding.  The heart is also involved in this, which is why there’s been many reports of heart issues after these injections.  It crosses the blood, brain barrier and can cause neurological damage.

Animals injected with the spike protein also developed these issues. This spike protein was found to cross the blood brain barrier and cause damage to the brain.

For an excellent video explanation, Dr. McCullough and Dr. Byram Bridle explain how the spike protein distributes all over the body within as little as 15 minutes and accumulates in organs.  They continue to circulate for weeks or longer.  Bridle says, “We made a big mistake.”  He admits those receiving the injections are being injected with a toxin which can cause damage.  He’s also concerned about infertility since it accumulates in the ovaries.

Borrelia (Lyme) love the brain as well and there is an association with brain diseases such as dementia, ALS, and Alzheimer’s, with borrelia.  An important question to ask is what are the effects of a ‘toxic’ spike protein AND borrelia in the human brain?  

Important quote:

Bridle cited the recent publication of a peer-reviewed study which detected spike protein in the blood plasma of three of 13 young healthcare workers that had received Moderna’s COVID-19 vaccine. In one of the workers, the spike protein circulated for 29 days.

The researcher states that this spike protein can attach to specific ACE2 receptors on blood platelets which can either cause clotting or bleeding and this would explain the recent reports of heart issues in youth who were injected.

The FDA was even warned of this danger by a pediatric rheumatologist.

This of course has implications for the Red Cross as these pathogenic spike proteins could be transferred to others.

It also suggests “vaccinated” mothers could transfer spike proteins to nursing babies, and there is evidence in VAERS of suckling infants experiencing bleeding disorders in the gastrointestinal tract.

High concentrations of spike proteins have been found in testes and ovaries, which supports a GSK whistleblower’s statement that these injections can cause sterility.

Unsurprisingly, the vaccine researcher in the article now is being attacked, harassed, and intimidated.  Thankfully, he’s standing his ground.

He’s part of  an independent group of Canadian doctors, scientists, and professions called the Canadian COVID Care Alliance (CCCA) which has stated,

“Seasonal influenza is associated with more severe illness than COVID-19.”

Meanwhile, vaccine manufacturers have not responded to these concerns.

For more:

https://www.aflds.org/agenda  Register Here (Other dates and locations listed)

The Uncensored Truth Tour

Physicians and Patients Standing Up for Science, Freedom, and Common Sense

Attendance is FREE when you Register in Advance!

About the Event

America’s Frontline Doctors takes the truth directly to the people, with a cross-country road tour headlined by AFLDS.org founder Dr. Gold delivering “The Religion of Public Health”, a profound diagnosis of 2020’s viral propaganda, and also featuring additional AFLDS physicians and attorneys at select venues.

The Uncensored Truth Tour is a relentless force of scientific and legal facts fighting back against censorship, chaos, and the undeniable slide towards communism that lurks beneath the tyrannical lockdowns of governmental “public health” policy.

Milwaukee, WI

DR. SIMONE GOLD

Doors at 5:30pm
SATURDAY, JUNE 26, 2021

https://lymediseaseassociation.org/blogs/lda-guest-blogs/adrian-baranchuk-md-guest-blog/

Adrian Baranchuk, MD, Guest Blog – Lyme Carditis 2021 Update

LDA Guest Blogger

Adrian_Baranchuk_Photo_2020

Adrian Baranchuk MD, FACC, FRCPC, FCCS, FSIAC is Professor of Medicine at Queen’s University, Kingston, Ontario, Canada. He is Editor-in-chief, Journal of Electrocardiology; Vice President, International Society of Holter and Non-Invasive Electrocardiology (ISHNE); Secretary, Interamerican Society of Cardiology (SIAC); Co-Director, ECG University; Past President, International Society of Electrocardiology (ISE); and Director, NET-Heart Project (Neglected Tropical Diseases and other Infectious Diseases affecting the Heart).

Lyme Carditis: Update 2021. An Evasive Diagnosis in the Time of COVID-19

Adrian Baranchuk MD, FACC, FRCPC, FCCS, FSIAC; Chang (Nancy) Wang MSc (c), MD
Department of Medicine, Kingston Health Science Center, Kingston, Ontario, Canada

Lyme disease (LD) is a tick-borne bacterial infection caused by Borrelia burgdorferi. Lyme carditis (LC) is an early-disseminated manifestation of LD, most commonly manifesting as a complete “shut-down” of the electrical system (high-degree atrioventricular block (AVB)) that can evolve rapidly over minutes, hours, or days producing severe symptoms like fainting, palpitations, shortness of breath, extreme dizziness, or sudden death (1-2).

Other cardiovascular manifestations include alterations of the “motor” of the heart (sinus node disease) (3), a disorganization of the cardiac rhythm that increases the risk of stroke (atrial fibrillation) (2), lesion in the distal cables of the heart (bundle branch blocks) (4), and different degrees of inflammation of the layers of the cardiac walls (myocarditis, pericarditis, and endocarditis) (2). Some of these manifestations could be so severe that a total dysfunction of the cardiac function occurs in a matter of hours, and the patient may die even if admitted to the best ICU in the world.

The initial symptoms of LD can be mistaken by other common infections or allergic reactions. Delayed diagnosis is one of the most important risk factors to serious LD presentations including LC in all its forms. The good news is that prompt diagnosis and appropriate antibiotic therapy links to a much better prognosis. In addition, we now know that when appropriately treated with antibiotics according to guidelines (2); there is no evidence of residual disease in the heart (5).

Most conduction abnormalities caused by LC resolve with appropriate antibiotic therapy (2).

The current COVID-19 pandemic is posing a new challenge in the diagnosis of LD. There are lots of overlapping symptoms such as: fever, malaise, generalized pain, lack of energy, etc. During these times, one would advise on ruling out COVID-19 first before embarking on any other test. However, what could we recommend in terms of confirming or ruling out LD, specifically during these challenging times?

Learning how to recognize the many presentations of LD from a clinical point of view has been published several times. It is especially important to ask about outdoor activities, history of tick bites, tick removal and dermatological rashes (remember that the classic “bull eye” is only present in about 40% of cases). Extensive dermatologic examination may be necessary. Residence in an endemic region for LD is essential for risk stratification, as these recommendations should be encouraged in all ED and family doctor offices in areas of high prevalence.

Once the diagnosis is suspected, specific interrogation should be directed to cardiovascular symptoms such as: dizziness, palpitations, fainting or near fainting, chest pain and shortness of breath. If the patient recognizes any of these symptoms, along with any other factors suggesting LD, a 12-lead ECG (the simple and unexpensive electrocardiogram) should be performed (2). Any evidence of electrical disturbance should prompt admission in hospital for a course of IV antibiotics while waiting the results of serological tests.

On the other hand, in patients presenting with unexpected high-degree AV block, clinical suspicion for LC can be assessed using the validated risk score called SILC (Suspicious Index in Lyme carditis) (6) where the acronym COSTAR(Constitutional symptoms, Outdoor activities/endemic region, Sex male, Tick bite, Age > 50, Rash) may help in determining the risk of presenting early disseminated LC.

In summary, use your clinical tools to suspect LD in the context of COVID-19 pandemic, order serological tests when appropriate, and remember to check for cardiovascular complications with a history, physical, and ECG. If evidence of LC, admit the patient to hospital with continuous cardiac monitoring and appropriate IV antibiotics. Decision for permanent pacemaker implantation should wait until completion of antibiotics as heart block in LC is often reversible. Most patients maintain normal rhythm on long-term follow-up. Avoiding unnecessary implants is crucial as most of these patients are young and active individuals.

References
1. Wan D, Blakely C, Branscombe P, Suarez-Fuster L, Glover B, Baranchuk A. Lyme Carditis and High-degree Atrioventricular Block. Am J Cardiol 2018; 26(5): 233-239
2. Yeung C, Baranchuk A. Diagnosis and Treatment of Lyme Carditis. J Am Coll Cardiol 2019; 73(6): 717-726
3. Gazendam N, Yeung C, Baranchuk A. Lyme carditis presenting as sick sinus syndrome. J Electrocardiol 2020; 59: 65-67
4. Maxwell N, Dryer M, Baranchuk A, Vinocur M. Phase 4 Block of the Right Bundle Branch Suggesting His-Purkinje System Involvement in Lyme Carditis. HeartRhythm Case Reports. 2020; 7(2): 112-116
5. Wang C, Baranchuk A. Long-term evolution of patients treated for early disseminated Lyme carditis. Third prize at the ICE 2021 (International Congress on Electrocardiology)
6. Besant G, Wan D, Yeung C, Blakely C, Branscombe P, Suarez-Fuster L, Redfearn D, Simpson C, Abdollah H, Glover B, Baranchuk A. Suspicious Index in Lyme Carditis (SILC): Systematic Review and Proposed New Risk Score. Clin Cardiol 2018; 41(12):1611-1616

______________________

For more:

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/29105701?

The US Centers for Disease Control is lying to the public about Lyme disease!

MAY 24, 2021 — 

As promised from the previous petition update, the following is a critique of Dr. Grace Marx’s, PowerPoint presentation which clearly shows that our public health officials are lying to us. You can voice your opinion and send her an email:  lwx1@cdc.gov

Dr. Marx contact info: (photo is from this link)

https://www.eventscribe.com/2019/IDWeek/ajaxcalls/AccountInfo.asp?efp=Q0NRVktHSkw2ODg2&userShareID=36678593&rnd=0.8305856

———- Original Message ———-

From: CARL TUTTLE <runagain@comcast.net>
To: “lwx1@cdc.gov” <lwx1@cdc.gov>, “coca@cdc.gov” <coca@cdc.gov>
Cc: All members of the NH Lyme Disease Study Commission,”governorsununu@nh.gov” governorsununu@nh.gov
Date: 05/22/2021 2:16 PM
Subject: Re: Lyme Disease Updates and New Educational Tools for Clinicians

Dr. Marx,

As anticipated, the Clinician Outreach and Communication Activity (COCA) Webinar failed to mention the ten important facts I pointed out in my email dated May 15th five days prior to your presentation.

After reviewing the slides of your presentation at the following link, I found additional areas of concern:

Lyme Disease Updates and New Educational Tools for Clinicians
https://emergency.cdc.gov/coca/ppt/2021/052021_Lyme_Disease_Slides.pdf?fbclid=IwAR05dtD4eswvd_8WLpBQkp_1j-A2iME1WRdWJmcGTaxehWdIZN5FC2KcpAA

_____________________________________________________________________________________________________________________
Page# 11

Transmission occurs:

  • After an infected tick has been attached for at least 24hrs
  • Most transmission occurs after 36 hours
Carl Tuttle’s comments:  Rapid transmission has been reported in under 4hrs  [1, 2, 3, 4]

Page# 15

95% of reported Lyme disease cases are from 15 states and D.C.

Carl Tuttle’s comments:  Quest diagnostics is reporting positive Lyme tests in all fifty states. [5]

Page# 21

  • A single dose of doxycycline can lower the risk of Lyme disease
Carl Tuttle’s comments:  Single dose Doxycycline after tick bite as prophylaxis against Lyme disease failed 80% of the time in the mouse model so why would this be recommended in humans? [6]

Page# 25

  • Most tick bites do NOT transmit disease, so antimicrobial PEP is not routinely recommended.
Carl Tuttle’s comments:   77% of the ticks tested in the town of Litchfield, NH were carrying tick-borne disease as reported by a 2009 UMass Tick Study [7] so assuming that disease will not be transmitted is like playing Russian roulette with the public’s health. Front line clinicians in this Lyme endemic region who are witnessing the devastation first hand will offer the patient thirty days of minocycline after a tick bite.

Page# 32

  • The LYMERix vaccine was available between 1998 and 2002
  • Safe and effective
  • Pulled from the market in 2002
Carl Tuttle’s comments:  The LYMErix vaccine was pulled due to adverse reactions [8]and class action lawsuit:

VACCINES AN-D RELATED BIOLOGICAL PRODUSTS ADVISORY COMMITTEE
Advisory Committee Meeting: l/31/01
https://www.dropbox.com/s/sodqs3pdeeesktf/Sheller%20Lymerix.pdf?dl=0

Below is communication with the attorney who handled the LYMErix lawsuit.

“The people who have contacted us were, prior to vaccination with LYMErix, healthy, active and energetic. Indeed, the very reason they sought the LYMErix vaccine was their desire to preserve their healthy, active lifestyle. However, what they experienced was a dramatic degradation of their health and quality of life. As will be described below, these previously healthy individuals are now afflicted with painful, at times debilitating arthritic symptoms, including joint pain and swelling, as well as extremely severe Lyme-disease-like symptoms which have persisted to this day.”  -Stephen A. Sheller, Esq

Page# 37

Typical Lyme Disease Manifestations

  • Three months or more; Arthritis [Late stage]
Carl Tuttle’s comments:  What stage of Lyme disease results in disability; patients in wheelchairs?  You can become horribly disabled or die [9] from Lyme disease and routinely denied Social Security Disability Compensation and yet the public knows nothing about this stage of disease.

Page# 38

  • Erythema migrans (bulls-eye rash) 70%
Carl Tuttle’s comments:  The State of Maine DOH reported incidence of rash less than 50% as mentioned in my previous email.

Page# 45

  • Blacklegged ticks may also transmit pathogens that cause:
    Anaplasmosis
    Babesiosis
    Ehrlichiosis
    Borrelia miyamotoi disease
    Borrelia mayonii (Lyme disease)
    Powassan virus disease
Carl Tuttle’s comments:  Why isn’t the CDC recommending a “tick panel” to check for all of these pathogens?

Page# 48

  • CDC recommends diagnostic tests for Lyme disease that have been evaluated and cleared by the FDA. Two-step serologic tests are the only FDA-cleared test for Lyme disease.
Carl Tuttle’s comments:  Why after nearly forty years since the discovery of Lyme do we not have an accurate test to detect Lyme in all stages of disease???

Page# 49

  • Two-Step Lyme Disease Serologic Testing
  • A NEGATIVE Elisa means NEGATIVE
Carl Tuttle’s comments:  The more sensitive Western blot is only ordered after a positive Elisa lab result and it is used to rule out a FALSE POSITIVE Elisa.

When a NEGATIVE Elisa is found the Western blot is never ordered to rule out a FALSE NEGATIVE. So basically a NEGATIVE Elisa is 100% reliable whereas a POSITIVE Elisa is never reliable. How can this test be reliable in one instance and not another? Physicians are not allowed to order the Western Blot after a NEGATIVE Elisa and this practice is criminal. The system of using the Elisa as first line testing is completely flawed.

“If false results are to be feared, it is the false negative result which holds the greatest peril for the patient.” – Dr. Allan MacDonald

Page# 51

Western blot for Lyme Disease

  • Positive test requires at least 2 out of 3 [IgM] bands
  • Positive test requires at least 5 out of 10 [IgG] bands
Carl Tuttle’s comments:  Interpretation of the Western immunoblot is an area of significant confusion. Strict criteria were created in 1994 for surveillance of Lyme disease and only those patients who met this strict case definition were reported to the CDC. So if you did not meet those criteria your Western blot stated NEGATIVE.

Under the Infectious Conditions for Public Health Surveillance page, the Centers for Disease Control updated its Lyme Case Definition  in 2011 stating the following:

“This surveillance case definition was developed for national reporting of Lyme disease; it is not intended to be used in clinical diagnosis”

Physicians who treat Lyme disease exclusively recognize that it is not necessary to have five positive Western blot IgG bands or two IgM bands in order to diagnose Lyme disease. Those guidelines were strictly developed for surveillance purposes only.

Page# 59

Test Sensitivity by Manifestation of Lyme Disease

  • Early Localized (bulls-eye rash) -POOR
  • Early Disseminated -VERY GOOD
  • Late Disseminated -EXCELLENT
Carl Tuttle’s comments: Serology for Lyme disease is no better than a coin toss [10, 11] and is responsible for unimaginable pain and suffering.

2010 Complaint Letter to Jose T. Montero, MD, Director NH DHHS
https://www.dropbox.com/s/3pfjav6mtj50hkd/2010%20Letter%20Jose%20T.%20Montero%2C%20MD%2C%20Director.pdf?dl=0

Page# 63

Each stage of disease can be treated effectively with antibiotics.

Carl Tuttle’s comments:  There are hundreds of references to failed treatment of the one-size-fits-all IDSA Lyme treatment guideline [12,13] so why does the CDC continue to refuse to recognize this problem leaving hundreds of thousands (if not millions worldwide) in a debilitated state?

Treatment Delays Increase Risk of Persistent Illness in Lyme Disease (Johns Hopkins)
https://www.hopkinslyme.org/news/treatment-delays-increase-risk-of-persistent-illness-in-lyme-disease/

Page# 66

Treatment for Neurologic Lyme Disease

  • 2-3 weeks duration in all cases
Carl Tuttle’s comments:  I have never met any Lyme patient horribly disabled from neurologic Lyme disease who returned to baseline health with 2-3 weeks of antibiotics.

One high profile case comes to mind:

NEWS: Former patient who testified as a child about Lyme disease recalls encounter with Sen. Ted Kennedy
https://www.lymedisease.org/186/

Evan White testified from his wheelchair in 1993 at Senator Ted Kennedy’s Hearing, Washington DC

Excerpt:

“No one could hear or feel the moment of that child and not be moved,” Kennedy explained to the [Boston] Globe at the time. Anyone who wasn’t moved, he said, “hasn’t got a heart.”

Based on the summary below it appears that it took years of antibiotics, not weeks to treat Evan’s disability. Had he not met Dr. Joseph Burrascano, Evan would have been a burden on the Social Security program today through “therapeutic nihilism.”
 
Late Neurologic Lyme Is Reversible: Evan White

Post by CaliforniaLyme » Wed 31 Oct 2007 16:46

https://www.lymeneteurope.org/forum/viewtopic.php?t=147

Page# 72

Lyme Disease Treatment Considerations

  • Pregnant or breastfeeding patients:
    • doxycycline in pregnant or breastfeeding woman has not been thoroughly studied
Carl Tuttle’s comments:  Where is the section on congenital transmission of Lyme disease which has been identified dating back to 1985? [14]

Page# 74

Post Treatment Consideration

  • Most patients with Lyme disease recover completely within WEEKS to MONTHS after a course of antibiotic treatment.
Carl Tuttle’s comments: This statement has been propagated by the CDC for over thirty years while the horribly disabled continue to go unrecognized .

Page# 74

Post Treatment Considerations

  • About 1 in 20 treated patients may experience symptoms more than six months after treatment.
Carl Tuttle’s comments:  Once again that number was pulled out of a hat and propagated by the CDC for over thirty years while researchers at Johns Hopkins found 35% of acute Lyme disease patients who were treated with the IDSA’s short course of antibiotics were found to meet the case definition of “Post Lyme Disease Syndrome” at six months:
 

Post-treatment Lyme disease syndrome symptomatology and the impact on life functioning: is there something here?
http://www.lymemd.org/pdf/aucott_et_al_qol_research.pdf

Page# 75

Post Treatment Considerations

  • Additional prolonged antibiotics have not been shown to improve long-term outcomes
  • long-term antibiotic therapy has the potential to cause serious side-effects…
  • More than two courses of antibiotics have NOT been recommended for the treatment of Lyme disease.
Carl Tuttle’s comments:  The Klempner NIH antibiotic trials were cut short at three months. Evan White would still be in a wheelchair today or deceased if his treatment ended after only three months.

Two Controlled Trials of Antibiotic Treatment in Patients with Persistent Symptoms and a History of Lyme Disease
http://www.nejm.org/doi/full/10.1056/NEJM200107123450202#article_references#t=references

Second comment: Doxycycline for Acne has been prescribed long term for decades but when Lyme is involved, suddenly we have a double standard.

____________________________

Dr. Marx,

It would appear that you are not a front-line treating physician for Lyme disease. The majority of our public health officials have never treated the late-stage Lyme patient and therefor have no practical experience whatsoever while propagating the disinformation as I have pointed out.

It is blatantly obvious that the CDC is now grooming its younger generation of Medical Epidemiologists in the practice of suppressing the truth, facts and scientific references in order to maintain the illusion that our public health officials have everything under control.

Carl Tuttle
Hudson, NH

Cc: All members of the NH Lyme Study Commission
Governor Chris Sununu

REFERENCES (Please read them!)

1. Clinical evidence for rapid transmission of Lyme disease following a tick bite

https://www.sciencedirect.com/science/article/abs/pii/S0732889311004159?via%3Dihub

2. B. Patmas, MA, Remora, C. Disseminated Lyme Disease After Short-Duration Tick Bite. JSTD 1994; 1:77-78

https://www.lymedisease.org/hard-science-on-lyme-ticks-can-transmit-infection-the-first-day/

3. Lyme borreliosis: a review of data on transmission time after tick attachment

Michael J Cook
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4278789/

The claims that removal of ticks within 24 hours or 48 hours of attachment will effectively prevent LB are not supported by the published data, and the minimum tick attachment time for transmission of LB in humans has never been established.

4. Regarding Tick Attachment Times –

https://history.nih.gov/display/history/Burgdorfer%2C+Willy+1986

there are about 5 to 10 percent of infected ticks that have a generalized infection, including salivary glands and saliva at the time of attachment. In such cases, transmission of spirochetes would and does occur immediately at time of attachment.” —Willy Burgdorfer

5. LYME SCI: Lyme has been found in all 50 states and is on the rise

https://www.lymedisease.org/lymesci-lyme-all-states/#:~:text=Quest%20Diagnostics%20has%20released%20its,cases%20continues%20to%20rise%20nationwide

6. A sustained-release formulation of doxycycline hyclate (Atridox) prevents simultaneous infection of Anaplasma phagocytophilum and Borrelia burgdorferi transmitted by tick bite
 
https://www.dropbox.com/s/jc0h9g9arjhc8l1/Zeidner%202008.pdf?dl=0

7. Correlation between Tick Density and Pathogen Endemicity, New Hampshire
https://wwwnc.cdc.gov/eid/article/15/4/08-0940_article

8. LymeRix Vaccine Victim’s Stories
https://www.dropbox.com/s/5ikfgocui4hk7h9/LymeRix%20Victims.pdf?dl=0

9.  Deaths From Lyme Disease Compiled by: John D. Scott, Research Scientist 17 April 2018
 
https://www.dropbox.com/s/eo794dx7zspc1ln/Ld%20deaths.doc?dl=0

10. Two-Year Evaluation of Borrelia burgdorferi Culture and Supplemental Tests for Definitive Diagnosis of Lyme Disease
 
Peggy Coulter , 1   Clara Lema , 1   Diane Flayhart , 1   Amy S. Linhardt , 1   John N. Aucott , 2   Paul G. Auwaerter , 2 and   J. Stephen Dumler  1, *

Published 2005

Comparisons with qualitative clinical assessments

“Overall, initial serologic tests agreed with possible or probable clinical Lyme disease diagnosis in only 50% (40/80) of cases.” [COIN TOSS]

11. Commercial test kits for detection of Lyme borreliosis: a meta-analysis of test accuracy
 
Michael J Cook   1 ,   Basant K Puri   2

Sensitivity for each test technology varied from 62.4% for Western blot kits, and 62.3% for enzyme-linked immunosorbent assay tests, to 53.9% for synthetic C6 peptide ELISA tests and 53.7% when the two-tier methodology was used.  [COIN TOSS]

12. 700 articles LYME EvidenceofPersistence-V2
 
https://www.dropbox.com/s/n09sk90eo6xz7ua/700%20articles%20LYME%20EvidenceofPersistence-V2.pdf?dl=0

13. Lyme borreliosis: diagnosis and management

https://www.bmj.com/content/369/bmj.m1041/rr-1

14. Congenital Transmission of Lyme
 
https://www.dropbox.com/s/xlju8w25phkypy0/Congenital%20Transmission%20of%20Lyme.pdf?dl=0

_______________________

**Comment**

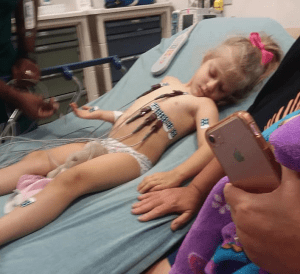
A picture is worth 1,000 words:
child-300x274

This is what an “insignificant” tick bite looks like and why all of this matters.
