Lincoln, Neb. – Recently, the Department of Health and Human Services (DHHS) was notified by the Northeast Nebraska Public Health Department of two cases of Lyme disease locally acquired within their jurisdiction. Both patients reported likely exposure around the same time frame at sites located near one another in Thurston County.
Due to the association between both cases, a coordinated environmental investigation involving DHHS, the Northeast Nebraska Public Health Department, and the Winnebago Public Health Department was completed at the suspected exposure sites. Ixodes scapularis (commonly called deer tick or the blacklegged tick) were collected from the sites of likely exposure.
Thurston County is now the fourth known county (Douglas, Sarpy, and Saunders were identified in 2019) in the state to have established black-legged tick populations. A subset of the ticks collected was sent to the CDC’s Division of Vector-Borne Disease and Creighton University for testing in an attempt to detect pathogens vectored by the tick including the bacteria (Borrelia burgdorferi) responsible for causing Lyme disease.
Ticks submitted to Creighton University and CDC came back positive for Borrelia burgdorferi indicating that the bacteria that causes Lyme disease is circulating in the tick population in the area. These results mark the first ever detection of Borrelia burgdorferi in Nebraska’s blacklegged tick populations and the first definitive evidence of Lyme disease cases acquired locally in the state.
The detection of an established population of black-legged ticks in Nebraska with evidence of detectable pathogens heightens concern of further establishment of the tick vector and its associated pathogens in other areas of the state. DHHS will continue to work with the Northeast Nebraska Public Health Department, the Winnebago Public Health Department, and other state public health partners on surveillance efforts for blacklegged and other medically important ticks.
While tick activity may be slowing down with colder weather, blacklegged ticks can be active year-round. There are simple steps people can take to protect themselves against tick bites.
Prevention steps include:
Use an EPA approved insect repellent containing DEET, picaridin, IR3535, oil of lemon eucalyptus, para-menthane-diol, or 2-undecanone.
Treat clothing and gear such as boots, pants, socks, and tents with products containing 0.5% permethrin.
Dress in long-sleeved shirts, pants, and socks when outside.
Do frequent tick checks after being outdoors and remove attached ticks promptly with fine-tipped tweezers. Don’t forget to check pets for ticks after being outdoors as well.
Shower as soon as possible after being outdoors.
Ticks are generally found near the ground, in brushy or wooded areas. They cannot jump or fly. Instead, they climb grasses or shrubs and wait for you to brush against them. This is called “questing”. When this happens, they hang on to you with small claws and then find a spot to attach and take a blood meal.
What to do if you find an attached tick:
Remove the attached tick as soon as you notice it by grasping with fine-tipped tweezers, as close to the skin as possible, and pull it straight out. Early removal can minimize and often eliminate the chance of infection. After removing the tick, thoroughly clean the bite area and your hands with rubbing alcohol or soap and water.
Avoid using nail polish, petroleum jelly, or heat to make the tick detach from the skin. These methods are not effective and may increase the risk of disease transmission.
Watch for signs of illness such as rash or fever in the days and weeks following the bite, and see a healthcare provider if these develop. Be sure to let your healthcare provider know you were recently bitten by a tick.
Image. Four (3 female; 1 male) Ixodes scapularis (black-legged ticks) collected from two exposure sites. The male Ixodes scapularis is located at the top of the image with the three other ticks being female Ixodes scapularis. Photo courtesy of Jeff Hamik (DHHS).
In the video in the top link and in the following article I discuss why IGenex offers the best tests for Lyme, Bartonella, Babesia, Ehrlichia and Anaplasma versus other lab systems. IGenex has a variety of tests that it offers for each tick-borne infection. I take the guesswork out of determining which IGenex test is best – I tell you which test to get for each infection.
Watch why I prefer IGenex testing over Galaxy Labs, Vibrant Labs and DNA Connexions. In addition to what I describe in the video, I also prefer IGenex antibody tests over T cell activation tests, also called elispot tests, offered by Infectolab, Armin labs, and IGenex. T cell tests are not as accurate at finding tick borne infections as the IGenex testing techniques I recommend in the video.
Resources
Watch the video in the top link for a detailed list and test codes for the IGenex tests I recommend.
IGenex Tests I Recommend
In the video I recommend the following specific IGenex tests.
Lyme (Borrelia)
IGM and IGG Immunoblot – Test Code 325 and 335
Bartonella
IGM and IGG Immunoblot – Test Code 374 and 384
Babesia
B. microti IgM & IgG IFA – Test Code 200
B. duncani IgM & IGG IFA – Test Code 720
Babesia FISH – Test Code 640
Ehrlichia
HME (Ehrlichia chaffeensis) IgM & IgG IFA – Test Code 203
Anaplasma
HGA (Anaplasma phagocytophilum) IgM & IgG IFA – Test Code 206
Marty Ross, MD is a passionate Lyme disease educator and clinical expert. He helps Lyme sufferers and their physicians see what really works based on his review of the science and extensive real-world experience. Dr. Ross is licensed to practice medicine in Washington State (License: MD00033296) where he has treated thousands of Lyme disease patients in his Seattle practice.
Marty Ross, MD is a graduate of Indiana University School of Medicine and Georgetown University Family Medicine Residency. He is a member of the International Lyme and Associated Disease Society (ILADS) and The Institute for Functional Medicine.
Sorry to have to cancel support group for tomorrow (Dec.11, 2021) but we are getting at least 5 inches of snow and the Sparrow’s Nest is located in an area where the plows take a while to get there.
Have a Merry Christmas and we’ll take it up again in Jan. or Feb.
The simple answer is we don’t know. We know what we’re being told is in them, but there is increasing evidence of big variations in the quality and composition of different batches, which may or may not be deliberate.
Omicron is being used by governments and health authorities to mandate or coerce ever more people into receiving COVID-19 jabs.
It is imperative that sufficient information is given to potential vaccinees to allow properly informed consent. This article reviews key information that is not widely reported by governments, health authorities, vaccinators, the mainstream medical profession or the mass media.
Given that the most commonly used COVID-19 jabs rely on providing genetic information to the body to force it to produce a modified form of the spike protein, the jabs should not be represented as “vaccines.”
The mRNA jabs rely on genetic material that is significantly altered to generate mutant spike proteins that retain their prefusion conformity even after they get into cells. The lipid nanoparticleshave not been adequately studied for their safety.
The viral vector jabs by AstraZeneca and Johnson & Johnson rely on human fetal cell lines and the majority of the protein in the jabs may be from this source, rather than from the viral vectors themselves.
The spike protein is toxic in its own right and may induce adverse effects on the body whether it is generated from genetic information from jabs or from naturally-acquired infection.
Contaminants, deliberate or accidental, have been found in many vial specimens.
There are no substantive data to justify the ‘safe and effective’ claims often made for COVID-19 jabs, especially not in the face of omicron.
COVID-19 jabs, especially if given repeatedly every few months, will likely cause lasting negative impacts on immune system function so increasing the risk of a wide range of other diseases while increasing risks of adverse reactions.
Clear evidence has emerged that data used for “vaccine surveillance” by the UK Health Security Agency (formerly Public Health England) has been accidentally or deliberately misrepresented to infer outcomes among the jabbed are better than for those who decline.
There is little or no evidence that informed consent is being, or has been, offered at any time during the “pandemic.”
Before diving into the detail, here is Rob’s short, 10-minute video summary:
Freedom on trial
Liberalism in Europe is not only under threat. It has in some parts already been extinguished.
As the first European nation to mandate COVID-19 injections, Austria will criminalize those who refuse the injections. Germany has since followed suit. Greeks will need to pay their government a monthly fee of €100 every month if they remain jab-free.
On Monday night Queensland-based medical doctor, Robert Brennan, told those of us attending the weekly World Council for Health meeting that doctors in Australia who are de-licensed for speaking out about lockdowns, testing or injection risks will be criminally charged for impersonation if they continue to use their doctor title.
We also heard more about the quarantine camps that are being set up, how indigenous populations are being targeted and how sacred sites are being destroyed under powers granted by the supposed “emergency” status.
Layered over all of this is the emergence of the new SARS-CoV-2 variant, omicron, that is providing authorities in Europe and North America further justification to mandate or coerce people to be jabbed, most notably with so-called “boosters” (presently existing stock of injections based on the original Wuhan strain, Wuhan_Hu-1).
Policies designed to increase “vaccination” coverage and re-injection of previously injected people (use of “boosters”) are not based on any conclusive data or even mechanistic evidence on the likely effectiveness of this strategy.
Instead, they rely on now outdateddatafrom Israel and England that an mRNA booster jab can reduce the chances of people getting severely ill if infected.
Such data are entirely irrelevant to a situation we might be in in the coming weeks if omicron becomes dominant. That’s because it is increasingly clear that the vaccinal antibodies elevated by the jab do precious little to protect people, given that omicron’s multiple mutations in the receptor-binding domain of its spike protein prevent the antibodies from neutralizing it.
With all the coercion around us it is more important than ever that people really understand what the jabs are and how they work. We now know a little more about them compared with when they were first released on the public, so let’s have a closer look.
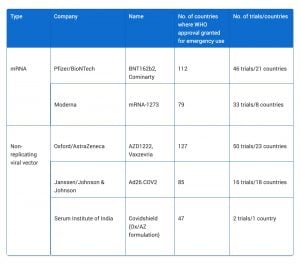
We will restrict our discussion to the two main types of “vaccines,” the mRNA and non-replicating viral vector types, respectively, that include 5 of the 8 World Health Organization-approved COVID-19 injections (Table 1).
Why the COVID-19 jabs shouldn’t be described as ‘vaccines’
In a recent video I explained why the main contenders (mRNA and viral vector types) should not be described as “vaccines” as they don’t meet the World Health Organization’s definition of being the administration of “agent-specific, but safe, antigenic components that in vaccinated individuals can induce protective immunity against the corresponding infectious agent.”
That’s because both these jab types don’t actually contain any antigenic components.
They contain genetic information that forces the body of the vaccinee to make antigenic components, namely the spike protein of the now no-longer-circulating Wuhan strain of SARS-CoV-2.
This is succinctly put by two eminent Austrian vaccine scientists from the Medical University of Vienna, Franz Heinz and Karin Stiasny, in their detailed review paper in a Nature journal, NPJ Vaccines, where they state that both types of “vaccine” “… do not contain the spike protein but provide genetic information for its biosynthesis in body cells of the vaccine.”
The U.S. Centers for Disease Control and Prevention (CDC) chose to revise its definition of a vaccine on Sept. 1 so the mRNA and viral vector jabs wouldn’t fall foul of it.
The vaccine definition changed from, “A product that stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease,” to the broader, more inclusive definition, “A preparation that is used to stimulate the body’s immune response against diseases.”
Other health authorities will undoubtedly follow suit as these new platforms become more and more widely used, and not just to target this one pathogen.
Such is the “let’s make it up as we go along” approach, we noticed, at the time of writing, the CDC has failed to update the “vaccine” entry on this glossary.
In their comprehensive review, Heinz and Stiasny refer to both the mRNA and viral vector type products as “genetic vaccines” — because they deliver genetic information to the body to make it synthesize the antigen. This is why the term “gene therapy products,” while having been branded repeatedly as conspiracy theory, is a reasonable description.
A paper published in the journal Genes and Immunity states that COVID-19 “vaccines” “… signify a breakthrough in the field of gene therapy, which has battled to achieve ordinary acknowledgement [sic] due to a large number of sceptical [sic] and conservative scientists and other claimed safety and translational concerns.”
The “vaccine” tag could be viewed as particularly misleading given the products are not capable of generating herd immunity as they don’t elicit a strong enough sterilizing response from antibodies to prevent infection and transmission.
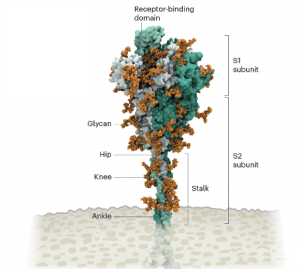
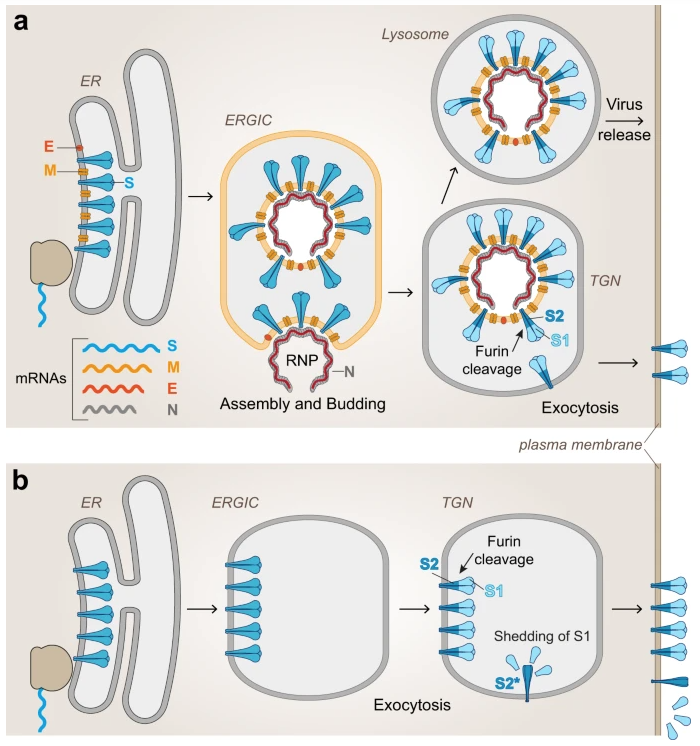
Furthermore, and contrary to what is inferred by health authorities, comprehensive research using a pseudovirus that expressed spike protein in Syrian hamsters conducted at the Salk Institute found that the spike protein (Fig 1) was far from harmless.
It appears to be toxic in its own right and it is the primary component that induces the vascular disease that develops in severe, life-threatening cases of COVID-19.
Figure 1. The spike protein of SARS-CoV-2, coated in sugar molecules (glycans), with receptor-binding domain in the upper, S1 subunit. Source:Nature, 2021
What might be in the vials that isn’t declared?
The simple answer is we don’t know. We know what we’re being told is in them, but there is increasing evidence of big variations in the quality and composition of different batches, which may or may not be deliberate.
Contaminants, described in mainstream media articles as “black particles,” have been foundin Japan as having “white floating matter” in the Pfizer jabs.
There has also been considerable speculation around the presence of other materials that do not appear on the official datasheets, notably reduced graphene oxide (rGO), in the injection products. Graphene is a single atom thick layer of bonded carbon atoms arranged in a hexagonal pattern.
It has many remarkable properties and has been extensively researched for its ability as a potential vaccine carrier and adjuvant.
Dr. Pablo Campra from Almeria University in Spain published a report on Nov. 2 claiming the detection of graphene in the Pfizer “vaccine.” An English translation can be found here and a video and more information here.
One group of anonymous scientists that appear to be based in Germany also reported at a conference finding graphene oxide in samples of all 5 of the WHO-approved “vaccines” considered here. Video material from the conference is readily accessible here.
More information and videos can be found on NotOnTheBeeb.
Contesting these highly controversial views are fact-checkers and mainstream news channels galore, as one would expect, but no serious analytical chemists.
Other than potential contaminants or hidden ingredients, there is also the possibility of being injected with nothingother thansaline.
What should be in the vials?
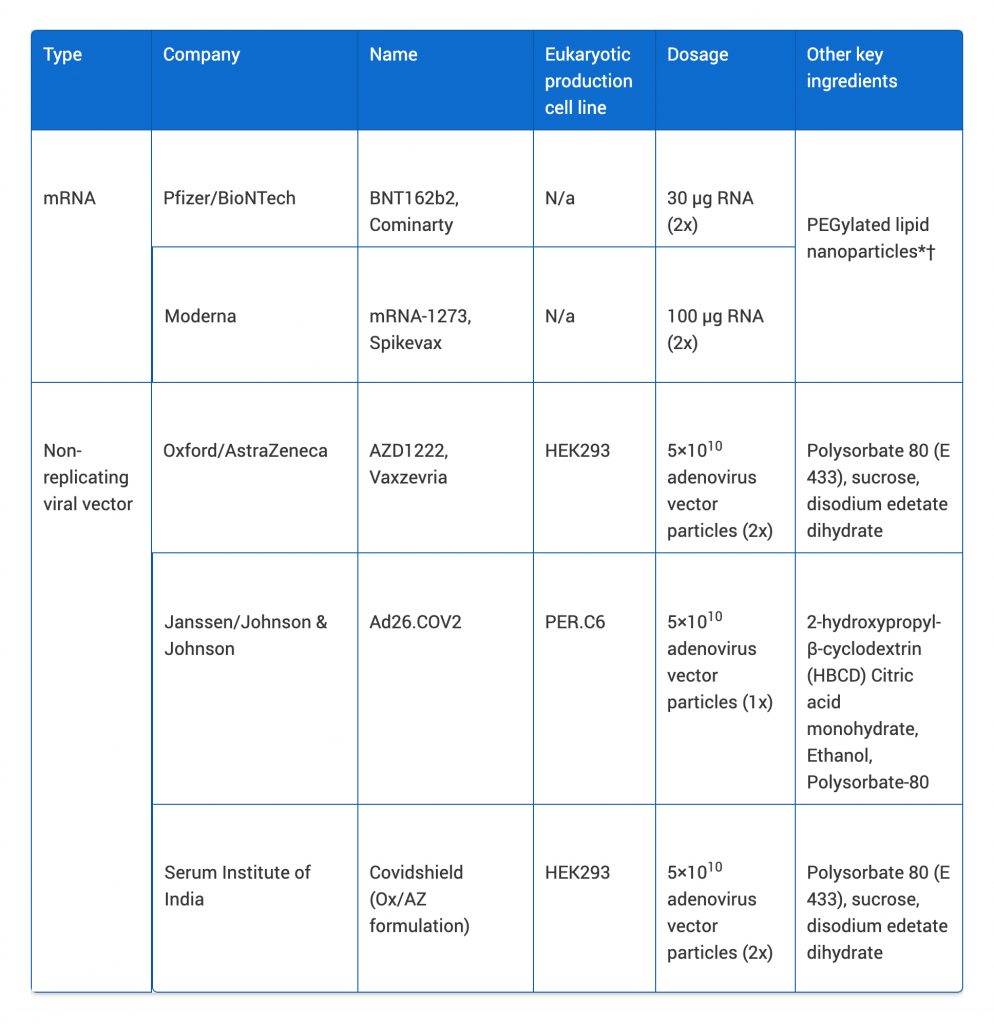
Let’s now look at what should be in the two types of “genetic vaccines,” summarized in Table 2.
Table 2. Claimed key ingredients in the 5 main WHO-approved COVID-19 injections
Both the Pfizer and Moderna jabs rely on similar technologies, namely mRNA (messenger RNA) that is a transient intermediary between genes and proteins. Companies like Moderna have been founded to exploit the potential to use this technology to get the body to produce an array of therapeutic proteins.
The Moderna jab relies on over three times as much mRNA as that of Pfizer. The messenger RNA (mRNA) is synthetic and now commoditized, encoding instructions that force the vaccinee’s cellular machinery to produce a modified form of the full-length SARS-CoV-2 protein.
The RNA sequence in each of the two mRNA “vaccines” is modified from the one used by the actual SARS-CoV-2 virus when it co-opts particular organelles in cells (endoplasmic reticulum and ribosomes) to translate the RNA that is converted to DNA to make its own spike proteins.
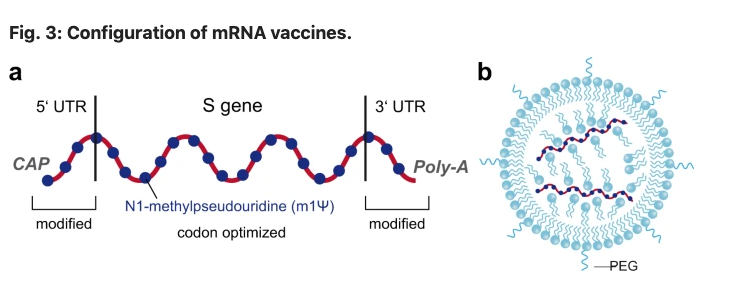
The uridine bases are all substituted for N1-methylpseudouridine to make the mRNA both evade the immune system and enhance protein production. The RNA strand is also “capped” and “tailed” with methylguanosine and poly-adenine, respectively, to further stabilize the mRNA and promote its translation.
The genetic instructions have yet another trick in store that’s at odds with what happens when hosts produce spike proteins from the RNA of beta-coronaviruses.
Two mutations that involve proline substitutions are built in at the beginning of the central helix of the spike protein to force it to stay in its “up” prefusion conformation — the state it’s in before it enters cells, after which it switches to the “down” position.
This unnatural “up” position forced upon it by the structurally stiff proline molecules is intended to increase the exposure of the spike protein to the host’s immune system. This way it increases the amount of neutralizing antibodies generated through the humoral (adaptive) immune response.
Each mRNA sequence is encased in a nanoparticle comprised of three main components: an ionizable phospholipid (phosphocholine), a sterol and a lipid-anchored polyethylene-glycol (PEG) molecule.
This is in effect a targeted drug delivery system that’s never been used at scale before — certainly not in efforts to treat a global population. The lipid nanoparticle (LNP) is multi-functional in that it protects the very fragile mRNA, reduces particle aggregation and exploits the tendency of cell membranes to draw the lipid (along with its mRNA cargo) into cells.
It is too early to fully understand how new-to-nature mRNA, modified spike proteins and lipid nanoparticles will affect those injected in the long term.
The likelihood is that these synthetic genetic “vaccines” that are injected directly into our bodies present a substantially greater risk to our species than the consumption of genetically modified foods that have been the subject of open scientific and public discourse for decades, with millions of consumers choosing to avoid their consumption.
Furthermore, it is now well known that the LNPs do not remain in the deltoid muscle injection sites, a fact that was revealed on disclosure of a Japanese biodistribution study used by regulators to grant Emergency Use Authorisation of the Pfizer jab.
The possibility of the mRNA being delivered to a young woman’s ovaries is more than a possibility. If it were to encode for the spike protein, toxicity or an immune response it could adversely affect fertility.
It is our view that there is no conclusive evidence that these “genetic vaccines” will not adversely affect fertility of either women or men. This risk is likely to increase with successive exposure to the jabs.
Viral vector type
While these “genetic vaccines” also get the body to produce the spike protein, they are more complex in nature. Unlike RNA jabs that are entirely synthetic in origin, they rely on mammalian cell cultures.
The adenoviral vectors are derived from chimpanzees and are subject to two key mutations: one that eliminates the E1 gene that stops the virus from replicating once in a vaccinee, the other that inserts the DNA of the adenovirus, a cloned gene that encodes for the full-length spike protein.
In the Oxford-AstraZeneca, Gamaleya and CanSino “vaccines,” viral vector particles are sourced from primary human fetal kidney cells (HEK293). The Janssen “vaccine” relies on human fetal retinal cells (PER.C6) (Table 2).
The process is complex and involves detergents and filters to remove free viral DNA and other debris. On all accounts, some 80% of the overall protein content of the jab may in fact be impurities from the fetal cell lines.Heinz and Stiasny separately calculated that the total protein content of the 50 billion adenoviral vector particles would amount to about 8 micrograms.
Yet a separate study found that the actual protein content was much higher, at between 35 to 40 micrograms. This additional amount (80%) must be related to protein-rich cellular impurities from the human fetal cells lines.
Have religious groups, vegetarians and vegans been informed of the presence of this human cell line debris?
Instead of the spike protein being made in the cytoplasm and endoplasmic reticulum outside the nucleus of the cell, the viral vectors rely on the adenoviral DNA entering the nucleus and transcribing itself to RNA before it can generate the spike protein.
The additional steps mean there are greater possibilities for aberrant genetic processes and transcription patterns, as shown by Almuqrin and colleagues. Animal experiments have shown that the adenoviral DNA, in contrast to mRNA, may remain viable and detectable for months following injection, this being one reason that viral vector jabs are less prone to waning immunity.
Do the ‘vaccines’ contain nanotechnology?
The LNPs in the Pfizer and Moderna jabs certainly are sub-100 nanometers in size. The adenoviral vector types rely on chimp adenoviruses that are typically at or just above this relatively arbitrary threshold.
However, given that size really does matter when it comes to changes in biological properties, the lack of robust safety data on the LNP-dependent mRNA jabs is of particular concern.
Equally concerning is that the public keeps being told there’s no nanotechnology in the jabs. Take a quote by Mark Lynas, a visiting fellow at the Alliance for Science and Cornell University, for example. He said, “None of the vaccines contain nanotechnology of any sort, let alone ‘transhumanism nanotechnology,’ which isn’t even a thing.”
Unfortunately, Mark Lynas, who writes for the New York Times, the Washington Post, the Wall Street Journal, the Guardian and CNN.com, is wrong on both counts. As we’ve already seen, the LNPs in the Pfizer and Moderna jabs are most certainly nanoparticles given their size distribution. The game is given away even in their name (LNPs)!
Then there’s the transhumanism claim. It is a thing — potentially a very real thing in the eyes of those who are pushing jabs as the only way out of this “pandemic.” For an introduction to transhumanism, you might want to dive into a somewhat conventional take on the subject via Wikipedia.
You might also want to check out the Fourth Industrial Revolution (Penguin, 2017), by founder of the World Economic Forum, Klaus Schwab. He describes this as a revolution “characterized by a fusion of technologies that is blurring the lines between the physical, digital, and biological spheres.”
Mark Lynas seems unaware of the insights of Schwab and other transhuman proponents on designer beings or humans with gene-edited artificial memories.
To create a robust and durable immune response, you ideally need trained innate immunity coupled with well-integrated adaptive immunity made up of an appropriate humoral (B cell-derived neutralizing antibodies) and cell-mediated (CD4+ and CD8+ T cells) response.
Spike protein-focused COVID-19 jabs largely elevate neutralizing antibodies that only partially neutralize the spike protein of the delta variant (even less so for omicron), while damaging both the innate immune and cell-mediated (T cell-based) adaptive immune response.
It’s a pandemic of the unvaccinated, right?
The UK Health Security Agency (UK HSA), formerly Public Health England, had a long-standing reputation, since the news of a new coronavirus in Wuhan broke in early 2020, as being one of the most comprehensive datasets for epidemiological study.
By October 2021 there was an emerging picture of catastrophic failure of the technology that so much of the industrialized world had appeared to pin its hopes on. That included data from the UK HSA.
It wasn’t long before one of many changes in reporting changed the pattern of the data. Initially, it was hard to understand why a process that had looked like increasing “vaccine” failure had suddenly turned itself around, with vaccinees appearing to have better outcomes in terms of cases, hospitalizations and deaths than the jab-free.
We started finding anomalies in the data on supposedly COVID-caused or all-cause mortality and immediately sensed that what might be going on was that the people who had been initially jabbed were being counted as jab-free.
Then we saw that Dr. Martin Neil and Prof. Norman Fenton of Queen Mary, University of London, along with a number of other colleagues, had done a stunning analysis of the latest UK HSA data.
Don’t expect a major journal to have published the work — as these have all been systematically blocking publication of any scientific views or analysis that contradicts the mainstream narrative. So you’ll have to read the paper, for now at least, on the preprint server Researchgate.
What the researchers found once they’d adjusted all-cause mortalities for likely miscategorizations of deaths was that the jabs had no benefits whatsoever. The first signal that something was wrong came when they saw consistent spikes in all-cause mortality deaths of specific age groups of the jab-free.
These coincided with the exact times that jabs were being rolled out to these age groups! How could the jab-free be affected? The answer appears to be: when the reportedly jab-free are actually the jabbed.
Their work is truly disturbing and concludes not only that there was almost certain systemic miscategorization of deaths between the different categories of unvaccinated and vaccinated, but also delayed or non-reporting of vaccinations, systemic underestimation of the proportion of unvaccinated, and/or incorrect population selection for COVID deaths.
It remains to be seen how the UK HSA will respond — but chances are the publication will either be ignored because it was not published in a peer-reviewed journal or Neil and Fenton will become targets for abuse and ridicule.
One thing is for sure: the UK HSA can no longer be trusted for its data quality.
Some numbers:
Over 5.8 million genome sequences of SARS-CoV-2 have been shared with GISAID.
55% of the world population has received at least one dose of a COVID-19 jab.
21 billion doses have been administered globally.
87 million are estimated to be administered every day.
Only 6.2% of people in low-income countries have received at least one dose.
Only 7.7% of people in the African continent have received at least one jab.
Figure 1. COVID-19 jab coverage by continent.Figure 2. COVID jab coverage in selected countries as of 6 December 2021.
Omicron update
Last week, we published a detailed article on the omicron variant that provided evidence suggesting that it was improbable that the variant originated in southern Africa. We figured it was politically expedient for Africa to be placed under huge pressure to increase its vaccination coverage (see Figs 1 and 2).
Will omicron successfully outcompete delta worldwide? Emerging data from the Tshwane District in South Africa, which has been described as the “global epicentre of Omicron Outbreak,” suggest omicron has been able to outcompete delta in this area and it appears likely this trend will be seen elsewhere.
Final word
This article scrapes the surface of what is known and not known about these gene therapy products widely misrepresented as “vaccines.” More than that, misrepresented as “safe and effective vaccines.”
Omicron will be used as a lever to jab more people. Recognizing that the “ardently jab-free” constitute many of the remaining so-called hesitants, countries like Austria, Germany, Canada and Australia are resorting to mandates or extreme coercion.
European Commission president Ursula von der Leyen has seized the opportunity afforded by omicron to get EU countries to debate and consider mandatory “vaccination” given her concerns over “low vaccination rates” in Europe.
The very least anyone should expect in the face of a virus that is now on par for lethality to circulating flu is the right to informed consent. That means informing each potential vaccinee what’s in the jabs, what’s known and not known about the greatest experiment ever conducted by, and on, humanity, and what other options there are that are known to effectively combat infection by SARS-CoV-2.
In short, that would mean that nothing you’ve read in this article should come as a surprise to anyone who has been jabbed. And we know from our many discussions, lectures, webinars and conversations around the world over these last 12 or so months, we are a million miles from achieving the required level of understanding for informed medical consent to have been offered.
To help improve the potential for properly informed consent, while allowing others to exercise their right of refusal in those countries that have yet to introduce mandates, please share this article as widely as you can. Thank you.
Please see: https://madisonarealymesupportgroup.com/2021/12/01/death-by-1000-cuts-graphene-hydroxide-in-covid-shots/ Well-known German chemist and one of the EU’s top graphene experts, Dr Andreas Noack died suddenly just hours after publishing this latest video about graphene oxide and graphene hydroxide. Graphene hydroxide molecules in the vaxx behave like nano razors that cut the epithelial lining of recipients’ veins, which he believes is the cause of blood clots and the sudden deaths observed in so many top athletes, lately. (See link for more)
#RealNotRare New Website for COVID-19 Vaccine Injured
by Brian Shilhavy Editor, Health Impact News
Dec. 9, 2021
A new website has been launched where people can tell their stories about being injured by one of the COVID-19 shots.
The name of the website is Real Not Rare, and they also have groups people can join, and it appears there is one group in each state.
They also have a “Take Action” section. Health Impact News subscribers will recognize quite a few of the people in their videos, as we have covered many of their stories here. (See link for article)
‘He Wants To Deny The Reality Of What He Said, What He Did!’: Ron Johnson Rips Fauci On Senate Floor
Dec 8, 2021
Senator Johnson has to correct mainstream media’s smear campaign on what he said and what he didn’t say. The spin-doctors are working hard to keep the spin going.
According to Robert F. Kennedy Jr., Fauci’s first instinct as national AIDS czar was to stoke contagion terror. Further, a fearmongering 1983 article in the Journal of the American Medical Association warned that AIDS could spread by casual contact, when it was almost exclusive to IV drug users and homosexuals. The world’s leading expert was “astounded” at Fauci’s “stupidity” as his statements did not reflect scientific knowledge.
A year later, Fauci had to acknowledge that health officials had never detected a case of the disease spread through “casual contact.”
The truth never stood in the way of a good money-maker, and Fauci’s been at it ever since – fearmongering, controlling, and claiming to embody science itself.
The Wall Street Journal won a Pulitzer Prize for its investigation of a deliberate HHS scheme to misrepresent AIDS as a general pandemic to secure greater public funding and financial support.
JUST IN: Senate Passes Resolution To Nullify President Biden’s Vaccine Mandate
Dec. 8, 2021
Wednesday evening, the Senate passed a resolution to nullify President Biden’s vaccine mandate, as Sens. Joe Manchin (D-W.Va.) and Jon Tester (D-Mont.) voted with their Republican colleagues against Biden’s measure. The vote came one day after a U.S. District Judge for the Southern District of Georgia, issued a 28-page rulingsuspending the mandate nationwide.
At the press conference, Sen. John Hoeven (R-N.D.), who sponsored the CRA said:
“We’re gonna pass this Congressional Review Act on a bipartisan basis in the Senate sending a very clear message, a very clear message, that this is an overreach by the Biden administration and we need to stop it. And I think in the House, there’s a very good chance that they will get enough people to sign on to this CRA to actually force a vote.
“Now, we understand that when that goes to the administration the president may well veto it, but we’ve sent a very clear bipartisan message on behalf of the people that this mandate needs to be stopped.”