Archive for the ‘Viruses’ Category

This Tick Bites, Clones Itself & Lays 2,000 Eggs

https://articles.mercola.com/sites/articles/archive/2019/08/10/new-tick-species.aspx

This tick bites, clones itself and lays 2,000 eggs

Analysis by Dr. Joseph MercolaFact Checked
new tick species

STORY AT-A-GLANCE

  • The Asian longhorned tick, first found in the U.S. in 2010, is now established in 11 states along the East Coast. The female is capable of laying 2,000 eggs without mating and an infestation may kill livestock from the blood loss
  • While ticks are known vectors of disease, thus far this species has not transmitted disease in the U.S. It is known to carry thrombocytopenia syndrome virus triggering human hemorrhagic fever, responsible for killing 15% of those the tick bites in Asia
  • The number of ticks and range in which they live have been expanding dramatically. Tickborne illnesses include Lyme disease, infecting 300,000 each year in the U.S., Rocky Mountain spotted fever, babesiosis, Powassan virus and Bourbon virus
  • As Lyme disease rates skyrocket, it’s important to do a quick check each time you come back inside after being in a grassy area or near trees and bushes; Lyme disease may be successfully treated when caught early. Your risk of infection is lower if you effectively remove the tick as soon as possible

While you might have thought a tick is an insect, it really belongs to the arachnid family, along with spiders, scorpions and mites.1 A tick survives by feeding on the blood of a host, growing from the size of an apple seed before food and swelling to more than double their size after feeding.2

Ticks are more active during the summer months, between March and November in the northern hemisphere. Most enjoy living in warm moist places, such as bushes, tall grasses and shrubs. Animals and humans get ticks while walking through these areas.3

Of the 899 species of ticks found throughout the world, only 90 reside in the U.S.,4 and just a select few are known to bite humans.5 After a tick gets on you, it doesn’t usually bite right away but will crawl around to find an acceptable place to latch on and feed. They look for soft, moist areas, including near your ears, hair, underarms and groin. They also like to settle under the waistband of your pants.6

After piercing your skin with its mouth, the tick inserts a tube to feed on your blood until it’s full. This may take up to two weeks.7 Tick bites are often painless so it may be difficult to tell if you’ve been bitten.

First new tick species in US in 50 years

In the past decade the U.S. has become home to a new species, the Asian longhorn. Dr. Gregory Poland from the Mayo Clinic says this tick represents the first time in 50 years a new species has made its way to the U.S.8 Because it is an emerging threat in the U.S. the CDC recommends that surveillance should include testing for pathogens.9

Ticks are associated with diseases in humans and animals. The Asian longhorn tick is known to carry human hemorrhagic fever caused by thrombocytopenia syndrome virus10 in Asia.11 This species has been found in 11 states, including:12

Arkansas Connecticut Kentucky
Maryland North Carolina New Jersey
New York Pennsylvania Tennessee
Virginia West Virginia

However, while it appears to be spreading across the eastern U.S., the CDC has reported there is currently no evidence these ticks have transmitted disease to humans or animals.13 Asian longhorned ticks in Asia carry a virus responsible for killing 15% of those they bite.14

In recent years, this population has spread to several Pacific Islands, Australia and New Zealand. Although some experts warn against extrapolating information to the Asian longhorn tick carrying serious viruses in the U.S.,15 this species also represents additional dangers to livestock and other animals.16

North Carolina State veterinarian Dr. Doug Meckes sent out information17 reminding farmers and pet owners to be vigilant with preventive measures to avoid ticks in their animals. Five cows in Surry County, North Carolina, recently died due to acute anemia triggered by a tick infestation.18


Asian tick sounds like something from a horror film

Samples from the cows confirmed the ticks were Asian longhorn. According to Meckes, this was the fourth confirmed case since 2018 and the first in 2019.19 One young bull presented to the diagnostic lab for necropsy had 1,000 ticks. As described in this short video, the ticks are aggressive biters, feeding on both animals and humans.

The first identified case, in 2010, involved a white-tailed deer from West Virginia.20 In other reports the tick was found in New Jersey in 201721 when a woman discovered them on her sheep.22

The first recorded human bite was reported by a 66-year-old man from Yonkers, New York, in June 2018. He removed the tick from his leg and subsequently took it to the Lyme Disease Diagnostic Center in Westchester County for testing.23 After confirmation that it was the Asian longhorned tick, sampling was done near his home and nearby park, finding 90 ticks.24

A unique characteristic of this species is its ability to reproduce quickly and prolifically without mating.25 The female does not need a male to lay as many as 2,000 eggs at a time.26 The threat to livestock may be significant. A dairy cow may experience a 25% drop in milk production after becoming a host.27

As the species continues to multiply and spread, it is conceivable millions of animals could be exposed.28 A study published in the Journal of Medical Entomology29 developed a model demonstrating the wide area of North America where favorable conditions for the Asian longhorned tick may exist.30

Study author Ilia Rochlin, Ph.D., is a professor at Rutgers University. She believes the adaptability of this species means it has the potential to spread across the U.S. and southern Canada.31 The ability of the tick to reproduce without mating may make it extremely hard to control. Rochlin said,32 “In practice, it’s impossible to eradicate this species.”

Tick population rising, along with the diseases they carry

The number of all ticks and the range in which they live have both increased. According to the CDC,33the lone star tick has expanded from the southeastern U.S. into the northern and Midwestern states. The range of the black-legged tick, responsible for many cases of Lyme disease, has more than doubled in the past 20 years. Between 1993 and 2012, the number of counties in the U.S. at high risk for Lyme disease rose by more than 300%.34

Although the Asian longhorned does not yet carry disease, many other ticks do. The CDC announced it will begin monitoring the population and diseases ticks carry as the number of people diagnosed with diseases carried by ticks has more than doubled. Anna Perea, from the CDC’s Division of Vector-Borne Diseases, commented on the new monitoring:35

“For the first time this year, the CDC is funding states to conduct widespread surveillance of ticks and the pathogens they can transmit, in addition to funding human disease surveillance and education and prevention. Taken together, the data can help define areas where ticks are spreading, the infectious pathogens that they carry, and where risk of tick-borne disease is increasing.”

Tick-borne diseases may include Lyme disease, suspected to affect nearly 300,000 people each year.36 Rocky Mountain spotted fever, anaplasmosis, ehrlichiosis and babesiosis are also spread by ticks. New infections have also been detected, including the Bourbon virus, Heartland virus37 and Powassan virus.38 Ticks spread disease by virtue of the way they find nutrients.

In order to transition through life stages, ticks must have a blood meal to survive.39 Through the process of hatching from the egg, going through the larvae, nymph and adult stage, they may live up to three years. If unable to find a suitable host, they die.40 As they ingest blood, they also suck up any pathogens from the host and spread it to their next host.

Lyme disease rates skyrocketing

The rising number of ticks and their spreading habitat has meant an increase in the number diagnosed with tick-borne diseases. Lyme disease is the most prevalent of those conditions. CDC41data show that in 1997, there were 12,801 confirmed cases which more than doubled to 29,513 confirmed and 13,230 probable cases in 2017.

Data also show more males than females are affected, with the age group of 5 to 9 years having the greatest number affected. The disease is most frequently diagnosed in the months of June and July.42One study from researchers at Carnegie Mellon University43 called the rising epidemic of Lyme disease a “Ticking Bomb.”

These researchers found a relationship between rising temperatures and the incidence of Lyme disease, predicting the number of people diagnosed may rise by more than 20% by midcentury.44 In addition to temperature playing a role in the rising number of tickborne illnesses, researchers find smaller patches of forest may also increase the number of Lyme carrying ticks.

White-footed mice, also known to carry Lyme disease,45 are often the first blood meal for the larval tick.46 In smaller forest fragments measuring less than 5 acres, the mice are abundant because smaller areas of forest support fewer predators.47

Felicia Keesing from Bard College, New York, and other researchers have found an average of three times the number of ticks in a three-acre forest fragment than in larger areas. As many as 80% of the arachnids in the smallest patches were infected.48

Challenges of diagnosis and treatment for Lyme disease

Although the disease has been around for thousands of years, the medical community only began describing it in the 1970s. An autopsy of a 5,300-year-old mummy found the presence of the bacteria and a German physician first wrote about symptoms more than 130 years ago.49

Lyme disease is caused by a bacterium, which when left untreated may spread to the joints, heart and nervous system. The bacterium, Borrelia burgdorferi, may be treated successfully when found early.50 However, while commonly acknowledged now, Lyme disease has historically been a challenge to diagnose.

CNN reported51 on a U.S. Air Force enlisted man, Ruben Lee Sims, who was voted the “top enlisted management analyst of the year” in 1977. Only seven years later he was discharged and labeled a hypochondriac when the military was unable to diagnose Lyme disease. Misdiagnosed for more than three decades, he now shares his story to help others.

Early symptoms resemble the flu and the bullseye rash is not always recognized.52 Within 30 days of being bitten, you may experience fever, chills, fatigue and muscle and joint aches. Up to 80% of those infected will have a rash resembling a bull’s-eye target at the site of the tick bite, which gradually reaches 12 inches or more across.53

Later on, signs of infection may include severe headache and neck stiffness, a spreading rash on other areas of your body, severe arthritis pain and swelling, facial palsy, heart palpitations and possibly an irregular heartbeat.54 If left untreated, you may develop inflammation of the brain and spinal cord. This can lead to pain, numbness and tingling in the hands and feet as well as problems with short-term memory.55

Some people have seen multiple physicians and undergone a plethora of tests before being given a correct diagnosis.56 Early tests may not detect antibodies to the bacteria as it may take several weeks to rise to detectable levels.

Since early treatment is most effective57 some physicians begin treatment before offering a definitive diagnosis.58 The Lyme antibody test looks for exposure to the bacteria, but it may take your immune system several weeks to produce measurable levels. This can result in a false negative test with early testing.59

You’ve found a tick — now what?

Anytime you’re out in grassy areas or around trees and bushes do a quick skin check when you get back inside. Look for small brown to black spots or crawling, eight-legged arachnids. If the tick is unattached to your skin and has not fed, slip a sheet of paper under it and seal it in a container with alcohol.

However, if it’s become attached to your skin, it’s important to remove it to lower your risk of infection. While there are several tools on the market you may want to consider, a set of fine-tipped tweezers will also do the job. According to the CDC you should:60

  • Grasp the tick close to the skin’s surface.
  • Using steady and even pressure, pull the tick upward. Twisting or jerking may cause the mouth parts to remain in the skin. If the mouth parts are left behind, try to remove them with clean tweezers. If you are unable to remove them easily, allow the skin to heal.
  • Clean the area and your hands thoroughly with rubbing alcohol or soap and water.
  • Do not crush the tick as this forces blood and pathogens into your body.61

Avoid using techniques such as painting the tick with nail polish or covering it with petroleum jelly. This will not suffocate it. Likewise, poking it or using heat to make it detach are not recommended.62

Once a tick has been safely removed drop it in a sealed container with alcohol and take it to your health department or Lyme disease center for identification. Keep an eye on the area for the next several weeks. If you develop a rash or flu-like symptoms, see a doctor who’s experienced in treating Lyme disease.

_________________

**Comment**

A few points for consideration:

  1. While human infection from the Asian Long-horned tick has not been documented in the U.S., it may still be happening. Remember, in Asia, it causes illness that KILLS 15% of those whom contract it. Don’t take this lightly.
  2. These “new” diseases aren’t new and there are plenty more out there that aren’t even named yet. While authorities are collecting climate data, which is erroneous to this issue, patients continue to suffer and yes, DIE, due to lack of good science and flat-out neglect:  https://madisonarealymesupportgroup.com/2018/11/07/ticks-on-the-move-due-to-migrating-birds-and-photoperiod-not-climate-change/
  3. The white-footed mouse is not the sole perp, in fact according to independent Canadian tick researcher John Scott, established tick populations exist in areas devoid of the mouse:  https://madisonarealymesupportgroup.com/2018/08/13/study-shows-lyme-not-propelled-by-climate-change/. Many mammals transport ticks – particularly birds, and reptiles play a role, especially down South:  https://madisonarealymesupportgroup.com/2019/01/25/bb-in-s-italian-ectoparasites-reptiles/  Please read comment after article as well.  https://madisonarealymesupportgroup.com/2019/01/14/python-covered-with-more-than-500-ticks-rescued-in-australia/
  4. “Rising temperatures” have nothing to do with this. In fact, research has shown warmer winters are actually lethal to black legged ticks. They also survive in 3 degrees for 24 hours:  https://madisonarealymesupportgroup.com/2016/01/20/polar-vorticks/
  5. Unfortunately, Ruben Lee Sims’ story is all too common:   https://madisonarealymesupportgroup.com/2017/09/21/its-all-in-your-head-untilfinally-a-lyme-diagnosis/, https://madisonarealymesupportgroup.com/2019/04/22/its-just-crazy-why-is-lyme-disease-treatment-so-difficult-to-find-in-mississippi/, https://madisonarealymesupportgroup.com/2016/09/24/arkansas-kids-denied-lyme-treatment/….I could literally go on and on with such examples.
  6. Regarding what to do when you find an attached tick – again – insanity is doing the same thing over and over and expecting different results. Since everyone admits catching this early makes all the difference, why are people still telling people to “wait and see?”  No, do NOT wait and see! By that point it will be TOO LATE!  Treat this as seriously as a heart attack and treat it prophylactically if you are bitten by a tick. It’s not worth the risk, trust me.  A month’s worth of cheap antibiotics are worth it. Take probiotics, avoid sugar, and live to see another day, or take your chances, spend $15K a year for potentially ever, and hope you can keep working to keep the lights on, as well as keep your family intact. People STILL are not “getting” the seriousness of this. Here’s better advice on what to do if you are bitten:  https://madisonarealymesupportgroup.com/2019/05/25/help-ive-been-bitten-by-a-tick-now-what/ and go here for better info on prevention:  https://madisonarealymesupportgroup.com/2019/04/12/tick-prevention-2019/

 

Military Eyes Bug-Repellent Coating To Replace Permethrin in Uniforms

https://www.military.com/daily-news/2019/08/02/military-eyes-bug-repellent-coating-replace-permethrin-uniforms.html?

Military Eyes Bug-Repellent Coating to Replace Permethrin in Uniforms

Army Reserve Spc. Susan Muir and Army Reserve Sgt. Sean Tynes, a preventive medicine specialist, trap and draw ticks for testing of Rocky Mountain spotted fever and Lyme disease at Lake Hurst at Joint Base McGuire-Dix-Lakehurst, June 11, 2015. (U.S. Army/Spc. Samuel Al-Nimri)

The Defense Department is exploring a replacement for permethrin, the bug repellent and insecticide that is soaked into most military combat uniforms.

Officials declined to provide details on the new product, which is still being tested and evaluated, but said it may be used “at a lower toxicity level” and last a uniform’s lifetime. Permethrin lasts through about 50 launderings.

“We are looking at new chemistries,” said Lt. Cmdr. James Dunford, a medical entomologist at the Uniformed Services University of the Health Sciences in Bethesda, Maryland, speaking with reporters on a call Wednesday to promote the Defense Health Agency’s “Bug Week.”

“We are working on a new chemical … that would also include environmental factors like sweat, ultraviolet light and abrasion, so we are trying to make it last longer,” added Dr. James English, a global health specialist with the Uniformed Services University, addressing several of the shortcomings of permethrin that cause it to lose its bug-fighting powers.

“DoD is always actively engaged in testing new products, methodologies and technologies to enhance the efficacy of the vector-borne disease protection we can provide for our service members. Any time we find a better tool … we are going to add it to our tool box,” English said.

The Pentagon’s marked its second annual “Bug Week” July 27 to Aug. 3 to raise awareness of the slew of disgusting diseases carried by bugs and provide information to service members and their families on preventing illness.

According to the Defense Department, Lyme disease continues to be the top domestic threat to U.S. troops when it comes to bug-borne diseases, with illnesses carried by mosquitoes being the major challenge overseas.

“Outdoor activities like farming, camping and military training exercises in grasslands or edges of the forest increase chances of these pathogens’ transmission,” Army Maj. Elizabeth Wanja of the Uniformed Services University for Health Sciences said in a news release.

The most ubiquitous vector-borne disease in the United States by far is Lyme, with more than 30,000 diagnosed cases of Lyme reported to the Centers for Disease Control and Prevention each year and estimates of infections as high as 300,000 annually.

From 2010 to 2016, the U.S. armed forces saw 721 confirmed cases and 3,266 suspected cases of Lyme, as well as 64 cases of Rocky Mountain spotted fever and 14 cases of ehrlichiosis — all carried by ticks.

Also from 2010 to 2016, the services saw 346 confirmed and 475 suspected cases of malaria, 86 cases of dengue, 78 cases of chikungunya and 52 cases of Zika.

Other diseases on the rise in the U.S. include the rare Powassan virus, with 33 cases across the U.S. in 2017. This illness, carried by the deer tick, affects the human nervous system, causing respiratory complications and brain swelling. And alpha-gal syndrome, which can be caused by a bite from the lone star tick, can cause a red meat allergy in humans.

To prevent infections, the Defense Department takes a “three-pronged approach,” English said.

This includes proper wearing of uniforms — “tucking your pants into your boots, long sleeves” — caring for uniforms so they maintain their insecticide impregnation and taking preventive medications for diseases such as malaria before and during deployment to endemic countries.

Officials say the key to preventing infection off-duty is to maintain similar practices. They recommend using an effective repellent containing DEET, IR3535 or oil of lemon eucalyptus, all of which the CDC classifies as providing “reasonably long-lasting protection,” wearing proper clothing (again, long pants and long sleeves) and conducting tick checks after being in grassy areas and woods.

“The more time you spend outside, the more likely you are to pick up ticks. The best way to prevent it is to not get them in the first place,” English said.

According to English, ticks need roughly 24 hours to transmit a disease, so if one is found on the body, remove it carefully, using tweezers to grasp it and pull away gently and “straight out in slow motion.”

Do not, he said, use a hot match to make it release or smother it with Vaseline or baby oil.

“None of that works and, in fact, all that does is make them regurgitate if they get trauma like that, and it can either [lead to] an infection or the pathogen can be vomited when it otherwise it wouldn’t,” he said.

To prevent mosquito-borne illnesses, deprive them of their breeding grounds, Dunford added. This means eliminating all standing water in yards and using environmentally friendly mosquito dunks in bird baths or fountains. Being aware of the potential for standing water has been especially important in a year that has seen extensive flooding at military bases, he said.

“As far as mosquitoes go, aedes aegypti [mosquitoes that carry dengue, Zika and other tropical diseases] don’t fly more than a block in their entire life, so if you are getting bit at your home in the daytime, they probably are breeding within a block of your home … even in something as small as a bottle cap full of water,” English said.

Again, wear protective clothing and use repellents, he added.

While several of these diseases are curable, many are not, and they not only pose a threat to readiness, given the symptoms and related down-time, they can carry long-term consequences.

In July, military researchers wrote a case study in the journal Military Medicine about a 24-year-old Army officer and U.S. Military Academy graduate who was discharged after exposure to Lyme disease resulted in chronic inflammation of his knees, rendering him unfit for duty.

In 2016, the Military Health System confirmed 156 cases of Zika, including five cases in pregnant beneficiaries. The Zika virus can cause severe birth defects in children, including microcephaly, a condition where a baby’s head is much smaller than normal that is linked to developmental and intellectual delays, seizures and other disabilities.

The Defense Department’s relationship with ticks made headlines earlier this month, thanks to an amendment to the proposed House national defense authorization act that seeks to determine whether the Pentagon has experimented with ticks and insects to spread disease.

Sponsored by Rep. Christopher Smith, R-New Jersey, the legislation would require the Pentagon inspector general to investigate the “possible involvement of DoD biowarfare labs in the weaponization of Lyme disease in ticks and other insects” from 1950 to 1975.

Smith said he was inspired to write the amendment based on several books, including “Bitten: The Secret History of Lyme Disease and Biological Weapons” by Kris Newby, that claim DoD research may have played a role in spreading Lyme.

“My amendment tasks the DoD Inspector General to ask the hard questions and report back,” Smith said in a news release.

Defense officials said Wednesday that the goal in studying Lyme and other tick-borne diseases is to prevent them.

Department spokeswoman Heather Babb said that the Pentagon cannot comment on Smith’s proposed legislation. But, she added, “DoD takes extreme care in all of our research programs to ensure the protection of our personnel and the community.”

— Patricia Kime can be reached at Patricia.Kime@Military.com. Follow her on Twitter @patriciakime.

__________________

**Comment**

First, Powassan is not rare:  https://madisonarealymesupportgroup.com/2019/07/27/maine-resident-contracts-rare-tick-borne-illness-that-can-cause-brain-infections-death-state-cdc-says-but-its-not-rare/  Please read comment after article.

For more on the bioweaponization issue:  https://madisonarealymesupportgroup.com/2019/08/04/lyme-disease-amendment-passes-house-tells-dod-ig-to-investigate-the-bioweaponization-of-ticks/

https://madisonarealymesupportgroup.com/2019/07/19/biological-warfare-experiment-on-american-citizens-results-in-spreading-pandemic/

Regarding the DoD “taking extreme care to ensure our protection,”  https://madisonarealymesupportgroup.com/2019/07/31/tick-expert-admits-to-working-on-ticks-dropping-them-out-of-airplanes/  Dropping tweaked lab ticks from airplanes is not being careful!

More on permethrin:  https://madisonarealymesupportgroup.com/2018/05/27/study-conforms-permethrin-causes-ticks-to-drop-off-clothing/

https://madisonarealymesupportgroup.com/2019/06/16/study-shows-effectiveness-of-factory-treated-permethrin-impregnated-clothing-works/

Bug sprays: https://madisonarealymesupportgroup.com/2019/07/01/what-you-need-to-know-about-bug-sprays/

Tick Prevention: https://madisonarealymesupportgroup.com/2019/04/12/tick-prevention-2019/
 

CCHF in Republic of Sudan: A Retrospective Study

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6645580/

. 2019 Jul; 13(7): e0007571.
Published online 2019 Jul 10. doi: 10.1371/journal.pntd.0007571
PMCID: PMC6645580
PMID: 31291242

Detection of Crimean-Congo Haemorrhagic Fever cases in a severe undifferentiated febrile illness outbreak in the Federal Republic of Sudan: A retrospective epidemiological and diagnostic cohort study

Hilary Bower, Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Supervision, Visualization, Writing – original draft, Writing – review & editing,1,2,‡*Mubarak El Karsany, Conceptualization, Investigation, Methodology, Project administration, Resources, Supervision, Writing – review & editing,3,4,‡ Mazza Alzain, Data curation, Formal analysis, Investigation, Writing – review & editing,5Benedict Gannon, Data curation, Investigation, Methodology, Resources, Supervision, Writing – review & editing,1,6Rehab Mohamed, Data curation, Investigation, Writing – review & editing,4 Iman Mahmoud, Data curation, Investigation, Writing – review & editing,4 Mawahib Eldegail, Data curation, Investigation, Writing – review & editing,4Rihab Taha, Data curation, Investigation, Writing – review & editing,4 Abdalla Osman, Project administration, Writing – review & editing,4 Salim Mohamednour, Conceptualization, Methodology, Writing – review & editing,5,¤aAmanda Semper, Conceptualization, Data curation, Methodology, Resources, Supervision, Writing – original draft, Writing – review & editing,7 Barry Atkinson, Investigation, Methodology, Writing – review & editing,7,¤b Daniel Carter, Investigation, Methodology, Writing – review & editing,7 Stuart Dowall, Investigation, Methodology, Writing – review & editing,7 Jenna Furneaux, Investigation, Methodology, Writing – review & editing,7 Victoria Graham, Investigation, Methodology, Writing – review & editing,7 Jack Mellors, Investigation, Methodology, Writing – review & editing,7Jane Osborne, Investigation, Methodology, Writing – review & editing,7 Steven T. Pullan, Investigation, Methodology, Writing – review & editing,7 Gillian S. Slack, Investigation, Methodology, Writing – review & editing,7 Tim Brooks, Conceptualization, Methodology, Writing – review & editing,7 Roger Hewson, Methodology, Writing – review & editing,7Nicholas J. Beeching, Conceptualization, Writing – review & editing,8 Jimmy Whitworth, Conceptualization, Writing – review & editing,1,2 Daniel G. Bausch, Writing – review & editing,1,6,9 and Tom E. Fletcher, Conceptualization, Data curation, Formal analysis, Investigation, Methodology, Project administration, Resources, Supervision, Visualization, Writing – original draft, Writing – review & editing8,‡
Darci Smith, Editor

Abstract
Background

Undifferentiated febrile illness (UFI) is one of the most common reasons for people seeking healthcare in low-income countries. While illness and death due to specific infections such as malaria are often well-quantified, others are frequently uncounted and their impact underappreciated. A number of high consequence infectious diseases, including Ebola virus, are endemic or epidemic in the Federal Republic of Sudan which has experienced at least 12 UFI outbreaks, frequently associated with haemorrhage and high case fatality rates (CFR), since 2012. One of these occurred in Darfur in 2015/2016 with 594 cases and 108 deaths (CFR 18.2%). The aetiology of these outbreaks remains unknown.

Methodology/Principal findings

We report a retrospective cohort study of the 2015/2016 Darfur outbreak, using a subset of 65 of 263 outbreak samples received by the National Public Health Laboratory which met selection criteria of sufficient sample volume and epidemiological data. Clinical features included fever (95.8%), bleeding (95.7%), headache (51.6%) and arthralgia (42.2%). No epidemiological patterns indicative of person-to-person transmission or health-worker cases were reported. Samples were tested at the Public Health England Rare and Imported Pathogens Laboratory using a bespoke panel of likely pathogens including haemorrhagic fever viruses, arboviruses and Rickettsia, Leptospira and Borrelia spp. Seven (11%) were positive for Crimean-Congo haemorrhagic fever virus (CCHFV) by real-time reverse transcription PCR. The remaining samples tested negative on all assays.

Conclusions/Significance

CCHFV is an important cause of fever and haemorrhage in Darfur, but not the sole major source of UFI outbreaks in Sudan. Prospective studies are needed to explore other aetiologies, including novel pathogens. The presence of CCHFV has critical infection, prevention and control as well as clinical implications for future response. Our study reinforces the need to boost surveillance, lab and investigative capacity to underpin effective response, and for local and international health security.

Author summary
The Federal Republic of Sudan has had at least 12 outbreaks of febrile illness of unknown cause associated with symptoms of haemorrhage and high case fatality rates since 2012. Outbreaks without clear diagnosis are concerning, particularly in countries such as Sudan where a range of high consequence diseases, including viral haemorrhagic fevers, are endemic or epidemic, and local laboratory capacity is limited. We transferred historical samples stored in the National Public Health Authority from one of these outbreaks that occurred in Darfur 2015–2016 to the Public Health England Laboratory at Porton, UK, and tested them against a wide range of infectious diseases to try to identify the cause, and to help the Sudanese Federal Ministry of Health to develop and target their limited laboratory capacity. We found that Crimean-Congo Haemorrhagic Fever was an important cause but not the only source of cases in this outbreak. This has implications for prevention and control as well as for treating cases. Our study also highlighted the need for future studies to explore other possible causes, including new pathogens, and reinforced the need to boost surveillance, lab and investigative capacity for more timely and complete outbreak response.

_______________

More on CCHF: https://madisonarealymesupportgroup.com/2019/07/03/deadly-ticks-carrying-ebola-like-congo-fever-found-in-uk-after-spreading-across-europe/

https://madisonarealymesupportgroup.com/2018/08/19/monster-ticks-found-in-germany-threaten-europe-with-deadly-disease-crimean-congo-fever/

https://madisonarealymesupportgroup.com/2019/05/23/crimean-congo-hemorrhagic-fever-outbreak-in-africa/

H. rufipes on the UK horse:  https://madisonarealymesupportgroup.com/2019/04/11/african-tick-found-on-untraveled-u-k-horse/

https://madisonarealymesupportgroup.com/2018/06/14/crimean-congo-the-asian-ebola-virus/


Not to be confused with SFTS, CCHF is often treated with Ribavirin: http://infectious-diseases-and-treatment.imedpub.com/research-advances-on-epidemiology-of-severefever-with-thrombocytopenia-syndrome-asystematic-review-of-the-literature.php?aid=17986

Ribavirin is reported to be effective for treating Crimean-Congo Hemorrhagic Fever (CCHF) infections and hemorrhagic fever with renal syndrome, but it is still inadequate to judge the effect of ribavirin on SFTS patients because of the study limitation without adequate parameters were investigated [45]. Host immune responses play an important role in determining the severity and clinical outcome in patients with infection by SFTSV

What is Vaccine Shedding?

https://articles.mercola.com/sites/articles/archive/2019/07/23/what-is-vaccine-shedding.aspx?

What is vaccine shedding?

Analysis by Dr. Joseph MercolaFact Checked
vaccine shedding

STORY AT-A-GLANCE

  • Live viral vaccines contain a weakened (or attenuated) version of the virus
  • Live attenuated viral vaccines can cause vaccinated persons to shed vaccine strain virus for a period of days, weeks or months, potentially infecting others and leading to symptoms of the very disease the vaccine was intended to prevent
  • One recent study revealed not only that influenza virus may be spread via simple breathing (i.e., no sneezing or coughing required) but also that repeated vaccination increases the amount of virus released into the air
  • Individuals who had gotten a flu vaccination in the current and previous season had 6.3 times more aerosol shedding of influenza virus than those who had received no vaccination in those two seasons
  • Due to a lack of active surveillance and testing, there’s no way to know how often vaccine-strain live virus shedding and disease transmission actually occurs

When you’re infected with a virus that causes an illness, that virus is shed in your saliva and other bodily fluids, and sometimes also via skin lesions. This means that a person who comes into direct contact with the shed virus may also become infected. The same holds true for live attenuated viral vaccines.

While inactivated vaccines use a killed version of the pathogen, live viral vaccines use a weakened (or attenuated) version of the virus. Typically, the live virus used in vaccine production is passed through a living cell culture or other host, such as chicken embryo, many times over until it becomes weakened to a point that it’s not likely to make you sick when it’s injected or, in the case of live oral vaccines, swallowed.

That being said, a live vaccine strain virus is still active and strong enough to trigger an inflammatory response in your body, prompting the creation of vaccine-acquired antibodies. There are a few problems with this, such as the possibility that the weakened vaccine-strain virus can revert to virulence, leading to serious complications identical or similar to complications of the natural disease the vaccine is supposed to prevent in the vaccinated person.1

Another noted problem is that the person who is given a live attenuated viral vaccine can asymptomatically shed and transmit vaccine-strain virus for a period of days, weeks or months and potentially infect close contacts, who can also experience symptoms of the very disease the vaccine was intended to prevent.

Live flu vaccine associated with increased viral shedding in exhaled breath

The possibility of vaccine strain viral shedding takes on renewed importance in the case of the government’s strong recommendation for annual flu vaccination. The U.S. Centers for Disease Control and Prevention’s (CDC) Advisory Committee on Immunization Practices (ACIP) recommends annual influenza vaccinations for everyone 6 months and older.

In the 2018 to 2019 flu season, CDC officials recommended health care providers “use any licensed, age-appropriate influenza vaccine (inactivated influenza vaccines (IIV), recombinant influenza vaccine (RIV), or live attenuated influenza vaccine (LAIV4) with no preference expressed for one vaccine over another.”2

The live influenza vaccine FluMist, which is approved for nonpregnant women as well as anyone aged 2 to 49 years, is administered in the form of a nasal spray.

While the CDC states that the live type A and B vaccine strain influenza viruses in FluMist are too weak to actually give recipients influenza, research has raised some serious doubts that this is the case. One recent study revealed not only that influenza virus may be spread via simple breathing (i.e., no sneezing or coughing required) but also that repeated vaccination increases the amount of influenza virus released into the air.3

“Self-reported vaccination for the current season was associated with a trend toward higher viral shedding in fine-aerosol samples; vaccination with both the current and previous year’s seasonal vaccines, however, was significantly associated with greater fine-aerosol shedding … ,” the researchers stated.4

What’s more, individuals who had been vaccinated in the current and previous season had 6.3 times more aerosol shedding than those who had received no vaccination in those two seasons. The researchers concluded:5

“The association of current and prior year vaccination with increased shedding of influenza A might lead one to speculate that certain types of prior immunity promote lung inflammation, airway closure and aerosol generation … If confirmed, this observation, together with recent literature suggesting reduced protection with annual vaccination, would have implications for influenza vaccination recommendations and policies.”


Virus shedding is common following FluMist — and can transmit flu

MedImmune, the company that developed FluMist, is aware that the vaccine sheds vaccine-strain virus. In its prescribing information, they describe a study on the transmission of vaccine-strain influenza viruses from vaccinated children to nonvaccinated children in a day care setting.

In 80 percent of the FluMist recipients, at least one vaccine-strain influenza virus was isolated anywhere from one to 21 days following vaccination. They further noted, “One placebo subject had mild symptomatic Type B virus infection confirmed as a transmitted vaccine virus by a FluMist recipient in the same playgroup.”6

Another MedImmune study revealed that 89 percent of babies under 2 years who received FluMist shed vaccine-strain influenza virus, as did 20 percent of adults. The most virus was shed two to three days following vaccination, continuing for up to 11 days.7

While the CDC claims vaccine-strain virus shedding, and subsequent transmission of disease, is rare, they have also stated that people with a weakened immune system, or those who will be caring for someone with a weakened immune system within seven days of vaccination, should not receive the live attenuated influenza vaccine due to the “theoretical” risk that the recently vaccinated person could shed and transmit the vaccine-strain virus to immunocompromised individuals.

That being said, there’s no way to know for sure how often vaccine-strain live virus shedding and disease transmission actually occurs. Barbara Loe Fisher, cofounder and president of the National Vaccine Information Center (NVIC), wrote a special report, The Emerging Risks of Live Virus and Viral Vectored Vaccines: Vaccine Strain Virus Infection, Shedding and Transmission, which contains over 200 references and delves into virus shedding and vaccine virus shedding. She noted:8

“There is no active surveillance and testing for evidence of vaccine strain live virus shedding, transmission and infection among populations routinely being given multiple doses of live virus vaccines, including measles vaccine. Therefore, it is unknown exactly how many vaccinated children and adults in the U.S. or other countries are shedding and transmitting vaccine strain live viruses.

Whether or not vaccine strain live virus shedding, transmission and infection is causing undiagnosed or misdiagnosed health problems, especially among people with severe immune deficiencies or autoimmune and other immune system disorders, is an open question.”

Which vaccines are capable of shedding?

Examples of live attenuated viral vaccines are measles, mumps, rubella, vaccinia (smallpox), varicella, zoster (which contains the same virus as varicella vaccine but in much higher amount), yellow fever, rotavirus and influenza (intranasal).9 As with the live virus influenza vaccine, there are many examples of other live attenuated viral vaccines spreading disease.

The live oral polio vaccine (OPV) is one of them. OPV is no longer used in the U.S., having been replaced by inactivated injectable polio vaccine in 1999, but OPV is still used in some developing countries. In 2017, there were 21 reported cases of vaccine-derived polio, compared to six cases of wild polio — marking the first time more cases of polio were caused by vaccine-derived strains than wild or naturally occurring strains.

In Syria alone, 15 children were paralyzed by vaccine-derived polio, according to the World Health Organization (WHO).10 Research published in the journal Cell also revealed that the live vaccine strain virus used in the oral polio vaccine can easily mutate and spread through a community.11 NPR reported:12

“After a child is vaccinated with live polio virus, the virus replicates inside the child’s intestine and eventually is excreted. In places with poor sanitation, fecal matter can enter the drinking water supply and the virus is able to start spreading from person to person.

‘We discovered there’s only a few [mutations] that have to happen and they happen rather quickly in the first month or two post-vaccination,” [lead study author Raul] Andino says. ‘As the virus starts circulating in the community, it acquires further mutations that make it basically indistinguishable from the wild-type virus. It’s polio in terms of virulence and in terms of how the virus spreads.'”

WHO also noted, “When a child is immunized with OPV, the weakened vaccine virus replicates in the intestine for a limited period … During this time, the vaccine virus is also excreted.”13 In some people, however, the period of replication may not be so “limited.”

One British man received three doses of attenuated live virus polio vaccine at 5, 7 and 12 months of age. He also received a booster at age 7, as was recommended. The man has a health condition that suppresses his immune system, making it more difficult for him to clear vaccine-strain poliovirus from the body.

Although he had no symptoms of the disease, when researchers tested his stool (more than 100 samples were taken over a period of 28 years), they confirmed high levels of the poliovirus even decades later.

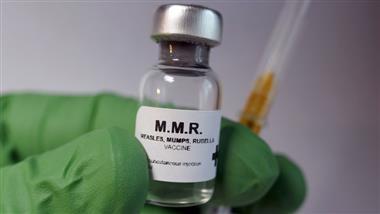
Virus shedding is also possible after MMR vaccination

The CDC recommends the MMR (measles, mumps and rubella) vaccine for children aged 12 to 15 months, with a booster between ages 4 and 6 years. This live attenuated combination vaccine has also been associated with vaccine-strain virus shedding and disease transmission.

For instance, following live virus measles vaccination, measles virus RNA was detected in 10 of 12 children, as early as one day or as late as 14 days after vaccination.14 Vaccine virus-related measles has also been documented, including in one 2-year-old boy who became ill 37 days after receiving an MMR vaccine.

The researchers who published the case report explained, “Although this is the first such reported case, it likely represents the existence of additional, but unidentified, exceptions to the typical timeframe for measles vaccine virus shedding and illness.”15

It’s often the case that measles outbreaks are blamed on unvaccinated individuals, but this suggests that recently vaccinated individuals could also transmit a vaccine strain version of the disease.

Likewise, mumps vaccine strain virus has also been confirmed as being transmitted by recently vaccinated children to their parents, while live rubella vaccine virus can be transmitted via breast milk. The live attenuated chickenpox vaccine can also cause vaccine-strain chickenpox in healthy or immunocompromised vaccine recipients — or their close contacts. According to Fisher:16

“It is possible for healthy children and adults to transmit vaccine strain varicella zoster infection to other healthy children and adults. However, immune compromised persons are at special risk for contracting vaccine strain chickenpox infections and suffering complications.

Generally, it is advised that persons recently given chickenpox vaccine avoid close contact for at least six weeks after vaccination with potentially susceptible persons, such as immune compromised persons, pregnant women, newborn infants and premature babies, especially if a rash develops after vaccination.”

Why are live virus vaccines still being used?

With documented cases of live virus vaccines contributing to vaccine strain virus shedding and transmission, it’s clear there remain many questions about their safety and effectiveness. Yet, their use continues, in part because the immune response triggered by live virus vaccines is considered to be superior to that triggered by inactivated vaccines.

In short, live virus vaccines tend to stimulate an immune response that’s more similar to one that would occur had you been exposed to the wild-type virus naturally. That being said, live virus vaccines rarely confer the same kind of longer lasting immunity that exposure to a naturally acquired infection can confer.

This is why booster shots are necessary, and why some have recommended that a third MMR vaccine dose be added to the U.S. vaccine schedule.

At the very least, it’s important to be aware of the differences between attenuated live virus vaccines and inactivated vaccines, especially if you’re part of a vulnerable population, such as very young children, the elderly, pregnant and breastfeeding women and people with acute or chronic health problems or a compromised immune system.

For now, however, there remain many unanswered questions regarding live virus vaccines and their ultimate impact on public health. As Fisher explained:17

“The impact of vaccine-strain virus shedding infection and transmission on individual and public health is a question that deserves to be asked and more thoroughly examined by the scientific community. The fact that children and adults given live virus vaccines have the potential to pose a health risk to both unvaccinated and vaccinated close contacts should be part of the public conversation about vaccination.”

____________________

For more:  https://madisonarealymesupportgroup.com/2018/12/09/vaccines-likely-infected-with-retroviruses-linked-to-chronic-disease/

https://madisonarealymesupportgroup.com/2017/10/15/vaccines-and-retroviruses-a-whistleblower-reveals-what-the-government-is-hiding/

https://madisonarealymesupportgroup.com/2018/03/01/vaccines-could-contribute-to-disease-epidemics-due-to-retrovirus-contamination/

https://madisonarealymesupportgroup.com/2018/06/23/the-role-of-retroviruses-in-chronic-illness-a-clinicians-perspective/

https://madisonarealymesupportgroup.com/2019/07/02/polio-like-manifestation-of-powassan-virus-with-anterior-horn-cell-involvement-canada/

https://madisonarealymesupportgroup.com/2019/06/15/therapeutic-efficacy-of-favipiravir-against-bourbon-virus-in-mice/

https://madisonarealymesupportgroup.com/2018/05/23/cdc-warns-about-7-new-tick-viruses/

https://madisonarealymesupportgroup.com/2018/12/04/is-the-chickenpox-vaccine-creating-a-shingles-epidemic/

https://articles.mercola.com/sites/articles/archive/2012/07/30/whooping-cough-vaccine.aspx  (Outbreaks of Whooping Cough related to pertussis vaccine)
https://ohioamf.org/wp-content/uploads/2015/11/HIGHLY-and-FULLY-VACCINATED-outbreaks.-1.pdf  (9 pages showing outbreaks in fully vaccinated populations)


North Central Integrated Pest Alert

https://www.ncipmc.org/projects/pest-alerts1/

image.png

They have the following for ticks and specific diseases:

https://www.ncipmc.org/projects/pest-alerts1/brown-dog-tick-vector-for-rocky-mountain-spotted-fever/

https://www.ncipmc.org/projects/pest-alerts1/rocky-mountain-spotted-fever-rickettsia-rickettsii/

https://www.ncipmc.org/projects/pest-alerts1/ticks-and-tick-borne-diseases/