Archive for the ‘Treatment’ Category

7 Signs and Symptoms of LD That Are Way Too Easy to Ignore

https://www.prevention.com/health/health-conditions/a21097669/lyme-disease-symptoms/

7 Lyme Disease Symptoms That Are Way Too Easy to Ignore

Lyme disease can do more than cause a rash—and if you don’t notice the symptoms right away, you’re at risk for major complications.

By Marygrace Taylor
Jun 7, 2018

lyme-disease-symptoms-1528314206LYME DISEASE SYMPTOMSGETTY IMAGES

Lyme disease is the most commonly reported insect-transmitted disease in the United States, affecting an estimated 300,000 people a year, according to the Centers For Disease Control and Prevention (CDC). In certain parts of the country (like the northeast or upper Midwest), checking for ticks is practically a summertime rite of passage.

Experts know that Lyme disease is caused by the bacteria Borrelia burgdorferi, which is transmitted from the bite of an infected tick. But diagnosing the condition isn’t always so straightforward. Once inside your body, the bacteria can wreak havoc in a number of ways. Yes, that can include the classic bullseye-shaped rash. But many of the other symptoms of Lyme disease aren’t as well known, and they can be frustratingly vague.

That’s why it’s important to familiarize yourself with the signs and seek medical assistance if you think you or a loved one may have Lyme. The disease is easy to treat as long as you know what to look for.

Early symptoms of Lyme disease

The first signs of Lyme can strike anywhere from 3 to 30 days after getting bitten by an infected tick. They can include:

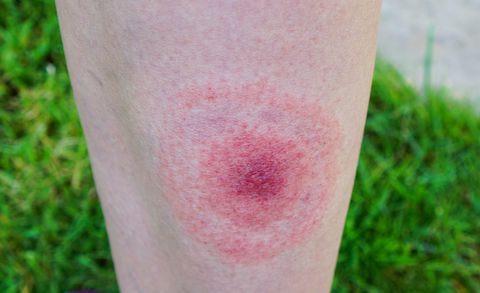
A red rash
lyme-disease-bulls-eye-1524676364

lyme disease rash – GETTY IMAGES

Up to 80 percent of people will develop a red rash in the days or weeks after contracting Lyme disease. It usually forms at the site of the tick bite, and the redness is basically an allergic reaction to the tick’s saliva, says Nikhil Bhayani, MD, an infectious disease specialist at Texas Health Hurst-Euless-Bedford.

Lyme disease rashes will often be bullseye-shaped, but they can also just be a red blotch. The rash will usually expand with time and can get as big as 12 inches. It might feel warm to the touch or look a little crusty in the center where you were bitten, but it won’t be itchy or uncomfortable.

Flu-like symptoms

Not everyone experiences a full laundry list of flu-like symptoms. But there’s a good chance you’ll notice at least a few, Dr. Bhayani says. Here’s how commonly specific symptoms affect Lyme patients:

Fatigue: 54 percent
Fever: 16 percent
Muscle pain: 44 percent
Headache: 42 percent
Neck stiffness: 35 percent
Swollen lymph nodes: 23 percent

The flu-like symptoms are a result of your immune system’s attempt to fight off the bacterial infection and help you get better, says Kalpana D. Shere-Wolfe, MD, an infectious disease specialist the University of Maryland Medical Center Midtown Campus.

Of course, these kinds of symptoms could indicate many different illnesses. One clue that a tick bite caused them? With Lyme disease, you won’t experience the coughing or congestion that often comes with the actual flu, Dr. Shere-Wolfe says.

neck-stiffness-1528384202

Later Lyme disease symptoms

After a month or so, people infected with Lyme disease may start showing additional symptoms. These can include:

Larger or additional rashes

As the Lyme disease infection spreads throughout the body, your rash might start to expand even more. You might also develop new, smaller rashes nearby. Like the early rash, these might be bullseye-shaped. But they can also just look splotchy or blob-like, according to the CDC. They might even take on a slightly bluish tint in the middle.

Exhaustion, fuzzy thinking, and other neurocognitive problems

Borrelia burgdorferi is one of the few bacteria that can cross the blood-brain barrier and infect the central nervous system, explains Timothy J. Sellati, PhD, Chief Scientific Officer for the Global Lyme Alliance. That can lead to inflammation of the brain, which can affect your central nervous system function in a few different ways.

One of those is extreme fatigue, which affects as many as 76 percent of people with advanced Lyme disease, according to research. Trouble concentrating, loss of coordination, and short-term memory loss are other possible problems, occurring in up to 24 percent of people. In extreme cases where the disease is left untreated for extended periods, you might even develop facial weakness and behavioral changes, Sellati says.

Intense headaches

The same inflammation that causes fatigue and fuzzy thinking can also lead to headaches, which findings suggest could strike in up to 70 percent of people with Lyme disease.

Usually, these feel intense and more similar to a migraine than your run of the mill tension headache, Dr. Bhayani says. In addition to throbbing pain, you might also experience hypersensitivity to noise or light.

Severe pain, numbness, or tingling in your joints and muscles

Around 60 percent of patients will develop joint pain or even arthritis as their Lyme disease progresses, according to a Johns Hopkins University School of Medicine study. Usually, it starts in the joints closest to where you were bitten and can spread from there, especially to areas like the knees. The pain isn’t usually constant, though. Experts don’t fully understand why, but “the symptoms can wax and wane over a period of weeks or months,” Sellati says.

Over time, the disease can attack the cartilage in the joints and lead to tissue damage, says Linda Yancey, MD, an infectious disease specialist with Memorial Hermann Katy Hospital in Katy, TX.

Like many of the other problems caused by Lyme disease, this one is also triggered by inflammation. “The damage to tissues, bone, and cartilage is caused by the production of pro-inflammatory proteins, the same protein responsible for damage caused by rheumatoid arthritis,” Sellati says.

joint-pain-1528383554

GETTY/DANA LEIGH SMITH

Heart palpitations, dizziness or shortness of breath

In addition to invading the central nervous system, Borrelia burgdorferi can make its way into heart tissue. That can cause the tissue to become inflamed, leading to heart palpitations, Sellati explains. It might feel like your heart is pounding, fluttering, or beating faster than usual. Usually, it becomes more noticeable with vigorous exercise or stress. The problem isn’t all that common, affecting only around 11 percent of patients. Still, it can be serious. “If [palpitations] occur frequently, seem to get worse, or are accompanied by chest pain, fainting, severe shortness of breath, or dizziness, you should seek immediate medical attention,” Sellati says.

One thing to note: Generally, shortness of breath is most likely to strike when you’re exerting yourself, but with Lyme that isn’t always the case. “A Lyme disease patient can experience shortness of breath during normal activity that in the past might not have resulted in this response,” Sellati explains.

⚠️ If you notice symptoms of Lyme disease, call your doctor right away

It’s best to seek medical attention sooner rather than later. The longer Lyme disease goes untreated, the more likely you are to develop severe complications like intense joint pain, heart problems, or cognitive issues.

Lyme disease treatment: Your doctor should refer you to an infectious disease specialist, who can evaluate your symptoms and decide whether you need testing, Dr. Yancey says. If you test positive, you’ll be given antibiotics to fight the infection.

False-negatives: If your test comes back clean, but you’re convinced that Lyme disease is the culprit, ask to be retested. False negatives are common early on since it takes a few weeks for your immune system to build up antibodies to the bacteria.

________________

**Comment**

This article has some good information mixed in with some very bad information.  The article states as up to 80% have the “classic” bullseye rash.  Hogwash.  ILADS states fewer than 50% see a tick bite or a rash:  http://www.ilads.org/lyme/about-lyme.php  Hardly anyone I work with has seen either.

As to the appearance of any rash that might occur:  “This emphasis on target-like lesions may have inadvertently contributed to an underappreciation for atypical skin lesions caused by Lyme disease.” — Some Visible Signs of Lyme Disease Are Easily Missed or Mistaken, Science Daily, Apr 22, 2013 https://www.sciencedaily.com/releases/2013/04/130422132507.htm?utm_source=feedburner&utm_medium=email&utm_campaign=Feed%3A+sciencedaily%2Fhealth_medicine%2Flyme_disease+%28ScienceDaily%3A+Health+%26+Medicine+News+–+Lyme+Disease%29

As to flu-like symptoms, a case of a little girl outside playing got bit by a tick and within about 6 hours couldn’t walk or talk.  She never got flu-like symptoms but quickly advanced to late stage symptoms WITHIN HOURS:  https://madisonarealymesupportgroup.com/2016/12/07/igenex-presentation/  All my initial symptoms were gynecological:  https://madisonarealymesupportgroup.com/2017/02/24/pcos-lyme-my-story/

Again, as to “Later Lyme Disease Symptoms,” people can jump from one stage to another quickly – within hours and seemingly bypass certain stages.  This is an important detail that if practitioners aren’t aware of, will dismiss patients entirely if they don’t present initially with a bullseye rash and flu-like symptoms.  The little girl’s case I mention is a prime example.  Regular doctors dismissed her entirely.  They rushed her to Dr. Jones, a well-known, respected, and experienced doctor with tick borne illness.  After the treatment he gave, the girl was right as rain.  I cringe when I consider the alternative.  She would join the increasing ranks of “Chronically infected” patients.

The article again, states “larger or additional rashes,” in this category but many fail to have any, ever.  

I am thankful the article mentions heart issues, pain, numbness, tingling, dizziness, shortness of breath, and headaches as these are symptoms many experience.  What they fail to mention is the involvement of other pathogens that could cause these very same symptoms and require different medications.

I’m also thankful they state to call your doctor right away.  Here’s the problem.  Most doctors don’t know what they hell they are doing and infectious disease “specialists” are often the worst offenders!  They are believing, regurgitating, and following the same ancient mythical advice that’s been going around like a bad case of the flu for over 40 years!  Don’t waste your time and money on these folks.  Contact your local lyme support group for Lyme literate physicians trained by ILADS.  Please point regular practitioners to this:  https://madisonarealymesupportgroup.com/2018/06/06/lyme-education-for-healthcare-professionals/ and https://madisonarealymesupportgroup.com/2018/02/19/calling-all-doctors-please-become-educated-regarding-tick-borne-illness-heres-how/

Case in point:  They state that those who get treated promptly fare much better, yet the video within the article (go to link) states to take a “wait and see” approach.  In other words, you get bit, and then you just wait around on pins and needles to SEE if you experience symptoms.  Anyone else out there see the Russian Roulette approach here?  It’s a damned if you do, damned if you don’t scenario, with you losing in the end.

Each and every tick bite needs to be taken as seriously as a heart attack and treated, in my opinion.  Why risk it?  As a patient and advocate who’s infected as well as her husband, and has spent over $120K out of pocket for over 4.5 years of treatment and needing to regularly maintain this health, I can attest to how this illness(es) can take everything you own and have.  It will rock your world like nothing else. The official ILADS word on this is that there IS NO black and white answer as to treating a tick bite prophylactically but if you live in an endemic area (as I do) you should definitely consider it because a high percentage of ticks are infected.  They also state IF you decide to be treated, it should be for NO LESS than 3 weeks.  This treatment will prevent the body from mounting an antibody response, which means subsequent testing for Lyme WILL BE NEGATIVE.  To which I say, what does that matter if you become sicker than a dog?  TREAT THIS SUCKER AND TREAT IT NOW!  http://www.ilads.org/lyme/what-to-do-if-bit-by-tick.php

If you are unfamiliar with what appropriate Lyme treatment looks like:  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/

You can type the other pathogens into the search bar for their treatments.  (i.e. Babesia, Bartonella, Mycoplasma, Viruses, etc)


ECU Researcher Gets Money From NIH to Develop Medication for Lyme

http://www.wnct.com/news/health-news/ecu-researcher-tries-to-find-better-way-to-treat-lyme-disease/1239691985

ECU researcher, MD A. Motableb has obtained  $1.7 million from the National Institutes of Health (NIH) to study borrelia, the causative agent of Lyme Disase in the human body.

The hope is to develop a medication.

The article goes on to state deeply entrenched myths about initial symptoms such as the bullseye rash that do not represent many patients.

For more on Lyme:  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/

Psychological symptoms of Lyme:  https://madisonarealymesupportgroup.com/2015/10/18/psychiatric-lymemsids/

I’m not holding my breath for this hoped for medication.  The first thing that has to be acknowledged by main stream medicine and researchers is this is NOT a one pathogen one drug illness.  Patients are often infected with a plethora of pathogens – some viral, some bacterial, some fungal, even nematodes (worms).  They all take different medications.  https://madisonarealymesupportgroup.com/2017/07/01/one-tick-bite-could-put-you-at-risk-for-at-least-6-different-diseases/  The actual number is 18 and counting.

Besides this crucial fact, these pathogens cause all sorts of havoc within the body including inflammation and an autoimmune response.  Many have mast cell issues, newly developed sensitivities, hormonal imbalances, adrenal issues, and on and on to infinity.

This is the perfect storm and it’s complicated to say the least.


Tick-Borne Disease Working Group Subcommittee Reports – Comments due by June 18

https://www.hhs.gov/ash/advisory-committees/tickbornedisease/reports/index.html

Reports

The Tick-Borne Disease Working Group (Working Group) is required to submit a report on its activities and any recommendations to the HHS Secretary and Congress every two years. The first report is due December 2018.

The six subcommittees of the Working Group prepared reports to inform the Working Group and its 14 voting members. These reports offer insights into gaps, opportunities and potentials actions to be considered by the Working Group for the report to Congress and HHS Secretary. 

Report of the Access to Care Services and Support to Patients Subcommittee

Report of the Disease Vectors, Surveillance, and Prevention Subcommittee

Report of the Other Tick-Borne Diseases and Co-Infections Subcommittee

Report of the Pathogenesis, Transmission and Treatment Subcommittee

Report of the Testing and Diagnostics Subcommittee

Report of the Vaccine and Therapeutics Subcommittee


You may make comment either by writing or verbally by June 18th, for the next meeting on June 21st.

Go here for the June 21st meeting.
https://www.hhs.gov/ash/advisorycommittees/tickbornedisease/meetings/index.html


Depression: the Radical Theory Linking it to Inflammation

https://www.nature.com/articles/d41586-018-05261-3

BOOKS AND ARTS 29 MAY 2018

Depression: the radical theory linking it to inflammation

Alison Abbott considers a persuasive case for the link between body and mind.

d41586-018-05261-3_15785092
Collage of coloured sagittal MRI scans of the human brain.
Magnetic resonance imaging scans of the human brain.Credit: Simon Fraser/SPL/Getty

The Inflamed Mind: A Radical New Approach to Depression Edward Bullmore Short (2018)

Depression affects one in four people at some time in their lives. It is often difficult to treat, in part because its causes are still debated. Psychiatrist Edward Bullmore is an ardent proponent of a radical theory now gaining traction: that inflammation in the brain may underlie some instances. His succinct, broad-brush study, The Inflamed Mind, looks at the mounting evidence.

The book outlines a persuasive case for the link between brain inflammation and depression. Bullmore pleads with the medical profession to open its collective mind, and the pharmaceutical industry to open its research budget, to the idea. He provides a current perspective on how the science of psychiatry is slowly emerging from a decades-long torpor. He sees the start of a shift in the Cartesian view that disorders of the body ‘belong’ to physicians, whereas those of the more ‘immaterial’ mind ‘belong’ to psychiatrists. Accepting that some cases of depression result from infections and other inflammation-causing disorders of the body could lead to much-needed new treatments, he argues.

In 1989, during his clinical training at St Bartholomew’s Hospital in London, Bullmore encountered a patient whom he calls Mrs P, who had severe rheumatoid arthritis. She left an indelible impression. He examined her physically and probed her general state of mind. He reported to his senior physician, with a certain pride in his diagnostic skill, that Mrs P was both arthritic and depressed. Replied the experienced rheumatologist dismissively, given her painful, incurable physical condition, “You would be, wouldn’t you?”

Mrs P is a recurring motif, as is the rhetorical question. Bullmore draws on more than two millennia of medical history — from ancient Greek physician Hippocrates to the work of neuroanatomist and 1906 Nobel laureate Santiago Ramón y Cajal — to illustrate his points. At times they seem like intellectual meanderings, but these passages also show how medical science often progresses by means of bold theories that break away from received wisdom.

After his training, Bullmore specialized in psychiatry, and quickly experienced its limitations. He describes his growing awareness of how poorly science has served the field, using the development of selective serotonin reuptake inhibitors (SSRIs) as a prime example.

That long and winding road began with the antibiotic iproniazid. It was discovered through scientific logic: by screening chemicals for their ability to kill Mycobacterium tuberculosis in the test tube and in mice. Iproniazid transformed the treatment of tuberculosis in the 1950s. Patients clawed back from the jaws of death exhibited euphoria — well, you would, wouldn’t you? — and the drug was soon launched as an antidepressant. Soon the theory emerged (based more on supposition than evidence, says Bullmore) that its psychiatric effects were the result of boosting the neurotransmitters adrenaline and noradrenaline. Drug developers began to focus on neurotransmission more broadly.

Prozac (fluoxetine), which boosts serotonin transmission, was launched in the mid-1980s, and many pharmaceutical companies quickly followed with their own SSRIs. It seemed to be the revolution psychiatrists had been waiting for. But it soon emerged that only a modest subset of patients benefited (estimates based on trials vary widely). That is unsurprising in retrospect, with the new appreciation that depression can have many causes. Bullmore holds that the emergence of SSRIs bypassed scientific logic. The serotonin theory, he writes, is as “unsatisfactory as the Freudian theory of unquantifiable libido or the Hippocratic theory of non-existent black bile”. He notes that, after SSRIs failed to live up to the hype, time once again stood still for psychiatry.

Bullmore recalls a teleconference in 2010, when he was working part-time with British pharmaceutical giant GlaxoSmithKline. During the call, the company announced it was pulling out of psychiatry research because no new ideas were emerging. In the following years, almost all of ‘big pharma’ abandoned mental health.

Then a window seemed to open — one that shed a different light on the plight of Mrs P. Some of the textbook certainty that Bullmore had learnt by rote at medical school started to look distinctly uncertain.

In particular, the blood–brain barrier turned out to be less impenetrable than assumed. A range of research showed that proteins in the body could reach the brain. These included inflammatory proteins called cytokines that were churned out in times of infection by immune cells called macrophages. Bullmore pulls together evidence that this echo of inflammation in the brain can be linked to depression. That, he argues, should inspire pharmaceutical companies to return to psychiatry.

It seems unfair that someone struck down by infection should have depression too. Is there a feasible evolutionary explanation? Bullmore hazards that depression would discourage ill individuals from socializing and spreading an infection that might otherwise wipe out a tribe.

Other brain disorders might turn out to be prompted or promoted by inflammation. An exciting link with neurodegenerative diseases, including Alzheimer’s, is also being studied (see Nature 556, 426–428; 2018). But we need to learn from the rollercoaster history of brain research, and keep expectations in check. Beneath his bombastic enthusiasm, Bullmore acknowledges this, too.

Nature 557, 633-634 (2018)

doi: 10.1038/d41586-018-05261-

_________________

**Comment**

Lyme/MSIDS patients are often depressed.  I certainly was.  I found the worse I felt physically, the worse I felt mentally.  My mental state improved on appropriate anti-microbial treatment right along with my physical state.

I wholeheartedly believe the reason we are seeing suicides with Lyme/MSIDS is because patients are being abused at every juncture.  They are not believed and live an isolated existence where they can not speak honestly to those closest to them.  If you find yourself in this situation, please, for your mental health, get to a support group.  Once inside those doors you will be affirmed, believed, and listened to.  Don’t have a support group?  Start one!  With an estimated 1 million to contract Lyme/MSIDS this year (2018) there’s going to be a whole lot more of us!  https://madisonarealymesupportgroup.com/2018/02/24/one-million-predicted-to-get-lyme-in-2018-in-the-u-s/

For some other info linking infections to depression:  https://madisonarealymesupportgroup.com/2017/10/03/treat-the-infection-psychiatric-symptoms-get-better/

https://madisonarealymesupportgroup.com/2017/10/01/panspandas-steroids-autoimmune-disease-lymemsids-the-need-for-medical-collaboration/

https://madisonarealymesupportgroup.com/2015/10/18/psychiatric-lymemsids/

https://madisonarealymesupportgroup.com/2017/01/17/lymemsids-and-psychiatric-illness/

https://madisonarealymesupportgroup.com/2017/10/08/misdiagnosed-how-children-with-treatable-medical-issues-are-mistakenly-labeled-as-mentally-ill/

https://madisonarealymesupportgroup.com/2017/06/30/child-with-lymemsidspans-told-by-doctors-she-made-it-all-up/

https://madisonarealymesupportgroup.com/2018/06/04/ld-diagnosis-took-forever-because-of-mental-health-stigma/

https://madisonarealymesupportgroup.com/2018/04/07/young-woman-with-lyme-takes-her-life/


Corruption & Human Rights Violations Against Lyme Doctors, Scientists, and Parents Now on United Nations Record

https://www.linkedin.com/pulse/corruption-human-rights-violations-against-lyme-now-luche-thayer/

Corruption and Human Rights Violations Against Lyme Doctors, Scientists and Parents Now on United Nations Record

0Published on June 12, 2018
Jenna Luche-Thayer
consulting Senior Advisor – US Government, United Nations, non-profits, corporate social responsibility programs

The 2018 Report ‘The Situation of the Human Rights Defenders of Lyme and Relapsing Fever Borreliosis Patients’ was submitted to Special Rapporteur Michel Forst and to Special Rapporteur Dr. Dainius Puras of the United Nations in March 2018. This resulted in a meeting between United Nations Human Rights Council Special Rapporteur Forst and medical professionals, scientists, human rights experts and advocates on June 5, 2018 in Geneva, Switzerland.

FOR IMMEDIATE RELEASE – June 12, 2018. The United Nations (UN) Special Rapporteur for Human Rights Defenders, Michel Forst, heard presentations on multiple countries from the all voluntary Ad Hoc Committee for Health Equity in ICD11 Borreliosis Codes, whose global members are dedicated to addressing the borreliosis pandemic.

Jenna Luché-Thayer, Director of the Ad Hoc Committee, gave an overview from the 2018 Report ‘The Situation of the Human Rights Defenders of Lyme and Relapsing Fever Borreliosis Patients’ that was followed by representatives sharing cases from their countries. She started by contrasting scenarios where the public recognition of human rights issues differs. For example, most people recognize the devotion to human rights of the journalist who goes into a war zone to find and share the truth of innocent people brutalized by war crimes and the risks taken by the persons who organize to free children from international sex trafficking. These defenders of human rights can be easily identified because they are working to address situations we all can recognize as horrific.

In contrast, the healthcare systems across the globe are largely recognized as flawed but not intentionally horrendous. However, increasing numbers of scholarly publications have documented how these healthcare systems have become quietly corrupted and this has led to a global healthcare situation wherein “criminal activities have become normalized”, according to Dr. Dainius Pūras, the UN Special Rapporteur on the right to health.

The defenders of Lyme and relapsing fever borreliosis patients include medical professionals, doctors, scientists, patients and advocates fighting for the health human rights of this patient group. The Report shows how many of these defenders are routinely defamed, their freedoms to associate and speak restricted, and their livelihoods are threatened. It also shows how parental rights of parents of severely ill children are routinely violated by State Actors.

According to the October 24, 2017 presentation to the UN General Assembly by Dainius Pūras, “In many countries, health is among the most corrupt sectors; this has significant implications for equality and non-discrimination.”

This second Report by the Ad Hoc Committee supports his findings. It details how financial motivations shared among a faction in a medical society, their associates, State Actors and insurers have contributed to a global situation whereby doctors, scientists and parents are attacked because they defend these patients’ rights to health, bodily integrity and life. It is not uncommon for these defenders’ reputations, livelihoods and finances to be ruined — doctors lose their licenses, scientists lose access to research monies and parental rights are violated when ill children under treatment that meet internationally accepted standards are seized from their homes.

Jenna Luché-Thayer, a human rights expert with 33 years of experience in 42 nations reported how the case definition of Lyme borreliosis (LB) was changed by colluding US State Actors and certain members of the Infectious Disease Society of America (IDSA)’ and that the timing of these changes concurred with the launch of a failed Lyme vaccine, promotion of an unreliable, yet profitable diagnostic test system and the unwillingness of US insurers to cover the chronic or persistent form of the disease as they moved into the ‘managed care’ model.

She noted how the revised LB case definition removed most references to the debilitating symptoms, disabling and potentially fatal complications, persistence and severity of the disease and the unreliable diagnostic technologies. She also noted that contrary to the case definition, over 200 patents — held by IDSA members, State Actors and associates — reflect these serious and life-threatening complications, persistence of the disease and how the infection is often missed by the unreliable serology diagnostic technology.

Luché-Thayer detailed how the current situation of these human rights defenders and this patient group shows violations of articles found in eleven international and/or regional human rights treatises and conventions.

She stated that it appears the corruption started in the early 1990s is reflected in the 2006 IDSA Guidelines that have been promoted globally and also appears to have shaped the World Health Organization’s (WHO) International Classification of Diseases (ICD) codes for the disease.

She stated the Report shows how this corruption appears to be globally organized across institutions such as the Association of Medical Microbiology and Infectious Diseases of Canada, European Union Concerted Action on Lyme Borreliosis (currently defunct) European Society of Clinical Microbiology and Infectious Diseases’ Study Group for Lyme Borreliosis (ESGBOR) and State Actors and is driving unnecessary suffering, death and bankruptcy among this patient group.

The former Senior Advisor to the United Nations and U.S. government asked, “There is universal agreement that prisoners have a right to medical care. Precisely what is the difference between a ‘prisoner of war’ and ‘an eight-year-old boy’ being denied medically necessary antimicrobial care? Seizing the business of a political opposition party leader is prohibited. Precisely what is the difference between ‘seizing the businesses from a political opposition party leader’ and a medical board with members representing one medical society ‘closing down the business of a medical doctor that belongs to a competing medical society’?”

Jim Wilson, President of CanLyme, and Jennifer Kravis, co-founder of LymeHope, lawyer and mother of a daughter with tick borne diseases, testified about the situation in Canada. Only two percent of all Canadian doctors have ever been under investigation by their respective provincial Colleges of Physicians and Surgeons whereas nearly 100 percent of the doctors who diagnose and treat LB clinically have either been harassed by their respective provincial Colleges of Physicians and Surgeons to the point they gave up their medical licenses, or were forced to stop seeing Lyme patients.

Dr. Kenneth Liegner (USA) spoke about how he used to cooperate with the US Centers for Disease Control and Prevention and detected the Lyme infection in the spinal fluid of his patient, Vicki Logan, despite prior antibiotic treatment. Early on, her private health insurer covered extended intravenous antibiotic treatment which improved her condition. Later, when in a nursing home and under Medicaid, her intravenous antibiotic treatment was suspended. While Liegner sought mechanisms for Medicaid reimbursement, Vicki experienced grand mal seizures and was transferred to a local hospital where Liegner did not have privileges. There she was found to have low blood pressure, her condition was not investigated and her family was persuaded to support a ‘do not resuscitate’ order. She subsequently died. An autopsy revealed ongoing neurologic Lyme disease and an acute heart attack that was neither diagnosed nor treated. Her case exemplifies the discrimination persons with Lyme experience.

Special Rapporteur Forst also heard of how many of Liegner’s colleagues were bullied into silence or submission; many of them losing their licenses or going bankrupt because of legal costs to fight the allegations made by insurance companies and supported by certain IDSA members. For example, defender Dr. Joseph Burrascano anticipated his own attacks in his 1993 Senate testimony on the apparent corruption and the unethical obstruction to diagnostics and care experienced by this patient group. Liegner also made a point of saying ‘it was not patients who made these allegations’.

French Professor Christian Perronne is an internationally renowned Infectious and Tropical Diseases specialist with over 300 scientific publications and has played an advisory role to WHO. Perronne told the Special Rapporteur how, following his 2016 presentation on LB at France’s Academy National of Medicine, he was publicly called a “terrorist” by former the President of the Academy, Professor Marc Gentilini.

The Ad Hoc Committee recognizes there are other patient groups and defenders’ experiencing similar human rights violations, and with the increasing corruption found in the health sector globally, these violations are trending across more groups. Emeritus Professor Malcolm Hooper (UK) testified how the defenders of an estimated 15-30 million people with Myalgic Encephalomyelitis diagnosis (also known as ‘chronic fatigue syndrome’) are similarly attacked and discredited. He shared how the guidelines for ME treatment also appear to be riddled with conflicts of interests, fraudulent science and harm patients’ health and obstruct their access to disability payments.

While in Geneva, Dutch social scientist and human rights researcher Huib Kraaijeveld and other Ad Hoc Committee members discussed these matters with officials from the Dutch Ministry of Health and Embassy. Ad Hoc members including Dr. Anne Fierlafijn (Belgium), retired senior engineer Michael Cook (UK), biologist Dr. Barbaros Çetin (Turkey), media expert Torben Thomsen (Denmark), human rights expert Dr. Astrid Stuckelberger (Switzerland), psychiatrist Dr. Ursula Talib (Switzerland), scientist Dr. Mualla McManus (Australia) and advocate Theresa Denham (USA) also met with an array of internationally recognized human rights leaders and advisors, documentary film makers, and a number of persons in the Swiss medical system and UN personnel with personal experience of Lyme.

To note, the WHO’s ICD codes for Lyme borreliosis are still inadequate and outdated. When Ad Hoc member Stuckelberger contacted WHO to set a meeting to discuss the LB codes, she received written communications stating that ‘WHO has no person for Lyme borreliosis’– one of the fastest growing vector borne diseases in the world and officially ranked by the European Union as one of the top public health threats in Europe. These inadequate codes may be why in West Africa many persons misdiagnosed with debilitating drug resistant malaria were eventually found to be suffering from borreliosis infection.

According to Ad Hoc Committee founder Luché-Thayer, “This global all-voluntary organization will continue to document the human rights violations and corruption surrounding this borreliosis pandemic; we are committed to addressing these self-serving, financially-motivated threats to global health.”

………………………………………………………. # # # ………………………………………………………………

Contact: Jenna Luché-Thayer at jennaluche@gmail.com

______________

For Vicki Logan’s story:  https://madisonarealymesupportgroup.com/2017/03/09/remember-vicki-logan/

More on the fraud, corruption, and collusion of the CDC and IDSA:  https://madisonarealymesupportgroup.com/2017/11/15/lyme-patients-file-lawsuit-against-idsa-and-insurers-over-treatment-denials/

https://madisonarealymesupportgroup.com/2017/09/25/speaking-of-fake-science-fifty-seven-million-anti-trust-lawsuit-against-cdc-lyme-tests/

https://madisonarealymesupportgroup.com/2016/11/29/spider-attacks-cdc/

https://madisonarealymesupportgroup.com/2018/04/06/cdcs-troubling-lack-of-research-ethics/

https://madisonarealymesupportgroup.com/2017/10/06/remembering-dr-masters-the-rebel-for-lyme-patients-who-took-on-the-cdc-single-handedly/   Masters went over the charts with a fine tooth comb and found huge CDC errors. Another contentious point was the arbitrary cut off date imposed by the CDC which did not pick up serious late-stage symptoms. Another was the CDC’s rejection of many positive blood tests performed in its own lab, as well as other lab work showing “motile spirochetes” in nearly 5% of lone star nymphs. Long story short, after numerous revisions, Masters could never sign onto the bastardized study. The CDC had purposely tossed out data and manipulated the results.  The CDC essentially tried blackmailing Masters into signing off on the study before they would let him see the final draft. Refusing the bait, he published a letter of objection in the Journal of Infectious Diseases as well as an article of his own in Missouri Medicine which showed Missouri patients met the CDC surveillance definition for LD and growing evidence that lone star ticks were infected with an unidentified spirochete causing identical symptoms of LD in patients. When the CDC study came out they unbelievably attributed the rashes they labeled STARI to an allergy to tick saliva! In the acknowledgment section of the paper where dozens of folks were thanked, they completely omitted the man who made it all possible – Dr. Ed Masters. RIP – we will never forget you.

Another example of how insurance companies hide behind the corrupt CDC guidelines:  https://madisonarealymesupportgroup.com/2018/02/14/another-lyme-patient-denied-health-benefits-files-lawsuit/
