Archive for the ‘Testing’ Category

Lyme Testing Using Two Recominant Proteins

Improved serodiagnostic performance for Lyme disease by use of two recombinant proteins in ELISA as compared to standardized two tier testing

Bradshaw GL, Thueson RK, Uriona TJ.

Journal of Clinical Microbiology, online first, 2017 Aug 2.

https://doi.org/10.1128/JCM.01004-17

Abstract

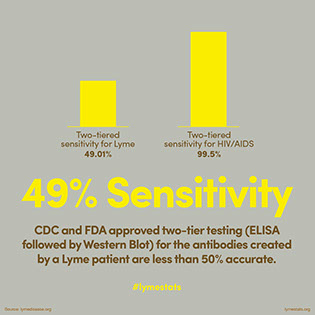
The most reliable test method for the serological confirmation of Lyme Disease (LD) is a 2-tiered method recommended by the CDC in 1995. The first-tier test is a low specificity ELISA test and the second-tier tests are higher specificity IgG and IgM Western blots. This study describes the selection of two Borrelia burgdorferi-recombinant proteins and evaluation of their performance in a simple 1-tier test for the serological confirmation of LD.

These two proteins were generated from
(a) the full length dbpA gene combined with the invariable region 6 of the VlsE gene (dbpA/C6) and
(b) the full length OspC gene.

The expressed dbpA/C6 and the OspC proteins were useful in detecting anti-Borrelia IgG and IgM antibodies, respectively. A blind study was conducted on a well-characterized panel of 279 human sera from the CDC comparing ELISA tests using these two recombinant antigens with the 2-tiered test method. The two methods (dbpA/C6-OspC vs 2-tiered) compared equivalently in identifying sera from negative control subjects (99% vs 100% specificity, respectively) and in detecting stage II & III LD patient sera (100% vs 100% sensitivity). However, the dbpA/C6-OspC ELISA test was markedly better (80% vs 63%) than the 2-tiered test method in detecting anti-Borrelia antibodies in stage I LD patients.

The finding suggest that these antigens could be used in a simple 1-tier ELISA assay that is faster to perform, easier to interpret, and less expensive than the 2-tiered test method, and which is better at detecting Borrelia specific antibodies in patient sera with stage I LD.

More on testing:

https://madisonarealymesupportgroup.com/2017/04/12/comparing-lyme-testing-with-hiv-testing/

38_sensitive316x316   01_test_petri316x31625_antibody316x316

https://www.lymedisease.org/lyme-basics/lyme-disease/diagnosis/  Testing explained and interpreted.


California Lyme Cases Get No Respect

https://www.lymedisease.org/touched-by-lyme-california/
Dorothy Kupcha Leland  07 AUG  2017

TOUCHED BY LYME: California Lyme cases “don’t get no respect”

There’s a troubling statement about Lyme disease on the CDC website which is widely cited in the media: “This disease does not occur nationwide.”

What in the world does that sentence mean?

Even using the CDC’s own highly restrictive Lyme surveillance criteria, there are cases on the east coast, cases on the west coast, and cases in the middle. So, what about that scenario is NOT “nationwide”?

The CDC emphasizes that virtually all US cases of Lyme disease occur in only 14 states: Connecticut, Delaware, Maine, Maryland, Massachusetts, Minnesota, New Hampshire, New Jersey, New York, Pennsylvania, Rhode Island, Vermont, Virginia, Wisconsin.

And the website strongly implies that if you haven’t spent time in one of those states, your chance of contracting Lyme is pretty much nil.

But as my colleague Lorraine Johnson recently pointed out in her blog the Lyme Policy Wonk, those numbers don’t jibe with data from other sources.  https://madisonarealymesupportgroup.com/2017/08/05/cdc-maps-for-lyme-disease-not-accurate/  (Why Doesn’t the CDC Count Lyme Disease Cases in the South and the West? Everybody Else Does.)

It is true that Lyme-infected people in the remaining 36 states often have a devil of a time getting properly diagnosed and treated for the illness—which can result in fewer cases being submitted to the CDC’s reporting system. But the problem is deeper than that.

A case in point—my home state of California. During my 12 years of Lyme advocacy, I’ve personally heard from hundreds if not thousands of Lyme-infected people who have been told by medical professionals, “You can’t have Lyme disease, because there’s no Lyme in California.”

A recent article from KQED public media in San Francisco spells out the conundrum of Lyme in this state. As one tick expert explains it:

“There are definitely patches in California where the risk is just as high as the East –it’s just not the same spatial extent.”

In other words, the risk isn’t spread out evenly. The article goes on to say:

Hikers can move from high-risk area to a low-risk area and never know it….One moment you’re strolling through redwood forests, the next through oak forests, and a couple of hours later you may come across scenic chaparral. While on this iconic hike, you probably don’t realize that you’ve moved through both high- and low-risk Lyme disease areas. The question is, do you know where you are most at risk? The answer is in the oak forest where layers of rich leaf litter are a kind of Club Med for ticks.

But you know what? While oak forest with layers of leaf litter may indeed be Club Med for ticks, plenty of ticks hang out in what might be considered the YMCA—ordinary spots like a backyard garden, a wooden picnic table , or an outcropping of rocks.

It all depends on where the garden, the picnic table, and the rocks are located! You do not have to be in an oak forest to get nailed by an infected tick in California.

The article goes on to say:

Part of what puts Californians at risk is a lack of awareness — among the public and even among doctors. Much of the research and public health information is based on East Coast ecology and may not apply to the West.

For many Californian physicians, Lyme disease is just not on the radar, even though …Lyme-infected ticks have been located in 42 of California’s 58 counties. About 100 cases of Lyme disease are reported in California each year, but according to Supervising Public Health Biologist Kerry Padgett of the state Department of Public Health, the disease is likely more widespread. “There is an under-diagnosis and under-reporting of Lyme disease in California,” says Padgett.

Well, there’s an understatement!

What KQED’s article fails to point out is that the words “100 reported cases” mean something very different to the CDC and state health officials than to the average person.

A more accurate way of putting it would be: Every year, about 100 cases make it through the meat-grinder that is the CDC’s labyrinthine Lyme disease reporting process. You start with thousands of people who go to their doctors with undiagnosed Lyme disease. Throw out all the ones who are misdiagnosed with something else. (“No Lyme in California,” remember, so the diagnosis isn’t even considered.)

Of the ones where Lyme is at least thought about, take all the positive lab tests that are reported (by law) to the state. Send those cases to the county health departments of the patients’ place of residence.

The county health department is now supposed to take those positive Lyme cases and investigate each one individually, to make sure it precisely fits the CDC’s rigorous surveillance criteria. This sometimes involves contacting the patient and/or the doctor (a time-consuming and resource-intensive undertaking).

And of course, most California counties, like their counterparts in other states, are under-funded and under-staffed. Is it any wonder that many Lyme cases just seem to fall off the end of the turnip truck, never to be heard from again? Only thoroughly vetted cases are sent on to state health officials, who double-check to make sure each one meets the CDC’s tough requirements in order to be counted, and then forward them on to the federal agency.

A few cases survive that winnowing process. Voilà: 100 reported cases of Lyme in California. The rest are left in the dust somewhere.

Under-diagnosed and under-reported, indeed.

TOUCHED BY LYME is written by Dorothy Kupcha Leland, LymeDisease.org’s VP for Education and Outreach. She is co-author of When Your Child Has Lyme Disease: A Parent’s Survival Guide. Contact her at dleland@lymedisease.org

**Comment**

Dorothy nailed this perfectly.  Each state has its unique terrain which can be highly variable.  To use the same criteria for every state is foolish.  The gauntlet of state reporting of Lyme Disease is too stringent and arbitrary.  This NEEDS to change.  The CDC is not getting an accurate picture at all of Lyme-land.  They also need to make coinfections reportable as well.


Chronic Lyme Patients Bemoan Dearth of Local Doctors

http://www.capecodtimes.com/news/20170604/chronic-lyme-patients-bemoan-dearth-of-local-doctors

Chronic Lyme patients bemoan dearth of local doctors
By Cynthia McCormick  Posted Jun 4, 2017 at 2:00 AM

Twice a year, Joanne Creel of Yarmouth Port and her husband, Clarence Eckerson, make a pilgrimage to the Hyde Park, New York, office of Dr. Richard Horowitz to get treated for Lyme disease and co-infections.

It’s a long day, punctuated by coffee on the way there and and a stop at a diner for lunch on the five-hour drive back to the Cape.

“I’ve gone 14 years to New York,” putting the bill on credit cards since Horowitz does not take insurance, Creel said. She said she doesn’t have a choice.

Despite the prevalence of Lyme and other tick-borne disease on the Cape and Islands, no full-time medical specialist in Barnstable County treats Lyme disease patients with persisting symptoms that include cognitive deficits, swollen joints, vision problems and anxiety and depression.

“All of these patients are out there,” said Creel, a social worker and former marathon runner. “There is no doctor who is specifically for Lyme patients.”

But at a time when the U.S. Centers for Disease Control says there are 300,000 new cases of Lyme a year, advocates for people with the disease say they are dismayed at the lack of resources available to study the illness and at the paucity of physicians who are willing to treat patients with lingering symptoms, a problem exacerbated by the fact most treatments for lasting symptoms consist of the controversial long-term use of antibiotics.

Now a physician from the Dean Center for Tick Borne Illness at Spaulding Outpatient Center Boston is calling for a massive effort to fund research and help patients whose lives have been uprooted by the disease named in the 1970s after an outbreak in Lyme, Connecticut.

“This is a national emergency. This is an epidemic,” said Dr. Nevena Zubcevik, clinical co-director of the Dean Center, which filled up shortly after opening in 2015.

“We should act fast,” Zubcevik said. “It’s just getting worse every year.”

And it’s not just Lyme. Co-infections including babesiosis, anaplasmosis, Borrelia miyamotoi and the Powassan virus are expanding their reach.

Lack of good diagnostic tools and limited physician time with patients — most appointments now run between 10 to 30 minutes — “are insufficient to properly evaluate the complex clinical presentation of a patient presenting with chronic effects of tick-borne illness,” Zubcevik said.

Patients can present with a “very complicated” cluster of symptoms including stomachaches, headaches, numbness and tingling, cardiac issues, hearing loss, eye and balance problems and —most detrimental — cognitive issues that can derail school work and cost people their jobs, Zubcevik said.

Lyme in its post-acute stages is known by various names including chronic Lyme, persisting Lyme, disseminated Lyme, late-stage Lyme and post-treatment Lyme disease syndrome.

Whatever the nomenclature, it’s not uncommon, Zubcevik said.

Research by Dr. John N. Aucott at Johns Hopkins University School of Medicine shows about 20 percent of people continue to have symptoms after being treated with recommended antibiotics after being diagnosed with Lyme disease, Zubcevik said. “We need to devote more research dollars to understand why.”

Katie Crocker, of Marstons Mills, said getting bitten by ticks, first as a child, upended her life.

Now 36, she had to quit college and go on disability while she dealt with a variety of symptoms from the Lyme and co-infections including headaches, joint pain, “air hunger,” sleep disorders, poor circulation and problems gaining muscle.

Her symptoms got worse after a bad car accident, said Crocker, who has since been treated. “My life just kind of stopped from chronic illness,” she said.

“It’s like having the flu for the rest of your life,” said Aucott, assistant professor of medicine at Johns Hopkins University School of Medicine and director of the Lyme Disease Research Center.

Aucott studies both acute and post-treatment Lyme disease syndrome and says he has proof that not all Lyme patients treated with antibiotics in the acute phase of the disease recover.

His 2015 study of post-Lyme patients published in the Infectious Disease Clinics of North America journal show that immune system proteins known as CCL19 chemokines remain elevated in post-treatment patients who complain of lingering symptoms of illness.

“The immune system is still active and talking to itself and moving immune cells around,” possibly to sites of inflammation, Aucott said.

The pain isn’t all in patients’ heads, Aucott said. It’s in their bodies and possibly their nerves or nervous systems, he said.

But figuring out what is driving the immune system to act out and how to treat suffering patients is the controversial part, Aucott said.

The few physicians who specialize in Lyme disease treatment, such as now-retired Dr. Sam Donta of Falmouth, include long-term antibiotics in their arsenal on the premise that bacterial infections are still present and active.

But the Centers for Disease Control, while acknowledging that symptoms can persist beyond six months, discourages the use of long-term antibiotics, citing studies that show them to be of limited or no use compared with placebos.

Patients may claim improvement, but those cases are anecdotal, said Dr. Patrick Cahill, an infectious disease specialist at Cape Cod Hospital. Cahill, who accepted an invitation to join the Barnstable County Tick-Borne Disease Task Force of which Donta is also a member, said there is no research that shows Lyme patients improve after more than 28 days of antibiotic treatment.

Cahill said he advocates for 10 days of treatment with doxycycline in early acute stages of Lyme and up to 28 days in cases where treatment has lagged or not worked, and Lyme has gone into a disseminated stage.

Inflammation and autoimmune responses could account for some chronic cases of Lyme, Zubcevik said. But animal studies have shown live spirochetes following antibiotic treatment, which suggests elements of persistence might be a factor in some cases, she said.

In a reversal of the usual Lyme disease transmission from tick to person, a study led by Dr. Linden Hu at Tufts University suggests it’s possible that “clean” ticks got sick after feeding on people who complained of lingering symptoms of Lyme including fatigue and arthritis.

One or two of the ticks who fed on the study participants showed the presence of Lyme pathogens after being tested by polymerase chain reaction in the lab, Aucott said. The study is currently in phase two, but Aucott said he could not comment since he is participating in the research.

If pathogen-free ticks pick up the disease after feeding on Lyme patients who complain of lingering symptoms, scientists consider it a good indication that the spiral-shaped bacteria that causes Lyme disease can survive in its human host even after being zapped for 21 to 28 days with antibiotics.

But until studies are complete, chronic Lyme patients and doctors who treat them say it’s cruel to deny patients the long-term antibiotics that many say improves their lives.

Long-term oral antibiotics prescribed by Dr. Nichola LaCava, of West Boylston, who travels to the Cape to see patients twice a month at Entire Healtha and Wellness in Mashpee “saved my life,” said landscaper Shelley Bouthillette.

She said she went to several physicians on the Cape and in Boston before seeing LaCava after a year and a half of misery with symptoms that including shaking, swelling of lymph nodes and one leg and unbearable itching. “I was bed ridden,” said Bouthillette, who credits LaCava for getting her back on her feet.

Donta, an infectious disease specialist in Falmouth who retired in 2015, said that one problem with clinical trials disproving the effectiveness of long-term antibiotics is that none of them lasted longer than three months.

His own studies — which are not considered double blind since they do not include a placebo group — demonstrate that a protocol involving different types of antibiotics can eliminate symptoms almost entirely, Donta said.

Solving the mystery of Lyme calls for a lot more research dollars, said Dr. Katherine Murray, of Plymouth, who said she follows Donta’s protocols but adds sulfa treatments to the antibiotics.

“There is so much we do not know about Lyme and so much that needs to be done,” said Murray, who said she only takes patients referred by their regular physicians. “It’s everywhere now.”

And so are the patients, as Lyme has reached every state but Hawaii.

The Dean Center, located in Spaulding at the Charlestown Naval Yard, has seen more than 650 Lyme and tick-borne disease patients since its launch and now has a waiting list of about a year for new patients, said Carole Stasiowski, spokeswoman for Spaulding Rehabilitation Hospital Cape Cod in Sandwich.

“It’s not going to go away. It’s only going to get worse,” Creel said. “Cape Cod Healthcare needs to realize they need to get a doctor here.”

— Follow Cynthia McCormick on Twitter: @Cmccormickcct.

**Comment**

Every state in the U.S. needs to realize they need to get doctors who treat tick borne infections!

Everytime I read something about Dr. Zubcevik I literally want to hug the woman.

This article truly brought up some great points.  Please share.


FREE: View “Under Our Skin” Best Primer on Lyme Disease

http://www.veoh.com/watch/v21055812yWtmpgB8  Approx. One hour forty five minutes.

If you have not watched the incredible documentary, “Under Our Skin,” please do so.  It reveals what patients and the doctors who dare to treat them go through.  It reveals the controversy up front and personally.  You will learn that Lyme is congenital, very probably a STD, and devastating.

The documentary covers so much ground but unfortunately doesn’t talk about the coinfections that typically come with Lyme (borrelia).

CDC Maps For Lyme Disease – NOT Accurate

Published on Aug 1, 2017

At Lymedisease.org’s June board meeting, CEO Lorraine Johnson presented information on how different sources map Lyme disease.

The CDC is systematically under reporting Lyme in the South and West causing researchers and medical professionals to use circular reasoning and who quip, “There is no Lyme here because there are no reported cases and there are no reported cases because there isn’t any Lyme here.”  

Please remember the little girls from Arkansas who could not get treatment because the head of infectious diseases claimed there were no reported cases in Arkansas and even admitted that they have the ticks that carry Lyme.  https://madisonarealymesupportgroup.com/2016/09/24/arkansas-kids-denied-lyme-treatment/

Then they had to recant that statement thanks to the girls’ mother who wasn’t having it:  https://madisonarealymesupportgroup.com/2017/03/02/hold-the-press-arkansas-has-lyme/

The next order of business is changing the surveillance criteria for reporting purposes.  Currently, if someone makes the CDC’s stringent criteria, I tell them that they’ve won the Lyme Lotto.  Few make the cut.  I didn’t, my husband didn’t, nor has hardly anyone else I work with.

CDC Laboratory Evidence for surveillance includes:   https://wwwn.cdc.gov/nndss/conditions/lyme-disease/case-definition/2017/  F

A positive culture for B. burgdorferi, OR
A positive two-tier test. (This is defined as a positive or equivocal enzyme immunoassay (EIA) or immunofluorescent assay (IFA) followed by a positive Immunoglobulin M1 (IgM) or Immunoglobulin G 2 (IgG) western immunoblot (WB) for Lyme disease) OR
A positive single-tier IgG2 WB test for Lyme disease3.

1. IgM WB is considered positive when at least two of the following three bands are present: 24 kilodalton (kDa) outer surface protein C (OspC)*, 39 kDa basic membrane protein A (BmpA), and 41 kDa (Fla). Disregard IgM results for specimens collected >30 days after symptom onset.

2. IgG WB is considered positive when at least five of the following 10 bands are present: 18 kDa, 24 kDa (OspC)*, 28 kDa, 30 kDa, 39 kDa (BmpA), 41 kDa flagellin (Fla), 45 kDa, 58 kDa (not GroEL), 66 kDa, and 93 kDa.

3. While a single IgG WB is adequate for surveillance purposes, a two-tier test is still recommended for patient diagnosis.

*Depending upon the assay, OspC could be indicated by a band of 21, 22, 23, 24 or 25 kDA.

Confirmed

A case of EM with exposure in a high incidence state (as defined above), OR
A case of EM with laboratory evidence of infection and a known exposure in a low incidence state, OR
Any case with at least one late manifestation that has laboratory evidence of infection.

In my case I had one positive band and an indeterminate in the IgM, and only 2 positive and 1 indeterminate for the IgG, yet I had migrating joint pain, severe fatigue, saw disco lights in my head, wild heart palpitations that would wake me up in the middle of the night (felt like a heart attack), chest pain, dizziness, horrific insomnia, pelvic pain, stiff and painful spine and neck, severe meningal headaches, confusion and memory loss, mood swings (rage, depression, couldn’t handle stress), and more.  

My husband and I were both pictures of health prior to this.

Thankfully a LLMD used the IGeneX extended Western Blot which is far more sensitive than the CDC’s two-tiered tests and diagnosed us clinically based on symptoms as well as evidence through testing.  For my story:  https://madisonarealymesupportgroup.com/2017/02/24/pcos-lyme-my-story/

The plot thickens when you understand that coinfections are often not reportable to the CDC in many states.  There is absolutely no way the CDC is getting an accurate picture of Lyme/MSIDS land.

Time for things to change.  And change they must.