No Good Test For Lyme Says Lab Director

R Esfandyarpour, A Kashi, M Nemat-Gorgani, J Wilhelmy and RW Davis. 2019
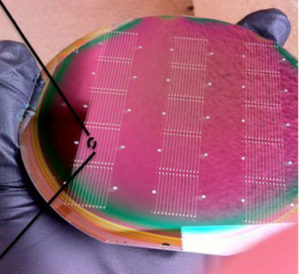
The research used nanomanufacturing techniques to embed large numbers of tiny electrodes within a silicon wafer. Each electrode, or nanoneedle, is comparable in size to a cell.
The researchers created a simplified blood sample for each patient that consisted of white blood cells (immune cells) in plasma, but without red blood cells and platelets. The scientists added each sample to a silicon wafer, and the electrodes then measured electrical impedance.
Impedance is a measure of how difficult it is for the electrical current to pass through the cells and/or plasma next to the electrodes. Critically, in the nanoelectric set-up, the authors say that change in impedance “results from cellular and molecular interactions”.
The key element of the test, which exposes the dramatic difference between patient and control samples, is to force the cells to use more energy than normal. The aim was to replicate at the cellular level a key aspect of ME/CFS: the way problems emerge when energy demands ramp up.
The researchers forced the cells to use more energy simply by adding sodium chloride — table salt — to the sample. In the jargon, the salt acts as a “hyperosmotic stressor”.
Some of the extra salt enters the cell and, through osmotic pressure, the salt draws water with it, causing the cell to swell up. The cell has to combat this tendency and so must use energy to power a molecular pump that pushes the extra salt back out of the cell.
The different response seen between the samples of patients and controls is striking. There is little change in electrical impedance for healthy cells. But after half an hour or so, there’s a huge increase in impedance for the samples from ME/CFS patients.
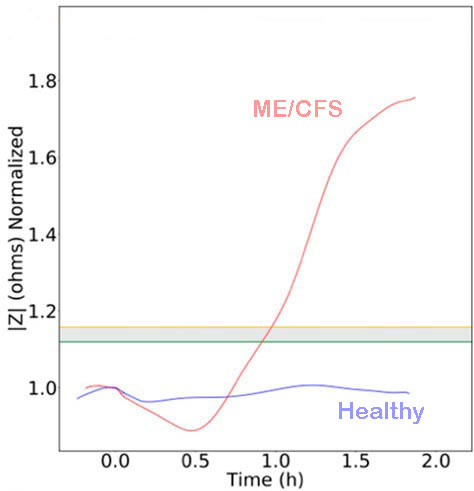
Lead author Rahmim Esfandyarpour told STAT News, “we’re forcing [patients’ cells to consume energy] and they are not happy… their reaction is different from the reaction of healthy cells”. The healthy cells seem to manage the situation comfortably.
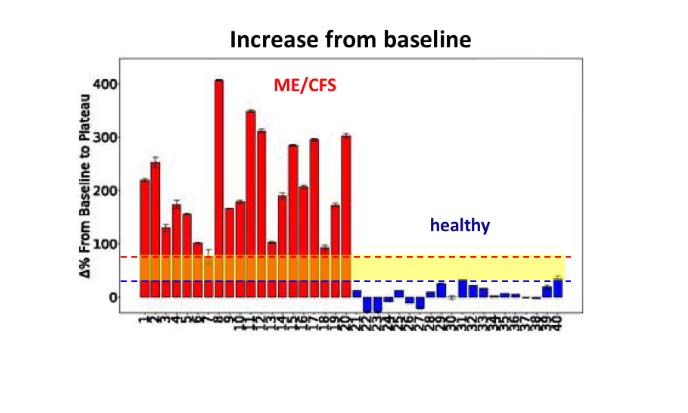
Strikingly, the increase in impedance for every single patient’s sample was substantially higher than for even the highest increase seen for any of the healthy controls’ samples.

It is the amount of clear daylight between patients and controls (indicated above by the yellow band in the graph) that makes these results so remarkable and so interesting. At the recent NIH ME/CFS conference, Dr Anthony Komaroff, a professor at Harvard Medical School, said that such a difference is “a clue to some underlying biology that could be causative of the symptoms of the illness.”
To make the findings more impressive, the authors also showed that the findings are highly reproducible. “If you test the same patient a week or month later, you get the exact same signal”, senior author Ron Davis told Medscape Medical News.
The study authors say that they believe these findings are unique to ME/CFS.
Commenting on the study, Chris Ponting, Professor of Medical Bioinformatics at Edinburgh University, said, “Excitingly, they appear to have discovered a distinguishing feature of ME/CFS, and one that can be measured simply and cheaply.” However, he stressed the need for replication of results and the need for sick controls. He said, “results should be replicated in a second cohort of individuals” and added that the device should be tested to see “whether it sets apart ME/CFS not just from general health but also from other disorders.”
Happily, the authors are planning to do just this. They have announced that they will be running a replication in a larger group of patients, — and will be including people with similar diseases as controls.
The researchers admit that they don’t know what biological differences lie behind the dramatic difference that the nanoelectricdevice shows between patients and controls. They speculate that they could be changes in the outer membrane of patients’ cells, amongst other possibilities. But the researchers are planning experiments to try to uncover the biology. The new work could be critical in understanding ME/CFS.
The authors are also working on adapting the technology to create a user-friendly platform for screening potential drugs. The basic idea is that any drugs that can make ME/CFS cells behave like healthy ones might be therapeutic in patients.
And the team have already started screening drugs that have already been approved for other conditions. If any of these prove effective in ME/CFS, they would be available to ME/CFS patients in a shorter timescale because they would have already passed through much of the regulatory process.
One of the most important uses for this new technology, if it proves to be accurate and if the differences are specific to ME/CFS, would be in helping to make robust diagnoses.
Davis’s team are already trying to adapt the technology so that it could be used in any doctor’s office (for now, it needs to be done in a lab). And the nanoelectric chips are very cheap to make commercially, so the test should be affordable and widely available.
In conjunction with existing measures, such as the Canadian Consensus Criteria, the nanoelectric device would make it relatively straightforward for physicians without specialist expertise to make a diagnosis.
Research in the US indicates that perhaps 80% of people with ME/CFS are undiagnosed. So there could be a million Americans who are sick with ME/CFS but don’t know what’s making them ill, and many more such people worldwide.
With a diagnosis, people could at least get advice on how to manage their condition more effectively until good treatments are available. That could improve life for a great many people, with the potential for making a huge difference once there are effective treatments.
___________________
For more: https://madisonarealymesupportgroup.com/2015/10/17/can-mecfs-be-caused-by-lyme/
https://madisonarealymesupportgroup.com/2019/03/12/unrest-documentary-about-me-cfs-on-netflix/
https://www.webwire.com/ViewPressRel.asp?aId=240044
“We have taken Lyme disease out of the woods and into the bedroom”
A report describing detection of the bacterial agent of Lyme disease in a genital lesion lends support to possible sexual transmission of the disease. The report was published in the prestigious Journal of Investigative Medicine High Impact Case Reports (https://journals.sagepub.com/articles/hic), and it supports a pilot study previously published in the online journal F1000Research(https://f1000research.com/articles/3-309/v3).
Lyme disease is a tickborne infection caused by Borrelia burgdorferi, a type of corkscrew-shaped bacteria known as a spirochete (pronounced spiro’keet). The Lyme spirochete resembles the agent of syphilis, long recognized as the poster child for sexually transmitted diseases. Recently the Centers for Disease Control and Prevention (CDC) announced that Lyme disease is much more common than previously thought, with over 400,000 new cases diagnosed each year in the United States. That makes Lyme disease in this country about twice as common as annual new cases of breast cancer and four times more common than annual new cases of HIV/AIDS, hepatitis C virus (HCV) infection and syphilis combined.
The current study was a collaborative effort by an international team of scientists. Researchers included Marianne Middelveen, a veterinary microbiologist from Calgary, Canada, molecular biologist Jennie Burke from Sydney, Australia, and nurse practitioner Melissa Fesler and internist Raphael Stricker from Union Square Medical Associates in San Francisco, CA.
“Our findings demonstrate the complexity of Lyme disease,” said Fesler, a lead author of the published study. “It explains why the disease is more common than one would think if only ticks were involved in transmission.”
In the study, researchers examined a genital lesion in a patient on treatment for Lyme disease. The lesion was found to contain live spirochetes that could be grown in special culture broth, and sophisticated immunology and molecular techniques revealed that the spirochetes were indeed Borrelia burgdorferi, the agent of Lyme disease. Testing for syphilis spirochetes and other pathogens was negative.
“The presence of live spirochetes in a genital lesion strongly suggests that sexual transmission of Lyme disease occurs,” said Middelveen. “We need to do more research to determine the risk of sexual transmission of this syphilis-like organism.”
Dr. Stricker pointed to the implications for Lyme disease diagnosis and treatment raised by the study. “We have taken Lyme disease out of the woods and into the bedroom,” he said. “We need to find better drugs to treat this runaway epidemic just like we did for HIV/AIDS and HCV.”
__________________
**Comment**
The 2014 pilot study should have sent a shock wave throughout the world. Should have, but didn’t. The CDC/IDSA/NIH barely rolled over in bed. 2014 study found in this link along with animal studies: https://madisonarealymesupportgroup.com/2017/02/24/pcos-lyme-my-story/
Notice it’s the same folks looking into this? Where’s the big studies? Where’s the power-players with all the money?
Lida Mattman, PhD. & Elizabeth Burgess, PhD. have been sounding the alarm on Bb being transmitted in a variety of ways since the 80’s: https://madisonarealymesupportgroup.com/2019/04/02/transmission-of-lyme-disease-lida-mattman-phd/
*Tokarz R, Tagliafierro T, Sameroff S, Cucura DM, Oleynik A, Che X, Jain K, Lipkin WI./Ticks and Tick-borne Diseases/, 2019 Apr 15. pii: S1877-959X(19)30033-0.https://doi.org/10.1016/j.ttbdis.2019.04.011
Abstract
We employed high throughput sequencing to survey the microbiomes of
Ixodes scapularis collected in New York and Connecticut. We examined 197
individual I. scapularis adults and pools from 132 adults and 197 nymphs.
We detected:
We did not detect Borrelia mayonii, Ehrlichia muris eauclairensis, Bartonella spp. or pathogenic Babesia species other than B. microti.
The most abundant bacterium(65%), and only rickettsial species identified, was the endosymbiont Rickettsia buchneri.
__________________
**Comment**
Nematodes (worms) have been found to hide borrelia spirochetes: https://madisonarealymesupportgroup.com/2016/06/03/borrelia-hiding-in-worms-causing-chronic-brain-diseases/ This is important from the standpoint that it shows anthelmintics may be helpful in some patients.

The black-legged tick, also known as the deer tick, can carry a variety of pathogens, including the bacteria that causes Lyme disease.
Syracuse, N.Y. — Bryon Backenson has taken ticks head-on since 1992, walking the woods and fields of New York and Connecticut to find, gather and test disease-carrying ticks.
“We go to 150 sites in spring and fall to collect ticks,” said Backenson, New York’s deputy director of communicable disease control. “In the years we’ve been doing this with staff and students, we’ve never had anybody who has gotten a tick-borne disease.”
Ticks, particularly the black-legged or deer tick, carry a variety of diseases. The most common and well-known is Lyme disease, caused by a bacteria carried in the tick’s gut.
Backenson said he and his fellow researchers are living proof that prevention works.
“We practice what we preach,” he said.

Upstate NY tick expert: How to protect yourself from Lyme disease
Ticks have been increasing as the climate warms, SUNY ESF researcher says.
He recommends that if you’re going to be in an area likely to have ticks, you do what researchers do:
— Wear light-colored clothes so you can see the dark ticks climbing on you.
— Tuck the bottoms of your pant legs into your socks to make it harder for ticks to reach your skin.
–Check your entire body at least every 24 hours, and remove any ticks you find on your skin.
— Consider using bug repellents that contain DEET for skin and permethrin for clothes. (Researchers in the field have one disadvantage here: They can’t wear bug repellent because they’re trying to catch ticks, not scare them away.)
“As long as people take the proper precautions and end up removing ticks, there’s a really good likelihood you’re not going to get some tick-borne disease,” Backenson said. “If you happen to get the rash from Lyme, or flu-like symptoms that make you suspect Lyme, early doses of antibiotics can cure relatively quickly the majority of cases we see.”
Backenson also said that most tick bites likely don’t lead to disease because the ticks are pulled off before they can ingest blood and inject the bacteria. He said New York has about 8,000 new cases of Lyme disease every year, but he estimates that New Yorkers get 40,000 to 50,000 tick bites every year.
“I firmly believe there are lots and lots of tick bites out there that don’t necessarily lead to disease,” Backenson said.
The health department has several videos on its website about how to keep ticks away, and how to pull them off when they bite.
The peak season for Lyme disease, late spring and summer, is approaching. That’s when the tick nymphs are feeding, and they account for the vast majority of Lyme disease cases. While nymphal ticks are less likely to carry the bacteria than adult ticks, nymphs are much smaller, so people don’t see them to remove in time. Nymphs also tend to be most active in summer, when more people are out in woods and fields.
In much of Upstate, about 25 percent of nymphs carry the Lyme bacteria. That jumps to about 50 percent in adults, which have fed more often than nymphs and have had more chances to get the bacteria from the blood of deer, rodents and other animals.
___________________
**Comment**
A few points:
Ticks are marvelous ecoadaptors and are impervious to the climate as shown by independent Canadian tick researcher John Scott: https://madisonarealymesupportgroup.com/2018/08/13/study-shows-lyme-not-propelled-by-climate-change/
“For blacklegged ticks, climate change is an apocryphal issue.” – John Scott
Again, researchers are about statistical significance – not individual significance. If you are the ONE sorry sucker who gets infected, all the statistics in the world become irrelevant. Why they state such things is beyond me. Treat each and EVERY tick bite seriously. https://madisonarealymesupportgroup.com/2016/12/07/igenex-presentation/ In this link we learn about a little girl that within 4-6 hours has facial palsy, and couldn’t walk or talk. Some cases escalate quickly.
As far as the bull’s eye rash goes, anywhere from 27-80% get it – hardly a sure thing. IF you have the rash, you HAVE LYME DISEASE. Period. If you don’t get the rash, it means nothing. The rash criteria has kept people from diagnosis and treatment for decades. Don’t let this happen to you. The “wait and see” if you develop symptoms approach has not and will not ever work. If you are bit by a tick, go in immediately and demand treatment. This could very well save your life and prevent you from chronic life-long symptoms.


Written
on May 19, 2019