Archive for the ‘research’ Category

Panic Attacks May be Lyme/MSIDS

I normally post current studies but this one from 2000 grabbed me as so many Lyme/MSIDS patients suffer with panic attacks, anxiety, and PTSD.  It’s also interesting to note that this symptom completely abated with appropriate “intensive doses of appropriate antimicrobial meds.”  This of course reveals the unrecognized fact that patients are often contending with far more than just Lyme (borrelia) and require different medications.  It also reveals that there can be an underlying infectious cause to things doctors consider to be psychological.  Lyme/MSIDS patients are often misdiagnosed as having mental disorders and are given drugs that actually suppress their immune systems further and allow the pathogens a perfect opportunity to worsen.  All the doxy in the world isn’t going to touch Babesia which requires anti-malarial drugs.  Please read my comment at the end of the Abstract.

_________________

https://www.ncbi.nlm.nih.gov/m/pubmed/15990495/

Panic attacks may reveal previously unsuspected chronic disseminated lyme disease.

Sherr VT. J Psychiatr Pract. 2000.

Abstract

The author describes the histories of three patients with panic-like episodes that turned out to be related to underlying, previously unsuspected tick-borne diseases. Each woman experienced symptoms that are not usual in panic disorder but are typical of neurological Lyme disease, including exquisite sensitivity to light, touch, and sounds, joint pain often in combination with cognitive changes including mental fogginess and loss of recent memory, and some degree of bizarre, shifting, and often excruciating neurological pain. Because these symptoms are atypical of primary panic disorder, they were very helpful in alerting the clinician to suspect an underlying physical illness. In each case, the results of testing revealed positive hallmarks of disseminated Lyme and other tick-borne diseases, including Lyme borreliosis caused by the spirochete, Borrelia burgdorferi, babesiosis, and ehrlichiosis.

Since beginning treatment with intensive doses of appropriate antimicrobial medications for their tick-borne infections, all three patients have become free of panic attacks. Treatment of their infections by a specialist in Lyme disease allowed one of the women to discontinue anti-anxiety medication completely and another to reduce the dose of medication to occasional use only. The third patient is no longer anxious but her depression is resolving more slowly despite the ongoing use of an antidepressant. Two of the patients have also needed ongoing medication for pain and other symptoms of late-stage, neurological Lyme disease.

__________________

Since testing is so abysmal, it is far more helpful to print out and check off symptom lists.  Take these lists with you to your doctor appointments:

https://madisonarealymesupportgroup.com/wp-content/uploads/2016/01/symptomlist.pdf

https://madisonarealymesupportgroup.com/2011/09/25/the-babesia-checklist-copyrighted-2011-james-schaller-md-mar-version-20/ (Circle symptoms you have)

https://madisonarealymesupportgroup.com/2011/09/25/the-bartonella-checklist-copyrighted-2011-james-schaller-md-version-11/ (Circle symptoms you have)

https://madisonarealymesupportgroup.com/2016/02/07/mycoplasma-treatment/  Read up on Mycoplasma as it is often a player and requires thoughtful treatment.

Treatment for Ehrlichiosis is fairly straight forward with doxycycline and normally that is a front-line med LLMD’s use for Lyme, so the good news is that you will lower the Lyme infection & deal with Ehrlichiosis at the same time.  The caveat for Lyme is the fact it is pleomorphic and requires far more than just doxy.  Please read this to understand the nuances of treating borrelia (Lyme):  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/

https://madisonarealymesupportgroup.com/2015/12/06/tips-for-newbies/

https://madisonarealymesupportgroup.com/2015/08/15/herxheimer-die-off-reaction-explained/

https://madisonarealymesupportgroup.com/2015/10/18/psychiatric-lymemsids/  The symptoms that can and often are a part of the Lyme/MSIDS picture are unbelievable and thankfully more and more is coming out on how devastating this illness is mentally.  I highly encourage you to get to a local support group to be around folks who understand.  Having camaraderie during this dark valley can be extremely helpful.  https://rawlsmd.com/lyme-support?
 

Ticks From U.S. Cats: Patterns of Infestation & Infection With Pathogens

https://www.sciencedirect.com/science/article/pii/S0304401718301596?via%3Dihub

Ticks from cats in the United States: patterns of infestation and infection with pathogens

Under a Creative Commons license
open access

Highlights

•

Tick infestations were documented on 332 cats from 18 states in the United States.

•

Adult and immature stages of Ixodes, Amblyomma, and Dermacentor were recovered.

•

Molecular assays documented infection with at least one pathogen in 17.1% of ticks.

•

One in 5 cats with ticks spent ≤30% time outdoors; 10 were reportedly indoor only.

•

Results show cats at risk of tick infestation and exposure to tick-borne pathogens.

Abstract

Ticks are an important but under recognized parasitic threat to cats in many areas of the United States. To characterize the species and stages of ticks most commonly recovered from cats and determine the prevalence of disease agents in the ticks, we conducted a survey of ticks removed from cats at veterinary practices in 18 states from April 2016 – June 2017.

A total of 796 ticks were submitted from 332 cats from 41 different veterinary practices. A single tick was submitted from the majority of cats, with a mean infestation intensity of 2.4 (range 1–46). The most common tick was Ixodes scapularis, accounting for 422/796 (53.0%) ticks submitted, followed by Amblyomma americanum (224/796; 28.1%) and Dermacentor variabilis (131/796; 16.5%); a few I. pacificus, I. banksi, D. occidentalis, A. maculatum, Rhipicephalus sanguineus, and Otobius megnini were also submitted.

A majority of ticks were adults (593/796; 74.5%); females predominated in all adult tick submissions including I. scapularis (277/327; 84.7% female), A. americanum(66/128; 51.6% female), and D. variabilis (75/126; 59.5% female). Immature ticks included 186 nymphs and 17 larvae and were primarily I. scapularis and A. americanum.

Adult I. scapularis were most reported to be attached to the dorsal head and neck; A. americanum to the abdomen and perianal region; and D. variabilis to the back and ear. Ticks were collected in every month; the largest number of submissions were in May and June (42.5% of ticks) and October and November (35.9% of ticks). Adults of I. scapularis were most commonly submitted October through December, A. americanum March through June, and D. variabilis May through July.

Cats with ticks were predominantly male (58.8%) and altered (76.2%), and most reportedly spent >30% of time outdoors, although 64/294 (21.8%) for which lifestyle estimates were provided were reported to live primarily (≤30% of time outside; n = 54) or entirely (100%; n = 10) indoors.

Assay of ticks removed from cats revealed I. scapularis were infected with Borrelia burgdorferi (25.7%) and Anaplasma phagocytophilum(4.4%); A. americanum were infected with Ehrlichia chaffeensis (1.3%); and D. variabilis were infected with spotted fever group Rickettsia spp. (3.1%). No ticks in this study tested positive for Cytauxzoon felis.

Pet cats, including those that live primarily indoors, are at risk of tick infestation, potentially exposed to tick-borne disease agents, and would benefit from routine tick control.

_______________

**Comment**

Some interesting points:

  1. Ticks were found on cats year-round
  2. The majority of ticks were ADULTS
  3. This study points out we need to essentially throw out the idea you can only get a tick bite in the spring and fall.  It also points out that adult ticks are to be taken just as seriously as nymphs.
  4. According to the study, molecular assays were used and the following pathogens found.  It says nothing of Bartonella, which is unfortunate.  We really need to determine why so many humans are infected with it.

Table 4. Pathogens detected in adult ticks recovered from cats.

Tick Pathogen % positive (No. positive/No. tested)
Ixodes scapularis Anaplasma phagocytophilum 4.4% (12/272)
Borrelia burgdorferi 25.7% (70/272)
Amblyomma americanum Cytauxzoon felis 0% (0/121)
Ehrlichia chaffeensis 1.7% (2/121)
Ehrlichia ewingii 0% (0/121)
Dermacentor variabilis Cytauxzoon felis 0% (0/123)
Rickettsia spp. 3.1% (4/123)

Tick & Mosquito-borne Diseases: Trends in the U.S.

https://www.gideononline.com/2018/05/04/tick-and-mosquito-borne-diseases-trends-in-the-united-states/

May 4th 2018

TICK AND MOSQUITO-BORNE DISEASES: TRENDS IN THE UNITED STATES

The following data are abstracted from Gideon and the Gideon e-book series. [1] Charts were created using an interactive tool driven by over 30,000 base graphs in the program. [2]

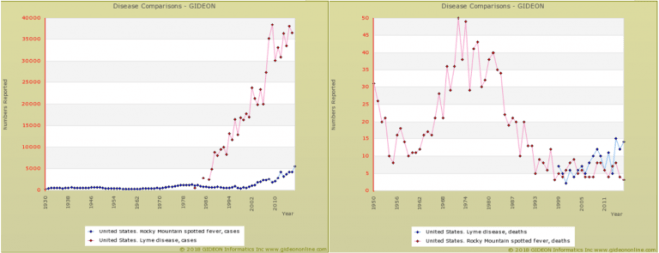
Chart 1 contrasts trends for reported incidence of Lyme disease and Rocky Mountain spotted fever (RMSF). Note that while rates of Lyme disease in 2016 are 15-fold those reported in 1987, those of RMSF increased by a factor of seven. The number of fatal cases for both diseases have remained similar in recent years (i.e., the relative case-fatality rate of Lyme disease has decreased)

LymeSF-768x295

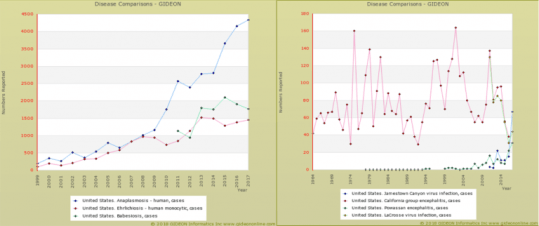
Chart 2 summarizes incidence data for a variety of tick-borne and mosquito-borne infections. Note that rates of Ehrlichiosis, Anaplasmosis, Babesiosis, Jamestown Canyon virus infection and Powassan encephalitis have increased since the year 2000. The incidence of LaCrosse encephalitis has decreased, while that of California encephalitis is largely unchanged.

MiscArbo-768x322

Charts 3 and 4 demonstrate that incidence and reported deaths for Western equine encephalitis, Eastern equine encephalitis, St. Louis encephalitis and West Nile fever have changed little in recent years.

Enceph-768x296

References:

Berger S. Infectious Diseases of the United States, 2018. 1,254 pages, 510 graphs, 16,672 references. Gideon e-books, https://www.gideononline.com/ebooks/country/infectious-diseases-of-the-united-states/
Gideon e-Gideon multi-graph tool, https://www.gideononline.com/cases/multi-graphs/

Rheumatological Presentation of Bartonella Koehlerae & Henselae: A Case Report – Chiropractors Please Read!

https://journals.lww.com/mdjournal/Fulltext/2018/04270/Rheumatological_presentation_of_Bartonella.32.aspx

Rheumatological presentation of Bartonella koehlerae and Bartonella henselae bacteremias: A case report

Mozayeni, Bobak, Robert, MDa; Maggi, Ricardo, Guillermo, PhDb; Bradley, Julie, Meredith, BSb; Breitschwerdt, Edward, Bealmear, DVMb,*

Medicine: April 2018 – Volume 97 – Issue 17 – p e0465
doi: 10.1097/MD.0000000000010465
Research Article: Clinical Case Report

Abstract

Introduction: Systemic Bartonella spp. infections are being increasingly reported in association with complex medical presentations. Individuals with frequent arthropod exposures or animal contact appear to be at risk for acquiring long standing infections with Bartonella spp.

Case report: This case report describes infections with Bartonella koehlerae and Bartonella henselae in a female veterinarian whose symptoms were predominantly rheumatologic in nature. Infection was confirmed by serology, polymerase chain reaction (PCR), enrichment blood culture, and DNA sequencing of amplified B koehlerae and B henselae DNA. Long-term medical management with antibiotics was required to achieve elimination of these infections and was accompanied by resolution of the patient’s symptoms. Interestingly, the patient experienced substantial improvement in the acquired joint hypermobility mimicking Ehlers–Danlos Syndrome (EDS) type III.

Conclusion: To facilitate early and directed medical interventions, systemic bartonellosis should potentially be considered as a differential diagnosis in patients with incalcitrant rheumatological symptoms and frequent arthropod exposures or extensive animal contact.

____________

**Comment**

Bartonella isn’t even on most GP’s radars regarding tick borne illness, and in fact many deny ticks can even transmit it, yet here we see that those with arthropod exposure and/or animal contact need to consider it.  Isn’t that just about everyone under the sun?

You need to know this for yourself, friends and family.  Educate the doctors!

This poor female veterinarian was put on clindamycin & rifampin but had to discontinue after becoming pregnant.  She had a thousand symptoms:  axillary lymphadenopathy from cat scratch disease (CSD) at 12 years of age, a tibial sesamoid bone fracture, plantar fasciitis, generalized muscle/joint pain, muscle weakness, headaches, tingling, and fatigue, cervical lymph node enlargement, extremity edema, ligamentous laxity, tenosynovitis, shoulder and elbow subluxations, elbow joint crepitus, progressively worsening joint hypermobility (Beighton score 7/9), multiple joint subluxations daily, and breast cysts, meeting criteria for benign classification.

Please note the joint popping with each articulation and continual joint subluxation issue.  

Chiropractors need to be told about this.  Please educate!  Send them this article.

I too had this bizarre popping of the joints with a lot of instability in the knees.  Treatment completely ameliorated this issue so treatment is primo important.

For more on Bartonella:  https://madisonarealymesupportgroup.com/2016/01/03/bartonella-treatment/

https://madisonarealymesupportgroup.com/2018/05/07/fox-news-bartonella-is-the-new-lyme-disease/  (Tons more links on Bart after this article)


Tens of Thousands Likely to Get TBD in Massachusetts This Year

https://www.bostonglobe.com/metro/2018/05/07/state-expert-tens-thousands-likely-will-get-tick-borne-disease-mass-this-year

Tens of thousands likely to get tick-borne disease in Mass. this year

06252007_25tick-5985597An adult deer tick.  MARK WILSON/GLOBE STAFF/FILE

By Felice J. Freyer and Martin Finucane GLOBE STAFF MAY 07, 2018

Few experiences are creepier than finding a tick attached to your body — except, perhaps, pondering the harmful germs the eight-legged critter may be injecting.

But ponder no more: If you send a tick to the University of Massachusetts Amherst, you can find out exactly what manner of microbe may have infected it — and possibly, you. Lyme disease is the most prevalent, but ticks carry several other viruses, parasites, and bacteria.

People who find a tick on their body can put it in a plastic bag — dead or alive — and mail it to the UMass lab. For a fee, confidential results come by e-mail within three days.

The germs ticks carry are a matter of growing concern: Last week, the Centers for Disease Control and Prevention said that reported illnesses from mosquito, tick, and flea bites more than tripled from 2004 to 2016.

In Massachusetts in 2017, some 8,692 people tested positive for Lyme disease, up from 5,829 four years earlier. But most cases are not reported, so Dr. Catherine M. Brown, deputy state epidemiologist, estimates that about 87,000 people a year are getting Lyme disease in the state.

Anaplasmosis/ehrlichiosis, the second most common tick-borne disease, was reported 341 times in 2013, and rose to 1,226 in 2017. That’s a 260 percent increase.

“So many people in Massachusetts are being impacted by at least one of these diseases,” Brown said. “It’s increasing dramatically.”

Stephen Rich, a microbiology professor and director of the Laboratory of Medical Zoology at UMass Amherst, said the increases probably reflect both more illness and more awareness. The biggest changes are in areas, such as upstate New York, where ticks are just starting to move in, he said.

In Massachusetts, ticks are always abundant statewide, so fluctuations in the tick population have little meaning, he said. People need to think of protecting themselves from bites in the same way they put on sunscreen at the beach — a necessary precaution, every year. To avoid tick bites, wear clothing treated with permethrin, apply DEET to the skin, check for ticks after being outside, and treat your yard and pets.

The TickReport program at UMass, which Rich runs, tested 14,000 ticks last year and expects to see many more in 2018. The program, which has received ticks from all 50 states, demonstrates the power of crowdsourcing, by gathering a wealth of information on the location of different tick species and the disease-causing microbes they carry, he said.

The only other way to track ticks is to drag a cloth over bushes and test the ticks that stick to it, he said. But that just gives a snapshot of a limited area on a given day. “That doesn’t reflect the ticks that are biting people,” Rich said.

TickReport goes directly to the source — the ticks’ human targets.

People who send a tick pay $50, $100, or $200, depending on how many microbes are being tested for.

A $100,000 federal grant announced Monday will subsidize those tests for Massachusetts residents. The goal is to get a better idea of the prevalence of the 23 potentially disease-causing microorganisms that ticks can carry.

Along with a discount added by the laboratory, the federal grant will lower the cost of the $100 test to $15 for the first 1,000 ticks the lab receives; then it will lower the $50 test to $15 for the next 1,500 ticks.

TickReport has been testing ticks since 2006. About 43 percent come from Massachusetts but not evenly across the state. Rich hopes to get more ticks from underrepresented areas, particularly the North Shore, the Berkshires, and Worcester County.

The tests don’t diagnose a person but they provide information that can guide medical decisions, Rich said.

TickReport has a partnership with another crowdsourcing project — TickSpotters at the University of Rhode Island, which is free:  http://www.tickencounter.org/tickspotters

With TickSpotters, people e-mail photos of bugs they think are ticks and provide basic information such as how long each was attached. The URI group identifies the species of tick and describes the risk of illness. Often the bugs pictured aren’t even ticks — the program has received photos of weevils and lice, said Thomas N. Mather, director of URI’s TickEncounter Resource Center:  http://www.tickencounter.org

Once participants get the basics from TickSpotters, those who want to know more are urged to send the tick to TickReport to find out if it was infected.

For example, a Rhode Island woman recently sent TickSpotters a photo of a tick that had been attached to her for less than a day, Mather said. The program identified it as an adult, female, black-legged tick, and advised that the risk of infection was low because the tick hadn’t been attached long enough to transmit illness. Still concerned, the woman sent the tick to UMass, where it was found to be infected with Lyme disease.

That doesn’t mean the woman has Lyme disease. A tick must feed for 36 to 48 hours before it transmits Lyme disease. (Please see my comment below)

“If I were her, I would just be alert for symptoms. But we try to stay out of it at this point,” Mather said. The rest is up to the woman and her physician.

After years of trying to educate the public about ticks and the risk of illness, and finding that misinformation remains rampant, Mather has found TickSpotters to be a useful educational tool.

“I don’t think there’s anyone more engaged in learning about ticks than someone who has had a tick on them,” he said. “We’re personalizing education, approaching people at their most needy and receptive.”

TickSpotters, which started in 2014, has received nearly 46,000 submissions, collecting a wealth of data about locations of different species of ticks nationwide — data no one has had time to analyze, Mather said.

_____________

**Comment**

While I love the work going on here a huge faux pax has been made regarding transmission times – and it’s a big deal:  https://madisonarealymesupportgroup.com/2017/04/14/transmission-time-for-lymemsids-infection/  

Transmission Time: Only one study done on Mice. At 24 hours every tick had transmitted borrelia to the mice; however, animal studies have proven that transmission can occur in under 16 hours and it occurs frequently in under 24 hours. No human studies have been done and https://www.dovepress.com/lyme-borreliosis-a-review-of-data-on-transmission-time-after-tick-atta-peer-reviewed-article-IJGM no studies have determined the minimum time it takes for transmission.
There’s also the issue of partially fed ticks transmitting more quickly: http://iai.asm.org/content/61/6/2396.full.pdf Ticks can spontaneously detach – and the authors of this study found that they did so 15% of the time in mice. They also state that about a tenth of questing nymphs appear distended with partially fed sub-adult ticks being common. This quicker transmission is due to spirochetes presiding in the salivary glands rather than the mid-gut.

https://madisonarealymesupportgroup.wordpress.com/2016/12/07/igenex Bob Giguere of IGeneX states a case of a little girl who went outside to play about 8:30a.m. and came inside at 10:30 with an attached tick above her right eye. By 2 o’clock, she had developed the facial palsy. At the hospital she was told it couldn’t be Lyme as the tick hadn’t been attached long enough. They offered a neuro-consult…..By 4pm she couldn’t walk or talk.
A Lyme literate doctor trained by ILADS met the family in his office on a Saturday, gave her an intramuscular injection of antibiotics and within 2 hours the palsy was gone. He continued her treatment for approximately 4 weeks.

Do NOT take a “wait and see” approach when it comes to this plague.  Get on it and get on it now.  The longer you wait the greater the potential for it to embed deep within the body including the brain.  Every SINGLE attached tick should be taken as seriously as a heart attack.  Please spread the word about this.  The myths must END!