Archive for the ‘research’ Category

Study Shows Berberine Induces Cell Death in Leukemia

https://science.news/2019-03-21-berberine-induces-cell-death-in-leukemia-cells-study.html

Berberine induces cell death in leukemia cells – study

A study published in The American Journal of Chinese Medicine revealed that a compound called berberine induces cell death in leukemia cells. In this study, the subcellular localization and the apoptotic mechanisms of berberine were investigated.

  • Berberine is an isoquinoline alkaloid found in medicinal plants used in traditional and folk medicines.
  • In the study, researchers at Nagasaki International University in Japan first treated human promyelocytic leukemia cells with berberine, then examined its antiproliferative activity.
  • Five to 15 minutes after treatment, berberine exhibited powerful antiproliferative activity in the cells.
  • Then, the researchers investigated the effect of berberine on inducing cell death and found that the compound induced cell death in leukemia cells.
In conclusion, these findings suggest that berberine can induce cell death in leukemia cells immediately after administration.

Journal Reference:

Okubo S, Uto T, Goto A, Tanaka H, Nishioku T, Yamada K, Shoyama Y. BERBERINE INDUCES APOPTOTIC CELL DEATH VIA ACTIVATION OF CASPASE-3 AND -8 IN HL-60 HUMAN LEUKEMIA CELLS: NUCLEAR LOCALIZATION AND STRUCTURE–ACTIVITY RELATIONSHIPS. The American Journal of Chinese Medicine. 6 October 2017; 45(7): 1497-1511. DOI: 10.1142/S0192415X17500811

___________________

**Comment**

Berberine is a chemical found in several plants including European barberry, goldenseal, goldthread, Oregon grape, phellodendron, and tree turmeric.  It might cause stronger heartbeats which might help heart conditions.  It also helps regulate how the body uses sugar in the blood which may help with diabetes. It also might also be able to kill bacteria and reduce swelling.  https://www.webmd.com/vitamins/ai/ingredientmono-1126/berberine

https://draxe.com/berberine/  According to Dr. Axe, research on berberine shows benefit for the following conditions:

  • Anti-aging
  • Diabetes
  • Gastrointestinal infections
  • Heart disease
  • High cholesterol
  • Hypertension (high blood pressure)
  • Immune challenges
  • Joint problems
  • Low bone density
  • Weight control

Another great article by Dr. Mercola:  https://articles.mercola.com/sites/articles/archive/2015/06/22/berberine-benefits.aspx

Berberine was able to control blood sugar and lipid metabolism as effectively as metformin, with researchers describing berberine as a “potent oral hypoglycemic agent.”4

A separate meta-analysis also revealed “berberine has comparable therapeutic effect on type 2 DM [diabetes mellitus], hyperlipidemia and hypertension with no serious side effect.”5

There is also evidence for reducing inflammation, oxidative stress, tumor growth, & depression and helping with infections, all of which Lyme/MSIDS patients can struggle with.

Ability of Stationary Phase Persister/Biofilm Microcolonies of Borrelia Burgdorferi to Cause More Severe Disease

https://globallymealliance.org/gla-pov-ability-stationary-phase-persister-biofilm-microcolonies-borrelia-burgdorferi-cause-severe-disease/?

Ability of Stationary Phase Persister/Biofilm Microcolonies of Borrelia burgdorferi to Cause More Severe Disease

borrelia-burgdorferi_mice

by Timothy Sellati, Ph.D., Chief Scientific Officer, GLA

Ying Zhang, Ph.D., a Global Lyme Alliance (GLA)-funded investigator, and his team at Johns Hopkins University just published a seminal study in the journal Discovery Medicine titled “Stationary phase persister/biofilm microcolony of Borrelia burgdorferi causes more severe disease in a mouse model of Lyme arthritis: Implications for understanding persistence, post-treatment Lyme disease syndrome (PTLDS), and treatment failure”.

Lyme disease patients, infected via tick bite with the bacterial spirochete B. burgdorferi, are routinely treated with two to four weeks of Doxycycline, Amoxicillin, or Cefuroxime, which is curative in many cases if treated at the onset of the infection. However, research shows that despite treatment, up to 20% of patients continue to suffer lingering symptoms of fatigue, pain, or joint and muscle aches, and neurocognitive manifestations that last 6 months or more.  This clinically-defined condition is known as post-treatment Lyme disease syndrome (PTLDS).  A long-standing mystery is whether development of PTLDS reflects

  1. persistence of B. burgdorferi in a patient’s tissues, consistent with chronic infection, or
  2. self-perpetuating inflammation caused by tissue damage triggered by the original infectious insult.

Zhang and colleagues published several influential papers over the past five years revealing a potential answer to this mystery. His lab showed that in vitro stationary phase (non-growing) cultures of B. burgdorferi contain different morphological variants. These bacterial variants include planktonic (free-swimming) spirochetal forms, round body forms, and aggregated microcolony (biofilm-like) forms, which have varying levels of persistence (e.g., the capacity to tolerate antibiotic exposure) in comparison to the log phase culture, which mainly consists of rapidly growing spirochetal forms with no or few persisters. B. burgdorferi develops into these morphological variants under stress conditions but their relevance to severe and persistent Lyme disease was unclear until the publication of this new study.

Zhang et al. report that biofilm-like microcolony (MC) and planktonic (free-swimming spirochete and round body; SP) variants found in stationary phase cultures were not only more tolerant of exposure to antibiotics but also caused more severe arthritis in mice than the log phase spirochetes (LOG). Importantly, the authors show that the murine infection caused by LOG could be eradicated by Ceftriaxone (CefT) whereas the persistent infection established with MC could not be eradicated by Doxycycline (Doxy), CefT, or Vancomycin (Van), or Doxy+CefT or Van+CefT, but could only be eradicated by the persister drug combination Daptomycin (Dapto)+Doxy+CefT.

This GLA-funded work establishes for the first time that:

Varying levels of persistence and the severity of disease pathology caused by infection with B. burgdorferi is linked to different morphological forms of the spirochete.

The following facts highlight the importance of this novel discovery. The number of patients developing PTLDS, or chronic Lyme, which is less clinically well-defined, is on the rise; a trend that is consistent with the rise in annual incidence of Lyme disease, which is ~427,000 cases. The absence of a full understanding of the cause(s) of PTLDS hampers efforts to effectively treat patients suffering with this syndrome. The authors demonstrated that the degree of persistence or persistent infection varied with different inoculae, where biofilm-like microcolony inoculae produced a more severe and persistent disease that could not be eradicated by the current Lyme antibiotics or even some two-drug combinations but could be eradicated by the persister drug combination Dapto+Doxy+CefT. In contrast, the disease induced by the log phase spirochetal forms is more readily eradicated by CefT. That the inclusion of persister drug Dapto, in combination with Doxy and CefT, is critical for eradicating the persistent infection established by persister inoculae validates the relevance of Dr. Zhang’s GLA-funded efforts to screen for drugs or drug combinations against stationary phase bacteria enriched in persisters in vitro, which were published by Feng et al. in 2014 and 2015 (see influential papers here).

Finally, the reported findings may not only provide a new understanding of PTLDS and perhaps chronic Lyme disease, but also will inform and accelerate development and testing of novel persister drug combination regimens that can more effectively cure persistent Lyme disease in the future. GLA’s goal in the near future will be to support human clinical trials to evaluate if the persister drug combination could more effectively treat or cure patients with PTLDS/chronic Lyme disease.

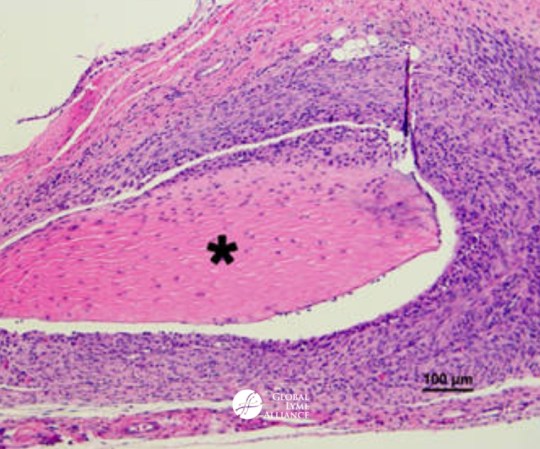
Pictured: Image of joint histopathology taken from a mouse infected with micro-colony/biofilm-like B. burgdorferi. Read Dr. Zhang’s full paper here.


timothy sellatiTimothy J. Sellati, PH.D. is Chief Scientific Officer at Global Lyme Alliance

As GLA’s Chief Scientific Officer, Dr. Sellati leads GLA’s research initiatives to accelerate the development of more effective methods of diagnosis and treatment of Lyme and other tick-borne diseasesmorphological variantshttps://www.dovepress.com/evaluation-of-in-vitro-antibiotic-susceptibility-of-different-morpholo-peer-reviewed-article-IDR  Metronidazole led to reduction of spirochetal structures by ~90% and round body forms by ~80%. Tigecycline and tinidazole treatment reduced both spirochetal and round body forms by ~80%–90%.
In terms of qualitative effects, only tinidazole reduced viable organisms by ~90%. Following treatment with the other antibiotics, viable organisms were detected in 70%–85% of the biofilm-like colonie

_________________

**Comment**

Great work by Zhang et al.!  Paper found here:  http://www.discoverymedicine.com/Jie-Feng/2019/03/persister-biofilm-microcolony-borrelia-burgdorferi-causes-severe-lyme-arthritis-in-mouse-model/

Unfortunately, they use the falsely skewed 10-20% percentages regarding the PTLDS group when microbiologist Holly Ahern argues convincingly that when ALL subgroups are added, it’s more like 60% that develop chronic/persistent symptoms:  https://madisonarealymesupportgroup.com/2019/02/25/medical-stalemate-what-causes-continuing-symptoms-after-lyme-treatment/  This is quite important and reveals the true state of affairs.

When I heard Dr. Zhang a few years back, he was working on this very concept, and please know the mycobacterium drugs have many side-effects that require close monitoring:  https://madisonarealymesupportgroup.com/2016/10/09/mycobacterium-drugs-for-ld/

The drug we used effectively throughout our treatment was Tinidazole which we pulsed throughout the entire time with 2-3 other antibiotics focusing on Bb’s different morphological variants as well as the various coinfections we had:  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/  Dr. Eva Sapi found:

https://www.dovepress.com/evaluation-of-in-vitro-antibiotic-susceptibility-of-different-morpholo-peer-reviewed-article-IDR  Metronidazole led to reduction of spirochetal structures by ~90% and round body forms by ~80%. Tigecycline and tinidazole treatment reduced both spirochetal and round body forms by ~80%–90%.  In terms of qualitative effects, only tinidazole reduced viable organisms by ~90%. Following treatment with the other antibiotics, viable organisms were detected in 70%–85% of the biofilm-like colonies.


Post Treatment Lyme Disease Syndrome: A Review of its Origin & its Consequences in the Socio-economic Sphere

https://www.ommegaonline.org/article-details/The-Post-Lyme-Disease-Treatment-Syndrome-(PTLDS)-a-review-of-its-origin-and-its-consequences-in-the-socio-economic-sphere./2407#.XKLo6qbumDo.linkedin

The Post-Lyme Disease Treatment Syndrome (PTLDS) a review of its origin and its consequences in the socio-economic sphere.

DR. JOSE LAPENTA
Lapenta J, Lapenta JM

Conclusion

It is demonstrated that the chronic symptoms of Lyme disease are a reality, referred to as:

Chronic Lyme disease (CLD); or Syndrome- Post-treatment of Lyme disease (PTLDS).

As we said at the beginning, the CDC does not recognize the term Chronic Lyme Disease (CLD) because it is confusing[1].

With respect to this, we conclude that the CDC is wrong because data demonstrated that months or years after adequate treatments with antibiotics, patients can have the same or worse symptoms, which gives truth to the term: chronic Lyme disease (CLD).

On the other hand, the CDC alleges that the term Post-treatment of Lyme disease syndrome (PTLDS) is used by some scientists to define symptoms after the treatment of the disease and that it is due to “unknown cause”:

With regard to this aspect, the “so called” Post-treatment of Lyme disease syndrome (PTLDS), is the same chronic Lyme disease, consisting of:

  • Lyme positive patients who were never treated.
  • Positive Lyme patients who after treatment in acute phase relapsed months or years later, and reached the secondary or late stage with symptoms equal or more severe than at the beginning.

Patients who were misdiagnosed due to lack of effective diagnostic tests and reached the chronic stage. Today the CDC recognizes that its diagnostic tests are not 100% effective.

Well-diagnosed Lyme patients who never responded to the treatments recommended by the CDC.

  • We also disagree with the CDC about the definition of “unknown cause” when most studies and research show that it is a chronic encephalopathy produced by Borrelia burgdorferi, either by:
  • Its persistence in the bloodstream, cerebrospinal fluid and tissues due to resistance to treatment, under the well-known mechanism of “Biofilm”.
  • Generation of neurological damage due to the persistence of Borrelia burgdorferi in tissues that do not regenerate, such as the nerve cells.
  • An inflammatory process that remained in the nervous system and tissues after eliminating the causative agent.
In some patients, the coexistence of other diseases such as Erlichiosis, Babesiosis and Bartonellosis, which worsen the symptoms and obstruct the treatment.

We find with an unprotected society, the reality is that thousands of patients are discarded as positive Lyme after 4 months of treatment, because the treatment guidelines of the CDC say that in that time or less you will be cured, which we prove is false in a good proportion of patients.

In 2019 May, is the limit for the recognition of ICD-11 Codes of Lyme disease (International classification of diseases), and the WHO refuse to recognize them all, which will cause patients without coverage for their treatments. One of the unrecognized codes is congenital Lyme[46-54] .

The global community of patients with Lyme must organize well and adequately claim from health authorities such as the World Health Organization (WHO) to recognize the entire Lyme codes, and ensure coverage of their treatment at all levels.

The Syndrome post-treatment of Lyme disease (PTLDS), which is nothing more than the ”chronic symptoms” of the disease, is being used perversely to cover the reality of this disease, avoid coverage by health insurance, and tell patients: “you have nothing, go to a psychologist” … when their blood and brain are sailing in a sea of ​​Borrelias.

Comments

With regard to the proposal of new treatment guidelines for Lyme disease, we prefer to wait for what the health authorities at the world level will propose; then we will make a new publication about it.

Dr. José Lapenta Dermatologist

Dr. José M. Lapenta Md

Acknowledgments

To the Lyme world community that fights for its rights to be treated as real patients and not as psychiatric patients.

To my son J. Miguel MD, for his logistical support and co-author.

To all patients with Lyme especially Stacy Cellier Gomez whose story was quite motivating.

References
  1. Post-Treatment Lyme Disease Syndrome. (2018) Cent Dis Control Prev.

Pubmed| Crossref| Others

  1. Lapenta, J., Lapenta, J.M. Lyme Disease and Dementia, Alzheimer, Parkinson, Autism, an Easy Way to Destroy your Brain. (2018) Inv Dermatol Venereology Res 4(1): 30-43.

Pubmed| Crossref| Others

  1. Krupp, L.B., Masur, D., Schwartz, J., et al. Cognitive functioning in late Lyme borreliosis. (1991) Arch Neurol 48(11): 1125–1129.

Pubmed| Crossref| Others

  1. Benke, T., Gasse, T., Hittmair-Delazer, M., et al. Lyme encepha- lopathy: Long-term neuropsychological deficits years after acute neuroborreliosis. (1995) Acta Neurol Scand 91(5): 353-357.

Pubmed| Crossref| Others

  1. Bujak, D.I., Weinstein, A., Dornbush, R.L. Clinical and neurocognitive features of the post Lyme syndrome. (1996) J Rheumatol 23(8): 1392-1397.

Pubmed| Crossref| Others

  1. Gaudino, E.A., Coyle, P.K., Krupp, L.B. Post-Lyme syndrome and chronic fatigue syndrome. Neuropsychiatric similarities and dif- ferences. (1997) Arch Neurol 54(11): 1372-1376.

Pubmed| Crossref| Others

  1. Bloom, B.J., Wyckoff, P.M., Meissner, H.C., et al. Neurocognitive abnormalities in children after classic manifestations of Lyme disease. (1998) Pediatr Infect Dis J 17(3): 189-196.

Pubmed| Crossref| Others

  1. Elkins L.E., Pollina, D.A., Scheffer, S.R., et al. Psychological states and neuropsychological performances in chronic Lyme disease. (1999) Appl Neuropsychol 6(1): 19-26.

Pubmed| Crossref| Others

  1. Kaplan, R.F., Jones-Woodward, L., Workman, K., et al. Neuropsychological deficits in Lyme disease patients with and without other evidence of central nervous system pathology. (1999) Appl Neuropsychol 6(1): 3-11.

Pubmed| Crossref| Others

  1. Klempner M.S., Hu, L.T., Evans, J., et al. Two controlled trials of antibiotic treatment in patients with persistent symptoms and a history of Lyme disease. (2001) N Engl J Med 345(2): 85-92.

Pubmed| Crossref| Others

  1. Morgen, K., Martin, R., Stone, R.D., et al. FLAIR and magnetization transfer imaging of patients with post-treatment Lyme disease syndrome. (2001) Neurology 57(11): 1980-1985.

Pubmed| Crossref| Others

  1. Weinstein, A., Britchkov, M. Lyme arthritis and post-Lyme disease syndrome. (2002) Curr Opin Rheumatol 14(4): 383-387.

Pubmed| Crossref| Others

  1. Shotland, L.I., Mastrioanni, M.A., Choo, D.L., et al. Audiologic manifestations of patients with post-treatment Lyme disease syndrome. (2003) Ear Hear 24(6): 508-517.

Pubmed| Crossref| Others

  1. Steven, E. P., Joseph, J. B., Nick, S. H., et al. Chronic infection in ‘post-Lyme borreliosis syndrome. (2005) Int J Epid 34(6): 1439-1440.

Pubmed| Crossref| Others

  1. Cairns, V., Godwin, J. Post-Lyme borreliosis syndrome: a meta-analysis of reported symptoms. (2005) Int J Epidemiol 34(6): 1340-1345.

Pubmed| Crossref| Others

  1. Pícha, D., Moravcova, L., Lasikova, S., et al. Symptoms of post-Lyme syndrome in long-term outcome of patients with neuroborreliosis. (2006) Scand J Infect Dis 38(8): 747-748.

Pubmed| Crossref| Others

  1. Pfister, H.W., Rupprecht, T.A. Clinical aspects of neuroborreliosis and post-Lyme disease syndrome in adult patients. (2006) Int J Med Microbiol 40: 11-6.

Pubmed| Crossref| Others

  1. Auwaerter, P.G. Point: antibiotic therapy is not the answer for patients with persisting symptoms attributable to lyme disease. (2007) Clin Infect Dis 45(2): 143-148.

Pubmed| Crossref| Others

  1. Stricker, R.B. Counterpoint: long-term antibiotic therapy improves persistent symptoms associated with lyme disease. (2007) Clin Infect Dis 45(2): 149-157.

Pubmed| Crossref| Others

  1. McAuliffe, P., Brassard, M.R., Fallon, B. Memory and executive functions in adolescents with posttreatment Lyme disease. (2008) Appl Neuropsychol 15(3): 208-219.

Pubmed| Crossref| Others

  1. Hassett, A.L., Radvanski, D.C., Buyske, S., et al. Role of psychiatric comorbidity in chronic Lyme disease. (2008) Arthritis Rheum 59(12): 1742-1749.

Pubmed| Crossref| Others

  1. Moniuszko, A., Czupryna, P., Zajkowska, J., et al. Post Lyme syndrome as a clinical problem. (2009) Pol Merkur Lekarski 26(153): 227-230.

Pubmed| Crossref| Others

  1. Clarissou, J., Song, A., Bernede, C., et al. Efficacy of a long-term antibiotic treatment in patients with a chronic Tick Associated Poly-organic Syndrome (TAPOS). (2009) Med Mal Infect 39(2): 108-115.

Pubmed| Crossref| Others

  1. Markeljevic, J., Sarac, H., Rados, M. Tremor, seizures and psychosis as presenting symptoms in a patient with chronic lyme neuroborreliosis (LNB). (2011) Coll Antropol 35(1): 313-318.

Pubmed| Crossref| Others

  1. Schutzer, S.E., Angel, T.E., Liu, T., et al. Distinct cerebrospinal fluid proteomes differentiate post-treatment lyme disease from chronic fatigue syndrome. (2011) PLoS One 6(2): e17287.

Pubmed| Crossref| Others

  1. Chandra, A., Wormser, G.P., Marques, A.R., et al. Anti-Borrelia burgdorferi antibody profile in post-Lyme disease syndrome. (2011) Clin Vaccine Immunol 18(5): 767-771.

Pubmed| Crossref| Others

  1. Fallon, B.A., Petkova, E., Keilp, J.G., et al. A reappraisal of the u.s. Clinical trials of post-treatment lyme disease syndrome. (2012) Open Neurol J 6: 79-87.

Pubmed| Crossref| Others

  1. Klempner, M.S., Baker, P.J., Shapiro, E.D., et al. Treatment trials for post-Lyme disease symptoms revisited. (2013) Am J Med 126(8): 665-669.

Pubmed| Crossref| Others

  1. Aucott, J.N., Rebman, A.W., Crowder, L.A., et al. Post-treatment Lyme disease syndrome symptomatology and the impact on life functioning: is there something here? (2013) Qual Life Res 22(1): 75-84.

Pubmed| Crossref| Others

  1. Aucott, J.N., Crowder, L.A., Kortte, K.B. Development of a foundation for a case definition of post-treatment Lyme disease syndrome. (2013) Int J Infect Dis 17(6): 443-449.

Pubmed| Crossref| Others

  1. Batheja, S., Nields, J.A., Landa, A., et al. Post-treatment lyme syndrome and central sensitization. (2013) J Neuropsychiatry Clin Neurosci 25(3): 176-186.

Pubmed| Crossref| Others

  1. Crowder, L.A., Yedlin, V.A., Weinstein, E.R., et al. Lyme disease and post-treatment Lyme disease syndrome: the neglected disease in our own backyard. (2014) Public Health 128(9): 784-791.

Pubmed| Crossref| Others

  1. Scieszka, J., Dabek, J., Cieslik, P. Post-Lyme disease syndrome. (2015) Reumatologia 53(1): 46-48.

Pubmed| Crossref| Others

  1. Weitzner, E., McKenna, D., Nowakowski, J., et al. Long-term Assessment of Post-Treatment Symptoms in Patients With Culture-Confirmed Early Lyme Disease. (2015) Clin Infect Dis 61(12): 1800-1806.

Pubmed| Crossref| Others

  1. Blaut-Jurkowska, J., Jurkowski, M. Post-Lyme disease syndrome. (2016) Pol Merkur Lekarski. 40(236): 129-133.

Pubmed| Crossref| Others

  1. Nemeth, J., Bernasconi, E., Heininger, U., et al. For The Swiss Society For Infectious Diseases And The Swiss Society For Neurology. Update of the Swiss guidelines on post-treatment Lyme disease syndrome. (2016) Swiss Med Wkly 146: 14353.

Pubmed| Crossref| Others

  1. Aucott, J.N., Soloski, M.J., Rebman, A.W., et al. CCL19 as a chemokine risk factor for posttreatment Lyme disease syndrome: A prospective clinical cohort study. (2016) Clin Vaccine Immunol 23(9): 757–766.

Pubmed| Crossref| Others

  1. Rebman, A.W., Aucott, J.N., Weinstein, E.R., et al. Living in Limbo: Contested Narratives of Patients with Chronic Symptoms Following Lyme Disease. (2017) Qual Health Res 27(4): 534-546.

Pubmed| Crossref| Others

  1. Rebman, A.W., Bechtold, K.T., Yang, T., et al. clinical, symptom, and quality-of-life characterization of a well-defined group of patients with posttreatment Lyme disease syndrome. (2017) Front Med (Lausanne) 4: 224.

Pubmed| Crossref| Others

  1. Hanna, A.F., Abraham, B., Hanna, A., et al. Effects of intravenous ketamine in a patient with post-treatment Lyme disease syndrome. (2017) Int Med Case Rep J 10: 305-308.

Pubmed| Crossref| Others

  1. Weinstein, E.R, Rebman, A.W., Aucott, J.N., et al. Sleep quality in well-defined Lyme disease: a clinical cohort study in Maryland. (2018) Sleep 1: 41(5).

Pubmed| Crossref| Others

  1. Cervantes, J., Doctor says you are cured, but you still feel the pain. Borrelia DNA persistence in Lyme disease. (2017) Microbes Infect 19(9-10): 459-463.

Pubmed| Crossref| Others

  1. Touradji, P., Aucott, J.N., Yang, T., et al. Cognitive Decline in Post-treatment Lyme Disease Syndrome. (2018) Arch Clin Neuropsychol.

Pubmed| Crossref| Others

  1. Davidsson, M. The Financial Implications of a Well-Hidden and Ignored Chronic Lyme Disease Pandemic. (2018) Healthcare Basel 6(1): 16.

Pubmed| Crossref| Others

  1. Lapenta, J., Lapenta, J.M. understanding the Lyme disease, Classification and codes. (2018) Ommega Pub 4(1): 1-11.

Pubmed| Crossref| Others

  1. Lapenta, J., Lapenta, J.M. Understanding the Lyme Disease, Classification And Codes. (2017)

Pubmed| Crossref| Others

  1. Lapenta, J., Lapenta, J.M. Minocycline, Alzheimer’s, and Other Neurological Disorders.

Pubmed| Crossref| Others

  1. Centers for Disease Control and prevention.

Pubmed| Crossref| Others

  1. Online ICD9/ICD9CM codes.

Pubmed| Crossref| Others

  1. ICD-10 Version 2016.

Pubmed| Crossref| Others

  1. ICD-10-CM Codes.

Pubmed| Crossref| Others

  1. Information from World Health Organization (WHO): List of Official ICD-10 Updates. For the ICD-11 revision: The ICD 11th Revision is due by 2017 (Archived, Feb. 2014); ICD Revision Timelines and ICD-11 Beta Draft (online beta-version of ICD-11). Source:

Pubmed| Crossref| Others

  1. International Statistical Classification of Diseases and Related Health Problems.

Pubmed| Crossref| Others

_________________

For a list of 700 peer-reviewed articles on the persistence of Lyme:  https://www.ilads.org/wp-content/uploads/2018/07/CLDList-ILADS.pdf

Great article by microbiologist Holly Ahern where she takes the PTLDS moniker head-on showing that the actual number of those with persistent/chronic symptoms is more like 60%:  https://madisonarealymesupportgroup.com/2019/02/25/medical-stalemate-what-causes-continuing-symptoms-after-lyme-treatment/

Please spread the word on this as researchers seeing the falsely skewed low percentages of 10-20% aren’t going to see the relevance in studying this further.  If; however, they see that 60% of patients are affected chronically, that puts the whole matter into a different urgent category.  We need to point out CDC/NIH errors.


Borrelia bissetti Found in Canadian Deer Ticks

https://www.ncbi.nlm.nih.gov/m/pubmed/30395480/

Identification of Borrelia bissettii in Ixodes scapularis ticks from New Brunswick, Canada.

Lewis J, et al. Can J Microbiol. 2019.

Abstract

Lyme disease is a tick-borne disease that is emerging in Canada. The disease is caused by spirochetes of the Lyme borreliosis group, which is expanding as new species are discovered. In Canada, Lyme disease risk has so far been assessed primarily by detection of Borrelia burgdorferi sensu stricto. Of Ixodes scapularis ticks collected between 2014 and 2016 in New Brunswick, Canada, 7 were shown to be infected with Borrelia bissettii by nested PCR and sequencing of 5 B. bissettii genes. Since different Borrelia species are associated with different clinical manifestations and are not detected with the same diagnostic tests, the identification of a previously undocumented or underreported pathogenic Borrelia species has important implications for public and veterinary medicine.

_________________

**Comment**

Again, the important issue here is that current CDC 2-tiered tests only test for ONE strain of borrelia when there are 300 and counting strains worldwide being transported everywhere by migrating birds, rodents, lizards, and mammals – including humans.

Before you discount Borrelia bissetti as being “somewhere else,” please know it was found in Chicago rodents:  https://www.ncbi.nlm.nih.gov/pubmed/11075925. These strains are unlike previous Borrelia isolates from NW Illinois and Wisconsin.

This excellent pdf has studies of bissetti in everything from mice to human heart valves: ws-B.Bissettii1  The pdf also makes an excellent point that desperately needs to be addressed:  Borrelia strains sequenced are strains that have been grown in culture medium. What about the diverse strains identified in the Southeastern United States that cannot be cultured? It also gives two studies showing that changing criteria of the Western Blot & mixing borrelia strains increased testing sensitivity.

 Time for the CDC to roll up their sleeves and deal with this. It is way past time.

For more on testing:  https://madisonarealymesupportgroup.com/2018/01/16/2-tier-lyme-testing-missed-85-7-of-patients-milford-hospital/

https://madisonarealymesupportgroup.com/2018/10/12/direct-diagnostic-tests-for-lyme-the-closest-thing-to-an-apology-you-are-ever-going-to-get/

Key quote:  

“These serologic tests cannot distinguish active infection, past infection, or reinfection.”

In plain English, these tests don’t show squat.


Can You ‘Catch’ Cancer?

https://blog.frontiersin.org/2019/03/27/helminth-worms-cause-cancer/?

Can you ‘catch’ cancer?

by Matthew Prior, Frontiers science writer

March 27, 2019

Frontiers in Medicine: Parasitic worms cause cancer – and could help cure it
In endemic regions, parasitic worms called ‘flukes’ are responsible for the majority of all bladder and liver cancer cases. Image: Shutterstock.


Parasitic worms cause cancer – and could help cure it

Billions worldwide are infected with tropical worms. Unsurprisingly, most of these people live in poor countries, kept poor by the effects of worm-related malnourishment.

What may surprise many is that worms are also a major cause of cancer in these countries.

Published in Frontiers in Medicine and Frontiers in Public Health as a Research Topic on parasite-associated malignancy, new research aims to inform prevention and treatment – and perhaps even turn worms against cancer. Frontiers Research Topics are highly visible peer-reviewed article collections led by the world’s leading researchers who harness collaborative knowledge on today’s biggest scientific questions.

Worms cause cancer

Over a million worm species are classified as helminths. A single characteristic unites them: parasitism.

“Helminths take many forms, but all of them harm their host in some way. In humans, they can live in the intestinal tract, urinary tract or bloodstream, causing a variety of illness from malnutrition to organ failure” explains co-editor of the research Dr. Monica Botelho of Portugal’s National Institute of Health.

In 2015 a more bizarre case of infection put helminths into the headlines: a man with HIV-AIDS died after his tapeworm contracted cancer and spread around his body. This remains the only such case ever recorded.

Meanwhile, scientists have known for decades that helminths can turn human cells into cancers.

“Three species of helminth are classified as class 1 carcinogens by the WHO,” adds Botelho. “These are all designated trematodes – after the Latin name for the grisly feeding cavity with which they latch onto their host’s insides.”

Worm-related cancer is not just a fluke – it’s three

Trematodes are known informally as ‘flukes’. In this case however, they’re anything but.

“In endemic regions – predominantly sub-saharan Africa and Southeast Asia – flukes are responsible for the majority of all bladder and liver cancer cases,” says Dr. Joachim Richter, Associate Professor at Charité Berlin and co-editor with Botelho. “Cancers arise in sites of fluke infection including the bladder wall and the bile ducts of the liver.”

But how does a worm cause cancer? According the research collection, their feeding – and breeding – habits might be to blame.

“Flukes constantly wound and re-wound their host as they latch on with their feeding cavity, burrow through organs, and deposit eggs in the bladder wall. This leads to chronic inflammation as the body tries endlessly to heal, meaning lots of cell division and so lots of opportunities for cancer-causing mutations to accumulate over years of infection.”

The flukes’ toxic toilet habits then add insult to injury.

“Worms and their eggs also excrete proteins that exacerbate this chronic inflammation, further promoting cell division as well as the blood vessel growth required to feed it,” adds Richter.

Hyper tapeworms protect hosts from cancer

Fluke infections and early stage cancers are often asymptomatic, so despite availability of anthelminthic drugs patients often present too late for curative treatment. Fortunately, flukes have an Achilles’ heel: they require freshwater snails as a first host before infecting humans.

“Flukes have been successfully eliminated in Japan by economic development and the filling and drainage of snail habitats,” says Richter. “Eradication efforts are underway in Thailand, which has the world’s highest rates of liver fluke infection and bile duct cancer – but some high-risk countries like Ethiopia lack a coordinated monitoring or prevention program for fluke-related cancer and need more help.”

Beyond eradication efforts lies another twist in the bizarre world of worms and cancer: helminths as a cure for malignancy.

“Many parasites, including some helminths like the liver fluke Fasciola hepatica, inhibit cancer growth in vitro. Another of these – the ominously named ‘hyper tapeworm’ – is associated with a significantly lower rate of cancer in human hosts,” reports Botelho.

“In fact, there is evidence that proteins produced by hyper tapeworms as well as F. hepatica not only kill cancer cells directly – but might also enhance their host’s immune response to tumors.”

“Even cancer-promoting fluke proteins might be repurposed as treatments for other conditions: for example, those that promote new blood vessel growth could help resolve chronic non-healing wounds in diabetics, tobacco users, and the elderly.”

__________________

**Comment**

There is a connection between helminths (worms) and Lyme/MSIDS and some patients improve dramatically on anthelmintics:  https://madisonarealymesupportgroup.com/2016/06/03/borrelia-hiding-in-worms-causing-chronic-brain-diseases/

Lyme discoverer, Willy Burgdorfer, wrote of finding nematodes in tick guts way back in 1984 and in 2014 University of New Haven researcher, Eva Sapi, found 22% of nymphs and 30% of adult Ixodes ticks carried nematodes.  

This study shows worms (Onchocerciasis) in Wisconsin ticks:  https://madisonarealymesupportgroup.com/2018/08/11/co-infection-patterns-in-wisconsin-black-legged-ticks-show-associations-between-viral-eukaryotic-bacterial-microorganisms/

The CDC states the treatment of choice is Ivermectin as well as doxycycline. Doxy kills the adult worms by killing the Wolbachia bacteria on which the adult worms depend in order to survive.  https://www.cdc.gov/parasites/onchocerciasis/treatment.html

There is a dog study, however, that shows wide-spread inflammation after heart worm medicine was given (Ivermectin & Pyrantel) so discuss ALL of this with your practitioner:  https://madisonarealymesupportgroup.com/2017/07/10/wolbachia-the-next-frankenstein/.  Since Dr. McDonald has found these worms containing spirochetes in the brain, the vast die-off herxheimer might be severe and needs to be carefully considered and monitored. This is NOT a do-it-yourself treatment!

https://madisonarealymesupportgroup.com/2016/08/09/dr-paul-duray-research-fellowship-foundation-some-great-research-being-done-on-lyme-disease/  Another great article by microbiologist Tom Greer and a repeat warning that anthelmintics can cause severe inflammatory reactions and fatal encephalitis.

Probably one of the most popular hits on this website contains information on parasite treatments:  https://madisonarealymesupportgroup.com/2017/10/03/removing-parasites-to-fix-lyme-chronic-illnesses-dr-jay-davidson/  It’s obviously a big problem.

The CDC’s mono-therapy of doxycycline isn’t ever going to cure the Lyme/MSIDS pandemic. This is a serious polymicrobial illness that takes savvy.

For more:  https://madisonarealymesupportgroup.com/2016/02/13/lyme-disease-treatment/