Archive for the ‘research’ Category

What You Need to Know About Neuralgia Caused by Lyme/MSIDS

Many Lyme/MSIDS patients suffer with neuralgia, a twenty dollar word for pain due to irritated or damaged nerves. The following articles do a great job explaining it. I was elated to see that the first article written this month attributes Lyme disease to causing it, along with other infections. My guess is Bartonella, Babesia, Mycoplasma, Brucella, and possibly other tick-borne illnesses, including viruses, could all play a part. Because the CDC/NIH/IDSA do not accept the fact this is often times a polymicrobial illness (infected with far more than just Lyme), and many of the coinfections are not reportable, authorities have absolutely no idea about prevalence.  

My guess is there are many diagnosed with neuralgia that have an undiagnosed Lyme/MSIDS infection.

https://www.medicalnewstoday.com/articles/325331.php

What to know about neuralgia

Last reviewed
Neuralgia refers to severe, shooting pain that occurs due to a damaged or irritated nerve. Neuralgia can affect any part of the body, causing mild to severe pain. Certain medications and surgical procedures can effectively treat neuralgia.
Severe neuralgia can interfere with a person’s ability to perform everyday tasks and may impact their quality of life.
Neuralgia has many possible causes, including:
  • infections, such as shingles, Lyme disease, or HIV
  • pressure on nerves from bones, blood vessels, or tumors
  • other medical conditions, such as kidney disease or diabetes
  • aging

    Types of neuralgia

    Healthcare professionals divide neuralgia into categories depending on the areas of the body it affects. The following are some common types of neuralgia:

    Trigeminal neuralgia

    Woman experiencing headache and neuralgia in face holding glass of water in pain

Trigeminal neuralgia (TN) involves the trigeminal nerve in the head. It has three branches that send signals from the brain to the face, mouth, teeth, and nose.

TN falls into two subdivisions: type 1 and type 2.

Type 1 TN causes a painful burning or electric shock-like sensation in parts of the face. People with type 1 TN experience irregular episodes that come on suddenly.

The duration of these episodes varies among people but can last up to 2 minutes, according to the National Institute of Neurological Disorders and Stroke.

Type 2 TN produces a constant, dull aching sensation in the face.

The exact cause of TN remains unclear. However, pressure from an enlarged blood vessel can irritate or even damage the trigeminal nerve.

Multiple sclerosis (MS) can give rise to TN. MS is a neurological disorder that causes inflammation that damages the myelin sheath surrounding nerve fibers in the central nervous system.

Postherpetic neuralgia

Postherpetic neuralgia (PHN) is a painful condition that affects the nerves in the skin.

According to the Centers for Disease Control and Prevention (CDC), PHN is the most common complication of shingles, affecting about 10–13% of people who develop it.

Shingles is a viral infection that causes blisters and a painful skin rash. The varicella-zoster virus, which causes chickenpox, remains dormant in the nervous system and reactivates later in life, causing shingles.

When the virus reactivates, it can cause inflammation in the nerve fibers. This inflammation can lead to permanent nerve damage that causes pain, even after the infection subsides.

Occipital neuralgia

This form of neuralgia affects the occipital nerves, which originate in the neck and send signals to the back of the head.

Occipital neuralgia causes a throbbing or shooting pain that starts near the base of the skull and radiates along the scalp. Occipital neuralgia pain can flow to the back of the eyes.

Occipital neuralgia has numerous potential causes, including:

  • sudden head movements
  • tense neck muscles
  • lesions or tumors in the neck
  • inflamed blood vessels
  • infections
  • gout
  • diabetes
  • neck injuries

Peripheral neuralgia

Difficulty eating or swallowing are potential symptoms of peripheral neuralgia.


Peripheral neuralgia, or peripheral neuropathy, refers to pain that occurs due to nerve damage in the peripheral nervous system. This includes all nerve fibers outside of the brain and spinal cord.

Peripheral neuralgia can affect a single nerve or entire nerve groups.

Sustaining damage to the peripheral nervous system can affect nerves that control muscle movements, transmit sensory information, and regulate internal organs.

Peripheral neuralgia can cause pain or numbnessin the hands, feet, arms, and legs. Other symptoms may include:

  • involuntary muscle twitching or cramping
  • loss of coordination
  • difficulty performing complex motor tasks, such as buttoning a shirt or tying shoelaces
  • hypersensitivity to touch or temperature
  • excess sweating
  • gastrointestinal problems
  • difficulty eating or swallowing
  • difficulty speaking

Intercostal neuralgia

Intercostal neuralgia affects the nerves that sit just below the ribs. Doctors call the muscles in this area the intercostal muscles.

Several potential factors may contribute to intercostal neuralgia, such as:

  • injuries or surgical procedures that involve the chest
  • pressure on the nerves
  • shingles or other viral infections

Intercostal neuralgia causes a sharp, burning pain that affects the chest wall, upper abdomen, and upper back. Certain physical movements, such as breathing, coughing, or laughing, can worsen the pain.

Additional symptoms may include:

  • tightness or pressure that wraps around the chest
  • tingling or numbness in the upper chest or upper back
  • muscle twitching
  • loss of appetite

Diabetic neuropathy

Diabetic neuropathy is the most common complication of diabetes. Because diabetes affects so many people, rates of peripheral neuropathy are now beginning to rise.

Symptoms include loss of balance and numbness, tingling, and pain. The best way to prevent diabetic neuropathy is to bring blood sugar levels within a suitable range.


Symptoms

In general, neuralgia causes intense and distinct symptoms, including:

  • sudden episodes of extreme shooting or stabbing pain that follows the path of a damaged or irritated nerve
  • persistent aching or burning pain
  • tingling or numbness
  • muscle weakness
  • loss of muscle mass, or atrophy
  • involuntary muscle twitching or cramping


Treatments

Treatment options for neuralgia vary depending on the type and severity of the condition.

Topical ointments, local nerve block, and steroid injections may offer temporary pain relief for mild neuralgia.

Treating severe neuralgia pain may require prescription medications, surgical procedures, or both.

Medications

A doctor may prescribe medication to treat neuralgia.

  • anticonvulsants, such as carbamazepine, topiramate, and lamotrigine
  • antidepressants, such as amitriptyline
  • muscle relaxants, such as baclofen
  • membrane-stabilizing medications, such as gabapentin

Surgery

Some surgical procedures can help relieve neuralgia pain when the condition does not respond to medication.

Examples of surgical procedures that can help treat neuralgia include:

  • Microvascular decompression: This helps remove an enlarged blood vessel pressing on a nerve. The procedure involves placing a soft pad between the blood vessel and the affected nerve.
  • Stereotactic surgery: This is a noninvasive procedure that delivers highly concentrated radiation beams to the root of a damaged nerve. The radiation disrupts the transmission of pain signals to the brain.
  • Balloon compression: This involves inserting a small balloon into the affected nerve. The balloon inflates, resulting in controlled, intentional nerve damage. This procedure prevents the affected nerve from sending pain signals to the brain. However, the effects of the procedure usually wear off after 1–2 years.


Outlook and takeaway

Neuralgia causes painful symptoms that vary in duration and severity. As well as pain, neuralgia can cause numbness, muscle weakness, and hypersensitivity.

If a person does not receive treatment, neuralgia can interfere with their ability to perform daily tasks.

People can work with a healthcare provider to establish the best course of treatment for their specific symptoms. If the condition does not respond to initial treatments, a healthcare provider may refer the person to a pain management specialist.

____________________

**Comment**

They don’t list antimicrobial treatment as a treatment for this, but it is. Again, if Lyme/MSIDS is behind it, the only thing that’s going to squash this pain at the root is to eradicate the pathogens behind it.  Nothing touched this pain for me but long-term antimicrobials.  While some of the listed treatments may help, they are bandaids. I talk more about this further down.  Keep reading….

https://www.medicalnewstoday.com/articles/320143.php

What you need to know about occipital neuralgia

Last reviewed
Occipital neuralgia is the term for a headache that starts in the upper neck or back of the head and spreads or radiates behind the eyes, forehead, and up to the scalp.


Headaches are one the world’s most common health problems, with 80-90 percent of Americans experiencing a “tension headache” at some point in their lives.

More painful migraine, cluster, and other headaches are a leading cause of doctor or emergency room visits.

Although headaches are a common health problem, occipital neuralgia is a specific type of headache. According to the American Migraine Foundation, it is also rare, affecting only 3.2 people out of every 100,000 a year.

Fast facts on occipital neuralgia:
  • It is called occipital because it affects the area around the occipital bone.
  • Pain associated with occipital neuralgia is often sudden and severe.
  • Symptoms can be alarming, but they are not usually associated with any life-threatening health conditions.

How is it different from other headaches?

man holding the back of his neck


Headaches due to occipital neuralgia are frequently quite painful, starting with a sharp, stabbing pain, but most people with this condition respond well to treatment and most recover.

Occipital neuralgia is different from other types of headaches in two ways:

  1. The cause of the condition.
  2. The specific places where individuals feel pain.

Other headaches have more general causes, which can range from sinus infections to high blood pressure to medications and many other potential triggers.

But occipital neuralgia only develops when the occipital nerves are irritated or injured. These nerves are found at the second and third vertebrae of the neck.

Occipital neuralgia pain will only develop in areas touched by the greater, lesser, and third occipital nerves.

With one on each side of the head, the occipital nerves run from the spine to the scalp, and sensitivity can develop anywhere along this route.

What are the main symptoms?

lady touching side of face whilst lying in bed


For most people, the pain strikes on only one side of the head. It also tends to spread, usually from where the skull meets the neck, and then traveling up the back of the head and to the sides or behind the eyes.

In many individuals, the scalp can be affected, especially where the occipital nerves connect.

It can feel sore or extremely sensitive.

Light may also irritate the eyes.

Occipital neuralgia is described as coming in bursts of pain that come and go, lasting for a few seconds or minutes. At times, individuals may experience a lingering ache between more extreme bouts of pain.

Small movements can trigger an outburst of pain from occipital neuralgia. These movements include:

  • turning the head to the side
  • putting the head down on a pillow
  • brushing or washing the hair

The pain can be quite intense, which can prompt some individuals with the condition to say it is like a migraine or a cluster headache, even though these are different types and require different treatments.

What causes it?

Different conditions and circumstances can irritate the occipital nerves, which then give rise to occipital neuralgia.

Injury

Injuries to the neck area, such as whiplash from a car accident or some other sort of trauma, can damage the occipital nerves and lead to this condition.

Muscular problems

Tight muscles in the neck and the back of the head can put the squeeze on occipital nerves and pinch or entrap them, which can also lead to occipital neuralgia.

Back issues

Problems with the spine, such as arthritis, degenerating discs, or spondylosis, are possible sources of pressure on the occipital nerves, as are tumors.

Other causes

Other conditions that can play a role in developing occipital neuralgia include:

In many cases, it is not possible for someone to identify a single factor that damaged or irritated the occipital nerves.

How is it diagnosed?

doctor examining women's head and neck


A doctor taking a medical history and conducting a physical exam diagnoses occipital neuralgia.

This condition causes extreme tenderness along the occipital nerves. So, during a physical exam, the doctor may press on these areas to see if the pressure generates pain.

It is not always easy to diagnose occipital neuralgia because it has similar characteristics to many other kinds of headaches.

After initial exams, a doctor may order more involved tests.

One way to diagnose occipital neuralgia can also provide relief.

If a nerve block injected between the C2 and C3 vertebrae makes the symptoms go away, it is a strong indication of occipital neuralgia.

Deadening the nerves with anesthetics and corticosteroids helps individuals feel better, although the effects are temporary, only lasting about 12 weeks. However, injections into the vertebrae and numbing nerves are involved procedures, so a doctor will often pursue less invasive treatments first.

Can it be prevented?

For some people, antiepileptic medications and tricyclic antidepressants can prevent bouts of pain due to occipital neuralgia.

Treatments

Doctors will usually recommend straightforward treatments when individuals are first diagnosed with occipital neuralgia. These include:

The aim is to provide many people with relief by relaxing and releasing the muscles that are putting pressure on the occipital nerves.

Other medications, such as muscle relaxants and anticonvulsants, can help offset symptoms.

Nerve blockers

Nerve-blocking injections, which are used to diagnose the condition, can also be used to prevent pain.

Pulsed radiofrequency

Pulsed radiofrequency may be employed to stimulate the occipital nerves to keep them from sending pain signals. Although this procedure is more invasive than massage and medication, it does not damage any nerves or nearby tissue.

Surgery

Surgery is reserved for the most painful and difficult cases. Through a process called microvascular decompression, doctors eliminate pressure on the nerves by moving encroaching blood vessels out of the way.

Home remedies

Home remedies can do a lot to relieve the pain when tight muscles, injury, and stress cause occipital neuralgia.

Rest, massage, and warm compresses can help individuals work out the kinks that are creating pressure in their necks.

Physical therapy can help individuals work through the crisis phase of their occipital neuralgia and provide them with exercises they can do to prevent a recurrence of this painful condition.

___________________

**Comment**

Again, they don’t state that proper antimicrobials addressing the systemic infection causing this as a treatment, but it is.  And for Lyme/MSIDS patients, it’s an extremely important treatment because as I stated before, all the others are mere bandaids.

This occipital neuralgia was my Achilles Heel and thorn in my side for years due to Lyme/MSIDS. I even had a MRI to rule out Chiari, which can be the result of a systemic infection.  I met 3 people in the same week with a Lyme/MSIDS diagnosis who also had Chiari:  https://madisonarealymesupportgroup.com/2016/04/02/chiari/

One of the best drugs for me was minocycline, due to its ability to cross the blood, brain barrier:  https://madisonarealymesupportgroup.com/2017/06/04/minocycline-for-ms-and-much-more/

I’m certain there are plenty more patients with this symptom who have an undiagnosed Lyme/MSIDS infection.

Home remedies wouldn’t touch this pain with a 10 foot pole, much less NSAIDS.  I would caution the use of corticosteroids as these will suppress your immune system. The caveat would be if you are on an antimicrobial regimen and your practitioner is monitoring you.  I also caution the use of NSAIDS as taking massive doses of Ibuprofen about shut my husband’s liver down.

This pain may be the person’s first acknowledged symptom of Lyme/MSIDS.  Often men will suffer and self medicate and deny a real problem.  This is where spouses, friends, and family need to be educated about the possibility of a tick borne illness so they can mention it to the suffering person. If you are popping NSIDS like candy, something’s wrong.  Getting them to an open-minded, trained practitioner who will consider tick borne illness is your next job.  Contact your local support group for a list of ILADS-trained doctors.

Also, this pain for me radiated to the right side of my head from the occipital area to the right temple. There were times my right shoulder was involved with pain and numbness going all the way down my arm into my right pinkie finger.  The finger would also move on its own.  This can happen anywhere in the body.

https://www.medicalnewstoday.com/articles/321513.php

The following neurological conditions may be responsible for headaches on one side:

  • Occipital neuralgia: This occurs when nerves running from the top of the spinal cord to the scalp (occipital nerves) become damaged or inflamed. Symptoms include sharp pain in the back of the head and neck, pain behind the eye, and sensitivity to light.
  • Temporal arteritis: Arteries in the head and neck become inflamed with temporal arteritis. Along with muscle pain, it causes a severe headache on the side of the head. Other symptoms include fatigue, jaw pain, and tender temples.
  • Trigeminal neuralgia: This causes intense pain in the face and head. The pain usually affects only one side at a time. It is caused by disruption to the trigeminal nerve at the base of the brain.
Lyme/MSIDS infections can be behind all of this.  Spread the word.
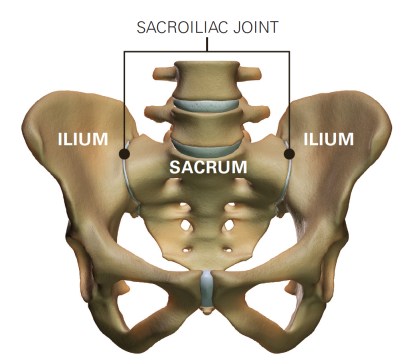


Review of PSI Joint Infections in Pediatrics – All With Negative Blood Cultures: Bartonella & Brucella, Among Others

https://www.ncbi.nlm.nih.gov/pubmed/31130517

2019 May 23. pii: S1695-4033(18)30548-4. doi: 10.1016/j.anpedi.2018.07.017. [Epub ahead of print]

[Pyogenic sacroiliitis: Lessons learned from an atypical case series].

[Article in Spanish]

Abstract

INTRODUCTION:

Pyogenic sacroiliitis (PSI) is a rare condition that amounts to 1% to 2% of all joint infections in the paediatric age group. Its diagnosis is often difficult and delayed due to its nonspecific signs, symptoms and physical findings. Also, the identification of the causative microorganism is frequently challenging due to a high proportion of negative blood cultures and the risks involved in joint aspiration in this site.

PATIENTS AND METHODS:

We performed a retrospective review of the health records of all patients aged less than 18 years admitted to a tertiary children’s hospital due to PSI between 2008 and 2016.

RESULTS:

We identified 6 cases of paediatric PSI. The blood cultures were negative, and the identification of the causative agent required joint fluid aspiration in one patient with infection by Aggregatibacter aphrophilus, and specific screening tests for less frequent agents in the other patients: Kingella kingae (n=2), Brucella melitensis (n=1) and Bartonella henselae (n=1). The patients were treated with specific antimicrobial regimens, and all had favourable clinical outcomes and were free from sequelae during the follow-up.

CONCLUSIONS:

Despite the small sample size, our study evinced the low effectiveness of blood cultures for diagnosis of paediatric PSI. It also highlights the need for a high level of suspicion for atypical agents and the early use of adequate diagnostic methods, including imaging and serological testing or polymerase chain-reaction (PCR) analysis of blood samples, as well as prescription of effective antimicrobial therapy.

____________________

**Comment**

Pyogenic sacroiliitis = puss forming joint infection in the sacroiliac joint.

iu-16

Brucella melitensis, a gram negative rod-shaped bacteria, is a human pathogen (Malta fever), B.abortus (Bang’s disease), and in rare cases, B. suis and B. canis. Transmission occurs through animal contact (birth) or animal products, inhalation of infected particles, STD, breastfeeding, bone marrow transplants, blood products, and yes, ticks.  Pathogens are found in macrophages which are transported to lymph nodes, then spread throughout the body.  Treatment consists of doxycycline, rifampicin, & gentamicin.  Also, Ciprofloxin 500mg twice a day for 7-14 days.  http://brucellamelitensis.com

http://drsusanmarra.com/patient-resources/lyme-disease/brucella/ It has been found in eggs, larvae and engorged females of Dermacentor marginatus ticks (that bite humans)  https://www.sciencedirect.com/science/article/pii/S1877959X17303990

Hosts are most mammals including humans.  http://www.bristoluniversitytickid.uk/page/Dermacentor+marginatus/13/#.XPgbgS2ZPSc

Symptoms are very non-specific:  https://www.cdc.gov/brucellosis/symptoms/index.html

http://www.cfsph.iastate.edu/Factsheets/pdfs/brucellosis_melitensis.pdf  Actually the best information is found here.

And…according to the CDC:  https://www.cdc.gov/brucellosis/clinicians/brucella-species.html

*Three types of the bacteria that cause brucellosis – Brucella abortus, Brucella melitensis and Brucella suis – are designated as select agents. This means that they have the potential to be developed as bioterrorism agents due to their ability to undergo aerosolization.

Oh goody, another potential bioweaponized agent spread by ticks.

For more on the history of brucella as a bioweapon:  https://www.globalsecurity.org/wmd/intro/bio_brucellosis.htm

https://www.ncbi.nlm.nih.gov/pubmed/8425348?dopt=Abstract  Acute Lyme arthritis in the hip mimicking acute pyogenic arthritis in 5-year old girl.

https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3358077/  Bartonella & all sorts of rheumatic symptoms in patients from Lyme endemic regions with histories of cat, dog, mosquitoes, ticks, fleas, and biting fly exposure.

Staph is usually the culprit, but this case report highlights that Lyme, Bartonella, Brucella, and mycoplasma should be tested for as well.  Things to watch for in children/babies – pain with diaper changes, limping, fever, irritability, decreased range of motion in the pelvic area.  This review stated the highest incidence was in adolescents:  https://link.springer.com/article/10.1007/s00431-019-03333-8, but that it’s an under recognized entity in infants with an unidentified bacterial source.  Could this be a manifestation of congenital Lyme/MSIDS that’s flying under the radar?


High Titers of Bartonella Found in Patients With Musculoskeletal Complaints

https://www.ncbi.nlm.nih.gov/pubmed/31115789

2019 May 22. doi: 10.1007/s10067-019-04591-5. [Epub ahead of print]

The seroprevalence of Bartonella spp. in the blood of patients with musculoskeletal complaints and blood donors, Poland: a pilot study.

Abstract

BACKGROUND:

Bartonella spp. can cause a variety of diseases, such as lymphadenopathies, cat scratch disease, and trench fever, but can also give rise to many non-specific symptoms. No data exists regarding the prevalence of Bartonella spp. in patients with musculoskeletal complaints, nor among blood donors in Poland.

METHODS:

The presence of anti-Bartonella IgM and IgG in the serum of blood donors (n = 65) (Lodz, Poland) and in the patients of the Department of Rheumatology Clinic (n = 40) suffering from musculoskeletal symptoms was tested by immunofluorescence. Blood samples were cultured on enriched media. Epidemiological questionnaires were used to identify key potential risk factors, such as sex, age, contact with companion animals, and bites from insects or animals.

RESULTS:

Altogether,

  • 27 of the 105 tested subjects were seropositive for Bartonella henselae IgG (23%)
  • 3 for Bartonella quintana IgG (2.85%)
  • IgMs against B. henselae were found in 3 individuals (2.85%)
  • IgMs against B. quintana were found in one (1.54%)

No statistically significant difference was found between the prevalence of B. henselae in the blood of donors or patients and the presence of unexplained musculoskeletal complaints (23% vs 30%). Individuals who had kept or been scratched by cats were not more likely to be B. henselae seropositive (p > 0.01). Tick bites were more commonly reported in patients, but insignificantly (p > 0.01).

CONCLUSION:

This is the first report of a high seroprevalence of anti-Bartonella IgG in patients with musculoskeletal symptoms and in blood donors in Poland. The obtained results indicate that such seroprevalence may have a possible significance in the development of musculoskeletal symptoms, although it should be confirmed on a larger group of patients. Asymptomatic bacteremia might occur and pose a threat to recipients of blood from infected donors. Hence, there is a need for more detailed research, including molecular biology methods, to clarify the potential risk of Bartonella spp. being spread to immunocompromised individuals.

KEY POINTS:

•This is the first study presenting high seroprevalence of Bartonella spp. in Poland. • IgG and IgM antibodies against B. quintana were found in blood samples of blood donors.


Another Tick-Borne Disease To Worry About – Alongshan virus (ALSV)

https://www.npr.org/sections/goatsandsoda/2019/06/01/728375159/another-tick-borne-disease-to-worry-about

Another Tick-Borne Disease To Worry About

June 1, 20197:00 AM ET

This photo depicts two Haemaphysalis longicornis ticks, commonly known as the longhorned tick. It has been linked to the spread of a hemorrhagic fever in China. The smaller of the two ticks on the left is a nymph. The larger tick is an adult female.

Science Source

When a tick bores into your skin, anchoring itself for what can be a leisurely meal while often spreading germs, it isn’t just Lyme disease that you have to worry about.

Various kinds of ticks have been shown to carry at least 16 diseases in the U.S alone that can infect humans, according to the Centers for Disease Control and Prevention. Now add one more to the global list of ills that a tick bite can bring about, according to a study in the May 30 New England Journal of Medicine.

The study, identifying a new tick-borne disease, shows that we still don’t know how many more diseases ticks can carry. “We continue to discover new viruses,” says Dr. Bobbi Pritt, director of the Clinical Parasitology Laboratory and co-director of the Vector-Borne Disease Lab Services at Mayo Clinic. She was not involved in the study.

The newly discovered disease was found in Inner Mongolia, an autonomous region of China. In April 2017, a 42-year-old female farmer from the Mongolian town Alongshan went to a county hospital complaining of fever and headache. She had a history of tick bites. In searching for the cause of the patient’s fever, researchers ruled out the usual tick-borne diseases found in the area. Using genome sequencing, a process of determining the makeup of an organism’s DNA, they isolated a new disease-causing agent, which they called Alongshan virus, or ALSV, after the patient’s hometown.

Further testing found 86 additional patients in the same Inner Mongolia region who were infected with ALSV. “Neither permanent clinical complications nor death occurred among patients with confirmed infection,” wrote the authors, from various universities and laboratories in China, in the journal article.

The patients in the study had symptoms of headache and fever coming an average of three to seven days after a tick bite, according to an email response to questions from Quan Liu, an author of the study from the School of Life Sciences and Engineering at Foshan University in Foshan, China. They were treated with ribavirin, an antiviral, and benzylpenicillin sodium, an antibiotic, for three to five days, he wrote.

“The symptoms usually resolved after six to eight days of treatment, and all patients had complete recovery.”

Diseases from a variety of ticks are seen around the world, but there are regional differences depending on the virus or bacteria carried by the ticks in the area. So far, ASLV has been found only in Inner Mongolia, in Ixodes persulcatus ticks, according to the study. It has also been found in mosquitoes in the same area, so researchers can’t be certain whether the patients got sick from a tick bite or a mosquito bite.

Like the victims of ASLV, most patients recover from the diseases caused by tick bites — although some tick-borne diseases can result in enduring joint pain, impaired muscle movements and fatigue.

Finding a new disease can only reinforce the need for people to take precautions to avoid tick bites.

In the U.S., where more than 59,000 cases of tick-borne diseases were reported in 2017, tick season is just beginning.

“Once the snow melts, the ticks come out. Stay away from tall grasses and forested areas,” says Pritt. “If you go into those areas, wear protective clothing and use an insect repellent with DEET.”

The CDC also suggests treating clothing and camping gear with the repellent permethrin, walking in the center of paths to avoid brushing against plants and leaves, and bathing and checking your body for ticks after an outdoor excursion.

And if you do come down with a fever that isn’t easily explained or diagnosed, make sure you tell your physician about any travel or recent outdoor experiences, says Pritt.

“The overarching theme is the more we look at ticks, the more we find,” says Wendy Adams, research grant director, Bay Area Lyme Foundation, who was not involved in the study. “We find parasites, viruses, bacteria. We just found worms in ticks in New York.”

It means that when humans are bitten by ticks, there are many diseases and infections they can contract — even a disease carried by a parasite within a tick.

Susan Brink is a freelance writer who covers health and medicine. She is the author of The Fourth Trimester: Understanding, Protecting, and Nurturing an Infant through the First Three Months, and co-author of A Change of Heart.

CorrectionJune 1, 2019

A previous version of this story incorrectly referred to the Centers for Disease Control and Prevention as the Centers for Disease Control and Infection.

__________________

**Comment**

OK, another virus discovered in ticks…..and in none other than the Asian Longhorned tick that’s galavanting it’s way across the U.S.:  https://madisonarealymesupportgroup.com/2019/05/30/invasive-longhorned-tick-found-in-east-tennessee/  According to this recent article, it’s in 11 states so far and shows no signs of slowing down.

To date this tick which causes significant havoc in Asia, has not transmitted any diseases in the U.S. yet, but the concern is palpable due to its ability to clone itself and replicate quickly.  It also lines up on a stalk of grass like a cluster bomb waiting to be touched by something to detonate.  When you study this tick for 5 min. it becomes clear why this particular tick infestation can drain cattle of their blood.  https://madisonarealymesupportgroup.com/2018/09/12/three-surprising-things-i-learned-about-asian-longhorned-ticks-the-tick-guy-tom-mather/

three_surprising_4.png

Notice the article states that ticks are full of all manner of things: bacteria, viruses, parasites, and yes, even worms – which is not a new thing, BTW.  Willy Burgdorfer found worms in ticks decades ago. Here we see filarial nematodes (worms) in N.Y. ticks:  https://madisonarealymesupportgroup.com/2019/05/10/study-shows-many-different-pathogens-in-deer-ticks-from-ny-ct/

Worms have been found to harbor spirochetes. This is a big deal because it will take anthelmintics to kill the worms to be able to get to the spirochetes (Lyme). Some patients only get better after anti-worm treatment:  https://madisonarealymesupportgroup.com/2017/10/03/removing-parasites-to-fix-lyme-chronic-illnesses-dr-jay-davidson/  If you’ve reached a plateau, discuss this with your practitioner as a consideration.

According to microbiologist Tom Grier, great care needs to be taken with anti-wormers because the die off can create severe, perhaps deadly herxes:  https://madisonarealymesupportgroup.com/2016/08/09/dr-paul-duray-research-fellowship-foundation-some-great-research-being-done-on-lyme-disease/

With the high rates of dementia, Alzheimer’s, ALS, etc., we should be considering tick borne illness with these patients as we’ve learned that many can regain their mental faculties with appropriate treatment:  https://madisonarealymesupportgroup.com/2019/04/09/the-diagnosis-is-alzheimers-but-thats-probably-not-the-only-problem/  See comment section.

Disulfiram in the Treatment of Lyme & Babesiosis: 3 Case Reports

https://www.mdpi.com/2079-6382/8/2/72

Disulfiram (Tetraethylthiuram Disulfide) in the Treatment of Lyme Disease and Babesiosis: Report of Experience in Three Cases

Health Quest System, Sharon Hospital, Sharon, CT 06069, USA
Antibiotics 2019, 8(2), 72; https://doi.org/10.3390/antibiotics8020072
Published: 30 May 2019
(This article belongs to the Special Issue Antibiotics Resistance of Borrelia)

|

PDF [248 KB, uploaded 30 May 2019]

|

Abstract

Three patients, each of whom had required intensive open-ended antimicrobial therapy for control of the symptoms of chronic relapsing neurological Lyme disease and relapsing babesiosis, were able to discontinue treatment and remain clinically well for periods of observation of 6–23 months following the completion of a finite course of treatment solely with disulfiram. One patient relapsed at six months and is being re-treated with disulfiram. View Full-Text

This is an open access article distributed under the Creative Commons Attribution License which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited (CC BY 4.0).

Supplementary material

___________________

**Comment**

Please notice this is by Dr. Ken Liegner, an experienced Lyme literate doctor affiliated with ILADS.  The IDSA/NIH/CDC people are not doing work like this.  They are fixated on the acute phase leaving chronically infected people out to dry.

Thankfully, some good work is being done in the treatment area.  Some examples:

https://madisonarealymesupportgroup.com/2019/05/05/good-news-for-bartonella-patients-identification-of-fda-approved-drugs-with-higher-activity-than-current-front-line-drugs/

https://madisonarealymesupportgroup.com/2019/04/24/three-antibiotic-cocktail-clears-persister-lyme-bacteria-in-mouse-study/  I mention disulfiram in the comment section.

https://madisonarealymesupportgroup.com/2019/04/17/global-lyme-alliance-doing-kick-butt-research/  I mention disulfiram in the comment section.

https://madisonarealymesupportgroup.com/2019/02/22/why-mainstream-lyme-msids-research-remains-in-the-dark-ages/ Within this article is a link to an ILADS video Dr. Burrascano made recently. I highlight his video and explain his findings within his own practice of what worked for many patients, including a “cycling” approach to treatment as well as the fact blood levels of antibiotics are different for people. This treatment points are important because if the blood level isn’t high enough, pathogens will not be killed with a potential for them to mutate and become stronger in the future.


Be encouraged.  There’s some great stuff in the works.



