Archive for the ‘research’ Category

Which Treatment Guidelines Should You Follow For Lyme Carditis?

https://danielcameronmd.com/treatment-guidelines-lyme-carditis/

WHICH TREATMENT GUIDELINES SHOULD YOU FOLLOW FOR LYME CARDITIS?

Lyme carditis occurs when Borrelia burgdorferi spirochete penetrate the pericardium (a membrane that encloses the heart) or myocardium (muscular tissue of the heart). The infection triggers an inflammatory response, typically causing atrioventricular (AV) conduction abnormalities, such as a first, second or third-degree heart block.

In their article Lyme Carditis: A Rare Presentation of Sinus Bradycardia Without Any Conduction Defects, Grella and colleagues present “a unique case of Lyme carditis, without the classical findings of Lyme disease [such as a rash] or common EKG findings of AV conduction abnormalities.”¹

A 56–year-old man was admitted to the emergency department with lightheadedness and chest pain. An EKG revealed sinus bradycardias. Western blot test results for Lyme disease were positive and included IgG bands 18, 28, 39, 41, 45, 58, 66, 93 and negative for IgM (band 23 was positive). The patient was given a 7-day course of IV ceftriaxone.

However, “he continued to have persistent bradycardia with his heart rate dropping to 20 to 30 beats per minute throughout the night,” writes Grella. “Additionally, he had several sinus pauses while sleeping, with the longest lasting for 6.1 seconds.”

The man required further treatment with a pacemaker and a 3-week course of IV ceftriaxone.

At his one-month follow-up appointment, he was symptom-free.

The authors note that Lyme disease patients’ presentations may differ. “A gray zone exists in regards to the treatment of Lyme disease because every patient does not present with the characteristic rash and symptoms of Lyme disease.”

Furthermore, as Grella points out, there are different treatment guidelines for Lyme disease.

“The Infectious Diseases Society of America (IDSA) recommends that patients be started on a short course of antibiotics as the persistent infection is infrequent or non-existent.”

“The International Lyme and Associated Diseases Society (ILADS) recommends the Grading of Recommendations, Assessment, Development, and Evaluation (GRADE) system. This system emphasizes that a prolonged course of antibiotics be required, keeping in mind the high failure rates from a short course of antibiotics and the high prevalence of disseminated disease in a large number of cases.”

Meanwhile, Lyme carditis treatment varies between patients, as well.

“Patients with Lyme carditis who do not have high-grade heart block are managed conservatively with oral antibiotics.”

“Patients with a high-grade heart block should be hospitalized, closely monitored, and treated with IV ceftriaxone 2 grams or IV penicillins for second/third-degree AV block or prolonged for PR interval > 300 ms.”

Other institutions offer different approaches. “The European Federation of Neurological Societies (EFNS) recommends ceftriaxone or cefotaxime for 2 weeks as the standard of care in acute Lyme carditis.”

The authors conclude: “A high clinical suspicion of Lyme carditis is required when someone from a Lyme endemic region presents with unexplained cardiac symptoms and has EKG findings suggestive of carditis.”

Editor’s note: The length of treatment for this patient was consistent with the ILADS guidelines, as the man had failed the initial treatment.

Editor’s disclosure: I am co-author of the ILADS treatment guidelines.

References:
  1. Grella BA, Patel M, Tadepalli S, Bader CW, Kronhaus K. Lyme Carditis: A Rare Presentation of Sinus Bradycardia Without Any Conduction Defects. Cureus. 2019 Sep 2;11(9):e5554

____________________

For more:  

https://madisonarealymesupportgroup.com/2020/01/12/broad-range-of-presentations-for-lyme-carditis-cases/

https://madisonarealymesupportgroup.com/2019/11/29/increasing-burden-of-lyme-carditis-in-united-states-childrens-hospitals/

https://madisonarealymesupportgroup.com/2019/02/21/diagnosis-treatment-of-lyme-carditis/

https://madisonarealymesupportgroup.com/2019/11/04/suspect-lyme-carditis-start-empiric-antibiotics-case-report-suggest-and-lyme-carditis-is-not-rare/

https://madisonarealymesupportgroup.com/2018/07/09/with-unexpected-death-autopsies-should-look-for-lyme-carditis/

https://madisonarealymesupportgroup.com/2019/05/15/lyme-carditis-presenting-as-atrial-fibrillation/

https://madisonarealymesupportgroup.com/2020/02/17/lyme-carditis-presenting-as-sick-sinus-syndrome/

https://madisonarealymesupportgroup.com/2019/12/21/patients-can-die-when-lyme-carditis-is-not-treated/

Hugging it Out: How Physical Connection Helps Us Heal

https://globallymealliance.org/hugging-it-out-how-physical-connection-helps-us-heal/

by Jennifer Crystal

RESEARCH SHOWS THAT HUGGING IS GOOD FOR OUR HEALTH

I remember vividly a scene from the medical show “Grey’s Anatomy” that aired years ago. All that happened in the scene was that a doctor grew overwhelmed and cried, eventually having a panic attack. Slowly, two other doctors embraced her from either side and held her tight. When a fourth doctor came in and asked what was going on, one said, “We’re hugging it out.”

That scene struck me because I saw how the simple act of human touch quelled a serious physiological reaction to emotional stress. Within minutes, the upset doctor’s sobs subsided and her breathing slowed. The original problem that had set off her distress wasn’t gone but her fight-or-flight reaction was.

I have thought of that scene many times during my decades-long journey with chronic illness. So much of that time was spent alone. Patients battling tick-borne or other long-term illnesses are often bedridden with little to occupy their minds besides worry and pain. They may see family members or roommates in the evenings or on weekends, but the endless days of lying in bed can get downright lonely. There were so many times when I thought, I just want a hug.

And there were many times when I got one. When I was convalescing at her home, my mom gave me a hug every day when she came home from work. Friends hugged me when they came to visit. They sent me funny emails and left me voicemails that made me laugh. I sometimes felt hugged even when I didn’t have physical connection with someone.

But I also often felt desperately alone. Lyme disease can be especially isolating because on top of the loneliness that comes from being bedridden, patients often feel misunderstood or invalidated by the people closest to them and by medical professionals. One night I woke from a terrible nightmare with my arms wrapped around myself in a self-hug.

As the “Grey’s Anatomy” scene displayed, physical touch is important for everyone, not just for the infirm. Research shows that hugging is good for our health. In an NBC news report, Michael Murphy, Ph.D., a research associate at the Laboratory for the Study of Stress, Immunity, and Disease in the Department of Psychology at Carnegie Mellon University said, “…touch deactivates the part of the brain that responds to threats, and in turn, fewer hormones are released to signal a stress response, and your cardiovascular system experiences less stress.” Human touch can also stimulate the feel-good hormone oxytocin.[i]

Moreover, touch can help our physical wellness, too. A study by Dr. Murphy’s colleagues, also mentioned in the NBC news report, found that “those who felt socially supported and were hugged more often also experienced less-severe signs of illness.” Physical touch can also boost immunity.

Family therapist Virginia Satir is known for her quote, “We need 4 hugs a day for survival. We need 8 hugs a day for maintenance. We need 12 hugs a day for growth.”  That’s a tall order for a bedridden patient, but there are still ways to get the connection we need. We can ask for or initiate hugs with people with whom we are close. Caregivers and friends can think about giving more hugs to their loved ones who are ill (the benefits go both ways!). The touch aspects of therapies like integrative manual therapy or light massage can also be soothing. And for those who aren’t comfortable with physical touch or who live alone, simply connecting with others—whether it’s through social media, email, an online or in-person support group—can simulate the benefits of hugging and make you feel less alone.

Hugging won’t cure illness, or emotional stress, or the woes of the world, but it can lay the groundwork for subsequent healing. In our technological age, it would behoove us to follow the advice of the old song: “Reach out and touch someone.”

1 https://www.nbcnews.com/better/pop-culture/health-benefits-hugging-ncna920751


jennifer crystal_2

Opinions expressed by contributors are their own.

Jennifer Crystal is a writer and educator in Boston. Her memoir about her medical journey is forthcoming. Contact her at lymewarriorjennifercrystal@gmail.com.


___________________

For more:  https://madisonarealymesupportgroup.com/2020/02/20/lyme-mental-health-discussion/

https://madisonarealymesupportgroup.com/2020/01/03/lyme-mind-podcast-dr-leigner-dr-horowitz/

https://madisonarealymesupportgroup.com/2019/09/17/ignoring-psychiatric-lyme-disease-at-our-peril/

https://madisonarealymesupportgroup.com/2018/06/04/ld-diagnosis-took-forever-because-of-mental-health-stigma/

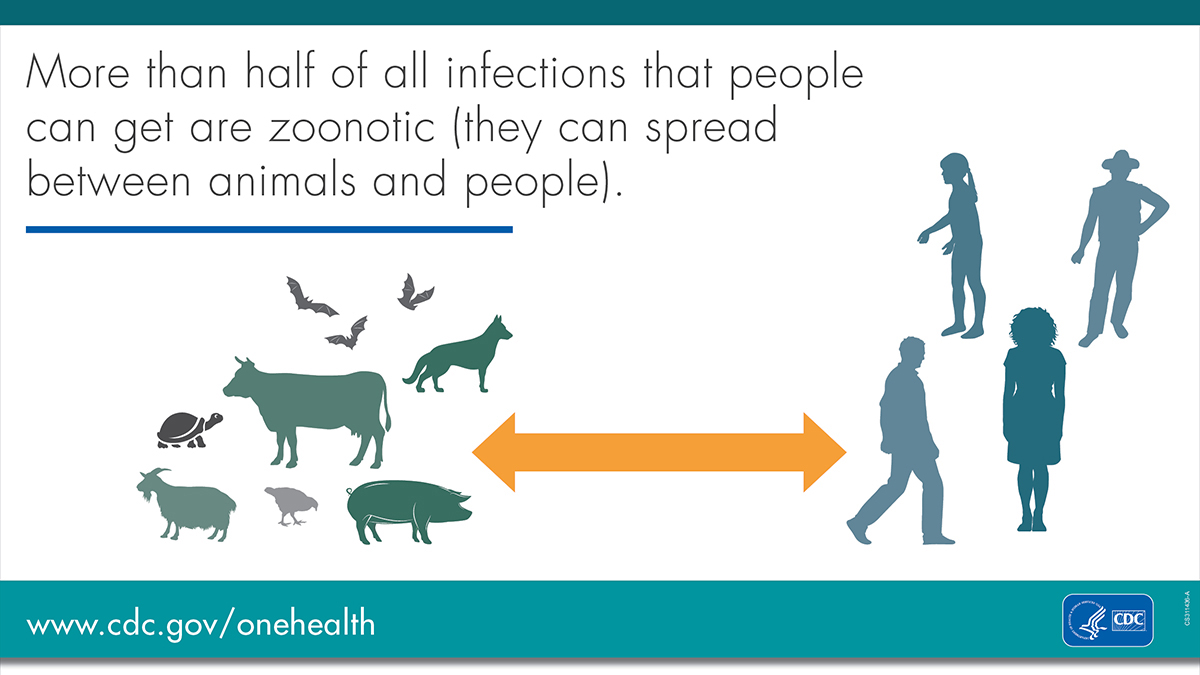
Zoonotic Diseases & Why We Are So Interested in Bats (Bartonella, Mycoplasma, & Coronavirus)

https://www.galaxydx.com/zoonotic-disease-and-one-health-with-bat-pathogens/

Zoonotic Diseases and Why We Are So Interested in Bats

Pathogenic Mycoplasma Infections in Chronic Illnesses: General Considerations in Selecting Conventional and Integrative Treatments

https://www.scirp.org/journal/paperinformation.aspx?paperid=95720

Pathogenic Mycoplasma Infections in Chronic Illnesses: General Considerations in Selecting Conventional and Integrative Treatments

Author(s)  Garth L. Nicolson
Department of Molecular Pathology, The Institute for Molecular Medicine, Huntington Beach, California, USA.

ABSTRACT

The presence of pathogenic mycoplasmas in various chronic illnesses and their successful suppression using conventional and integrative medicine approaches are reviewed. Evidence gathered over the last three decades has demonstrated the presence of pathogenic mycoplasma species in the blood, body fluids and tissues from patients with a variety of chronic clinical conditions: atypical pneumonia, asthma and other respiratory conditions; oral cavity infections; urogenital conditions; neurodegenerative and neurobehavioral diseases; autoimmune diseases; immunosuppressive diseases; inflammatory diseases; and illnesses and syndromes of unknown origin, such as fatiguing illnesses.
Only recently have these small intracellular bacteria received attention as possible causative agents, cofactors or opportunistic infections or co-infections in these and other conditions. Their clinical management is often inadequate, primarily because of missed diagnosis, under- and inadequate treatment and the presence of persister or dormant microorganisms due to biofilm, resistence and other mechanisms.
Pathogenic Mycoplasma species infections have been suppressed slowly by anti-microbial and integrative treatments, resulting in gradual reductions in morbidity, but not in every patient. Even if mycoplasmas are not a cause or an initial trigger for many chronic illnesses, they appear to play important roles in the inception, progression, morbidity and relapse of chronic illnesses in rather large patient subsets. Ignoring such infections can result in failure to achieve eventual patient recovery, even with application of potentially curative treatments.
___________________
**Comment**
As Dr. Breitshwerdt is the Bart Guru, Dr. Nicolson is the Mycoplasma King.  Both are involved intimately with pathogens that have changed their lives.  We owe these men a great debt as without their expertise and fortitude, we would be completely in the dark.  To read about Dr. Nicolson’s experience with bioweaponized Mycoplasma read the provocative book, “Project Daylily.”  I notice that he dedicated this article to his deceased wife who survived a lethal mycoplasma infection.
Please refer to the full-length article in the link at the top of the story but I’ve highlighted a few things below on how Mycoplasma evades the immune system as well as effective treatment.  There’s much, much more in the full-length article you should understand.
According to Dr. Nicolson, 80% of Lyme/MSIDS patients also have Mycoplasma.
CFS/ME patients according to PCR have various mycoplasmas.
Excerpt from section 2 on Host Response Systems:
Pathogenic mycoplasmas can evade immune recognition and destruction by undergoing rapid surface antigenic variations [7] [27]. Even with their slow intracellular growth rates, by rapidly altering their cell surface antigenic structures as well as modulating host immune responses, pathogenic mycoplasmas can evade host surveillance mechanisms [7] [27]. This helps explain the chronic nature of mycoplasmal infections and the inability of hosts to completely suppress pathogenic mycoplasmal infections via host responses that are effective against other more rapidly growing bacteria [27].
Excerpt from 4.12 Fatiguing Illnesses:
The most common fatiguing illness is chronic fatigue syndrome (CFS) or myalgic encephalomyelitis. This is an unexplained, long-term, persistent illness characterized by disabling fatigue plus additional signs and symptoms [98] [99]. Most if not all patients with CFS show evidence of chronic viral and bacterial infections (reviewed in [45] [47] ). In fact, the odds ratio for the presence of chronic infections was calculated to be 18.0 (p < 0.001), suggesting that CFS patients have a very high probability of multiple chronic infections [100]. The most commonly found infections (by PCR of blood monocytes) were various pathogenic species of mycoplasmas [100] [101].  M. pneumoniae was the most common mycoplasma species found, followed by M. fermentans, M. hominis, and M. penetrans [101].
Excerpt from Section 5 Treatment of Pathogenic Mycoplasmal Infections:
In many cases mycoplasmal infections are not the definitive infection that defines the condition. An example of this is chronic Lyme disease, a complex clinical condition with Borrelia species as the prominent infectious agent but with other bacterial, parasite, and viral components as co-infections [47] [119] [120] [121]. Pathogenic mycoplasmal co-infections are important in such multiple infection diseases, being present in up to 80% of chronic Lyme diseases cases [120] [122].
Excerpt from Section 5.1 Antimicrobial Treatments:

The conventional antimicrobial treatments of pathogenic mycoplasmal infections usually involve systemic therapy with oral antibiotics, but the choice of antibiotic(s) depends to a certain degree on the mycoplasma species being treated. Since mycoplasmas do not have a cell wall, antibiotics that act on cell wall synthesis are ineffective [2] [3] [7] [40] [50] [59] [124] [125]. Instead, mycoplasmas are treated with anti-microbials that attack their metabolism, replication, synthetic machinery or other specific bacterial targets. Since most mycoplasmas and ureaplasmas are generally sensitive to tetracyclines (doxycycline, minocycline, among others), with some notable exceptions, these should be considered for frontline treatment, and quinolones (ciprofloxacin, sparfloxacin, levofloxacin, ofloxacin, among others) [125] [126] [127] [128] , as alternative treatment. However, M. pneumoniae and M. genitalium strains are especially sensitive to macrolides (azithromycin, clarithromycin, erythromycin, among others), whereas M. hominis strains are usually resistant [126] [127] [128]. Ureaplasmas are moderately susceptible to macrolides [127] [128]. M. hominis and Ureaplasma urealyticum are generally more resistant to tetracyclines than other species [129] [130] , and M. hominis strains have been observed to be resistant to quinolones [131]. Some discussion of these antimicrobials and their uses in treating pathogenic mycoplasmal infections in chronic illnesses can be found in [132] [133] [134].

Treatment of pathogenic mycoplasma infections with oral antibiotics generally involves daily or pulsed treatment, such as every-other-day administration, at the maximum dose recommended for a particular antibiotic [132] [133] [134] [135]. Due to the cyclic nature of mycoplasmal proliferation some organizations recommend every-other-day antibiotic regimens [135].

Another important consideration is antibiotic resistance, which can occur during treatment [132] [138]. A major problem has been the shifting minimum inhibitory dose concentrations required to treat mycoplasmal infections with antibiotics, such as treatment of M. genitalium infections with oral tetracyclines [139]. This requires increasing dose levels or shifting to a different antibiotic regimen [132].

In most chronic illness patients pathogenic mycoplasma infections do not respond quickly to anti-microbial therapy, so long-term therapy must be considered [123] [132] [133] [135].

When antibiotics are used to treat pathogenic mycoplasmal infections, Jarisch-Herxheimer reactions (J-H reactions) usually occur [132] [141]. These are observed as temporary increases in the severity of signs and symptoms, and J-H reactions generally involve fevers, chills, muscle aches, fatigue, skin rashes, pain and other signs and symptoms related to cytokine release [141].

In most patients this has required prolonged treatments that have resulted in very slow recoveries, often requiring a year or more of treatment [48] [121] [123] [132] [133].

There are some alternative procedures that can increase the in vivo effectiveness of antimicrobial therapies. One method that has been used to increase the effectiveness of antibiotics has been the use of agents that increase the penetrability or the intracellular activities or effectiveness of antibiotics or other drugs. For example, the anti-malarial drug Plaquenil (hydroxychloroquine) has been used to alkalize intracellular compartments and improve antimicrobial entry and cytotoxic effects [121] [132] [145].

_____________________

For more:  https://madisonarealymesupportgroup.com/2015/08/12/connecting-dots-mycoplasma/

https://madisonarealymesupportgroup.com/2016/02/07/mycoplasma-treatment/

https://madisonarealymesupportgroup.com/2017/07/14/clinical-association-lyme-disease-and-guillain-barre/Epstein-Barr, also known as Mono, is an infection that triggers Guillain-Barre as well as mycoplasma and cytomegalovirus.  http://www.webmd.com/brain/tc/guillain-barre-syndrome-topic-overview#1

https://madisonarealymesupportgroup.com/2017/07/16/mycoplasma-and-other-intracellular-bacterial-infections-in-rheumatic-diseases-comorbid-condition-or-cause/

5-Week Old Girl With Lyme Disease Podcast

LYME PODCAST: 5-WEEK-OLD GIRL WITH LYME DISEASE

Lyme Disease Podcast: 5-week-old girl with Lyme disease

Welcome to an Inside Lyme case study. I find that the best way to get to know Lyme disease is through reviewing actual cases. In this case study, I will be discussing a 5-week old baby girl with Lyme disease. This case series will be discussed on my Facebook and made available on podcast and YouTube.

In this episode, I will be discussing a 5-week old baby girl with Lyme disease.

This case was described in the journal Pediatrics, written by Handel and colleagues in 2019.

This paper reminds parents of the need to look for a tick bite and Lyme disease even in babies. The authors described a healthy 5-week-old girl who was diagnosed with Lyme disease. The baby girl lived in Long Island, New York, an area endemic for Lyme disease.  The baby was rarely outdoors, but the family dog was allowed outdoors. The dog could have brought the baby in contact with the tick.  Other researchers have reported a higher risk of Lyme disease in pet owners.

The parents did not report seeing a tick. Instead, the parents removed “an engorged, black “bug” from behind her left ear six days before symptoms started.” writes Handel. This highlights the difficulties parents can face in recognizing a tick.

The fact that the presumed tick was engorged was also important. The risk of Lyme disease from an engorged tick is much higher.  The number of spirochetes rises as the tick takes a blood meal. The spirochetes in a tick have more time to multiply and migrate from the midgut of the tick to the salivary glands.  The higher numbers of spirochetes in the salivary gland, the more likely the bite will lead to a tick-borne disease.

The baby girl was diagnosed with early disseminated Lyme disease.  The rashes were typical with “multiple flat rings with peripheral blanching erythema, a central clearing, and outward expansion without tenderness or peripheral scaling” writes Handel.  He added, there was also a rash near the bite.  Early disseminated Lyme disease often occurs without the initial erythema migrans rash when the bacteria have already spread throughout the body.

The doctors hospitalized the baby.  The baby had a fever 101.1 and was irritable.  The tick-borne tests were negative, which is common in early Lyme disease. The western blot Lyme disease test was not performed, as the ELISA screen was negative.

The doctors were concerned that the baby might suffer from Lyme meningitis.  This is an uncommon but important concern for the doctor treating Lyme disease.  The spinal tap was not successful. The doctors treated for Lyme meningitis with intravenous antibiotics since they were still concerned the baby might have Lyme meningitis. The baby girl was discharged from the hospital after two weeks of intravenous ceftriaxone.

There were no complications on follow-up, according to the doctor.

The authors noted that there are few cases of babies being treated for tick-borne illnesses in the published literature. That does not mean that young children aren’t contracting tick-borne diseases in practice.  Children under the age of 5 years-of-age are the most likely to be infected with Lyme disease according to the CDC.

What can we learn from this case?

  1. Babies can be infected with a tick-borne infection even with little outdoor exposure.
  2. The family pet can bring a baby into contact with ticks.
  3. It can be difficult to determine if a baby has Lyme meningitis. The spinal tap in this 5-week-old baby girl was unsuccessful.  Even if the spinal tap had been successful, the spinal tap may be negative in neurologic Lyme disease.

What questions does this case raise?

  1. Would it have been helpful if the parents had recognized the “bug” as a tick?
  2. Would the parents or the doctor have recognized Lyme disease if the rash were single or atypicial?  The most common rash is a flat red rash in one study.
  3. Would the baby have been successfully treated with oral antibiotics rather than intravenous antibiotics?
  4. What if the baby did not have a rash? Would the doctor have been willing to use clinical judgment to diagnose Lyme disease in a baby?
  5. Would the IgM western blot test for Lyme disease have been positive if the doctor had ordered a western blot test?  The IgM western blot test is often positive in early Lyme disease.
  6. Would antibiotic treatment at the time of the engorged tick bite have prevented the need for a 24 days hospitalization, a spinal tap, and intravenous antibiotics in the baby girl?
  7. When is it important to perform a spinal tap?
  8. Will the baby girl develop a co-infection like Ehrlichia, Anaplasmosis, and Babesia? This is particularly important as the intravenous ceftriaxone prescribed for the baby would not be effective for these tick-borne infections.
  9. Will two weeks of intravenous antibiotics prevent chronic manifestations of Lyme disease?

TREATING TICK-BORNE DISEASE IN MY PRACTICE

In my practice, each individual requires a careful assessment. That is why I order tests a broad range of tests, including blood counts, liver and kidney function, thyroid disease, lupus, and rheumatoid arthritis in addition to tests for tick-borne infections. I also arrange consultations such as neurologists, rheumatologists, and ophthalmologists.

Many patients are complex, as highlighted in this Inside Lyme Podcast series.

We need more doctors with skills diagnosing and treating Lyme disease in children. We could use a reliable test to determine who has Lyme disease and a test to be sure Lyme disease has resolved. We need to determine the best course of treatment for babies.  In this case, were there oral antibiotics that would have been effective? We hope that if a professional sees a baby that they can use this case to remind them to look for Lyme disease and treat accordingly.

We also need to give doctors the freedom to treat these difficult cases without undue interference by colleagues, insurance companies, medical societies, and medical boards.

Inside Lyme Podcast Series

This Inside Lyme case series will be discussed on my Facebook and made available on podcast and YouTube.  As always, it is your likes, comments, and shares that help spread the word about this series and our work. If you can, please leave a review on iTunes or wherever else you get your podcasts.

Sign up for our newsletter to keep up with our cases.

References:
  1.  Two Neonates With Postnatally Acquired Tickborne Infections Andrew S. Handel, Harriet Hellman and Saul R. Hymes Pediatrics 2019;144;