Archive for the ‘Lyme’ Category

WLN Newsletter Feb. 2019

At_a_Glance-February_2019

WLN-Logo-copy-300x84

Highlights (Newsletter in link):

  • Condolences to Lyme Advocate Kristin Collins on the death of her mother
  • Opportunities to Volunteer
  • Article on “Why Mainstream Lyme/MSIDS Research Remains in the Dark Ages”
  • Upcoming WI Lyme Conference in La Crosse, March 23, 2019
  • Upcoming WI Lyme Walk (Date TBD)
  • Upcoming WI Lyme Support Group Meetings
  • WLN Fundraising to educate WI doctors – selling permethrin treated socks:  https://wisconsinlymenetwork.z2systems.com/np/clients/wisconsinlymenetwork/giftstore.jsp


Lyme Disease: Don’t Wait For Blood Tests Where Patients Have ‘Bullseye’ Rash

https://www.independent.co.uk/news/health/lyme-disease-rash-tick-bite-infection-antibiotics-gp-nice-bulls-eye-a8774511.html  (News Story in Link)

Alex Matthews-King Health Correspondent

11 Feb 2019

Lyme Disease:  Doctors Told Don’t Wait For Blood Tests Where Patients Have ‘Bullseye’ Rash

Doctors have been told to diagnose Lyme disease without waiting for blood test results if patients have the characteristic “bull’s eye” rash.

Blood tests for the tick-borne infections may miss the condition in the early weeks, according to new draft guidance published by the National Institute for Health and Care Excellence (Nice).

This could reduce the chances of a full recovery, the NHS treatment watchdog said. As a result, it said patients should be offered antibiotics where they show the characteristic ringed rash, known as erythema migrans.

The bull’s eye rash appears in around two thirds of cases usually within a month of a bite from an infected tick.

“For most people with Lyme disease, a course of antibiotics will be effective, so it is important we diagnose and treat people as soon as possible,” Professor Gillian Leng, director of health and social care at Nice, said. “A person with Lyme disease may present with a wide range of symptoms, so we have clear advice for professionals about the use of lab tests for diagnosis and the most appropriate antibiotic treatments.”

Tests can check for antibodies in the blood, however these may not appear until up to eight weeks after the patient is bitten.

It is hoped the new draft guidance will increase the number of early diagnoses and allow patients to receive treatment immediately, reducing the risk of further symptoms developing.

When there is no rash present and symptoms are unclear, doctors will be advised to carry out blood tests.

Professor Saul Faust, chairman of the guideline committee, said:

“Lab tests are necessary when a person’s symptoms are unclear, but they are not needed if a person presents the characteristic red rash, erythema migrans. Doctors should feel confident to prescribe antibiotics immediately for those with erythema migrans.”

Veronica Hughes, chief executive of Caudwell LymeCo, a UK charity for patients with Lyme disease, said:

“Waiting for blood test results always delays treatment. When a patient has the rash, this delay is unnecessary and reduces the likelihood of total cure.”

Additional reporting by Press Association

____________________

**Comment**

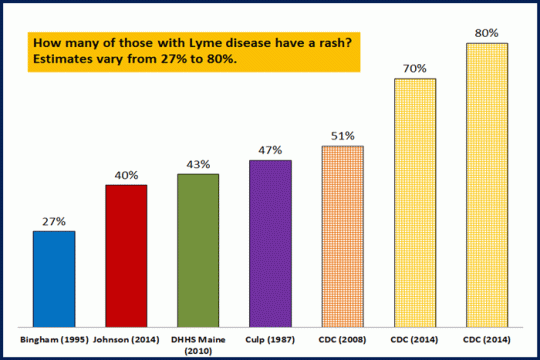
EM rash = Lyme.  Period.  The sad thing is many do not present with the classic EM rash, if they have a rash at all.  The statement that two thirds present with the rash is objectionable.  This article states the percentage varies from 27-80%, hardly a set number.  https://www.lymedisease.org/lymepolicywonk-how-many-of-those-with-lyme-disease-have-the-rash-estimates-range-from-27-80-2/  (Table from this link)

Rashes-larger-blog

Please notice that the CDC has much higher percentages.  Why?  They are using the surveillance definition for recording Lyme cases.  This will naturally skew percentages towards rash reporting.  It won’t include the thousands upon thousands that don’t notice or have the rash.  Even the CDC with it’s stringent criteria report the percentages vary widely depending upon the state.

Also, rashes vary widely.  Clinical diagnosis must consider any skin rash, regardless of its resemblance to the bull’s-eye.   

“Researchers note that multiple textbooks and websites prominently feature the bull’s-eye image as a visual representation of Lyme disease.” They write, “This emphasis on target-like lesions may have inadvertently contributed to an underappreciation for atypical skin lesions caused by Lyme disease.” — Some Visible Signs of Lyme Disease Are Easily Missed or Mistaken, Science Daily, Apr 22, 2013 https://www.sciencedaily.com/releases/2013/04/130422132507.htm?utm_source=feedburner&utm_medium=email&utm_campaign=Feed%3A+sciencedaily%2Fhealth_medicine%2Flyme_disease+%28ScienceDaily%3A+Health+%26+Medicine+News+–+Lyme+Disease%29

Good news:  you have a perfect EM rash you get treatment.  Bad news:  those with an atypical rash and those without a rash are hung out to dry.


Midcoast Lyme Conference “Empowering the Patient” FREE in April

ext


Serology Test for Lyme Virtually Worthless

https://www.change.org/p/the-us-senate-calling-for-a-congressional-investigation-of-the-cdc-idsa-and-aldf/u/24192106?cs_tk=As2-

Diagnostic Tests for Lyme Disease

FEB 19, 2019 — 

Wormser, Steere and Molins from the CDC are looking to promote antibody tests for Lyme disease while everyone knows these tests are virtually useless for 4-6 weeks after a tick bite and too restrictive thereafter. These two con artists need to retire.

——— Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To: tickbornedisease@hhs.gov, brett.giroir@hhs.gov
Cc: (79 Undisclosed recipients)
Date: February 18, 2019 at 11:11 AM
Subject: Diagnostic Tests for Lyme Disease

To: the Tick Borne Disease Working Group and ADM Brett P. Giroir, M.D., Assistant Secretary for Health,

Per the link below, Dr. Allen Steere filed a patent in 2013 for yet more antibody detection tests for Lyme disease: (Application #20150219646)

Compositions and Methods for the Detection of Bacterial Infections Associated with Lyme Disease
https://patents.justia.com/patent/20150219646

Faulty/misleading antibody tests are the root cause of unimaginable pain and suffering as we are all aware of Dr. Neil Spector’s need for a heart transplant after his antibody tests for Lyme were repeatedly negative. Lives are being ruined through false negative Lyme disease tests results.

Serology cannot be used to gauge treatment failure or success which is ideal for concealing chronic infection while perpetuating the dogma/racketeering scheme downplaying the severity of Lyme.

The following letter was forwarded to the Editors of multiple journals to warn of any future papers promoting antibody detection of Borrelia infection. It is time to fast track direct detection methods for all species of Borrelia in all stages of disease. Lyme has become a public health disaster under the direction of the US Centers for Disease Control.

Letter to the Editors:

———- Original Message ———-
From: CARL TUTTLE <runagain@comcast.net>
To:editor.cmo@clinicalmedicaljournals.com,clinmicrobiol@microbiologyinsights.com,in3011@poh.osaka-med.ac.jp,volker.kroemker@hs-hannover.de,udai.singh@uscmed.sc.edu,rschooley@ucsd.edu
Date: February 18, 2019 at 7:49 AM
Subject: Diagnostic Tests for Lyme Disease
JAMA

Clinical Infectious Diseases

Clinical Microbiology

To the Editors,

Before Wormser, Steere and Molins (from the CDC) publish any of their promotional papers in your Journal regarding tests for Borrelia infection I would like to point out the following paper recently acknowledging that current antibody tests are inadequate for the management of Lyme disease.

Direct Diagnostic Tests for Lyme Disease

Clinical Infectious Diseases, ciy614, https://doi.org/10.1093/cid/ciy614

Published: 11 October 2018 (Coauthored by Dr. Paul Mead of the CDC)

Excerpt:

“… serologic tests cannot distinguish active infection, past infection, or reinfection. Reliable direct-detection methods for active B. burgdorferi infection have been lacking in the past but are needed and appear achievable.”

_____________________________

Failure to include this reference in any manuscript involving serology for the detection of Borrelia would be misleading the reader and may tarnish the peer-review process at your journal.

Sincerely,

Carl Tuttle

Hudson, NH USA

_________________________
**Comment**
Keep in mind there is a long & sordid history of serology testing for Lyme:  https://madisonarealymesupportgroup.com/2018/04/03/cdc-deliberately-avoids-direct-detection-testing-methods-for-ld/  Excerpt:

It would appear that there has been a deliberate avoidance of direct detection methods and it is believed that these efforts are to insure that the current thirty year dogma remain intact.

We have a dire need to develop rapid detection methods for a serious growing health threat which has the ability to disable its victim as described in the attached letter addressed to the previous Director of the CDC. (Please see attachment in link)

I would like to point out that employees of the U.S. Centers for Disease Control hold patents on metabolomics (Lyme tests).

CDC Employee Patent:https://www.google.com/patents/EP2805168A1?cl=en

For nearly four decades now the only FDA approved test for Lyme disease is the indirect two-tiered antibody test. Direct detection methods to identify the causative agent responsible for the disease have been avoided, criticized and shelved.

https://madisonarealymesupportgroup.com/2018/12/16/laboratory-testing-for-lyme-disease/  Direct detection laboratory testing (DNA/PCR Sequencing) is used for many infections (Ebola (1), Zika (2), Bartonella (3) etc.) but not Lyme disease.

More on testing:  https://madisonarealymesupportgroup.com/2018/09/12/lyme-testing-problems-solutions/

https://madisonarealymesupportgroup.com/2018/10/13/direct-test-for-ld-carl-tuttle-chews-up-cdc-spits-them-out/

https://madisonarealymesupportgroup.com/2017/12/13/suppression-of-microscopy-for-lyme-diagnostics-professor-laane/  Excerpt:

After publishing the 2013 article ‘A simple method for the detection of live Borrelia spirochetes in human blood using classical microscopy techniques’, professor Laane was invited to give a lecture at the 2014 Norvect conference in Oslo. An English patient saved the pdf, so you can still read it, via the link provided.

I was present at that conference and still remember how nervous he was. The reason was that several medical professors complained to his university. He was threatened with losing his job, if he would speak at the conference.

In fact, he did not literally speak – as you can see in the movie below – but used performing arts to show the slides of the spirochetes. Professor Laane was fired anyway and his laboratory was closed down.

CDC Endorsement of Single Dose Antibiotic for Lyme Challenged

https://www.webwire.com/ViewPressRel.asp?aId=235946

CDC Endorsement of Single Dose Antibiotic for Lyme Disease Prevention Challenged

Advocates claim policy harms patients and violates HHS standards for information quality

Washington, DC – WEBWIRE – Tuesday, February 19, 2019

CDC’s endorsement of the IDSA recomendation for a single dose of doxyclycline to prevent Lyme Disease has potential to cause serious harm to patients for whom the prophylaxis fails to prevent infection.

Advocates for Lyme disease patients are calling on the Centers for Disease Control and Prevention (CDC) to withdraw its endorsement of single-dose antibiotic prophylaxis for prevention of Lyme disease after a tick bite.

A key limitation of the recommendation is that it is based on a single study that has not been replicated and which did not prove that the prophylaxis actually prevented Lyme disease. In addition, the recommendation is restrictive since it is only recommended if certain criteria are met. This is likely to confuse both the public and health care providers.

The recommendation on tick bite prophylaxis is from the Infectious Diseases Society of America (IDSA) 2006 guidelines for diagnosis and treatment of Lyme disease.

In addition to being more than a decade out of date, the IDSA guidelines are based on low-quality evidence and are widely regarded as critically flawed. The National Academy of Medicine report, Clinical Practice Guidelines We Can Trust, cites the 2006 IDSA Lyme guidelines to illustrate the problems of conflicts of interests, lack of transparency, and scientific bias in guidelines development.

On February 14, the Patient Centered Care Advocacy Group filed an “information quality request for correction” with CDC’s Office of the Associate Director for Science.

The complaint argues that the IDSA recommendation endorsed by CDC

“lacks utility, objectivity, and integrity and misleads patients and healthcare providers. This not only can result in human harm but can increase the number of long-term Lyme disease cases, worsening the current Lyme epidemic and increasing the financial impact on our country in terms of lost productivity, disability, and increased medical expenses.”

The contested information on tick-bite prophylaxis—which is included on CDC’s website and in the CDC publication, Tick-Borne Diseases of the United States, Fifth Edition, 2018—states:

“The Infectious Disease Society of America (IDSA) does not generally recommend antimicrobial prophylaxis for prevention of Lyme disease after a recognized tick bite. However, in areas that are highly endemic for Lyme disease, a single dose of doxycycline may be offered to adult patients (200 mg) who are not pregnant and to children older than 8 years of age…”

According to Holly Ahern, associate professor of microbiology at SUNY Adirondack and Lyme Action Network board member, this recommendation is based on a single study from 2001 that has not been reproduced and which has the following scientific limitations:

  1. The “primary endpoint” used to determine whether the prophylactic treatment “prevented” Lyme disease was the appearance of an erythema migrans rash at the site of the tick bite. More recent studies consistently show that the rate of any type of skin rash is less than 50%, and the rate of EM is less than 10%. Therefore this study excludes more than half of true cases of Lyme disease from the data analysis.
  2. Subjects who developed subjective symptoms of Lyme disease such as headaches, profound fatigue, brain fog, joint pain without swelling, weakness, numbness, or difficulty controlling specific muscles were excluded from the data analysis.
  3. Participants were only observed for 6 weeks before being considered “negative” for Lyme disease, and therefore persons who developed symptoms after 6 weeks were excluded from the data analysis.

The complaint maintains that,

“Patients and healthcare providers alike gain a false sense that a tick-borne disease was prevented with this prophylaxis and, therefore, full treatment may be delayed or denied. Research shows that delayed treatment increases the rate of treatment failure. In addition, this partial treatment has been shown to result in false negative blood test results for Lyme disease in the future.”

According to Bruce Fries, president of the Patient Centered Care Advocacy Group and lead author of the complaint:

“CDC’s endorsement of the IDSA recommendation for a single dose of doxycycline to prevent Lyme Disease has potential to cause serious harm to patients for whom the prophylaxis fails to prevent infection.  CDC’s dissemination of this information also violates HHS Guidelines for Ensuring and Maximizing the Quality, Objectivity, Utility, and Integrity of Information Disseminated to the Public.”

Fries says

“It should be noted that the IDSA guidelines represent one of two standards of care for Lyme disease. More recent and comprehensive evidence-based guidelines for Lyme disease were published by the International Lyme and Associated Diseases Society (ILADS) in 2014. The ILADS guidelines, which are fully compliant with current standards, specifically recommend against a single dose of doxycycline for prevention of Lyme disease.”

To read the full complaint visit: https://tinyurl.com/CDC-Misinfo

___________________

For More:

Yet, despite the lack of evidence, many are doing it:  https://madisonarealymesupportgroup.com/2017/08/09/one-dose-of-antibiotic-for-lyme-disease-in-rhode-island/

Dr. Zhang has stated that it has been shown that doxycycline as a mono therapy can throw borrelia into a more persistent form (round body forms).  This is something the CDC/NIH/IDSA isn’t acknowledging at all.  https://www.ncbi.nlm.nih.gov/pubmed/21753890# Doxycycline reduced spirochetal structures ∼90% but increased the number of round body forms about twofold.
I guess since a researcher outside The Cabal discovered this – it is tossed out like yesterday’s garbage.