MetLife Discrimination Against Chronic Lyme Patient Engages Senior Vice President of Global Benefits for Comcast and NBCUniversal and an International Human Rights Expert
In 2016, international human rights expert Jenna Luché-Thayer and founder of the Global Response to Borreliosis and Coinfections Consortium (Global RBCC) responded to a cry for help from Jane Furer, an NBCLA producer who is living with chronic Lyme. Jane’s illness had led to her being unable to work for a year, and even though the State of California had provided her short-term disability benefits, insurer MetLife refused to cover her longer-term disability.
Luché-Thayer then secured documentation demonstrating how MetLife made bad faith practices and discriminated against Jane Furer. This discrimination is based on Jane’s suffering from a chronic and complicated case of Lyme disease. According to Luché-Thayer, MetLife and other insurance companies routinely deny benefits to persons living with chronic Lyme despite the Affordable Care Act’s (ACA) formal recognition of chronic Lyme disease in 2012. Not only does the ACA recognize chronic Lyme, the federal Job Accommodation Network (JAN) also recognizes chronic Lyme and assists those who suffer from this illness to receive disability benefits. JAN is a service provided by the Department of Labor to support the Americans with Disabilities Act.
MetLife’s denial of Jane’s benefits was based on the outdated science found in the 2006 Infectious Diseases Society of America’s Lyme disease guidelines –these outdated guidelines do not meet the Institute of Medicine’s (IOM) internationally accepted 2011 standards for guidelines and they do not recognize chronic Lyme disease. MetLife’s practice of discrimination is demonstrated by their refusal to adopt Lyme treatment guidelines that do meet the IOM 2011 standards –these updated guidelines recognize chronic Lyme and the many debilitations and disability it may cause.
Luché-Thayer also found that MetLife fraudulently misrepresented their legal responsibility for Jane’s coverage –as well as that of Jane’s employer– in correspondence to a senior official with the state of Pennsylvania’s Insurance Department. Luché-Thayer brought this to the attention of Comcast/ NBCUniversal.
Shawn Leavitt, the Senior Vice President of Global Benefits for Comcast and NBCUniversal, personally engaged to try and address the situation. Leavitt expressed concern and has since facilitated collaboration between Global RBCC and key medical staff at Comcast and NBCUniversal resulting in the dissemination of updated science on Lyme disease. Most recently, an interactive quiz on Lyme disease –developed by Dr. Holly Ahern, professor of microbiology and member of Global RBCC– was used as an educational tool for Comcast employees. When Jane heard about the quiz, she said, “I am glad to know my situation might help other Comcast and NBCUniversal employees.”
In June 2017, Luché-Thayer organized an international team of scientists, medical professionals, human rights experts and patient advocates to testify before the United Nations Special Rapporteur responsible for health and human rights. The human rights violations validated included the obstruction to treatment options and coverage for the many confirmed serious complications and disability caused by Lyme disease.
In the meanwhile, NBCLA producer Jane Furer remains uncompensated for her extended period of disability that left her unable to work. With support from NBCUniversal, she is working less than full time under the protection of the Americans with Disabilities Act and while still under significant therapy, including intravenous treatment taken at her desk.
Much of this treatment is not covered because most health insurers use the outdated 2006 IDSA guidelines to determine treatment coverage as opposed to the protocols that have met the 2011 IOM standards. Jane asks, “How can I possibly afford to pay for policies that do not cover my Lyme disease expenses … particularly when I have children to care for and I used up all available financial resources because MetLife refused to provide my disability coverage?”
Luché-Thayer believes such practices of discrimination could be quickly overturned when employers realize just how much it is costing them in loss of skilled labor, productivity and absenteeism. For example, according to the CDC, Lyme disease is found in 48 states. Based on the CDC’s conservative estimate of annual Lyme disease infection, their 2017 article on persistent infection and their 2006 study on the cost of Lyme disease, Lyme disease may already be costing Comcast/NBCUniversal over four million dollars per year for new infections.
Says Luché-Thayer, “This calculation of four million does not include the estimated 36 percent of those infected who will develop long-term illness that is often not covered by insurance. This illness causes significant financial stress for employers, employees and their families.” For example, based on CDC infection estimates, between 2011 and 2017, more than 3200 new Lyme patients and 1000 new chronically ill Lyme patients needed medical, or medical and disability coverage from their Comcast/NBCUniversal employee benefits packages.
Lyme patients – including many who go undiagnosed due to the low accuracy of the standard tests– may have compromised function and neurological symptoms that impair driving, vision, climbing, technical proficiency, and judgement. These impairments are considered serious enough that federal authorities such as the Federal Aviation Administration ground infected pilots until they are six months clear of Lyme symptoms.
Luché-Thayer asks, “Why would any major employer allow for their employee benefits to not properly cover the treatments and disabilities caused by the fastest growing vector borne disease in the nation?”
POSTED ON AUGUST 23, 2017
In this week’s issue of PEOPLE, former Real Housewives of Beverly Hills star Yolanda Hadid opens up about her battle with late-stage Lyme disease, and how the illness drove her to contemplate suicide. But what is the mysterious illness?
Lyme disease is a potentially debilitating infection caused by bacteria called Borrelia burgdorferi, and is transmitted through the bite of an infected blacklegged tick.
“For some people, Lyme is easily treated but for others this disease is devastating,” says Linda Giampa, executive director of the Bay Area Lyme Foundation. The CDC has also documented cases in which Lyme has been fatal. (See link for article)
For more on Hadid’s struggle with Lyme, check out her new memoir – Believe Me: My Battle with the Invisibility of Lyme Disease – which comes out Sept. 12.
BVIKZ interview The sound of the movie is softer than intended, so it is subtitled in both English and Dutch. Click on settings to select your language.
The BVIKZ, the Interest Group for Intensive Child Care, is doing an ongoing investigation into false claims of child neglect and abuse by the Dutch Child Protection Services. It has now compiled and researched 168 individual cases. Over thirty percent of these cases are about children with Lyme disease.
During the last eight months hundreds of Dutch parents have been contacting the BVIKZ to report what happened to them. They have also received many reports from parents of children with Lyme disease. National media made this into a primetime topic, which was viewed by 1.5 million people. Shortly afterwards the BVIKZ had their third meeting with the Board of the Dutch Child Protection Services called ‘Safe Home’ (SH).
BVIZK chairman Vera Hooglugt agreed to do an exclusive interview for the On Lyme Foundation. We asked her to tell about their general findings of the BVIKZ investigation and specifically about the Lyme cases. The interview took us over three hours.
The BVIKZ has been working intensively to build all cases, scan all files, support the traumatised parents and children, assist in conversations, provide legal help and build up a case to create political impact to fundamentally change the way the whole system is operating. The meetings with SH are absolutely very important for the process.
Hooglugt thinks that they are only just seeing the tip of a much larger iceberg and wants to encourage other parents to be brave and come with their complaints in case of false allegations.
The tipping process
Tips or reporting seem to come from all angles. Tips come from all angles and we have the impression that the ones doing the reporting don’t realise how much impact it can have on the lives of the children and the families.
Almost all of the reports we saw are subjective and most are very suggestive. As an independent organisation we can really be neutral and unbiased enough to look at the claims without prejudice. So we strip all assumptions, subjective ‘gut feelings’ and also check on the motives of the ones doing the reporting.
Too often we see that the child’s best interests in not at stake. We often see divorced husbands reporting on their ex-wives. The system just regards this as an objective fact, worthy of a formal investigation.
Another example is a government official charged with school absence, who had already given the child leave to skip school. When the family moved house, he found what province they had moved to and asked his colleague to assist in filing in a report on ‘child abuse’.
In another case a commercial company was annoyed that they did not get a contract, because the parents did not find the care provided as fitting for their child. The company reported on the parents and SH did a year long investigation, wrecking the social life of this family.
We urged the parents to ask for the original report, which is within their rights. Their request was denied without reason, so we filed a request as their formal representative.
We then received a paper copy, in which a large part of the text was white-washed. Again we requested the original digital version from SH, but were told that it was deleted due to computer problems. Finally we managed to get the original complaint. By comparing the different versions we could see that all subjective remarks were white-washed.
Employees of the Consultation Office, where new parents go to check on their baby’s health and progress, have been reporting them to SH. Simply for not vaccinating their child or wanting to use other services offered by this institution.
Another poignant case is the one of an adult lady, who suffers from Lyme Disease and who is been taken care of by her old mother. She cannot stand light or sound, so she lives in a darkened room. The mother of a distant acquaintance of their neighbour reported on them, after hearing a gossip story about closed curtains. People like her seem to be influenced by prompting calls in the media.
In this case SH tried to get a psychiatrist to both judge the mother with ‘Munchausen by Proxy’ and proclaim the daughter legally ‘incompetent’ (not having her own will). This would allow them to lock her up in a psychiatric ward and blame the mother. Why would Youth Care deal with someone who is of age? After a change in Dutch policy they now have the function to provide safety in everyone’s life; from zero to hundred.
Although these examples are shocking enough in themselves, we also saw statements of how family doctors state that they were intimidated by SH to testify against their patients. Fortunately they refused to act against their Hippocratic Oath to ‘first not do harm’.”
The foundation of the accusations
In all cases we see how easy it has been made for anyone to report on everyone else. This allows everyone to report, without a proper filter in the system. Even though a ‘code of conduct’ has to be used, we see that happening far too little. Although Dutch Law obliges SH to do ‘truth finding’ or objective research, we don’t see this is organised well enough by the different organsiations involved in this field. Our conclusion is that a legal perspective needs to be added: are there enough facts present to merit an investigation.
SH does work with the ‘Triage Model’, but if you look into it, you see meaningless categories and no expertise to actually judge them. The overall tendency is that the people working at SH are committed to ‘win the game’, no matter what. In our investigation we do a scan on who is doing the reporting.
We have compiled a spreadsheet of what is being used as the basis for the allegations. Concerns for ‘social isolation’, ‘cognitive well-being’, ‘somatic well-being’, ‘emotional well-being’. Not going to school for a few weeks is considered as damaging the ‘cognitive well-being’ of the child and thus framed as ‘child abuse’.
So these definitions used in this Triage model are so broad that any report, no matter how suggestive, automatically leads to a formal investigation. The fact that a child has not been to school for several weeks, is framed as ‘damage to mental mental health’ and later as child abuse.
If you look at how these organisations build their cases, these ‘investigations’ serve one purpose only: to get their way. The result is forced measures that are imposed on the family. In Dutch these are either called OTS (state surveillance) or UHP (placement in a foster home).
From all the files we have studied, the fosters from almost all these organisations are disastrous for the children. In a case of a girl with Lyme the foster told her that she was faking the disease and that since his contract said he should force her to go the school, that was what he would do. The girl fell asleep within one hour in class out of pure misery.
Reversed proof
Oftentimes we help parents in these cases. From this experience and the 168 cases we have already investigated, we see that SH operates from a predisposed distrust. They are backed up in this attitude by the organizations that are supposed to provide an objective and unbiased check.
Parents are charged under Criminal Law (articles 300 – 304 in Dutch criminal law). What shocked us is that they are forced to cooperate towards their own conviction. In essence this means that parents are convicted upfront, unless they can proof they are innocent, which is hard to do, given the amount of stereotyping. (attorney Richard Korver, who was recently interviewed in Dutch to provide practical information to parents with children with Lyme, suggested that the legal prinpicple of Confidence be used more often. This means to start with the assumption of attitude that most people simply care for their children; unless proven otherwise.)
Often on the same day a child is released, we see SH apply for a fast track procedure in court. Without the needed for any further research, custody is taken away, based solely on the claim that there is ’eminent danger in the home situation’.
Different organizations are supposed to act as an impartial factor, but we basically see copying and pasting. SH copies the subjective tips and frames them into legal language. The Council for Child Protection (RvdK) copies these reports in their independent evaluation. Judges copy these conclusions in their verdicts. The other side is not even heard.
The Lyme cases
“We have now researched over fifty cases; the ones which we have fully assembled. These people came after the On Lyme Foundation and the Dutch Federation for Lyme Patients (NVLP) notified them to our research. We had no idea Lyme was such a problem because of the medical and political controversies around it.
We have the strong impression that there are many more Lyme parents, who have become victim of SH but who do not yet dare to contact us. Some parents are so traumatized, it takes us ten phone calls to reassure them that their information is really save with us.
We do see some specific differences with other diseases, which have a less disputed status. Apparently national Lyme policies dictate that after a few weeks of treatment, the cause of the disease is suddenly a ‘mental issue’ (called MUS: Medically Unexplained Symptoms). Regardless of the fact that these children are still as ill as before.
Again and again we hear stories of parents who tried everything to get medical help in the Netherlands, but who had to go abroad to find better help. The SH doctors overrule the decisions of these specialised physicians instead of cooperating with them.
Suggestions to remedy the system
Some political parties have started to get interested now; however, what they propose is by far not enough to put a stop to this.
If our investigation of these 168 cases is any indication of the general tendency of how the whole chain of Youth Care acts, we are facing a very grave problem. Every day new cases come in and we cannot even keep up with it, since we want to research it meticulously.
In short our recommendations would be:
Awareness of the ones doing the reporting & how much impact it can have
A better check on the validity of the reports, before the start of a formal investigation
Create an independent supervisory system with a Disciplinary Board
Stop SH doctors from questioning or interfering with medical care without consulting with the parents and other specialists
Judges should have their own check instead of relying on the reports of this system
Stop the liberty of SH to order a fast track judgement, with no need for any investigation
Provide money for aftercare of the victims, but certainly not by SH itself
Have the Inspection perform an investigation into how SH operates
Looking at the stacks of paperwork on their table, BVIKZ concludes: “This is the actual child abuse”.
A call to parents
The BVIKZ has to limit its investigation to the Netherlands and can hardly deal with the number of complaints now. Still, they encourage Dutch parents to file their complaints with them, so that together they can make a difference and stop the system from traumatising families like this. You can report them by email.
The On Lyme Foundation however would like to get an impression of the number of parents who faced similar situations in other countries. If you are not from the Netherlands, but you had similar experience because your children suffered from Lyme or its many misdiagnoses, you can mail us (also confidentially, of course) with a short description of what happened.
Note from the interviewer
This topic ties into what is recently discovered regarding the role of the World Health Organization (WHO) regarding the international diagnostic codes for Lyme disease. The WHO has not properly updated their ICD-codes to reflect the many conditions caused by Lyme borreliosis.
These outdated codes contribute to children being classified as having ‘non-specific’ illnesses and having treatments that are ‘experimental’. This allows for the allegations towards both parents and their ill children as well as their expert physicians.
Similar abuses can befall anyone, but is it particularly problematic for those who are already vulnerable. The outdated codes contribute to discrimination and marginalization by many institutions against this patient group.
This topic has hardly even been broached here in the U.S., but abuse allegations are happening regularly to families with Lyme/MSIDS. This is why I support the Parental Rights Amendment so parents are not forced to comply with the arbitrary U.N. Rights of the Child which effectively imposes international law upon families which is NOT in the best interest of children. For more: https://madisonarealymesupportgroup.com/2017/04/20/why-we-need-the-parental-rights-amendment/
https://madisonarealymesupportgroup.com/2017/05/18/first-peer-reviewed-study-of-vaccinated-vs-unvaccinated-children/ For families struggling with Lyme Disease, they are already fighting a system that doesn’t know how to cope with very ill children who often can’t keep up. Their little bodies are in a raging war of epic proportions. They are often bullied and mocked not only by peers but even by teachers and standard medical professionals who believe they are just being lazy. Infected, exhausted parents often don’t have the energy to fight the “mandatory vaccine” regimens being pushed upon them so just go along rather than weighing in their child’s current health issues. The entire system is stacked against them – forcing many to homeschool just to avoid the unbelievable pressure to conform.
LYMEPOLICYWONK: Canine maps predict Lyme disease risk better than the CDC does.
Dogs are considered a good gauge of the exposure of their human owners to infected ticks because they usually share the same environment and visit the same outdoor areas. In other words, canines are considered to be sentinel indicators of Lyme disease risk for humans. Not all dogs who test positive for Lyme antibodies are ill. However, they have been exposed to the Lyme disease bacteria.
A combination of studies out of the Netherlands found that hunters and their hunting dogs had tested positive for Lyme disease at similar rates (17% hunting dogs vs. 15% hunters.)
However, the same study found that pet ownership itself did not increase risk, but that exposure was the primary factor: “Only 12% of the seropositive hunters had hunting dogs which were also seropositive. Moreover, hunters without dog ownership showed no significantly lower rates of seropositivity.”
Unlike people, dogs are routinely screened for Lyme disease and other common co-infections by their vets. IDEXX has tracked Lyme disease and other tick-borne diseases in canines for years by collecting data from veterinarians who test dogs at annual check-ups.
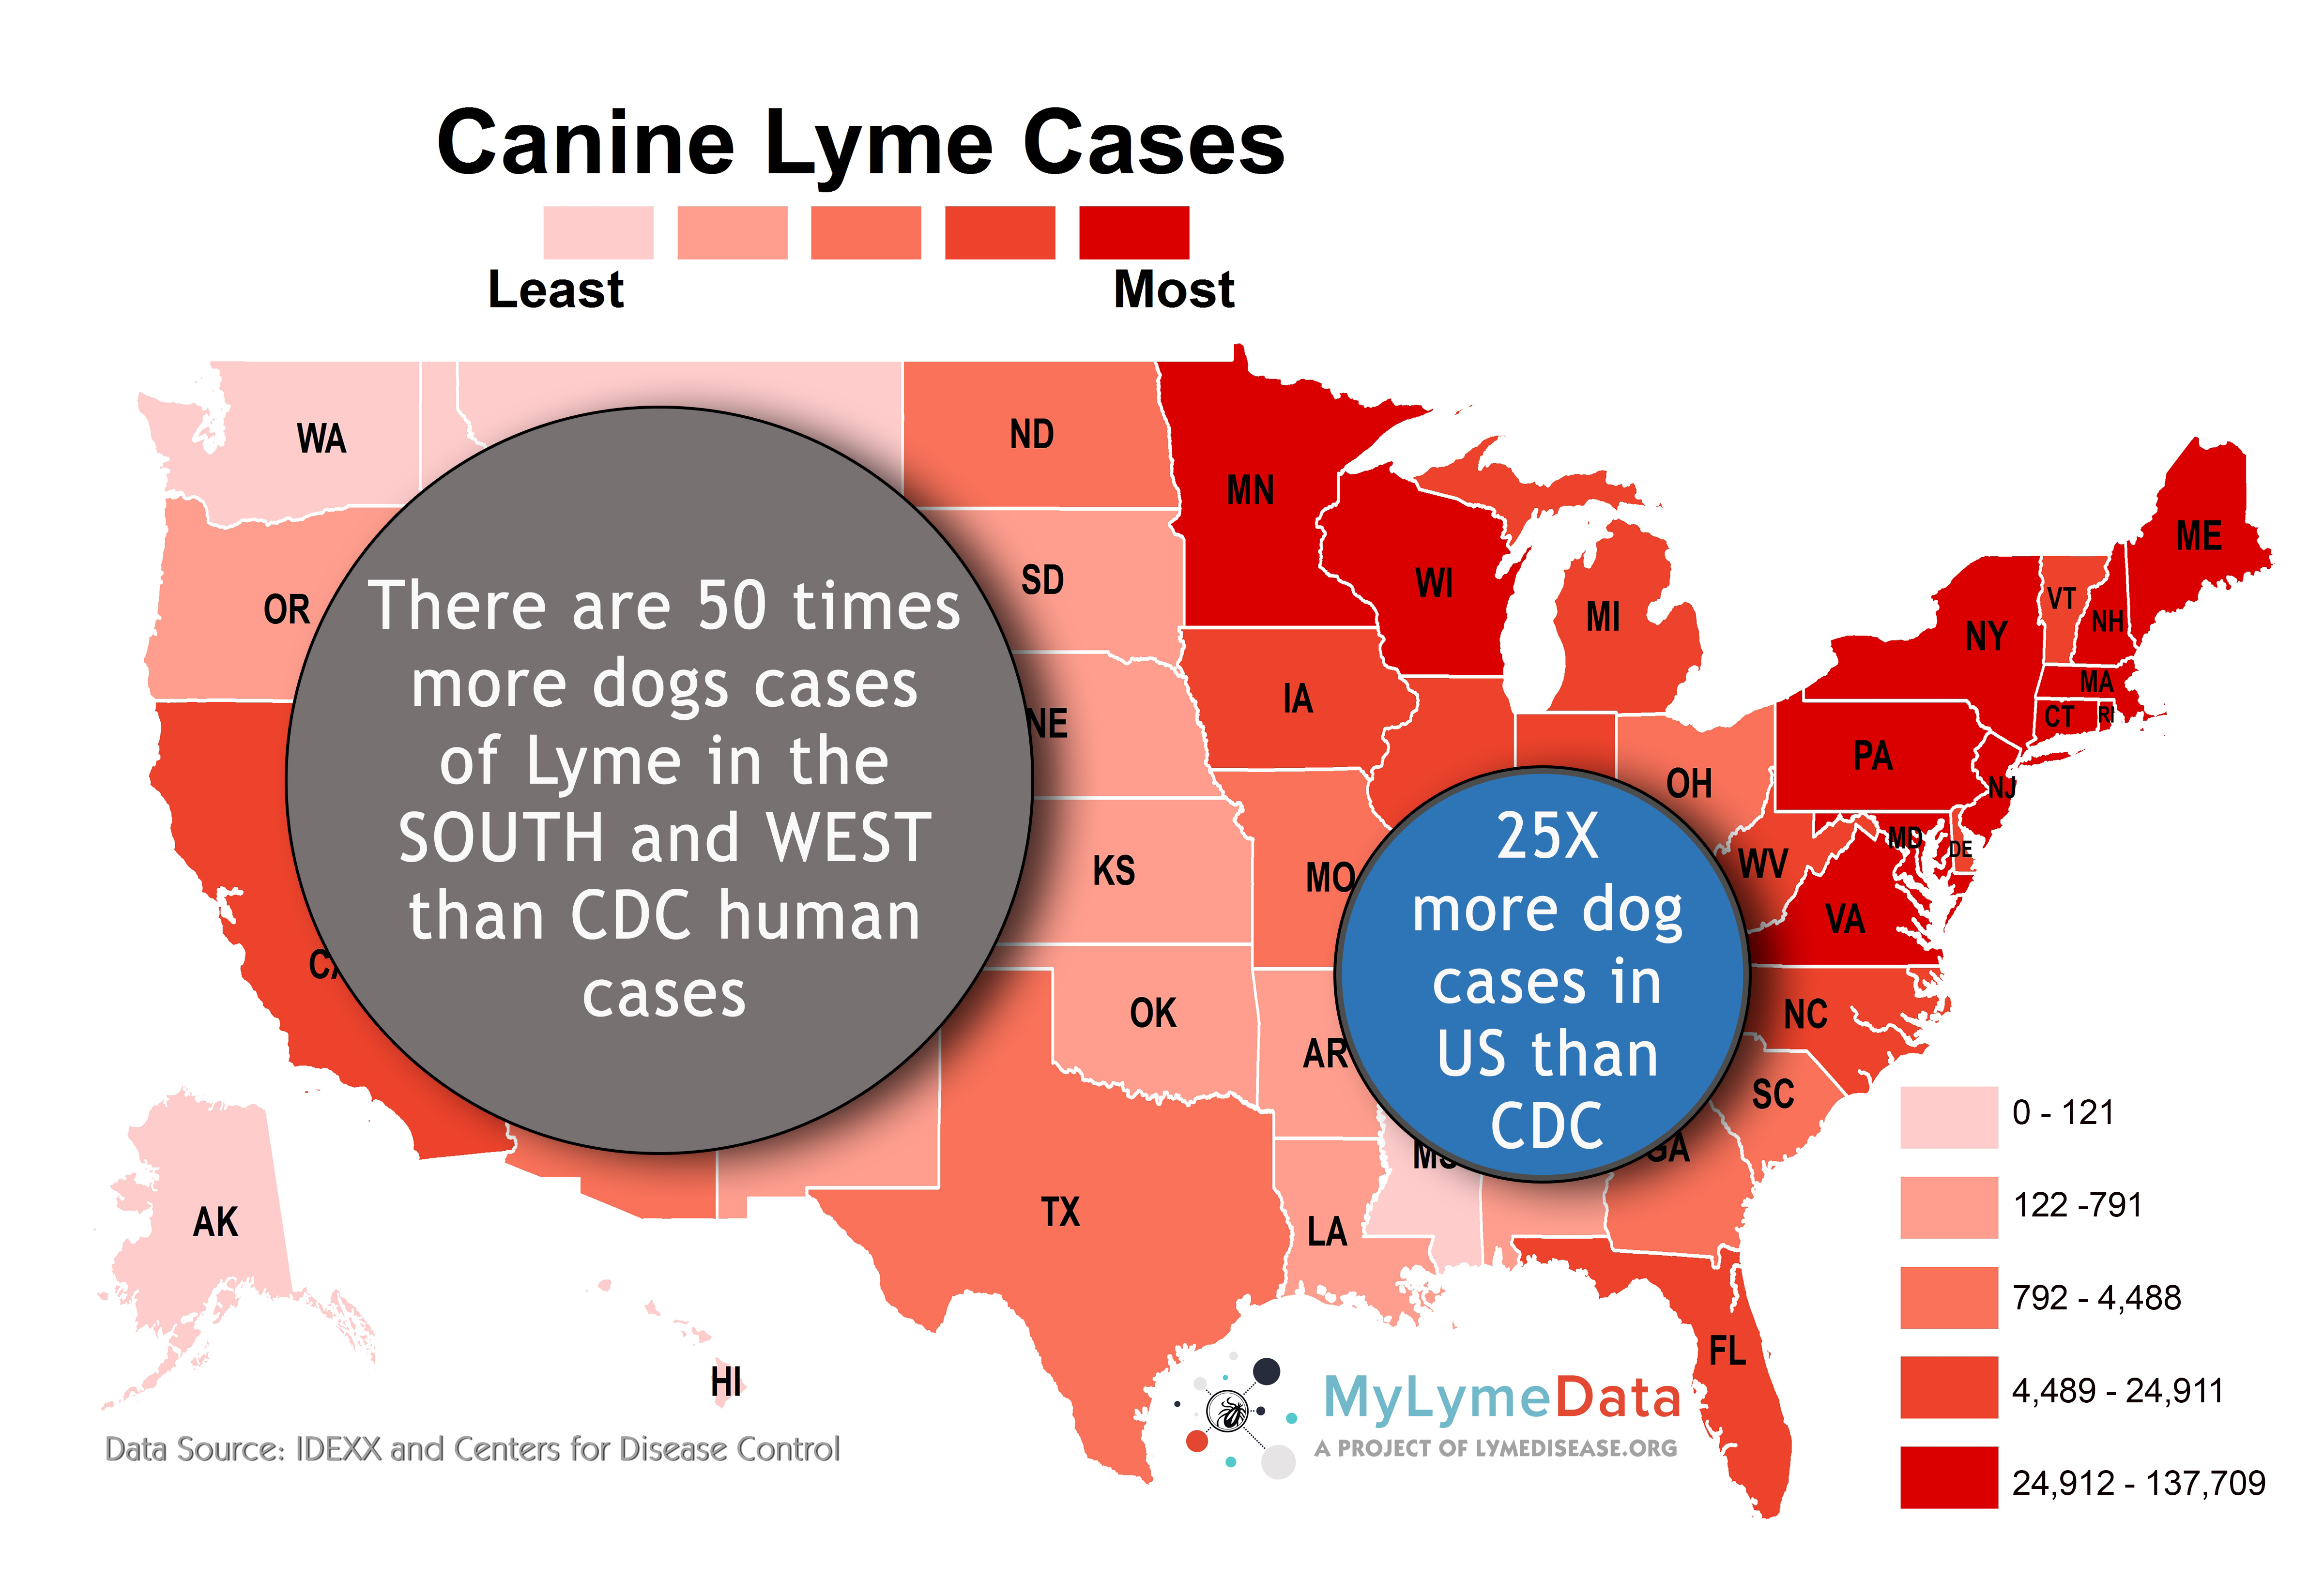
Between 2011 and 2015, IDEXX collected nearly 12 million Lyme disease test results from US veterinarians on a county-by-county basis. The data indicates that Lyme disease is present in abundance in every state in the US.
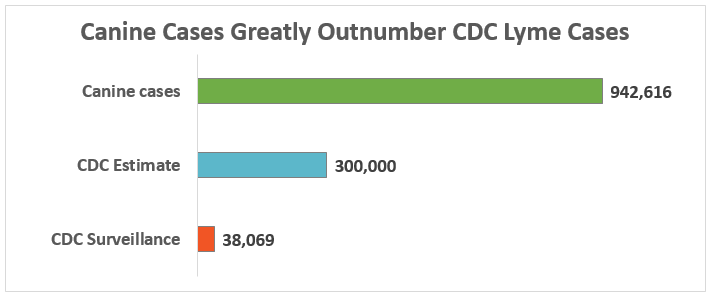
The number of canine positive test reports is vastly greater than the number of human cases reported by the Centers for Disease Control (CDC). There are close to one million canine positive test results annually in the US, compared to 38,069 cases included in CDC surveillance reports.
This means that there are roughly 25 times more canine cases than CDC surveillance cases. Even taking into account the fact that the CDC acknowledges that surveillance reports significantly underestimate the real incidence of Lyme disease by a factor of 10, the discrepancy is extraordinary. As the chart below reflects, canine cases are still more than three times the number of CDC estimated cases (300,000).
The discrepancy between CDC and canine cases is even more pronounced in the western and southern states. In the West and the South, there are 104,104 cases in dogs annually, compared to 2,342 CDC-reported cases. In other words, there are roughly 50 times more canine cases than CDC surveillance cases.
Michael Yabsley, a parasitologist at the University of Georgia, and Christopher McMahan, an assistant professor of mathematical sciences at Clemson University, have used the IDEXX canine data to develop a risk forecast map for the predicted Lyme disease prevalence — the percentage of dogs who are likely to test positive — by county in each of the 48 contiguous states. Yabsley explains the predictive relationship:
“Dogs really are the canary in the coal mine for human infection. Our research team has evidence that the relationship between canine disease and human disease is strong. Because dogs are being tested for exposure during annual exams, these data are available on a national scale, something that is difficult to get when studying the ticks and environment directly.”
Aside from indicating environmental exposure risk, the data illustrates that people who own pets need to be aware that they face the same exposure when walking their animals or when their animals return home from outdoors carrying ticks. Hence, preventative measures for pets—such as using appropriate tick and flea collars—are essential health matters for both people and their pets to avoid exposure.
LymeDisease.org believes that the IDEXX maps, which track Lyme disease as well as other tick-borne diseases such as ehrlichiosis and anaplasmosis, are the most accurate reflection of exposure. You can type in your zip code in the top right corner to assess your riskhere.
For example, in my zip code alone in Los Angeles, 626 cases of canine Lyme disease have been identified. (There are more than 3,500 zip codes in Los Angeles county.) That’s substantially more than the CDC reports for Californiaas a STATE for the last five years (2010-2015).
If you are interested in more information, check out the LymeSci blog on the predictive mapping of canine risk.
The LYME POLICY WONK blog is written by Lorraine Johnson, JD, MBA, who is the Chief Executive Officer of LymeDisease.org. You can contact her at lbjohnson@lymedisease.org. On Twitter, follow her @lymepolicywonk. If you have not signed up for our patient-centered big data project, MyLymeData, please register now.
**Comment**
Fantastic, informative article and so true. My dog got better treatment than we did. The tests for animals are much more accurate and veterinarians completely understand the seriousness of TBI’s (tick borne illness) unlike human doctors. Our vet had NO TROUBLE treating my dog for over a month even though HE HAD NO SYMPTOMS. Compare that attitude with the reality of multitudes of humans being continually turned away because of arbitrary reasons such as a lack of an EM rash, a map that demonstrating a lack of ticks or infected ticks on that geographical region, not enough time passed before accepted dogma of transmission, and so many other reasons.
Neil Spector, MD, knows a lot about cancer. He’s one of the country’s top oncologists and is a cancer researcher at Duke University School of Medicine. He knows a lot about Lyme disease, too—from personal experience.
Dr. Spector suffered from misdiagnosed Lyme disease for many years, and during that time, his heart was battered and beaten up by the unrecognized illness. Although he was eventually diagnosed and treated for Lyme, by then his heart was severely damaged.
Since then, Dr. Spector has become a unique advocate for Lyme patients. He thoroughly understands the patient’s viewpoint, including what it’s like to know that something is seriously wrong with your body and yet have doctors dismiss your symptoms.
At the same time, he is a man of science and understands that we need a new way of looking at Lyme disease diagnosis and treatment. (Same-old, same-old diagnostics and treatment with 60-year-old antibiotics? Lyme patients deserve better, he says.)
As a cancer researcher, he knows what great strides have been made in terms of “personalized medicine” for cancer treatment—and that a similar approach to Lyme disease offers great promise.
Earlier this year, Dr. Spector spoke at the Focus on Lymeconference in Scottsdale, AZ. He and conference organizers graciously allowed LymeDisease.org to videotape his presentation and share it with you here. Take a listen to his remarkable story.