https://www.lymedisease.org/touchedbylyme-fairhealth-wsj/

TOUCHED BY LYME: Say what? California fifth in nation for Lyme insurance claims?

The CDC’s official count of approximately 30,000 Lyme disease cases per year in the United States has been a constant source of exasperation to the Lyme community.

The agency acknowledged some years back that its “estimate” of cases is 10 times that—300,000+ annually. But an estimate is all it’s ever been. “Reported” cases have remained in the 30,000 range.

(“Reported” actually means: cases which meet CDC’s rigid surveillance criteria, leaving out tens of thousands of DIAGNOSED cases of Lyme disease because they don’t meet that high bar.)

Thus, for years, CDC has put out information saying that 95% of Lyme cases are located in just 14 states, sending the (inaccurate) message that the rest of the country is essentially Lyme-free. (See: Why doesn’t CDC count Lyme disease cases in the South and the West?  https://www.lymedisease.org/lymepolicywonk-cdc-count-lyme-cases-south/)

Now, the Wall Street Journal has published an eye-popping article that tells a different story.

Take a look at this chart, provided to the newspaper by FAIR Health, a nonprofit organization that manages the nation’s largest database of privately billed health insurance claims.

top-5-states-for-Lyme-495x622

According to this, in 2016, California had the FIFTH highest number of Lyme-related insurance claims in the nation! Here’s how the WSJ described it:

North Carolina reported 32 Lyme cases to the CDC in 2016 but in the same year made 88,539 health-care claims for a Lyme diagnosis. California reported 90 cases to the CDC but had 46,820 claims. Texas reported 31 cases to the CDC but had 31,129 claims. All three are considered low-incidence states.

It’s important to note that this data represents the number of “claim lines” reflecting services rendered to those with a Lyme diagnosis, not unique individuals with Lyme. This data captures every time a person with Lyme receives an insurance-covered service in connection with their Lyme diagnosis. So, if California’s case number of 90 was at all accurate, that would mean each patient saw their doctor or had another Lyme-related interaction 520 times that year. Highly doubtful!

We can’t know from this data how many individuals are involved. But for discussion sake, let’s say that each California Lyme patient represented here saw their doctor (or had other covered services) 10 times that year. That would translate into 4682 people. I suspect that number is closer to reality than the 90 case figure cited by state health officials and the CDC.

The FAIR Health numbers don’t account for those who are diagnosed and treated by Lyme-literate doctors—most of whom aren’t in the insurance system at all. Furthermore, how many people have Lyme but are misdiagnosed with something else? They are of course not reflected whatsoever.

As a Californian myself, I am extremely frustrated when the California Department of Public Health announces its pitifully low count of Lyme cases every year–which are then reflected on the CDC website.

I encourage you to read the entire Wall Street Journal article:  https://www.wsj.com/articles/lyme-disease-an-even-bigger-threat-than-you-think-1529672401

I hope this latest information will be included in the Tick-Borne Disease Working Group’s upcoming report to Congress. It’s one more example of how “off” the CDC Lyme statistics have been for years. The system is broken and needs to be fixed.

TOUCHED BY LYME is written by Dorothy Kupcha Leland, LymeDisease.org’s Vice-president and Director of Communications. She is co-author of When Your Child Has Lyme Disease: A Parent’s Survival Guide. Contact her at dleland@lymedisease.org .

______________

**Comment**

Fantastic article that shows the illogic that abounds regarding numbers of Lyme/MSIDs cases.  Please share this info with everyone you know.  Much must change!

https://klinghardtinstitute.com/wp-content/uploads/2018/05/IHCAN-Dr-K-article-HERV-05.1.pdf

The Role of Retroviruses in Chronic Illness- Dietrich Klinghardt, MD, PhD

The role of retroviruses in chronic illness is greatly disputed in academic circles. However, at the Sophia Health Institute Dr DIETRICH KLINGHARDT, MD, PhD, reports seeing significant improvement in treatment outcomes – in the most severely affected patients with chronic illness – when anti- retroviral strategies are included.

The results we are seeing at the Sophia Health Institute at our locations in Seattle and Marin County would not have been possible without the brilliant work of Judy Mikovits, PhD.

What is published and what illnesses are potentially caused by, or have as a contributing factor, activated retroviruses?

  • CNS-related illnesses: ME/CFS, Gulf War Syndrome, Autism, MS, Parkinson’s, ALS, Schizophrenia
  • Auto-immune diseases: Lupus, Crohn’s, Hashimoto’s Thyroiditis, Polymyositis, Sjogren’s syndrome, Bechet’s Disease, primary biliary cirrhosis
  • Cancer: prostate, breast, non-Hodgkin’s lymphoma, chronic lymphocytic leukaemia, mantle cell lymphoma, hairy cell leukaemia, bladder, colorectal, kidney, ovarian.

To that I am adding a list of other illnesses that have responded under my care to retroviral interventions: intractable Lyme disease, mold illness, insomnia, brain fog and all stages of a deteriorating brain, most childhood illnesses including ADHD and behavioural problems, asthma, breast cancer, lung cancer and many more.

Working backwards

What are retroviruses? The more familiar DNA viruses such as those from the “herpes family” – and many others – work their way from DNA over to RNA and from there to the manufacture of viral proteins. Retroviruses work their way backwards – from the RNA to the DNA – and then forward again from there.

Retroviruses are subdivided into different- lettered classes – Beta Retroviruses: HERV-K. Gamma Retroviruses: HERV-H and HERV-W.

The generally accepted key contributors to chronic illness are inflammation, oxidative stress and microbial infection. All of these are known triggers for retroviral activity, and in turn are also caused by retroviral activity.

Both human and animal retroviruses can infect the central nervous system (CNS). These are associated with many diseases of the CNS and cause neurological disease by several mechanisms:

1. Directly through infection of immune cells which traffic to the brain;

2. Indirectly through increases in proinflammatory cytokines and chemokines, or

3. In the absence of detectable brain inflammation indirect effects known as “bystander effects”- causing chronic retroviral replication of immune cells.

A retrovirus works via the enzyme “reverse transcriptase”. Once inside the cell, it uses the enzyme to force the cell to create viral DNA. This viral DNA becomes integrated into the host cell DNA. A retrovirus integrated into our genome may be passed from mother to child during pregnancy (Sakuma et al, 2012).

Only 2% of our DNA is protein-coding, but 6-8% of our DNA is retroviral DNA – passed down to us from our ancestors as scars from our constant encounter with an often hostile microbial and virus-rich environment (Stoyle, 2006, Mayer et al, 2011; Li et al, 2001). These viruses are referred to as Human Endogenous Retroviruses or HERVs.

However, not all embedded retroviral DNA is bad. Some sections have become a functional part of our genome because they have given us an evolutionary advantage, such as the formation of the p53 gene regulatory network (Shin et al, 2013; Barbusecu et al, 2001). Other retroviruses have to be silenced throughout life, mainly through DNA methylation and acetylation.

The transcription of retroviral DNA makes the infected person susceptible to numerous de-novo genetic mutations, including MTHFR, DNMT and other genes which control methylation. Many other illness-producing effects are known, implicating HERV-K in the pathogenesis of neuroinflammatory and autoimmune illnesses. For a patient to get well today, it is rarely enough to just interpret the genomic testing and to substitute accordingly.

Acquiring infection

How do we become infected? Retroviruses can be acquired (inhalation, blood-based products, physical contact) or the viruses already present in our DNA can be activated through influences such as a viral infection or chronic inflammation (Manghera and Douville, 2013).

For example, the Epstein Barr virus induces expression of the HERV-K envelope gene and the transactivation of MSRV, the Multiple Sclerosis retrovirus (Mameli et al, 2007; Sutkowski et al, 2001). Herpes simplex type-2 activates members of the HERV-W family. These and other mechanisms are likely responsible for the activation of HERVs seen in rheumatoid arthritis, SLE, Sjorgens disease, schizophrenia, autism, MS and cancer. Cell phone radiation has disabled many of our protective proteins (Fragopoulou et al, 2012) and so have many of the food-based toxins such as glyphosate (Seneff et al, 2017) and air-based inhalants (aluminium etc).  An unintended source of retroviruses are some vaccines as reported in Frontiers in Microbiology in January 2011).

Diagnosis

Currently PCR testing is only available to
the research community. We have to rely on indirect parameters:

  • decrease of CD56 NK cells (CD56 is involved in adhesion, migration, growth, differentiation and other cellular functions); down regulation of IL-13, IL-2, IFN gamma, TH-1 cytokines (J. Mikovits et al, 1998)
  • upregulated levels of TH-2 cytokines: IL-4, IL-10 and pro-inflammatory cytokines: IL-1, IL-6, IL-8 and TNF-alpha.
  • elevated levels of TGF beta-1: has profound effects on innate and adaptive immunity through stimulation of mast cells (often mistaken as mould-related). This may be the true cause of mastocytosis.

Other practical markers from my experience: low wbc (white blood count below 4500), low CD 56. I always include the CD 57 to rule out an active Borrelia burgdorferi infection as compounding factor.

Treatment

When the retroviruses are effectively addressed early in the treatment of chronic illness, other issues such as bacterial infections (Borrelia, Mycoplasma, Bartonella etc), mould illness, EBV, CMV, HHV-6, silent inflammation, parasites, heavy metal toxicity and many other problems become less symptomatic and often undetectable – and respond much better to treatment, even to interventions that have failed before.

Plants have been exposed to the same retroviruses as us, but for 300 million years longer – and many have developed potent adaptogens. Even though drugs like Truvada and AZT can be successfully used, I prefer the use of plant-based products that have unique anti-retroviral properties. A few examples with the key references:

  • Scutalaria root (Ruscetti et al: “Inhibition of HIV infection by baicalin – a flavonoid compound purified from Chinese herbal medicine”, Cellular & Molecular Biology Research 39, 2 (1993): 119-124).
  • Cistus incanus (Rebensburg et al: “Potent in vitro antiviral activity of Cistus incanus extract against HIV and Filoviruses targets viral envelope proteins”. Scientific Reports 6 (2016): 20394).
  • Broccoli sprouts (Furuya et al: “Sulforaphane inhibits HIV infection of macrophages through Nrf2.” PLoS Pathogens, 12.4 (2016): e1005581)
  • St John’s Wort (Meruelo, Lavie and Lavie: “Therapeutic agents with dramatic anti- retroviral activity and little toxicity at effective doses: aromatic polycyclic diones hypericin and pseudohypericin.” Proc Nal Acad Sci 85.14 (1988): 5230-5234).

In addition, I like to put my patients on a high dose of seleno-cysteine (commonly 800mcg, a dose that has been established as safe (Yang, G.; Zhou, R. (1994) “Further Observations on the Human Maximum Safe Dietary Selenium Intake in a Seleniferous Area of China”. Journal of Trace Elements and Electrolytes in Health and Disease. 8 (3–4): 159–165. Baum et al. “High risk of HIV- related mortality is associated with selenium deficiency.” JAIDS 15.5 (1997): 370-374).

Suramin, an old anti-parasitic, has turned out to be one of the most effective anti- retroviral agents. Retroviruses activate the “cell danger response” and the P2 purinergic receptor on each cell. Suramin downregulates this receptor and inhibits the binding of growth factors TGF-beta, EGF, PDGF to their receptors and thus antagonises the ability of these factors to stimulate growth of tumour cells. It can be given iv every six weeks.

I prefer giving daily homeopathic doses (Mitsuya et al: “Suramin protection of T cells in vitro against infectivity and cytopathic effect of HTLV-III.” Science 226.4671 (1984): 172-174).

When we use suitable liposomal extracts of plants in proper dose and frequency, together with selenium and “energetic copies” of immune modulators like suramin, olmetarsan (vitamin D receptor), rapamycin (mTOR), significant results can be achieved in the treatment of chronic illness that were not possible before. This new therapeutic approach should always be combined with the synergistic use of EMR protection, treatment of Lyme and co-infections, mould and metal detox.

• On June 10, Dr Klinghardt will present a one-day seminar on the correct and effective use of anti-retroviral interventions in chronic illness. For more information and to book see news story on page 9 and visit www. Klinghardtinstitute.com.

About the author

Dr DIETRICH KLINGHARDT studied medicine and psychology in Freiburg, Germany, completing his PhD on the involvement of the autonomic nervous system in autoimmune disorders. Early in his career he became interested in the sequelae of chronic toxicity (especially lead, mercury, environmental pollutants & electromagnetic fields) in the course of illness.

While working in India he encountered Eastern concepts of disease aetiology and blended them with his Western training. This laid the foundation for his 5-level system of Integrative Medicine. In the US he spent three years as a full-time emergency physician before becoming Medical Director of the Santa Fe Pain Centre.

Increasingly aware of the limitations of conventional medicine when dealing with chronic conditions, he trained in Ericksonian hypnotherapy and began to include body-oriented psychotherapeutic and counselling approaches in his work, along with neural therapy, mesotherapy injection techniques and applied psychoneurobiology. Dr Klinghardt has contributed significantly to the understanding of metal toxicity and its connection with chronic infections, illness and pain. He has been instrumental in advancing various fields within biological medicine – non-invasive pain management, injection techniques for pain and orthopaedic dysfunction, anti-ageing medicine, toxicology, paediatrics (neuro-developmental disorders), energy psychology, biological dentistry and others. He has also developed Autonomic Response Testing, a comprehensive diagnostic system that has helped many practitioners to become accomplished holistic physicians. He founded Sophia Health Institute in 2012, and is actively involved in patient care at his clinic.

______________

**Comment**

For more on Mikovitz’s work:  https://madisonarealymesupportgroup.com/2017/10/15/vaccines-and-retroviruses-a-whistleblower-reveals-what-the-government-is-hiding/

https://madisonarealymesupportgroup.com/2018/03/01/vaccines-could-contribute-to-disease-epidemics-due-to-retrovirus-contamination/

To hear the audio of the talk & slides, go here:  http://simplymimi.net/archives/1151


https://embed.ted.com/talks/lang/en/david_brenner_a_new_weapon_in_the_fight_against_superbugs”

Since the widespread use of antibiotics began in the 1940s, we’ve tried to develop new drugs faster than bacteria can evolve — but this strategy isn’t working. Drug-resistant bacteria known as superbugs killed nearly 700,000 people last year, and by 2050 that number could be 10 million — more than cancer kills each year. Can physics help? In a talk from the frontiers of science, radiation scientist David Brenner shares his work studying a potentially life-saving weapon: a wavelength of ultraviolet light known as far-UVC, which can kill superbugs safely, without penetrating our skin. Followed by a Q&A with TED Curator Chris Anderson.

This talk was presented at an official TED conference, and was featured by our editors on the home page.

https://www.ted.com/speakers/david_brenner?language=en


http://www.greenmedinfo.com/blog/corruption-evidence-based-medicine-killing-profit

The Corruption of Evidence Based Medicine — Killing for Profit

Tuesday, June 19th 2018
Written By: Dr. Jason Fung
This article is copyrighted by GreenMedInfo LLC, 2018

The idea of Evidence Based Medicine (EBM) is great. The reality, though, not so much. Human perception is often flawed, so the premise of EBM is to formally study medical treatments and there have certainly been some successes.

Consider the procedure of angioplasty. Doctors insert a catheter into the blood vessels of the heart and use a balloon like device to open up the artery and restore blood flow. In acute heart attacks studies confirm that this is an effective procedure. In chronic heart disease the COURAGE study and more recently the ORBITA study showed that angioplasty is largely useless. EBM helped distinguish the best use of an invasive procedure.

So, why do prominent physicians call EBM mostly useless? The 2 most prestigious journals of medicine in the world are The Lancet and The New England Journal of Medicine. Richard Horton, editor in chief of The Lancet said this in 2015 https://www.thelancet.com/journals/lancet/article/PIIS0140-6736%2815%2960696-1/fulltext

The case against science is straightforward: much of the scientific literature, perhaps half, may simply be untrue

Dr. Marcia Angell, former editor in chief of NEJM wrote in 2009 that http://www.nybooks.com/articles/2009/01/15/drug-companies-doctorsa-story-of-corruption/

It is simply no longer possible to believe much of the clinical research that is published, or to rely on the judgment of trusted physicians or authoritative medical guidelines. I take no pleasure in this conclusion, which I reached slowly and reluctantly over my two decades as an editor

This has huge implications. Evidence based medicine is completely worthless if the evidence base is false or corrupted. It’s like building a wooden house knowing the wood is termite infested. What caused this sorry state of affairs? Well, Dr. Relman another former editor in chief of the NEJM said this in 2002  https://www.ncbi.nlm.nih.gov/pubmed/12561803

The medical profession is being bought by the pharmaceutical industry, not only in terms of the practice of medicine, but also in terms of teaching and research. The academic institutions of this country are allowing themselves to be the paid agents of the pharmaceutical industry. I think it’s disgraceful

The people in charge of the system — the editors of the most important medical journals in the world, gradually learn over a few decades that their life’s work is being slowly and steadily corrupted. Physicians and universities have allowed themselves to be bribed.

The examples in medicine are everywhere. Research is almost always paid for by pharmaceutical companies. But studies done by industry are well known to have positive results far more frequently https://www.ncbi.nlm.nih.gov/pubmed/20679560.  Trials run by industry are 70% more likely than government funded trials to show a positive result. Think about that for a second. If EBM says that 2+2 = 5 is correct 70% of the time, would you trust this sort of ‘science’?

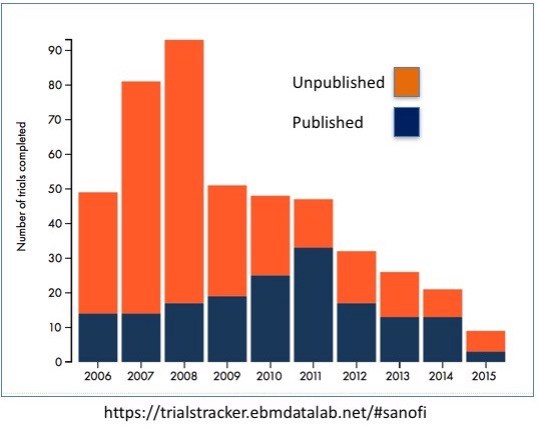
Selective Publication — Negative trials (those that show no benefit for the drugs) are likely to be suppressed. For example, in the case of antidepressants, 36/37 https://www.nejm.org/doi/full/10.1056/NEJMsa065779 studies that were favourable to drugs were published. But of the studies not favorable to drugs, a paltry 3/36 were published. Selective publication of positive (for the drug company) results means that a review of the literature would suggest that 94% of studies favor drugs where in truth, only 51% were actually positive. Suppose you know that your stockbroker publishes all his winning trades, but suppresses all his losing trades. Would you trust him with your money? But yet, we trust EBM with our lives, even though the same thing is happening.
KillingForProfitGraph

Let’s look at the following graph of the number of trials completed versus those that were published. In 2008, the company Sanofi completed 92 studies but only a piddly 14 were published. Who gets to decide which gets published and which does not? Right. Sanofi. Which ones do you think will be published? The ones that favor its drugs, or the ones that prove their drugs do not work? Right. Keep in mind that this is the only rational course of action for Sanofi, or any other company to pursue. It’s idiotic to publish data that harms yourself. It’s financial suicide. So this sort of rational behavior will happen now, and it will not stop in the future. But knowing this, why do we still believe the evidence based medicine, when the evidence base is completely biased? An outside observer, only looking at all published data, will conclude that the drugs are far, far more effective than they are in reality. Yet, if you point this out in academic circles, people label you a quack, who does not ‘believe the evidence’.
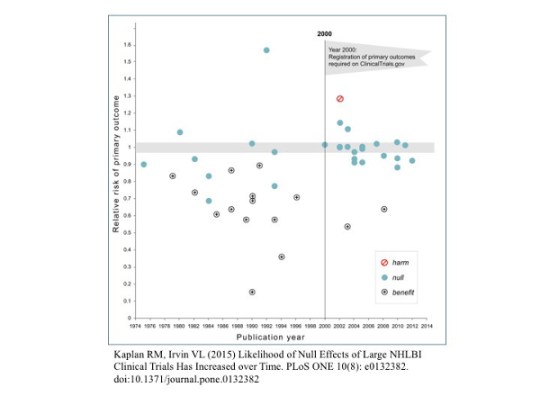
KillingForProfitGraph2Rigging of Outcomes — Or consider the example of registration of primary outcomes. Prior to year 2000, companies doing trials did not need to declare what end points they measured. So they measure many different endpoints and simply figured out which one looked best and then declared the trial a success. Kind of like tossing a coin, looking at which one come up more, and saying that they were backing the winning side. If you measured enough outcomes, something was bound to come up positive.

In 2000, the government moved to stop these shenanigans. They required companies to register what they were measuring ahead of time. Prior to 2000, 57% of trials showed a positive result. After 2000, a paltry 8% showed good results. More evidence of the evidence base being completely corrupted by commercial interest, and the academic physicians who were getting rich on it tacitly allowing corruption because they know that you don’t bite the hand that feeds you

KillingForProfitExcerpt

‘Advertorials’ — Or this example of a review paper in the NEJM https://www.nejm.org/doi/pdf/10.1056/NEJMoa1001086 that fracture rates caused by the lucrative bisphosphonate drugs were “very rare”. Not only did the drug companies pay lots of consulting fees to the doctors, three of the authors of this review were full time employees! To allow an advertorial to be published as the best scientific fact is scandalous. Doctors, trusting the NEJM to publish quality, unbiased advice have no idea that this review article is pure advertising. Yet, we still consider the NEJM to be the very pinnacle of evidence based medicine. Instead, as all the editors of the journals sadly recognize, it has become lucre-based publishing. Mo money = better results.

Money from Reprints — The reasons for this problem is obvious to all  https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2964337/ — it’s insanely profitable for journals to take money from Big Pharma. Journals want to be read. So they all try to get a high Impact Factor (IF). To do this, you need to get cited by other authors. And nothing boosts ratings like a blockbuster produced by Big Pharma. They have the contacts and the sales force to make any study a landmark. A less obvious benefit is the fees that are generated by Big Pharma purchasing articles for reprint. If a company publishes an article in the NEJM, they may order several hundred thousand copies of the article to be distributed to unsuspecting doctors everywhere. These fees are not trivial. The NEJM publisher Massachusetts Medical Society gets 23% of its income from reprints. The Lancet — 41%. The American Medical Association — a gut busting 53%. No wonder these journals are ready to sell their readers (ordinary physicians) down the river. It pays. Who needs journalistic ethics when there’s a Mercedes in the driveway? Mo money, baby. Mo money.

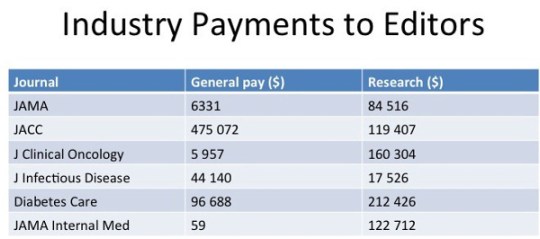
Bribery of Journal Editors — A recent study by Liu et al in the BMJ https://www.bmj.com/content/359/bmj.j4619 shed more light on the problem of crooked journals. Crooked journal editors. Editors play a crucial role in determining the scientific dialogue by deciding which manuscripts are published. They determine who the peer reviewers are. Using the Open Payments database, they looked at how much money the editors of the most influential journals in the world were taking from industry sources. This includes ‘research’ payments, which are largely unregulated. As mention previously, much ‘research’ consists of going to meetings in exotic locale. It funny how many conferences are held in beautiful European cities like Barcelona, and how few are done in brutally cold Quebec City.

Of all journal editors that could be assessed, 50.6% were on the take. The average payment in 2014 was $27,564. Each. This does not include an average $37, 330 given for ‘research’ payments. Other particularly corrupt journals include:
KillingForProfitPayToEditors

This is slightly horrifying. Each editor of the Journal of the American College of Cardiology received, on average $475 072 personally and another $119 407 for ‘research’. With 35 editors, that’s about $15 million in bribes to doctors. No wonder the JACC loves drugs and devices. It pays the private school bills. Mo money = we’ll publish your crooked studies for you. Mo money, baby, mo money.

Publication Bias — The evidence base that EBM depends upon is completely biased. Some people think I’m really anti-Pharma, but this is not really true. Big Pharma companies have a duty to their shareholders to make money. They have no duty to patients. On the other hand, doctors have a duty to patients. Universities have a duty to remain unbiased.

It is the failure of doctors and universities to keep their greedy paws out of the corrupting influence of Big Pharma money that is the problem. If Big Pharma is allowed to spend lots of $$$ paying off doctors and universities and professors, then it should do so to maximize profits. That is their mission statement. Doctors love to blame Big Pharma companies because it takes peoples gaze off the real problem — lots of doctors taking $$$ from anybody who will pay. The pharma industry is not the problem. Bribery of university doctors is the problem — one that is easily fixed if the political will exists.

Consider this study:  https://onlinelibrary.wiley.com/doi/pdf/10.1111/ene.13336  Looking at studies in the field of neurodegenerative disease, researchers looked at all the studies that were started but never finished or never published. Approximately 28% of studies never made it to the finish line. That’s a problem. If all the studies that don’t look promising for drug candidates are not published, then it appears that the drugs are way way more effective than they really are. But the published ‘evidence base’ would falsely support the drug. Indeed, Pharma sponsored trials were 5 times more likely to be unpublished.

Imagine you have a coin flipping contest. Suppose a player call ‘Big Pharma” chooses heads, and also pays the coin flipper. Every time the coin flipper pulls up tails, the results don’t count. Every time it comes up heads, it counts. This happens 28% of the time. Now, instead of a 50/50 split of heads and tails, it’s more like a 66/34 split of heads/tails. So the ‘evidence based medicine’ lover claims that heads is far more likely to come up than tails, and castigates people who don’t believe the results as ‘anti-science’.

Evidence based medicine depends entirely upon having a reliable base of evidence (studies). If the evidence base is tampered with, and paid for, then EBM as a science is completely useless. Indeed, the very editors whose entire careers have been EBM have now discovered it to be worthless. Does the CEO of Phillip Morris (maker of Marlboro cigarettes http://www.greenmedinfo.com/disease/tobacco-toxicity) smoke? That tells you all you need to know about the health risks. Do the editors of the NEJM and the Lancet believe EBM anymore? Not at all. So neither should we. We can’t believe evidence based medicine until the evidence has been cleaned up from the corrupting influence of commercial interests.

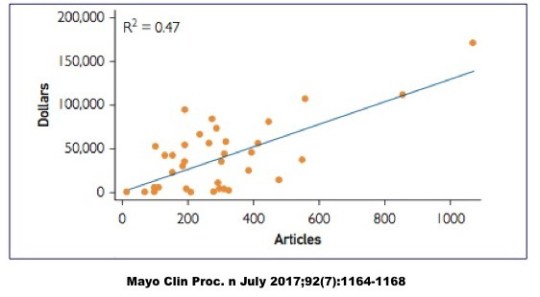
Financial conflicts of interest (COI), also known as gifts to doctors, is a well accepted practice. A national survey in the New England Journal of Medicine in 2007 https://www.nejm.org/doi/pdf/10.1056/NEJMsa064508 shows that 94% of physicians had ties to the pharmaceutical industry. This gravy train only rides in one direction. From Big Pharma to the wallets of doctors. Sure Big Pharma can simply pay doctors directly, and it does plenty of that. It’s no surprise that medical students with more exposure to pharmaceutical reps develop a more positive attitude towards them https://www.ncbi.nlm.nih.gov/pubmed/20672554. Many medical schools have limited exposure of medical students in response, but declined to get off the gravy train themselves. There is a simple relationship between how prominent a physician is (more articles published — almost always academic doctors and professors) and how much money they take from Big Pharma. Mo prominent = mo money. Further, there is a ‘clear and strong link’ between taking industry money and minimizing the risk of side effects of medications https://www.ncbi.nlm.nih.gov/pubmed/20299696.  What, you thought people teach at prestigious institutions like universities for the good of mankind? Maybe that’s why they went there, but that’s not why they stay. They came for the science. They stayed for the money.
KillingForProfitGraph3

So here’s a damning list of all the problems of EBM

  1. Selective Publication
  2. Rigged outcomes
  3. Advertorials
  4. Reprint Revenues
  5. Bribery of Journal Editors
  6. Publication Bias
  7. Financial Conflicts of Interests

When the evidence base of medicine is bought and paid for, people die. That is how doctors have created this opioid crisis that kills thousands of people. Pharmaceutical companies want to pay off doctors, just as drug lord want to pay off judges and police officers. Doctors, being human, should put safeguards against this temptation. Unfortunately, doctors and universities have been willing participants in this game of killing for profit https://www.facebook.com/NathanGillOfficial/videos/2134121280141545/.   We need to end it now. End the corruption of the universities. Stop the bribery of doctors.

Dr. Aseem Malhotra will be speaking about this very issue to the European Parliament this Thursday:  https://www.dietdoctor.com/live-stream-big-food-big-pharma-killing-profit

Nephrologist. Special interest in type 2 diabetes reversal and intermittent fasting. Founder of Intensive Dietary Management Program.

Disclaimer: This article is not intended to provide medical advice, diagnosis or treatment. Views expressed here do not necessarily reflect those of GreenMedInfo or its staff.

“© [Article Date] GreenMedInfo LLC. This work is reproduced and distributed with the permission of GreenMedInfo LLC. Want to learn more from GreenMedInfo? Sign up for the newsletter here http://www.greenmedinfo.com/greenmed/newsletter.”

______________

**Comment**

I am so thankful people are speaking out about what’s happening to Science.  This is being seen across the board, but particularly with tick borne illness.  This complex illness has been riddled with fraud, collusion, and conflicts of interest from the get-go and hasn’t changed in over 40 years.

For more:  https://madisonarealymesupportgroup.com/2017/01/13/lyme-science-owned-by-good-ol-boys/

https://madisonarealymesupportgroup.com/2018/06/14/corruption-human-rights-violations-against-lyme-doctors-scientists-and-parents-now-on-united-nations-record/

https://madisonarealymesupportgroup.com/2017/08/19/dr-liegner-guidelines-used-by-managed-care-causing-lyme-deaths/

https://madisonarealymesupportgroup.com/2017/01/02/fake-science/

https://madisonarealymesupportgroup.com/2017/09/25/trump-should-eliminate-fake-science/

https://madisonarealymesupportgroup.com/2017/01/28/sit-down-science/

https://madisonarealymesupportgroup.com/2017/12/05/bought-documentary-on-pharma-vaccines-gmos/


https://www.nysenate.gov/newsroom/press-releases/senate-approves-1-million-investment-combat-lyme-across-new-york-state

Senate Approves $1 Million Investment to Combat Lyme Across New York State

June 19, 2018 ISSUE: LYME AND TICK-BORNE DISEASES

Historic Levels of Funding Build Upon the Senate’s Commitment to Increasing Public Awareness, Treatment, and Prevention of Lyme and Other Tick-Borne Illnesses
The New York State Senate today approved a resolution to provide a record $1 million to help fight the scourge of Lyme and other tick-borne diseases (TBDs) throughout the state. The new funding will help support a wide variety of local investments identified by the Senate’s Task Force on Lyme and Tick-Borne Diseases to increase education, research, prevention, and treatment options, and combat the ongoing increase in TBDs throughout New York.

The Senate Majority – and specifically the Task Force – led the charge in securing this historic level of funding in the 2018-19 state budget. Based on the Task Force’s recommendations, the final budget restores $400,000 in Executive Budget cuts and includes $600,000 in new funding for a total of $1 million.

Senator Sue Serino, Chair of the Task Force on Lyme and Tick-Borne Diseases, said,

“With the State Senate successfully securing an unprecedented $1 million in this year’s budget to bolster awareness, prevention and research initiatives, we are sending a strong message to New Yorkers who have spent years grappling with the devastating impacts of Lyme and tick-borne diseases. This critical funding will play a direct role in helping us to combat the spread of Lyme and TBDs in the state, and with the Hudson Valley sitting at the epicenter of this epidemic, I am especially proud to have secured funding that will go directly to our local community. I thank Senator Kemp Hannon, Chair of the Senate’s Health Committee, who has partnered with me to continue building momentum on this important issue. Working together with partners at all levels, we can ensure that New York has an effective statewide action plan in place to empower patients and better protect residents against the scourge of Lyme and TBDs.”

Senator Kenneth P. LaValle (R-C-I, Port Jefferson) said,

“I am pleased that the Senate was able to secure $1 million for Lyme and Tick Borne Disease (TBD) funding. My colleagues and I fought hard to secure this funding, recognizing the importance of fighting the spread of Lyme and TBD’s throughout the state. My district is particularly hard hit, especially on the East End of Long Island. This money will allow for the continuation of the highly successful Tick Borne Disease Center at Southampton Hospital, a four poster program on Shelter Island directly targeting the spread of ticks from the deer population, and the creation of a new state-of-the-art infectious disease lab at Stony Brook University.”

Senator Betty Little (R-C-I, Queensbury) said,

“I represent a beautiful region of New York State and we want people outdoors, enjoying nature. But the fear of contracting Lyme Disease is increasingly a deterrent and that’s a shame. My experience is that the statistics of reported cases fall short of what is actually happening. A mere mention of Lyme disease among a group of people and you immediately hear horror stories of misdiagnosis and costly long-term treatments. The good news is we are making progress and the Senate task force is playing a major role. We’ve secured funding and spearheaded legislation. We have taken our direction from the public we serve, from those leading the effort to improve diagnosis and treatment and from the incredible insight of patients themselves. This additional funding will make an impact in the North Country and I am very grateful to have helped secure it as part of this year’s budget.”

Highlights of the resolution passed today include:
  • Cary Institute of Ecosystem Studies, Inc. – $192,000 to research community-based prevention methods by continuing and expanding “The Tick Project,” a five-year research project. The funding will help determine whether neighborhood-based prevention can reduce human cases of Lyme and other TBDs.
  • Stony Brook University – $175,000 to open a state-of-the art infectious disease laboratory, which will have an insectary dedicated solely for work on ticks. The laboratory will be open to Stony Brook scientists and others as a regional facility with unique research capabilities. The funds will be used to support activities in the laboratory and new research on TBDs.
  • Cornell University – $130,000 to study the distribution of ticks and the diseases they carry in various parts of the state through the Tick Outreach and Surveillance Project for New York. Run through the New York State Integrated Pest Management (IPM) Program at Cornell University, the research will primarily focus on the spread of ticks by species within certain counties. Other areas of study include ways to reduce human exposure to TBDs, tick management workshops, and best practices in schools, camps, parks, and places where people gather outdoors.
  • New York State Association of County Health Officials (NYSACHO) – $112,000 to increase public awareness throughout New York through eight to 10 regional educational lectures. The informational seminars will focus on community awareness, best practices for TBD investigation, tick surveillance, and disease prevention to local parts of the state heavily impacted by the effects of Lyme and TBDs.
  • SUNY Adirondack – $100,000 for laboratory research on lesser-known TBDs, including infectious diseases known to be comorbid with Lyme disease, such as Babesia, Bartonella, Ehrlichia, Anaplasma, and Powassen virus. The work would help provide much needed information about the rates of these coinfections in people with Lyme disease in New York.
  • Southampton Hospital – $75,000 to fund the Tick-Borne Disease Resource Center, which helps doctors in multiple disciplines collaborate with researchers and community outreach experts to inform and treat individuals from across the region.
  • New York State Department of Health – $60,000 to increase the number of tick collection sites in New York, and the number of ticks tested for pathogens statewide. The funding will also be used to hire temporary staff to assist with sampling and testing, as well as targeting of educational messages in a more efficient manner.
  • SUNY College of Environmental Science and Forestry – $50,000 to monitor seasonal variations of ticks in Western and Central New York to help provide a better understanding of how disease transmission risks are changing. The study will also provide public information to better explain the risks of tick exposure.
  • Paul Smith’s College – $30,000 to study the emergence of TBDs in the North Country by continuing and expanding academic studies that monitor ticks and TBDs.
  • Cornell Cooperative Extension – $26,000 for a series of regional Lyme and TBD forums to be hosted throughout the state. The forums will help provide the public with information on tick identification, tick bite prevention, Lyme disease and co-infection awareness, impact on pets and livestock, and health resources that are available for individuals who have been bitten by a tick.
  • New York State Department of Health – $25,000 to continue database mining, which would include various projects associated with Lyme carditis, as well as deaths associated with Lyme and other TBDs.
  • Town of Shelter Island – $25,000 to help combat the spread of ticks on Shelter Island, which is one of the worst hit areas of the public health crisis. The town has developed a four-poster program to stem the spread of ticks associated with the deer population. The town has built and installed four-poster stations, to remove ticks from deer across the Island, and this funding would maintain and expand the efforts of this critical initiative.

In addition to the $1 million announced today, the Senate was instrumental earlier this year in passing apackage of bills aimed at combating Lyme and TBDs, based on the recommendations of the Senate’s Task Force on Lyme and Tick-Borne Diseases.

________________

Also see:  https://madisonarealymesupportgroup.com/2018/06/20/ny-governor-cuomo-announces-public-private-research-collaboration-to-advance-diagnosis-and-treatment-of-tick-borne-diseases/