Marna Ericson, PhD, Assistant Professor, University of Minnesota
Monica Embers, PhD, Associate Professor, Tulane University
Edward Breitschwerdt, DVM
Melanie S. Steele Professor of Medicine and Infectious Diseases, North Carolina State University College of Veterinary Medicine
Robert Mozayeni, MD, Translational Medicine Group
Neil Spector, MD (posthumously), Associate Professor Medicine, Duke University Medical Center
Why is Bartonella important to consider as a differential diagnosis? What should patients and the public know about prevention, diagnosis and treatment? What does the latest science tell us about Bartonella? How does it interact with Lyme and other tick-borne diseases? What should patients/public know about prevention, diagnosis and treatment?
Hosted by “Icahn School of Medicine at Mount Sinai proudly supported by the Steven & Alexandra Cohen Foundation: Cohen Lyme & Tickborne Disease Initiative”
Effect of Dapsone alone and in combination with intracellular antibiotics against the resistant morphological forms of Borrelia burgdorferi, Richard Horowitz, MD
Also see:https://www.mdpi.com/2079-6382/9/11/725 Case study of 3 patients with relapsing and remitting Lyme disease as well as a retrospective chart review of 37 additional patients undergoing DDD CT therapy (40 patients in total) was also performed, which demonstrated tick-borne symptom improvements in 98% of patients, with 45% remaining in remission for 1 year or longer.
Melatonin has been shown to play a role in viral infections and research suggests it may be an important adjunct to COVID-19 treatment
Data analysis by Cleveland Clinic found patients who used supplemental melatonin had a 28% lower risk of testing positive for COVID-19. Blacks who used melatonin were 52% less likely to test positive for the virus
Melatonin attenuates several pathological features of COVID-19, including excessive inflammation and oxidation, exaggerated immune response resulting in a cytokine storm, acute lung injury and acute respiratory distress syndrome
A case series reports patients given 36 mg to 72 mg of intravenous melatonin per day as an adjunct therapy to standard of care improved within four to five days; all survived
Texas urgent care clinics using high-dose melatonin in combination with vitamin C and vitamin D say they’ve successfully treated hundreds of COVID-19 patients.Melatonin enhances vitamin D signaling and the two work synergistically to enhance your mitochondrial function
Melatonin is a hormone synthesized in your pineal gland and many other organs.1 While it is most well-known as a natural sleep regulator, it also has many other important functions.2 For example, melatonin:
Is a potent antioxidant3 with the rare ability to enter your mitochondria,4 where it helps “prevent mitochondrial impairment, energy failure and apoptosis of mitochondria damaged by oxidation.”5 It also helps recharge glutathione,6 and glutathione deficiency has been linked to COVID-19 severity
May prevent or improve autoimmune diseases, including Type 1 diabetes10
Is an important energy hormone that can influence your energy level11
Helps regulate gene expression via a series of enzymes12
Has anticonvulsant and antiexcitotoxic properties13
Melatonin Also Has Important Role in COVID-19 Treatment
Melatonin has also been shown to play a role in viral infections14 and according to a June 2020 research paper15,16,17 in Life Sciences journal, it may be an important adjunct to COVID-19 treatment. According to the authors, melatonin attenuates several pathological features of COVID-19, including:18
Excessive oxidative stress and inflammation
Exaggerated immune response resulting in a cytokine storm
Acute lung injury
Acute respiratory distress syndrome
They point out that melatonin is also “effective in critical care patients by reducing vessel permeability, anxiety, sedation use, and improving sleeping quality, which might also be beneficial for better clinical outcomes.”19
The scientific review paper,20 “Melatonin Potentials Against Viral Infections Including COVID-19: Current Evidence and New Findings,” published October 2020 in Virus Research journal, also summarizes the many potential mechanisms by which melatonin can protect against and ameliorate viral infections.
The authors review research looking at melatonin’s beneficial effects against a variety of viruses, including respiratory syncytial virus, Venezuelan equine encephalitis virus, viral hepatitis, viral myocarditis, Ebola, West Nile virus and dengue virus. Based on these collective findings, they believe melatonin may offer similar protection against SARS-CoV-2.
Melatonin Reduces Risk of Positive COVID-19 Test
Data21,22 from Cleveland Clinic also supports the use of melatonin. Here, the researchers analyzed patient data from the Cleveland Clinic’s COVID-19 registry using an artificial intelligence platform designed to identify drugs that may be repurposed.23,24
By identifying clinical manifestations and pathologies shared by COVID-19 and 64 other diseases, they were able to conclude that certain proteins associated with chronic diseases are highly connected with SARS-CoV-2 proteins. Put another way, a number of proteins appear to play a key role in the pathologies seen both in COVID-19 and other chronic diseases. For example:25
“Analyses of single-cell RNA sequencing data show that co-expression of ACE2 and TMPRSS2 is elevated in absorptive enterocytes from the inflamed ileal tissues of Crohn disease patients compared to uninflamed tissues, revealing shared pathobiology between COVID-19 and inflammatory bowel disease.
Integrative analyses of metabolomics and transcriptomics (bulk and single-cell) data from asthma patients indicate that COVID-19 shares an intermediate inflammatory molecular profile with asthma (including IRAK3 and ADRB2).”
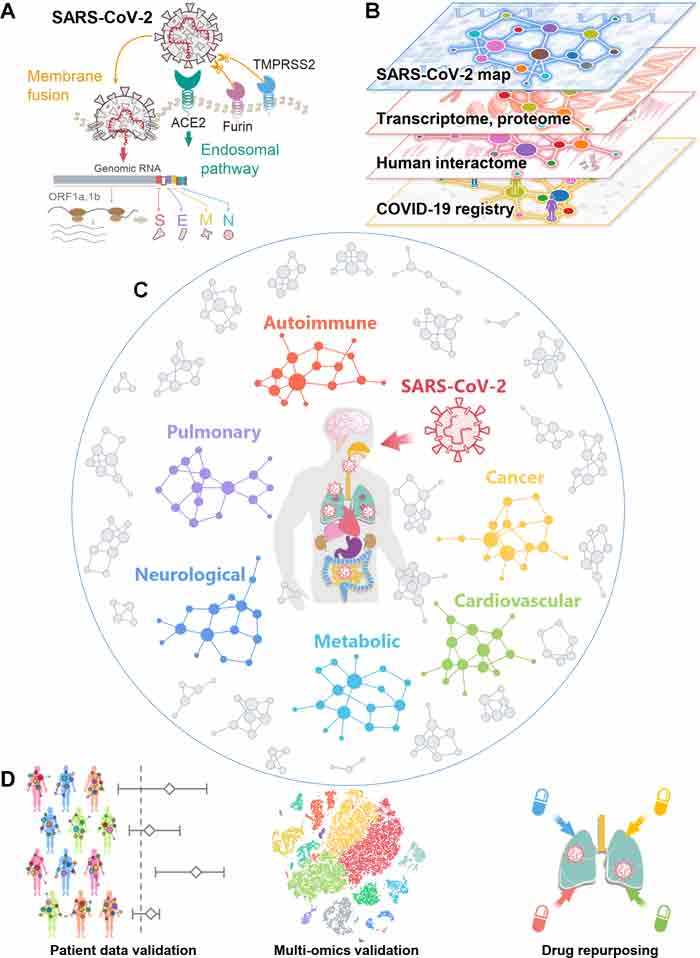
The diagram below illustrates (among other things) the basic pathogenesis of SARS-CoV-2 (figure A) and the network of disease manifestations associated with the infection (figure C).
These connections suggest that drugs already in use for a chronic disease may be repurposed and used in the treatment of COVID-19, as it acts on one or more shared biological targets. Melatonin stood out in this regard. Patients who used melatonin as a supplement had, on average, a 28% lower risk of testing positive for SARS-CoV-2. Blacks who used melatonin were 52% less likely to test positive for the virus.
Confounding variables adjusted for in the calculations included age, sex, race, smoking history and several known comorbidities. The authors point out that while the findings look promising, large observational studies and randomized controlled trials are still needed to validate the clinical benefits of melatonin.
Two key data points missing from the analysis are the dosage used and the length of supplementation. These data were not included in the patient registry, so we don’t know how much melatonin is required to lower your risk of SARS-CoV-2 infection to the degree found in this study.
High-Dose Melatonin Successfully Treats COVID-19
It’s possible that higher doses than those used for sleep may be needed, at least when treating an active infection. A recent case series26published in the journal Melatonin Research details how high-dose intravenous melatonin can benefit patients with COVID-19 pneumonia.
Here, patients were given 36 mg to 72 mg per day in four divided doses as an adjunct therapy to standard of care. Most supplements contain between 0.5 mg and 5 mg, and when used for sleep, you’d typically start with the lowest dose and work your way up as needed.
All of the patients given melatonin improved within four to five days, and all survived. On average, those given melatonin were discharged from the hospital after 7.3 days, compared to 13 days for those who did not get melatonin.
This is far better than the expensive treatment Remdesivir, which costs over $3,000 and doesn’t produce anywhere near this improvement.
Other Doctors Are Also Using Melatonin Against COVID-19
Dr. Richard Neel and colleagues at Little Alsace and Uvalde Urgent Care clinics in Texas also report using high-dose melatonin in combination with vitamin C and vitamin D, and had as of the last week of July 2020 successfully treated more than 400 patients.27
As reviewed in a section below, melatonin enhances vitamin D signaling and the two work synergistically to enhance your mitochondrial function. Melatonin and vitamin C are both also involved with ACE2, the receptor that SARS-CoV-2 uses to gain entry into the cell.
Together, melatonin and vitamin C help reduce SARS-CoV-2 virulence by inhibiting NLRP3 inflammasomes, which in turn inhibits cytokine storms. The Front Line COVID-19 Critical Care Working Group (FLCCC)28 also lists melatonin as an optional addition to their MATH+ protocolfor COVID-19.
How Melatonin Combats COVID-19
Research suggests melatonin may have the ability to combat COVID-19 via several different mechanisms. For example, it’s been shown to regulate immune responses and prevent cytokine storms.29 As explained by the authors of one such study,30 when your immune cells are in a hyper-inflammatory state, their metabolism changes in a way similar to that of cancer cells:
“Similar to cancer cells … immune cells such as macrophages/monocytes under inflammatory conditions abandon mitochondrial oxidative phosphorylation for ATP production in favor of cytosolic aerobic glycolysis (also known as the Warburg effect) …
The change to aerobic glycolysis allows immune cells to become highly phagocytic, accelerate ATP production, intensify their oxidative burst and to provide the abundant metabolic precursors required for enhanced cellular proliferation and increased synthesis and release of cytokines …
Because of melatonin’s potent antioxidant and anti-inflammatory activities, it would normally reduce the highly proinflammatory cytokine storm and neutralize the generated free radicals thereby preserving cellular integrity and preventing lung damage.”
Cytokine storm is one of the reasons why sepsis (blood poisoning) is so lethal, and studies have confirmed melatonin has a favorable influence on sepsis. (Sepsis is also a feature of severe COVID-19.) As reported in a 2010 study in the Journal of Critical Care:31
“Melatonin is an effective anti-inflammatory agent … Its anti-inflammatory action has been attributed to inhibition of nitric oxide synthase with consequent reduction of peroxynitrite formation, to the stimulation of various antioxidant enzymes thus contributing to enhance the antioxidant defense, and to protective effects on mitochondrial function and in preventing apoptosis.
In a number of animal models of septic shock, as well as in patients with septic disease, melatonin reportedly exerts beneficial effects to arrest cellular damage and multiorgan failure …
Apart from action on the local sites of inflammation, melatonin also exerts its beneficial actions through a multifactorial pathway including its effects as immunomodulatory, antioxidant and antiapoptotic agent.”
More recently, a 2019 animal study32 in the journal Frontiers in Immunology discusses how melatonin can protect against polymicrobial sepsis — i.e., sepsis caused by more than one microbial organism — which has a twofold higher lethality than unimicrobial sepsis (sepsis caused by a single microbe).33
In this case, melatonin appears to offer protection by having an antibacterial effect on white blood cells called neutrophils. A high neutrophil count is an indicator for infection. Melatonin may also combat SARS-CoV-2 infection by:34
Suppressing oxidative stress35
Regulating blood pressure (a risk factor for severe COVID-19)
Improving metabolic defects associated with diabetes and insulin resistance (risk factors for severe COVID-19) via inhibition of the renin-angiotensin system (RAS)
Protecting mesenchymal stem cells (MSCs, which have been shown to ameliorate severe SARS-CoV-2 infection) against injuries and improving their biological activities
Promoting both cell-mediated and humoral immunity
Promoting synthesis of progenitor cells for macrophages and granulocytes, natural killer (NK) cells and T-helper cells, specifically CD4+ cells
Inhibiting NLRP3 inflammasomes36
General Guidance for Supplementation
As mentioned, it’s very difficult to make dosage recommendations based on the limited evidence currently at hand, but since Cleveland Clinic looked at the supplements patients reported using, it seems reasonable to assume they were using it as you typically would. Most melatonin supplements contain between 0.5 mg and 5 mg.
In the case report mentioned earlier, patients were given 36 mg to 72 mg of melatonin intravenously per day, which would likely be excessive for prophylactic use. That said, research37 has found no adverse effects for dosages ranging from 20 mg up to 100 mg.
Whatever dose you take, and I recommend starting low, at 1 mg or less, be sure to take melatonin at night, before bed. Rising melatonin levels is the reason you feel sleepy in the evening, so it’s ill advised to take it in the morning or during the day, when your natural level is (and should be) low. If you happen to wake up in the middle of the night, especially if you’re exposed to a light source, you could also take some then, to help you go back to sleep.
Melatonin is also best taken sublingually, either in the form of a spray or sublingual tablet. Sublingually, it can enter your blood stream directly and doesn’t have to go through the digestive tract. As a result, its effect will be felt more rapidly.
Melatonin and Vitamin D Are a Winning Combo
Another supplement of crucial importance in the age of COVID-19 is vitamin D. Interestingly, melatonin enhances vitamin D signaling, and optimizing your vitamin D may be one of the most beneficial steps you can take to lower all of the risks associated with COVID-19, from reducing your risk of testing positive to lowering your risk of severe infection and death.
To learn more about this, download my free vitamin D report from StopCovidCold.com. Together, melatonin and vitamin D synergistically act to optimize your mitochondrial function. In fact, your mitochondria are the final common target for both.38
A deficiency in either vitamin D or melatonin has been associated with the pathogenesis of several chronic diseases, including high blood pressure, cardiovascular disease, metabolic syndrome and diabetes, just to name a few.39
These conditions have also emerged as comorbidities that significantly raise your risk of death from COVID-19. Synthesis of both vitamin D and melatonin is also dramatically reduced with advancing age, and old age is a primary risk factor for COVID-19 death. So, while vitamin D3 and melatonin supplementation may be beneficial for most people, it’s particularly important for the elderly.
Support Your Body’s Production of Melatonin and Vitamin D
Keep in mind, however, that it makes little sense to take a supplement unless you’re also seeking to optimize your body’s natural production. In the case of melatonin, this includes making sure you get good sleep on a regular basis.
You also need a good dose of natural sunlight around midday to synchronize your circadian clock so that your body produces melatonin at the appropriate time (i.e., in late evening). As the evening wears on and the sun sets, you’ll want to avoid bright and all blue lighting, as blue light inhibits melatonin synthesis. Blue lighting is predominant in LED and fluorescent bulbs that are “cool white.”
Sun exposure, of course, is also the ideal way to optimize your vitamin D. I recommend getting sensible sun exposure on large portions of your body on a regular basis, ideally daily. For further guidance, see “The Risks and Benefits of Sun Exposure.”
If for whatever reason you cannot get sufficient amounts of sun exposure, consider taking a vitamin D3 supplement (along with a little extra vitamin K2 to maintain a healthy ratio between these two nutrients).
I personally have not taken any oral vitamin D for well over 10 years and my levels are typically over 60 ng/mL, even in the winter. I have, however, started taking sublingual melatonin a few years ago as I am now in my mid-60s, even though I sleep in pitch dark and get bright sun exposure during the day.
Despite these COVID-19 treatments, our government has done all in its power to malign them. Their only answer is an experimental, fast-tracked vaccine that has caused serious adverse reactions.
A total of 71 patients with Lyme disease were identified for analysis in whom treatment with disulfiram was initiated between 15 March 2017 and 15 March 2020. Four patients were lost to follow-up, leaving 67 evaluable patients. Our retrospective review found patients to fall into a:
“high-dose” group (≥4 mg/kg/day)
“low-dose” group (<4 mg/kg/day)
62 of 67 (92.5%) patients treated with disulfiram were able to endorse a net benefit of the treatment with regard to their symptoms.
12 of 33 (36.4%) patients who completed one or two courses of “high-dose” therapy enjoyed an “enduring remission”, defined as remaining clinically well for ≥6 months without further anti-infective treatment.
The most common adverse reactions from disulfiram treatment in the high-dose group were fatigue (66.7%), psychiatric symptoms (48.5%), peripheral neuropathy (27.3%), and mild to moderate elevation of liver enzymes (15.2%).
We observed that although patients on high dose experienced a higher risk for adverse reactions than those on a low dose, high-dose patients were significantly more likely to achieve enduring remission. View Full-Text
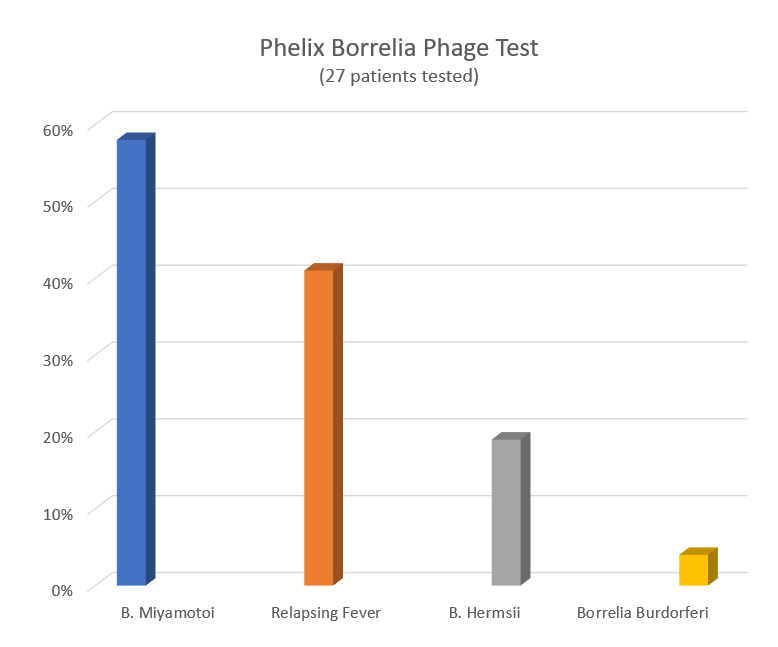
New, more sensitive, and precise testing reveals a troubling finding in the treatment of Lyme disease. As this study reveals, many doctors may often be prescribing the incorrect antibiotics, due to the narrow focus on B. burgdorferi. In twenty-seven people from sixteen states, 96% were found to have other Borrelia strains than B. burgdorferi, many of which cannot be treated with the same antibiotics.
Limitations of Conventional Lyme Testing
Treatment-resistant, chronic and apparent relapsing Lyme disease (borreliosis), with its oft associated co-infections which worsen the illness, though once debated, is now well-documented in the scientific literature. Chronic Lyme disease has reached the true status of a global pandemic, though largely unappreciated by the media and mainstream medicine.
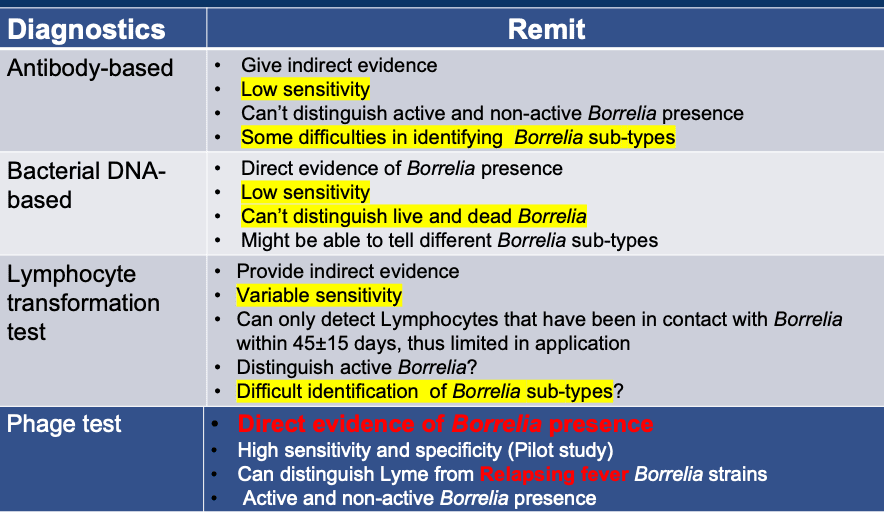
Conventional iagnostic lab testing, such as Western Blot, ELISA, and Conventional Bacteria PCR testing for the dectectin of Borrelia spirochete of Lyme disease has had limited success. Most types of conventional tests having high false-negative results, with as little as 30% sensitivity, meaning as much as 70% of people tested, actually have the infection, but never get treatment due to their lab test coming back negative. These people fall between the cracks of medicine as their body and lives fall apart as doctors do not know what is wrong with them, assuming the tests were correct. (See Fig. 1)
Fig. 1
The painful reality is that conventional labs which are not focused solely on testing for Lyme disease, often are not as diligent in their testing, not getting paid more to find the bacteria or not, and seeming to forget that there is a real and desperate person at the other end of the blood test. Unfortunately beyond this, the medico-political environment regarding the existence of chronic Lyme disease also gets in the way of getting many, if not most conventional physicians to order the test, even at the pleading of their patients.
New Testing Pinpoints Acute and Chronic Infections
In 2019 a new, highly sensitive test (See Fig. 1 Phage Test) was developed by the University of Leicester, in England, and performed by the R.E.D Laboratory, for the diagnosis of Borrelia infections. This test is so sensitive and the testing process so rigorous, that the test is nearing 100% accurate, at >80% sensitivity to detecting not just the presence of Borrelia burgdorferi, but all of the 20 types of Borrelia that can cause tick-borne and vector-borne illness. This test is call the Phelix Borrelia-Phage Test, and is such a breath of fresh air in that the test results come back not with encrypted, hard to determine bands, as in Lyme Western Blot tests, but instead clearly state, Positive or Negative and the exact type of Borrelia infection or multiple types of Borrelia strains that you have, without needing your doctor to interpret the results. Doctors in the United States or any other country can order this test.
Testing from Many Regions and States in the U.S.
The world is a much smaller place than many appreciate. It is commonly, although mistakenly thought that some of the twenty Borrelia bacteria strains are only in Europe, or only in Asia, or only in certain regions of the U.S. As this study demonstrates, only one person had B. burgdorferi in the group of 27 people in this study.
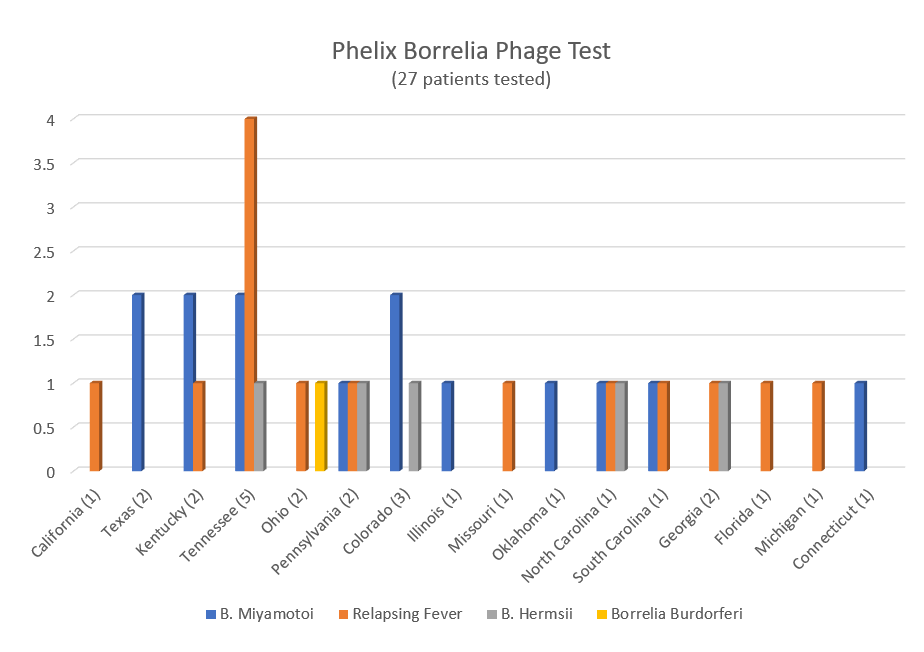
Armed with the newest and most sensitive Borrelia test, we undertook a retrospective study of 27 people from 16 different states (see Fig. 2) to achieve a wide view of what types of Borrelia infections people actually had in the different parts of the country. The results were unexpected, as the graphs and figures in this article demonstrate. The pre-study expectation was that people with chronic Lyme disease, especially in the U.S., would be infected with Borrelia burgdorferi.
Fig. 2
Results of 27 People with Positive Borrelia-Phage Tests
As seen in Fig. 3 below, many people had one or multiple strains of Borrelia. The vast majority, 52% (14 people) had Borrelia miyamotoi, followed by 42% (11 people) having Borrelia strains that fall under the category of Relapsing Fever group. Relapsing Fever group is illness from one or more of the following strains of Borrelia, B. hermsii, B. recurrentis, B. crocidurae, B. duttonii. After the Relapsing Fever group, 19% (5 people) had Borrelia hermsii, and only one person in the group had B. burgdorferi.
Fig. 3
Conclusion
The implications of this review are that Borrelia burgdorferi is likely not the primary culprit in many cases of chronic Lyme disease in the United States, as was previously thought. The other huge takeaway from this study is that many if not most people are not receiving the correct treatment, since the antibiotics typically used for B. burgdorferi are not the same as those used for other strains of Borrelia.
The specific strain of Borrelia bacteria cannot reliably be determined using bands on a Western Blot test. Any lab test that is focusing only upon B. burgdorferi, will miss the true diagnosis of other strains of Borrelia.
The Phelix Borrelia-Phage test is just one of a new breed of phage-based lab tests that will likely become the gold-standard of all bacterial testing. It would be advisable for anyone who suspects that they have or had Lyme disease, yet have either been told they are negative, or who have lingering symptoms to be tested again with the Phelix test.
Our view of what symptoms are typical of classic Lyme disease, based upon the B. burgdorferi model, needs to be expanded to include the symptoms that are unique to the other strains of Borrelia, as their presentation can be quite different, as well as their vectors not being always a tick.
Phage-based Testing and Now Phage-based, Strain-Specific Treatment
Treatments for B. burgdorferi, should be expanded to include the actual type or multiple types of Borrelia actually infecting a person. Although antibiotics, which can be likened to carpet-bombing, killing many bad bacteria, the Borrelia always causes the bad bacteria to mutate. This means the all types of bacteria lose some of their aspects that make it vulnerable to the antibiotics, not to mention the fact that antibiotics are notorious damaging to irreparably upset the populations of the friendly flora (microbiome) of the body, and cause prolonged and severe suffering through Jarische-Herxheimer reactions (Herx). A new Borrelia-phage-based targeted treatment has been developed that has been documented by repeated Phelix Borrelia-Phage testing, to rapidly eliminate only the types of Borrelia a person has been found positive, with no harm to the body, with minimal Herx reactions, and no harm to good bacteria.
Ruling out False-Positives and False-Negatives with Phelix Borrelia-Phage Testing
The Phelix Borrelia-Phage test is the premier, newest, most sensitive Borrelia lab test available. The Phelix test is statistically the most accurate test, as each blood sample undergoes quadruplicate real-time PCR tests for 3 different targets (B. burgdorferi sl, B. miyamotoi, Relapsing fever) for a total of 12 assessments. All positive-like samples are submitted to confirmatory sequencing to rule out false positive results. Before the Phage real-time PCRs, each sample is submitted to 2 rounds of QC to rule out false-negative results that would relate to the technical flaws: (i) to assess the quality of extracted DNA by performing low cycles actin PCR, and (ii) to assess the absence of PCR inhibitors by doing a real-time PCR for IAC (internal amplification control).
Ongoing Development of INPT at the Biologix Center
INPT was developed by Phagen Corp. and is being used at the Biologix Center for Optimum Health, as a part of an IRB study, to go beyond Borrelia and target any microbial issue, including all of the co-infections associated with Lyme disease, as well as Candida sp., mold, and parasite infections, however at this time the only lab test for detecting bacteria-specific phages is for Borrelia strains.
The future of INPT includes intravenous and injectable forms of application, in addition to the oral medication, through doctors only. INPT is not projected to be sold directly to the public at this time.
A more detailed report of these findings are presently being edited for publication in peer-reviewed article submission.
Bartonella Research Collaboration
The Biologix Center is collaborating with researchers who are working to develop phage lab tests for Bartonella and other types of microbes. The Phelix Bartonella-Phage Test is hoped to be offered before the end of 2020. If you have been diagnosed with Bartonella and would like to contribute a blood sample for the development of this new test, please let us know. Offer available only to patients of the Biologix Center who have been pre-qualified by our testing.
*INPT is a patent-pending innovation developed by Phagen Corp, and is being researched at the Biologix Center for Optimum Health, in Franklin, Tennessee. A patient-funded, Retrospective Registry IRB is in place to publish peer-reviewed articles as this clinical work progresses. Approximately 98% of funds go to support the ongoing research.
There are no financial or academic conflicts to be reported between Biologix Center for Optimum Health and RED Laboratories.
Testing on over 2,000 humans (mainly late stage/chronic patients) showed 30% negative results and 70% positive, among which over 60% indicated the presence of specific Borrelia miyamotoi phages.
It appears Borrelia Miyamotoi is far more prevalent than thought, and is yet another example of something our public ‘authorities’ have labeled ‘rare’ that isn’t.