Archive for the ‘Lyme’ Category

Officers of GLA & A Woman Incapacitated By Lyme Criticize An Article Depicting The Disease As Easy To Treat

https://globallymealliance.org/news/the-new-york-times-dont-minimize-health-risks-of-lyme-disease/

new york times lyme

The New York Times Opinion: Letters to the Editor
July 9, 2019

OFFICERS OF THE GLOBAL LYME ALLIANCE AND A WOMAN INCAPACITATED BY LYME CRITICIZE AN ARTICLE DEPICTING THE DISEASE AS EASY TO TREAT.

To the Editor:

Re “My Son Got Lyme Disease. He’s Totally Fine” (Well, nytimes.com, June 27):

Apoorva Mandavilli celebrates her son’s recovery from Lyme disease. But while the vast majority of those diagnosed with Lyme and other tick-borne diseases are cured with antibiotics, up to 20 percent of more than 427,000 newly diagnosed Americans go on each year to suffer devastating long-term chronic effects — even if they are treated early, like her son.

These patients can become afflicted with neurocognitive disorders, disabling fatigue, extreme joint pain, heart problems and so on. Sadly, with their lives severely disrupted if not destroyed, too many commit suicide. A recent study published by the journal BMC Public Health predicts the number of people suffering post-treatment Lyme could increase to almost two million by 2020.

Rather than minimizing the risks of Lyme disease by stating it is easy to diagnose and easy to cure — which is not the case — and lulling the public into a false sense of security, let’s pull together to address the great public health risk that irrefutably exists.


Babesiosis Could Be More Common in Sweden Than Previously Thought

https://www.ncbi.nlm.nih.gov/pubmed/31265116/

2019 Jun 28;116. pii: FL4D.

Babesiosis could be more common in Sweden than previously thought

[Article in Swedish]

Abstract

Babesia is a malaria-like, intraerythrocytic parasite with more than 100 different species. It is a zoonosis and some of the species are transmitted to humans by ticks and also as a possible transfusion-transmitted infection. In Sweden the disease has been well known in veterinary medicine for a long time, but only a few but severe cases have been published in humans during the last decades. Common symptoms from human Babesia infections (babesiosis) are fever, chills and myalgia and they vary from subclinical to potentially fatal among those with risk factors such as immunosuppression and splenectomy. In the U.S. more than 2,000 cases of babesiosis are found yearly and it is one of the most frequent fatal infections following blood transfusion. A study from southern Sweden has recently revealed a seroprevalence of 16% of Babesia antibodies among Borrelia-infected persons. These results indicate that there is a need to broaden awareness of Babesia in Sweden.

_________________

**Comment**

This abstract underplays the prevalence of Babesia. Not sure why they state it is a possible transfusion-transmitted infection when the Red Cross recently came out with a test to screen Babesia for blood.  It’s an obvious problem:

https://madisonarealymesupportgroup.com/2019/07/11/characteristics-of-transfusion-transmitted-babesia-microti-american-red-cross-2010-2017/

Here’s an even earlier article going transfusion-transmission:  https://madisonarealymesupportgroup.com/2016/12/15/blood-screening-for-babesia/  of those confirmed to be positive, 20% were PCR-positive, with 13% antibody-negative.

Here we have babies contracting it from blood:  https://madisonarealymesupportgroup.com/2017/09/27/premature-infants-develop-babesia-via-blood-transfusion

Here we have people contracting Babesia from transfusions, even in non-endemic areas.  https://madisonarealymesupportgroup.com/2017/08/08/transfusion-transmitted-babesiosis-in-nonendemic-areas/   Excerpt:

“Asymptomatic individuals with Babesia infection are able to donate blood in the United States because of the lack of specific blood donation testing. Blood products collected in Babesia-endemic areas are distributed nationally; thus, clinicians in nonendemic states may fail to include babesiosis in the differential diagnosis of a patient who had a recent transfusion history and a fever of unknown origin.”  

In the abstract, those with Lyme also had a seroprevalence of 16% of Babesia antibodies. In this study,  https://madisonarealymesupportgroup.com/2016/11/19/seroprevalence-of-babesia-in-individuals-with-ld/  it was nearly 29%. To me this demonstrates those with Lyme are at risk for Babesia and other pathogens.

To date, little work has been done on concurrent infections, and has been underplayed for decades.

The most important, recent work demonstrating multiple pathogen involvement:  https://madisonarealymesupportgroup.com/2018/10/30/study-shows-lyme-msids-patients-infected-with-many-pathogens-and-explains-why-we-are-so-sick/  This shows Lyme patients are at risk for not only other tick borne illnesses but opportunistic infections as well.  This is what we experience and see in the real world of Lymeland.

I don’t think mainstream medicine has a clue how important concurrent infection is.

http://www.nejm.org/doi/full/10.1056/NEJM199807163390304  When left untreated, silent babesial infection may persist for months or even years. Although treatment with clindamycin and quinine reduces the duration of parasitemia, infection may still persist and recrudesce and side effects are common. Improved treatments are needed.

Dr. Krause published in the New England Journal of Medicine that when a patient has Lyme and Babesia, Lyme is found three-times more frequently in the blood, proving Babesia suppresses the immune system.  http://danielcameronmd.com/babesia-and-lyme-its-worse-than-you-think/

https://madisonarealymesupportgroup.com/2017/06/28/concurrent-babesiosis-and-lyme-in-patient/   Dr. Horowitz warns that due to this immune suppression,patients with Rheumatoid Arthritis or Lupus and are on immunosuppressant drugs, if they have Babesia, could get much worse. The strain, B. divergens, causes a higher mortality rate and more severe symptoms, and if left untreated, this strain can develop into shock-like symptoms with pulmonary edema and renal failure.

More on Babesia:  https://madisonarealymesupportgroup.com/2016/01/16/babesia-treatment/  Dr. Horowitz, a nationally recognized LLMD, states Babesia is one of the most tenacious coinfections he sees in his patients and that treatment often takes 9 months to a year, particularly with those also infected with Lyme disease (borrelia).  Treatment options for you to discuss with your practitioner in this link.  


Lyme Q & A With Dr. Ross Tonight at 5 PM CST

https://events.genndi.com/register/169105139238438973/9629589511 Register here


af38f50e-505c-46d0-9e89-43a15953ea5b


Register in link for three events in July

Join Marty Ross MD on Thursdays for a 1.5 hour Lyme disease Q&A webinar. He answers any questions you may have about Lyme.
​​​​​​

Next event starts in…

  • Thursday, 11 July 2019, at 5:00 PM CST
  • Thursday, 18 July 2019, at 6:00 PM CST
  • Thursday, 25 July 2019, at 6:00 PM CST

__________________

**Comment**

Make sure you note the times listed. A mistake was made so for tonight (July 11) it will be at 5PM CST, with future times being at 6PM CST.

This is a great opportunity to ask all your questions and get feedback from an experienced practitioner.

Dr. Ross’ Youtube Channel, where you can listen to previous webinars: https://www.youtube.com/channel/UC2rR9VdwTEuXvrJ5tt7j6yw

Lyme, Alzheimer’s, Enbrel – New Potential Treatment

http://lymemd.blogspot.com/2019/06/lyme-alzheimers-enbrel-new-potential.html

Thursday, June 6, 2019

By Dr. Jaller

Lyme, Alzheimer’s, Enbrel — New Potential Treatment

iu

I have learned that most people want a simple sound bite answer or conclusion. The edges of medicine always operate in the grey and nuanced.

It has long been dogma in Lyme circles that immune suppressing drugs, e.g. Enbrel are very dangerous and should not be used.  The same is true with prednisone.

I have patients who get the occasional injection by their rheumatologist; joint pain gets better and they are no worse for the wear.

The drug is used for psoriasis amongst other many other conditions. The drug has serious side effects: its use should not be taken lightly.

A study suppressed by Pfizer, brought to light by the Washington Post, was based on insurance company data considering outcomes of  hundreds of thousands of patients and found those taking Enbrel had a 64% decrease in the incidence of Alzheimer’s disease. 

Enbrel impairs the function of TNF alpha, a master cytokine responsible for trafficking immune cells.

Pfizer did not make the disclosure because: a generic version will be  available.  A shiny new, me-too drug promoted heavily by pharm reps costing obscene amounts of money will take its place. Doctors will be given shiny data, along with lunch, proving equivalency? with the old drug.

The myth that generics are poor (dangerous) and lack quality control may be resurrected.

Watch out for first year generic prices: cute trick. For the first year a single company is given a monopoly and only required to reduce the price by 20%.  “See, the generic is almost as cheap as the brand,” the rep will inform a doctor. This is a bad pro big-pharma rule passed by Congress decades ago I’m sure) by the way. Cheap is a relative term.

The pharmaceutical giant, Pizer has excuses, reasons why it withheld the data, for example, they  claimed the data is wrong because of biological plausibility: the molecule is too large to cross the blood brain barrier.

Really? I care if the molecule gets into the brain; maybe it’s an advantage.  The brain has its own immune system which needs to be tweaked lightly. Ask anyone who has had a brain Herxheimer reaction knows. The Cytokine storm which may make you crazy results from peripheral cytokine reactions/overproduction primarily.  And there is no data the molecule cannot get into the brain. Cytokines get in the brain.

Alzheimer’s is in part motivated by inflammation. Other major factors are: production of amyloid beta protein (AB) (plaques and tangles), genetic factors and multiple external factors.

It is thought that AB protein is a naturally occurring antibiotic which responds to inflammation. Discussed elsewhere. Lyme resides in the brain along with many  bacteria, viruses, protozoans. It is true that spirochetes have been reported to aid in the transportation of AB into the brain.  Infection (or colonization) may be omnipresent and therefore not the whole story — or the most critical piece.

The vast majority of my patients present with cognitive complaints. Many or most Lyme patients, at one time or another fit the criteria for a disorder call MCI, minimal cognitive impairment. The mainstream medical community considers this a pre-Alzheimer’s condition, often.

What’s a Lyme patient to do?

First off, if symptoms completely resolve with usual therapy do nothing.

If you are a patient who has had very aggressive therapy, e.g. months of IV antibiotics and cognitive symptoms persist, look up MCI and consider the following:

Get an AB PET. The tests measures metabolic activity in the brain and the presence of early AB protein deposition. IF the test is positive you are at very high risk for developing Alzheimer’s.

Prednisone and Enbrel have largely been seen as dangerous because patients are misdiagnosed and not also treated for Lyme. Enbrel is likely tolerably safe, in many cases, considering benefit to risk ratio.

A lot of money has been spent searching for an Alzheimer’s cure. To no avail. Nothing very promising in the literature.

I for one am very angry with Pfizer. I suppose it is typical behavior in the industry. We still need big pharma. Don’t throw out the baby with bathwater. Hold them accountable. But, do not  conclude big pharma is corrupt therefore all drugs developed through the system are fruit of a poisoned tree and are therefore inherently untrustworthy and dangerous — in addition to being immorally overpriced.

It’s a bad syllogism. Drug companies are a very necessary evil.

Getting back to Enbrel.  Is this a silver bullet?.  More comment, biostatistics and analysis are required as well as prospective RCT medical studies. Since the drug will be generic soon big pharma will not finance the research. Fortunately, Alzheimer’s, a burgeoning epidemic as our population ages, is well funded through private sources.

Ideal prospective studies, which will likely be done make observations moving forward starting with a baseline current population. The process is slow.

Retrospective, population studies, primarily manipulation of data already there will not take long. These studies are never as good as prospective studies but perhaps good enough.

If you want my  bottom line: don’t run out and get Enbrel– YET.

I am not endorsing the use of the drug for any medical condition, including Alzheimer’s. This site is for informational purposes only. Medical care can only be delivered by a certified medical practioner who properly evaluates your particular issues. Please don’t diagnose or treat yourself. 

http://www.drjaller.com Dr. Jaller’s practice is in Maryland
__________________________
Regarding immune suppressants, many LLMD’s use them IF the patient is also on antimicrobial therapy at the same time. This tandem usage will protect the patient from a worsening infection(s), be it Lyme or any of the coinfections or even a latent infection.
Talk with your doctor about all treatments.

Chronic Inflammation Removes Motivation By Reducing Dopamine in the Brain

https://www.news-medical.net/news/20190605/Chronic-inflammation-removes-motivation-by-reducing-dopamine-in-the-brain.aspx

Chronic inflammation removes motivation by reducing dopamine in the brain

June 5, 2109

Written by Dr. Liji Thomas

Why do we feel listless when we are recovering from an illness? The answer is, apparently, that low-grade chronic inflammation interferes with the dopaminergic signaling system in the brain that motivates us to do things.

This was reported in a new paper published in the journal Trends in Cognitive Sciences.

The research carried out at Emory University explains the links between the reduced release of dopamine in the brain, the motivation to do things, and the presence of an inflammatory reaction in the body. It also presents the possibility that this is part of the body’s effort to optimize its energy expenditure during such inflammatory episodes, citing evidence gathered during their study.

The authors also published an experimental framework based on computational tools, devised to test the theory.

The underlying hypothesis is that the body needs more energy to heal a wound or overcome an infection, for instance, both of which are associated with low-grade inflammation. To ensure that energy is available, the brain uses an adaptive technique to reduce the natural drive to perform other tasks which could potentially drain away the energy needed for healing. This is essentially a recalibration of the specialized reward neurons in the motivation center of the brain, so that ordinary tasks no longer feel like they’re worth doing.

According to the new study, the mechanism of this recalibration is immune-mediated disruption of the dopamine pathway, reducing dopamine release.

The computational technique published by the scientists is designed to allow experimental measurements of the extent to which low-grade inflammation affects the amount of energy available, and the decision to do something based on the effort needed. This could allow us to better understand why and how chronic inflammatory states cause a lack of motivation in other disease conditions as well, including schizophrenia and depression.

Andrew Miller, co-author of the study, says,

“If our theory is correct, then it could have a tremendous impact on treating cases of depression and other behavioral disorders that may be driven by inflammation. It would open up opportunities for the development of therapies that target energy utilization by immune cells, which would be something completely new in our field.”

It is already known that immune cells release cellular signaling molecules called cytokines, which affect the functioning of the dopamine-releasing neurons in the area of the brain called the mesolimbic system. This area enhances our willingness to work hard for the sake of a reward.

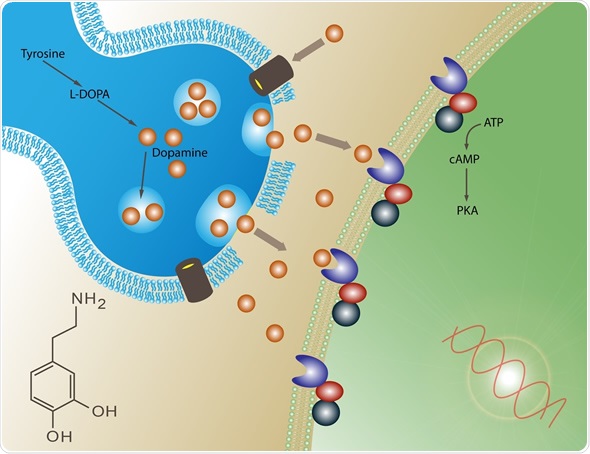
Dopamine

Image Copyright: Meletios, Image ID: 71648629 via shutterstock.com
Recently, it was discovered that immune cells also enjoy a unique capability to shift between various metabolic states, unlike other cells. This could affect cytokine release patterns in such a way as to signal the brain to conserve available energy for the use of the immune system.
These facts were the foundation of the new hypothesis, which explains it in terms of evolutionary adaptation. In the hypothetical early environment, the immune system, faced with abundant microbial and predatory challenges, needed tremendous amounts of energy. It therefore had its own mechanism to signal other body systems, via the mesolimbic dopamine system, to control the use of energy resources during periods when the organism was undergoing severe or sudden stress.
Modern life is relatively soft and less challenging. With less physical activity, low-grade inflammation is chiefly due to factors such as obesity, chronic stress, metabolic syndrome, aging and other lifestyle illnesses. This could mistakenly cause the mesolimbic dopamine neurons to produce less dopamine. Lower dopamine levels in turn decrease the motivation for work, by reducing the perception of reward while increasing the perception of effort involved. This ultimately conserves energy for use by the immune system.
Previous studies by Miller as well as other scientists have shown that a high level of immune functioning in association with low levels of dopamine and reduced motivation characterizes some cases of schizophrenia, depression and certain other mental health conditions.
The scientists do not think these disorders are caused by the low-grade inflammation, but that some people who have these illnesses are hypersensitive to immune cytokines. This could in turn cause them to lose motivation for daily living.
The scientists are currently performing a clinical trial on people with depression, to test the theory using the computational framework.


Source: Treadway M. T. et al., (2019). Can’t or Won’t? Immunometabolic Constraints on Dopaminergic Drive. Trends in Cognitive Sciences. https://doi.org/10.1016/j.tics.2019.03.003

________________

**Comment**
Interestingly,
2017 May;3(3). doi: 10.15761/JSIN.1000163. Epub 2017 May 11.

Lyme and Dopaminergic Function: Hypothesizing Reduced Reward Deficiency Symptomatology by Regulating Dopamine Transmission.

Abstract

The principal vector of Lyme disease in the United States is Ixodes scapularis: black legged or deer ticks. There is increased evidence that those infected may be plagued by anxiety or depression as well. Researchers have identified transcripts coding for two putative cytosolic sulfotransferases in these ticks, which recognized phenolic monoamines as their substrates. It is hypothesized that protracted Lyme disease sequelae may be due to impairment of dopaminergic function of the brain reward circuitry. The subsequent recombinant proteins exhibited sulfotransferase function against two neurotransmitters: dopamine and octopamine. This, in itself, can reduce dopamine function leading to many Reward Deficiency Syndrome behaviors, including depression and possibly, anxiety. In fact, it was shown that activity of Ixosc Sult 1 and Sult 2 in the Ixodid tick salivary glands might contain inactivation of the salivation signal through sulfonation of either dopamine or octopamine. This infraction results in a number of clinically observed mood changes, such as anxiety and depression. In fact, there are common symptoms observed for both Parkinson and Lyme diseases. The importance of understanding the mechanistic and neurobiological effects of Lyme on the central nervous system (CNS) provides the basis for pro-dopamine regulation as a treatment. WC 195.

Great article on dopamine:  https://suzycohen.com/articles/depression_low_dopamine/ Excerpt:

Dopamine deficiency will cause you to wake up sluggish in the morning, usually with brain fog, but you might feel happier and suddenly more enthusiastic with a “hit” of some sort, perhaps a cup of coffee.  Low dopamine (as opposed to low serotonin) causes a different kind of depression, one that is hallmarked by a lack of pleasure.