Archive for the ‘Lyme’ Category

8 Reasons Why the Standard Western Blot is a Poor Diagnostic Indicator of Lyme & Tips for Making Sense of Your Lab Result
https://www.uprootinglyme.com/8-reasons-why-the-standard-western-blot-is-a-poor-diagnostic-indicator-of-lyme/?

8 Reasons Why The Standard Western Blot Is A Poor Diagnostic Indicator of Lyme – and tips for making sense of your lab result

 In Understanding Lyme

This post was inspired by one of my practitioner-students who is in the process of both healing her own Lyme disease and co-infections, and learning how to be the best resource and guide for her own patients.

It is confusing for everyone, including health professionals, that the diagnostic testing for Lyme disease is so poor, and often meaningless.  

If you’ve had a tick bite you might be wondering if you contracted Lyme and want to take the blood test to see if infection shows up.  If you’ve had Lyme in the past and been treated, but still have remaining health issues, you may questioningwant to know if it’s still active through blood work.  Or, if you have a mysterious chronic disease that might be caused by Lyme-Borreliosis and/or its co-infections, the blood work could tell you if your illness is due to Lyme disease.  Right?

It’s vitally important to know what the CDC’s standard Western Blot test for Lyme is good for, and what it is not.  Unfortunately, it’s not good for much, but there are some key indicators that can be useful.

First, here are 8 reasons why it is such a poor diagnostic tool:

1. Poor test sensitivity. The CDC standard western blot (SWB) is not as sensitive as blots done by companies that specialize in testing tick borne disease, such as Igenex, and misses approximately 50% of cases (statistics vary, but it’s a lot!).   False negative are common, often moreso in people who are very sick. Blots performed by Lyme specialty labs are more sensitive, however there are still a percentage of false negatives, especially in the late stages of the disease.

2. Diagnostic criteria. Even if a patient tests positive for a highly specific Borrelia band (bands 18, 23, 31, 34, 37, 39, 83 and 94) indicating exposure, a test will still be considered negative.

The CDC created a high standard for medical reporting of  Lyme disease cases for tracking and statistical use that requires at least 2 bands of IgM or at least 5 bands of IgG to qualify for a positive result.  Their standard was not intended to become doctor’s diagnostic guideline, yet it was adopted by the Infectious Disease Society of America’s (IDSA’s) guideline and has been.

3. Interpretation of the test is subjective. A test result depends on the skill of the technician who reads it. Different people can come up with different results. A strong positive on a band will likely be read the same by lab-techdifferent people but a weaker positive may have different interpretations.  This is one reason it is recommended to use a Lyme-literate lab such as Igenex. 

4. All antibody bands are not created equal!   SWB surveillance for IgG includes 5 that are non-specific to Borrelia, and several that could only be attributed to Borrelia (and it excludes 3 others that are Borrelia specific).  There is definitely room for improving the standard lab test for Lyme disease, simply by using more of the Borrelia-specific bands.  Igenex testing includes two more Borrelia specific bands than the SWB.

5. Different antibody bands may become positive during different stages of the infection.  It is common that the first antibodies to appear is for band 41, yet it is non-specific and would be called “negative”.  Weeks, months or years later, if re-tested, different antibodies (bands) may appear, and there may be more or fewer bands that show up.

This depends on many factors, including the stage of disease, the health or decline of the immune system, what treatments you have received, and more.
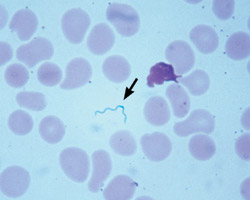
borrelia-in-blood6. Borrelia exists sparsely in the blood.  This is the reason it is difficult to test for it directly and an antibody panel is used.  PCR tests look for DNA directly in the blood but only detect a small number of cases.

Yet an antibody test only works well when the microbe is visible to the immune system, and can generate antibodies against it.  Lyme-borreliosis and the other stealth co-infections have numerous survival techniques of immune system evasion, including techniques for cloaking themselves and disrupting the body’s natural immune system response.

7. Failure to generate antibodies.  An antibody test also only works if a person’s immune system is strong enough to generate an antibody response. Late stage patients or immune compromised patients may not mount an appropriate antibody response.

8. Species Variation. There are 5 known subspecies, and over 100 strains of Borrelia in the US and 300 worldwide (source: http://www.ILADS.org), yet the SWB only tests bands for 1 subspecies of Borrelia burgdorferi; specialized testing labs such as IGENEX test for only two.  Ideally, the testing would be region-specific.

That was a lot of information to take in, so here are 3 main points to take away, to help you self-advocate and navigate the Lyme diagnosis maze:

  • If you are dealing with an acute case of Lyme disease or a recent bite, know that any Lyme test given before 6 weeks out is not likely to be accurate, since it takes that long for your body to generate the antibodies to the bands that the Western Blot tests for. tick

  • I didn’t waste any time discussing the ELISA test for Lyme disease in this article – and don’t waste any of your time with this lab!  For numerous reasons, it is even less accurate than the Western Blot for detecting Lyme-Borreliosis.
  • If your Lyme Western Blot came back negative, and you are a little or a lot sick, it is meaningless.  You may very well still have Lyme disease.  Try 6-8 weeks of a natural antimicrobial protocol, and re-test.  You will be more likely to show antibodies at this time (but it’s not a guarantee).
  • Always ask for a copy of your blood work, and look at the test results yourself.  If you have one of the Lyme Borreliosis-specific bands that are positive (again, that’s bands 18, 23, 31, 34, 37, 39, 83 and 94) – even just 1! – even though the CDC (and therefore most doctors) would call it negative, this is a clear positive diagnostic indicator of Lyme disease.  
  • Keep in mind that what you’re suffering from could be a different stealth pathogen, such as Babesia or Bartonella, which require a different lab test, and are also notoriously difficult to detect.

fishing-sunsetThere are times when it becomes impossible to determine whether someone’s health problems are due to Lyme-borreliosis infection or not.

The good news is, from the holistic medical perspective you can still recover your health and your life through treatment that is based on your symptom presentation and the restoration of your energy, immunity and vitality – regardless of whether you ever determine the cause.  The question then becomes, do you want a diagnosis, OR DO YOU WANT TO GET BETTER?


If you are confused about whether or not you have Lyme, a co-infection, or other complex chronic disease, call us at 845-687-6211 or email info@uprootinglyme.com to set up an in-person or virtual holistic Lyme consultation at reasonable rates. We’ll help you interpret your labs and co-create a strategic holistic treatment plan. Navigating Lyme disease is confusing, and confusion can cost you time and money that could be spent on getting the treatment you need. Contact us now!

____________________

**Comment**

Great article with many valid points.  CDC 2-tiered testing is virtually worthless and the required arbitrary and stringent antibody levels are asinine.  For a quote on this:

“setting arbitrary level of antibodies to diagnose a disease that has not been amenable to Koch’s postulates seems open to question.  By the same token, ignoring antibody results unless they meet arbitrary levels seems suspect.  The vast majority of patients in this series showed some WB antibody exposure, but many did not meet the arbitrary limits set….in our present state of knowledge, the diagnosis of chronic Lyme disease is a clinical one.  Many of the patients in this series have suffered serious ‘hurts’ when they have been told that they could not have LD because their WB did not meet arbitrary limits.”  Dr. Waisbren https://madisonarealymesupportgroup.com/2017/07/09/idsa-founder-used-potent-iv-antibiotics-for-chronic-lyme/

I’ve been in discussion with a PhD who is researching Lyme testing. He feels, as do I, that testing should initially cast a wide net with follow up testing being more specific; however, just the opposite is true with current testing.  He also questions the CDC insistence that p41 is too non-specific to use.  

According to microbiologist Tom Greer p41 is the flagellin protein of all spirochetes and is usually the first to appear after a Bb infection. Western Blot explained by Grier

For another great read on testing:  https://madisonarealymesupportgroup.com/2018/09/12/lyme-testing-problems-solutions/

Please remember that this testing is ONLY for Lyme disease and will NOT pick up coinfections.  The tests for those, as stated in this article, are just as abysmal.

A trained Lyme literate doctor is experienced in understanding the symptoms of all of these pathogens and will diagnose you clinically.  They understand the limitations of testing.  The Horowitz questionnaire has been validated and is a much better indicator of infection:  https://madisonarealymesupportgroup.com/wp-content/uploads/2016/01/symptomlist.pdf  If you suspect you are infected, print this out, fill it out, and take it with you to your first appointment.  Avoid mainstream medicine if at all possible as they are truly in the dark ages with all things tick-borne.

Until medical professionals realize this is not a straight forward disease, patients need to seek help from those who understand it.

Immunoassay May Help Identify Pediatric Lyme Arthritis

https://www.medscape.com/viewarticle/922645?src=rss

Immunoassay May Help Identify Pediatric Lyme Arthritis

By Marilynn Larkin

December 18, 2019

NEW YORK (Reuters Health) – In Lyme disease-endemic areas, a C6 peptide enzyme immunoassay (EIA) test may help guide initial management of children with acute arthritis, an observational study suggests.

“Children with Lyme disease frequently present to the emergency department with an inflamed joint,” Dr. Lise Nigrovic of Boston Children’s Hospital told Reuters Health by email. “Although Lyme arthritis is initially treated with oral antibiotics, many children will undergo an invasive procedure such as a joint tap or even wash-out as part of the initial evaluation.”

“We demonstrated that the C6 EIA test, a previously approved first-tier test for Lyme disease, with results available within a few hours, could be used to safely guide initial management for children with inflamed joints to avoid unnecessary invasive procedures for children with Lyme arthritis,” she said.

The authors performed C6 EIA tests on 911 children presenting to a Pedi Lyme Net emergency department from 2015-2019. Lyme arthritis was defined as a positive or equivocal C6 EIA test followed by a positive supplemental immunoblot result; septic arthritis was defined as a positive synovial fluid culture result or a positive blood culture result with synovial fluid pleocytosis. Other cases were considered inflammatory arthritis.

As reported in Pediatrics, C6 EIA test results indicated that 211 children (23.2%) had Lyme arthritis, 11 (1.2%) had septic arthritis, and 689 (75.6%) had other inflammatory arthritis.

A positive or equivocal C6 EIA result had a sensitivity of 100% and specificity of 94.2% for Lyme arthritis. None of the 250 children with a positive or equivocal C6 EIA result had septic arthritis. However, of those with a positive first-tier Lyme disease test result, 75 underwent arthrocentesis (30%) and 27 had an operative joint washout performed (10.8%).

Dr. Eugene Shapiro of Yale School of Medicine in New Haven, Connecticut, coauthor of a related editorial, commented by email to Reuters Health, “In an area in which Lyme disease is endemic, although a positive C6 ELISA result in a child with arthritis of the knee is suggestive of Lyme disease, it does not rule out the possibility that it is due a different bacterium such as Staphylococcus aureus. Clinical judgement is still critical in deciding how to manage such patients.”

Lyme disease specialist Dr. Tania Dempsey, founder of Armonk Integrative Medicine in New York, commented, “The C6 EIA test has shown promise over the older ELISA test that is part of the two-tier Lyme testing recommended by the U.S. Centers for Disease Control and Prevention, dating back to 1995. There are serious limitations to the two-tier test, including a nearly 50% false-negative rate.”

“While this study shows promise . . . to accurately identify Lyme arthritis with the use of the C6 EIA test, it is not clear what the false negative rate was,” she told Reuters Health by email. “Their numbers show that they were able to diagnose 23.2% of children with Lyme arthritis and 1.2% with septic arthritis. But 75.6% were identified as having inflammatory arthritis, which means that the diagnosis is unclear. Based on the published false negative rate of this test, we can assume that a fair percentage of those with inflammatory arthritis probably had Lyme arthritis.”

“One key point is that the study design included a confirmatory immunoblot test for C6 EAI positive or equivocal results. This would be equivalent to a two-tier test,” she noted. However, “no immunoblot testing was done on any of the C6 EAI- negative results. Since we we know a large number of patients will be missed by this (test), it is discouraging to think of all those patients who might still be suffering with Lyme disease that was undetected with the screening C6 EAI test.”

“There is no question that we need better testing for Lyme disease,” she said. “The C6 EIA has some benefits but is clearly not sufficient.

SOURCE: http://bit.ly/34fODsR and http://bit.ly/2EgdP8g Pediatrics, online December 13, 2019.

__________________

**Comment**

While this article desires to make you believe this test is accurate, Dr. Demsey clearly points out it has many problems including not knowing what the false negative rate was, as well as the fact 75.6% were identified as having inflammatory arthritis –  meaning that the diagnosis is unclear. And lastly, based on the published false negative’s, a fair percentage of those with inflammatory arthritis probably had Lyme arthritis.

Take away:  The test still sucks.

For more:  https://madisonarealymesupportgroup.com/2019/03/07/yet-another-worthless-study-showing-2-tiered-lyme-testing-can-not-rule-infection-out/

https://madisonarealymesupportgroup.com/2019/12/01/c6-peptide-test-for-lyme-disease-may-indicate-borrelia-miyamotoi-infection/

https://madisonarealymesupportgroup.com/2019/08/15/borrelia-miyamotoi-infection-leads-to-cross-reactive-antibodies-to-the-c6-peptide-in-mice-men/

https://madisonarealymesupportgroup.com/2018/09/12/lyme-testing-problems-solutions/


Chronic Lyme Disease: An Evidence-Based Definition by the ILADS Working Group

https://www.mdpi.com/2079-6382/8/4/269

Chronic Lyme Disease: An Evidence-Based Definition by the ILADS Working Group†

International Lyme and Associated Diseases Society.
Antibiotics 2019, 8(4), 269; https://doi.org/10.3390/antibiotics8040269 (registering DOI)
Received: 8 October 2019 / Revised: 9 December 2019 / Accepted: 11 December 2019 / Published: 16 December 2019
(This article belongs to the Special Issue Antibiotics Resistance of Borrelia)
Objective: Chronic Lyme disease has been a poorly defined term and often dismissed as a fictitious entity. In this paper, the International Lyme and Associated Diseases Society (ILADS) provides its evidence-based definition of chronic Lyme disease. Definition: ILADS defines chronic Lyme disease (CLD) as a multisystem illness with a wide range of symptoms and/or signs that are either continuously or intermittently present for a minimum of six months. The illness is the result of an active and ongoing infection by any of several pathogenic members of the Borrelia burgdorferi sensu lato complex (Bbsl). The infection has variable latency periods and signs and symptoms may wax, wane and migrate. CLD has two subcategories, CLD, untreated (CLD-U) and CLD, previously treated (CLD-PT). The latter requires that CLD manifestations persist or recur following treatment and are present continuously or in a relapsing/remitting pattern for a duration of six months or more.
Methods: Systematic review of over 250 peer reviewed papers in the international literature to characterize the clinical spectrum of CLD-U and CLD-PT.
Conclusion: This evidence-based definition of chronic Lyme disease clarifies the term’s meaning and the literature review validates that chronic and ongoing Bbsl infections can result in chronic disease. Use of this CLD definition will promote a better understanding of the infection and facilitate future research of this infection.
Shor, S.; Green, C.; Szantyr, B.; Phillips, S.; Liegner, K.; Burrascano, J., Jr.; Bransfield, R.; Maloney, E.L. Chronic Lyme Disease: An Evidence-Based Definition by the ILADS Working Group. Antibiotics 2019, 8, 269.
_________________
**Comment**
Please give this to each and every doctor and nurse you know.  This is not conjecture.
Thousands of people are walking around with chronic Lyme disease and it’s not going away.

https://madisonarealymesupportgroup.com/2019/05/18/more-than-2-million-could-suffer-from-post-treatment-lyme-disease-syndrome-in-2010-study-says/

Peer-Reviewed Evidence of Persistence of Lyme:MSIDS copy  Over 700 peer-reviewed articles showing pathogen persistence.

It’s also congenital (spread from mother to baby):  https://madisonarealymesupportgroup.com/2018/06/19/33-years-of-documentation-of-maternal-child-transmission-of-lyme-disease-and-congenital-lyme-borreliosis-a-review/

https://madisonarealymesupportgroup.com/2018/02/26/transplacental-transmission-fetal-damage-with-lyme-disease/

https://madisonarealymesupportgroup.com/2018/05/24/new-berlin-mom-given-life-altering-lyme-disease-diagnoses-after-pregnancy/

https://madisonarealymesupportgroup.com/2018/11/11/gestational-lyme-other-tick-borne-diseases-dr-jones/

Dr. Lida Mattman, an expert on the cell wall deficient form of borrelia believes Lyme can be transmitted in many ways – including sexually:  https://madisonarealymesupportgroup.com/2019/04/02/transmission-of-lyme-disease-lida-mattman-phd/

https://madisonarealymesupportgroup.com/2019/05/24/microbiology-professor-im-convinced-lyme-disease-is-transmittable-from-person-to-person/


Lyme Insurance Claims Make Huge Jump in U.S.

https://www.lymedisease.org/fair-health-lyme-claim-lines/

10 DEC 2019

TOUCHED BY LYME: Lyme insurance claims make huge jump in US

General Symptom Questionnaire-30 (GSQ-30): A Brief Measure of Multi-System Symptom Burden in Lyme Disease

https://www.frontiersin.org/articles/10.3389/fmed.2019.00283/full

ORIGINAL RESEARCH ARTICLE
Front. Med., 06 December 2019 | https://doi.org/10.3389/fmed.2019.00283

The General Symptom Questionnaire-30 (GSQ-30): A Brief Measure of Multi-System Symptom Burden in Lyme Disease

Introduction: The multi-system symptoms accompanying acute and post-treatment Lyme disease syndrome pose a challenge for time-limited assessment. The General Symptom Questionnaire (GSQ-30) was developed to fill the need for a brief patient-reported measure of multi-system symptom burden. In this study we assess the psychometric properties and sensitivity to change of the GSQ-30.

Materials and Methods: 342 adult participants comprised 4 diagnostic groups: Lyme disease (post-treatment Lyme disease syndrome, n = 124; erythema migrans, n = 94); depression, n = 36; traumatic brain injury, n = 51; healthy, n = 37. Participants were recruited from clinical research facilities in Massachusetts, Maryland, and New York. Validation measures for the GSQ-30 included the Patient Health Questionnaire-4 for depression and anxiety, visual analog scales for fatigue and pain, the Sheehan Disability Scale for functional impairment, and one global health question. To assess sensitivity to change, 53 patients with erythema migrans completed the GSQ-30 before treatment and 6 months after 3 weeks of treatment with doxycycline.

Results: The GSQ-30 demonstrated excellent internal consistency (Cronbach α = 0.95). The factor structure reflects four core domains: pain/fatigue, neuropsychiatric, neurologic, and viral-like symptoms. Symptom burden was significantly associated with depression (rs = 0.60), anxiety (rs = 0.55), pain (rs = 0.75), fatigue (rs = 0.77), functional impairment (rs = 0.79), and general health (rs = −0.58). The GSQ-30 detected significant change in symptom burden before and after antibiotic therapy; this change correlated with change in functional impairment. The GSQ-30 total score significantly differed for erythema migrans vs. three other groups (post-treatment Lyme disease syndrome, depression, healthy controls).

The GSQ-30 total scores for traumatic brain injury and depression were not significantly different from post-treatment Lyme disease syndrome.

Conclusions and Relevance: The GSQ-30 is a valid and reliable instrument to assess symptom burden among patients with acute and post-treatment Lyme disease syndrome and is sensitive in the detection of change after treatment among patients with erythema migrans. The GSQ-30 should prove useful in clinical and research settings to assess multi-system symptom burden and to monitor change over time. The GSQ-30 may also prove useful in future precision medicine studies as a clinical measure to correlate with disease-relevant biomarkers.

_______________

**Comment**

The good thing about this is it clearly shows that there is a significant change in symptom burden after antibiotic therapy.  In other words – the proof is in the pudding.  If you treat this properly, patients will improve.  This should shut the IDSA/CDC up, but it won’t.

Unfortunately they decided to keep the CDC/IDSA “Post Treatment Lyme Disease Syndrome” moniker rather than deal with persistent infection.  Until this issue is laid to rest, research will be skewed and authorities will not treat this appropriately.  There’s over 700-peer reviewed articles showing the persistence of Lyme disease: Peer-Reviewed Evidence of Persistence of Lyme:MSIDS copy

Another good thing this shows is the seriousness of symptoms that patients can be left with – the total scores aren’t significantly different from those with traumatic brain injury or depression. The symptoms are very, very real and very, very serious.

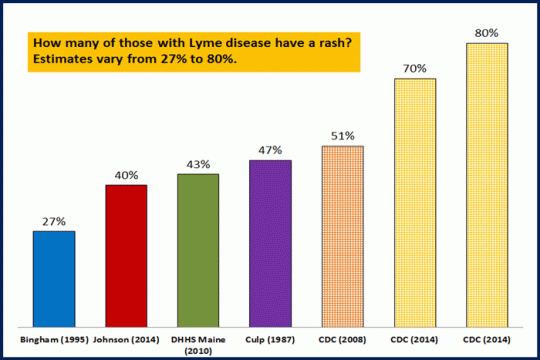
Please remember that those with the EM rash is highly variable:  https://madisonarealymesupportgroup.com/2019/02/22/why-mainstream-lyme-msids-research-remains-in-the-dark-ages/

Rashes-larger-blog-3

It is a bit of a head-scratcher as to why the authors felt compelled to do this study when a validated symptom questionnaire already exists:  https://madisonarealymesupportgroup.com/2017/09/05/empirical-validation-of-the-horowitz-questionnaire-for-suspected-lyme-disease/

https://madisonarealymesupportgroup.com/wp-content/uploads/2016/01/symptomlist.pdf

This symptom checklist is far more accurate than any serology testing at this point.  Doctors would be wise to utilize it.  There are also checklists for Babesia and Bartonella as well:

https://madisonarealymesupportgroup.com/2011/09/25/the-babesia-checklist-copyrighted-2011-james-schaller-md-mar-version-20/

https://madisonarealymesupportgroup.com/2011/09/25/the-bartonella-checklist-copyrighted-2011-james-schaller-md-version-11/

What we really need are checklists such as these for ALL tick-borne infections.  Then we desperately need doctor education.