Archive for the ‘Viruses’ Category

Combating Viruses


herpes-simplex-virus-01a-924x924

3-D animation by Bryan Brandenburg.  March 9, 2013

<a href=http://www.bryanmbrandenburg.com>Courtesy of Bryan Brandenburg </a>

http://science.howstuffworks.com/life/cellular-microscopic/virus-human.htm  A virus is a tiny particle – about 1,000 times smaller than bacteria and must be viewed using an electron microscope. It consists of:
• Nucleic acid – set of genetic instructions, either DNA or RNA, either single-stranded or double-stranded (see How Cells Work for details on DNA and RNA)
• Coat of protein – surrounds the DNA or RNA to protect it
• Lipid membrane – surrounds the protein coat (found only in some viruses, including influenza; these types of viruses are called enveloped viruses as opposed to naked viruses)

Viruses are all over the place, just waiting for a host cell to survive and proliferate. They enter through our nose, mouth, or breaks in the skin. Once they’ve infiltrated, they take over the host cell and make copies of viral genetic instructions to make new viruses. Then they either break the cell open, destroying it or they pinch out and break away with a piece of the cell membrane surrounding them, but not destroying the host cell. Once freed, they attack other cells, and spread quickly.

When you catch a cold here’s what happens:
*An infected person sneezes near you.
*You inhale the virus particle, and it attaches to cells lining the sinuses in your nose.
*The virus attacks the cells lining the sinuses and rapidly reproduces new viruses.
*The host cells break, and new viruses spread into your bloodstream and lungs.
*Viruses in nasal fluid drips down your throat giving you a sore throat.
*Viruses in your bloodstream can attack muscle cells and give you muscle aches.

The immune system finally responds producing chemicals which cause you to have a fever. This fever helps by slowing down the rate of viral reproduction and continues until the viruses are eliminated; however, if you sneeze, you can spread it into the environment where they again lie in wait for another host.  This is why it’s wisest to not use fever reducers unless absolutely needed.  By using a fever reducer you are eliminating one of the most powerful interventions against viruses in your own body.

In viruses like herpes and HIV; however, they mix their genetic code into the host cell’s genetic instructions so when the host call reproduces, the new instructions get copied into the his cell’s offspring. These particular host cells can go through many rounds of reproduction and then some environmental or predetermined genetic signal will wake up the “sleeping” viral instructions that now take over the host’s machinery and make new viruses.
Some routes of viral transport:
*Carriers such as mosquitoes, fleas, and ticks
*The air
*Body fluids such as sailva, sweat, mucus, blood, semen, vaginal secretions
*Surfaces on which bodily fluids have dried

What helps?
Interestingly, viruses often change slightly, changing their genetic instructions and altering their protein coat, making vaccines ineffective. Vaccine proponents will say this is why they must continually make new vaccines. Those opposed to vaccines will say this is why they rarely work. Just like MSIDS (multi systemic infectious disease syndrome or Lyme with friends) there is a schism in the medical community over vaccines.

To read more on vaccines, please go here and be informed:  https://madisonarealymesupportgroup.wordpress.com/2015/06/19/a-word-on-vaccines/ and https://madisonarealymesupportgroup.wordpress.com/2015/07/15/vaccines-continued/ and https://madisonarealymesupportgroup.wordpress.com/2016/03/19/a-dozen-collapse-after-vaccine/

To combat viruses, we must look at the immune system and make ourselves tough targets.  http://health-truth.com/our-program/health-articles/chronic-fatigue-syndrome/how-to-conquer-the-viral-bacterial-syndrome/

According to Michael Biamonte, C.C.D., the immune system uses nutrients from food to manufacture substances that attack and kill viruses. Viruses help bacteria by invading the cells in an area, and if the immune system is too weak, bacteria begin to swarm the  damaged cells invaded by the virus. As the virus begins to die having gone through it life cycle, the bacteria then start a secondary infection. For an MSIDS (multi systemic infectious disease syndrome) patient, they might be fighting borrelia (Lyme), Babesia, Bartonella, and many more pathogens, on top of viruses. This makes their illness much more complex.

Biomonte says to avoid sugar as it reduces the number of white bloods cells which fight off infection. He states that garlic is the most effective food against all infections as well as Echinacea, Zinc, water-soluble vitamin A, protein (stimulates the adrenal and thyroid), and eggs (contain large quantities of lecithin).

http://science.howstuffworks.com/life/cellular-microscopic/light-virus.htm  Interestingly, a study done at Arizona State and Johns Hopkins shows strong, quick blasts of purple light from a low power laser can kill viruses by vibrating and damaging their outer shells, but unlike other treatments doesn’t cause mutations leading to viral resistance. Blood UV radiation, similarly to the laser, also kills viruses by breaking down their cell walls.

Anti-virals:
Green Tea
Licorice (glycyrrhizin)
Pau D-Arco
Olive Leaf
Elderberry
Zinc
Garlic
Echinacea
St. John’s Wort
Coconut oil
Eucalyptus oil
Vitamin C

Blood UV

Ozone

Monolaurin

Always check with your health care professional before starting any supplement.

wellnessresources.com.http://www.wellnessresources.com/health/articles/monolaurin_a_natural_immune_boosting_powerhouse/  Written by Byron J. Richards, Board Certified Clinical Nutritionist

“Monolaurin a 12-carbon long fatty acid, derived from coconut oil but prepared into a mono-ester of lauric acid, is another anti-viral with decades of research showing the germ-killing and disinfectant properties of this natural compound. Monolaurin is a component of breast milk, part of Mother Nature’s immune support that is passed from mother to child.

Research dating back 30 years first identified that the 12 carbon fatty acid2 of monolaurin was highly effective at combating gram positive bacteria and yeasts (like Candida albicans). The Candida killing ability of monolaurin3 has been established. The most research has been done on gram positive bacteria, as the compound can be used to reduce infections on poultry and help clean equipment involved in the production of food. And monolaurin is effective against many viruses. The nutrient has been in widespread use as an immune support dietary supplement for several decades.

Monolaurin has been found to incorporate itself into the cell membrane of gram positive bacteria and have the net effect of disturbing the integrity of its cell membrane, blocking replication and making it an easier enemy for your immune system to take care of. 

In 1992 University of Minnesota researchers demonstrated an additional way that monolaurin helps, showing that it could reduce the toxicityof Staphylococcus gram positive bacteria. More recently, another gram positive bacteria, Bacillus anthracis, has been thrust into public attention by the threat of its use in bioterrorism. Like many bacteria, it’s severity of infection is based on how much toxin it can produce. In 2005 the University of Minnesota researchers this time demonstrated that monolaurin inhibited the genes that enabled anthrax to generate toxins. In 2006 research they showed the mechanism of reducing gram positive infection toxicity applied to many organisms, indicating that monolaurin is likely to help reduce the toxicity of any gram positive infection by making it less severe. This research also found that healthy cells were made stronger by monolaurin, also helping them combat the toxicity.
Monolaurin has demonstrated some ability to help regulate gram negative bacteria, one of which is the common intestinal inhabitant known as Helicobacter pylori (H. pylori). If H. pylori starts getting out of balance and turns hostile, like a bad gang in the neighborhood, then a lot of stomach distress can follow. Researchers have shown that monolaurin has a direct and potent germ killing effect on H. pyloria, regardless of stomach pH. The H. pyloria germ killing ability of monolaurin has been confirmed by a second group of researchers. Exactly how monolaurin is able to kill these gram negative bacteria has not been identified.
Research has shown that monolaurin is not effective against most gram negative bacteria like Salmonella or E. coli, which have a different kind of outer cell membrane than gram positive bacteria. In contrast to this general finding, one study of bacteria cultured from the skin of children found that monolaurin inhibited the growth of gram positive and gram negative bacteria.
It has been generally observed that no gram positive bacteria are resistant to monolaurin. However, a recent study demonstrated that various super strains of gram positive Vancomycin Resistant Enterococcus (VRE) have developed partial (up to 70%) resistance to monolaurin. VRE is especially problematic to those with weak immunity. It is unknown if monolaurin is effective or not against Methicillin-resistant Staphylococcus aureus (MRSA). A detailed analysis in the VRE study showed that the mutated enterococcus bacteria had learned to tighten their cell walls, making it more difficult for monolaurin to get a toehold (the same problem antibiotics were having). Monolaurin has been shown to reduce the toxicity of gram positive infections, and has been shown to help Vancomycin work better against these super strains – meaning that monolaurin used along with appropriate medical care may produce a superior result.

Monolaurin and Viruses
Monolaurin is one of the most popular nutrients to assist in combating various viruses. It is believed to work by interacting with the lipids and phospholipids that form the envelope of the virus, causing it to weaken or disintegrate.  Research suggests that monolaurin exerts some degree of immune support for the following viruses:

• Human immunodeficiency virus HIV-1, HIV+ *Measles virus
 *Herpes simplex virus-1
 *Herpes simplex virus-2
 *Herpes viridae (all)
 *Human lymphotropic viruses (type 1)
 *Vesicular stomatitis virus
 *Visna virus
 *Cytomegalovirus
 *Epstein-Barr virus
 *Influenza virus
*Pneumonovirus
 *Sarcoma virus
 *Syncytial virus

One study showed that while monolaurin was effective against Cytomegalovirus it was not effective against rhinoviruses, the cause of the common cold.  There are many anecdotal reports of monolaurin helping combat the flu.  

Many of the types of viruses monolaurin helps are those that can be chronic low grade infections that deplete energy on a regular basis and flare up when you are stressed or down. If you have ever had a bad bug and never really got your energy back then monolaurin may help your immune system clean up the problem – even years later. Many find it useful for recurring mouth sores that are herpes-based problems.
The new discovery that many lipid coated viruses can live in your stored fat and disturb your metabolism, promoting obesity, opens the door for the use of monolaurin to assist weight management – though no specific studies have been done on this topic.
In summary, monolaurin is a nutritional fatty acid that is non toxic to humans and a friendly nutrient for human cell health. In contrast, it can be a knock out punch for gram positive bacteria and a number of difficult viral problems. It can also help to keep normal inhabitants of your digestive tract, such as H. Pylori and Candida albicans, in a better state of healthy balance.”

MSIDS sufferers need as many tools as possible in their toolbox as our bodies are in a war. Thankfully we have many aids at our disposal to assist our bodies along the way.

Why We Can’t Get Better

Most MSIDS (multi systemic infectious disease syndrome – or Lyme with friends) sufferers are familiar with Dr. Horowitz, a famous and gifted LLMD (Lyme Literate Doctor) who wrote the book, “Why I Can’t Get Better?  Solving the Mystery of Lyme and Chronic Disease.”  I just noticed you can get it new for $7.99 – the best eight bucks you’ll ever spend!  I warn you; however, it’s deep and it’s wide, and you will be looking up a few terms unless you’re a M.D. http://www.amazon.com/Better-Solving-Mystery-Chronic-Disease/dp/1250019400

In fact, he’s the person who came up with the term MSIDS as it more adequately explains what’s going on in most patients diagnosed with “Lyme Disease,” as research shows we are typically infected with multiple pathogens making our treatment pictures far more complex than most GP’s realize and is also a very good reason why people don’t get better.  This issue is what he discusses in the following videos.  For some of you, you just can’t get on top of things – even after years of treatment.  There can be numerous reasons for this but the following videos may enlighten both you and your doctor.

Working with an LLMD is definitely a partnership.  In the beginning, unless you’ve watched someone go down this pot-hole riddled road, you know very little other than the fact that your body’s going to hell in a hand basket!  As time progresses, you talk to others, watch videos, read books, and become an on-line researcher learning things you never in your wildest dreams would have thought about learning (the life-cycles of ticks).

For those of you who are new to the journey, you want to get someone you know up to speed quickly, or if you need a refresher course, these videos will do it.  Horowitz is engaging, intelligent, and funny.  The first video is only 8 minutes long and explains the nuts and bolts of how he came to his current knowledge.

The second video is an hour long, but definitely worth watching.  In a much more detailed fashion, it explains many symptoms of the various coinfections that could be holding up your progress unless you are dealing with them.  Watch these videos, take notes, and go back to your doctor and discuss these possibilities.  Remember, testing for all of these pathogens is extremely poor and not to be solely relied upon for diagnosis.  It’s important to “study thy enemy,” so you understand him and know how to combat him.  In this case the more you know about the various pathogens and how they affect the human body the better.

Published on Nov 3, 2014
At the “Symposium on Tick-borne Diseases” held May 17, 2014 at the Hyatt in Cambridge, Maryland, Dr. Richard Horowitz provided insights into the many diseases humans are contracting from ticks, and he helps us to differentiate between the different illnesses. The event was hosted by the Lyme Disease Association of the Eastern Shore of Maryland (soon to be the Lyme Disease Association of Delmarva), a 501(c)(3) non-profit organization providing educational resources on tick-borne diseases. This and other videos from the Symposium were made possible by a very generous private donation for which we are very thankful to have received. The wonderful videographer/editor for the event was Bryan Krandle (krandle86@yahoo.com). If you enjoy having wonderful resources like the videos from this conference, please consider a donation to the LDAESM, P.O. Box 5360, Salisbury, Maryland 21802. Thank you!

Fixation on Zika

zika-virus

A transmission electron micrograph (TEM) provided by the Centers For Disease Control in Atlanta, Georgia shows the Zika virus. (CDC/Cynthia Goldsmith/Reuters)

http://www.thevaccinereaction.org/2016/03/our-fixation-with-polio-and-zika-7/

“Imagine 100 people who have symptoms of severe paralysis somewhere on their body… say, their legs. They are all permanently paralyzed, but some of the people have one or more of the following conditions which can produce paralysis similar to polio:

Acute Flaccid Paralysis (AFP); Arsenic Poisoning; Bilious Remittent Fever; Chinese Paralytic Syndrome; Cholera Morbus virus; Coxsackie virus; DDT Poisoning; ECHO; Enteroviral Encephalopathy; Epidemic Cholera; Ergotism; Famine Fever; Guillain-Barré Syndrome; Hand, Foot, and Mouth Disease; Inhibitory Palsy; Intermittent Fever; Lead Poisoning; Myalgic Encephalomyelitis (Chronic Fatigue Syndrome); Post-Polio Syndrome; Reye’s Syndrome; Spinal Apoplexy; Spinal Meningitis; Transverse Myelitis; Traumatic Neuritis; Undiagnosed Congenital Syphilis; Viral or Aseptic Meningitis; Worm Fever… and “provocation of limb paralysis by intramuscular injections of many types, including a variety of vaccines.”1 2

Remember; however, it is possible – highly possible – that those testing positive for polio may NOT have been paralyzed by polio.  Scientists STILL don’t know why some become paralyzed and some do not, and it is completely harmless or mild in more than 99% of polio carriers.  Did you know that?  Just as Zika is a mild virus that’s been around for over 40 years and has never caused an issue before. https://madisonarealymesupportgroup.wordpress.com/2016/02/05/zika-sexually-transmitted/

I was always told that assuming something makes an ass out of u and mi.

And yet, today, “scientists” are stating that tissue samples from two fetuses containing Zika proves Zika caused microcephaly in these children, and before long, the way things are going,

“Zika will become synonymous with microcephaly – much like polio has become synonymous with severe paralysis.” 

Global health officials have said, however, that as many as 80% of people exposed to the virus have little to no symptoms. According to the U.S. Centers for Disease Control and Prevention, only about 1 out of every five infected will become ill with mild symptoms such as fever, rash, joint pain, or conjunctivitis, lasting for several days to a week. http://www.cdc.gov/zika/symptoms/ and https://madisonarealymesupportgroup.wordpress.com/2016/02/05/zika-sexually-transmitted/

For two possible causes of the increase in microcephaly please read:  https://madisonarealymesupportgroup.wordpress.com/2016/03/04/health-policy-recap/

https://jameslyonsweiler.com/2016/02/29/vaccine-safety-research-reform/  Also worth noting:  Brazil has been using WHOLE-CELL pertussis on impoverished pregnant women.  Microcephaly is concentrated in the slums of Brazil.  Interestingly, there is no sign of Zika in many cases of microcephaly, and the Zika virus has spread to over 40 countries with no sign of increased micrcoephaly.  And while microcephaly started to increase in 2012, Zika increases came on the scene in July 2014.

http://kellybroganmd.com/pregnancy-friendly-protection-truth-about-whooping-cough-vaccine-pertussis/

“Pertussis incidence was waning on its own until a 1980 mandate to vaccinate in 42 states. Since this time, and since the introduction of the seemingly “less dangerous” acellular pertussis or whooping cough vaccine (the whole cell vaccine was so clearly toxic that seizure activity and fevers drove parents away from vaccination, and it still took almost 50 years to change the product) was introduced in 1996, ten years after pharmaceutical companies were granted immunity through the National Childhood Vaccine Injury Act (i.e. ten years after there stopped being any incentive to produce safe vaccines).”  Dr. Kelly Brogan

http://www.thevaccinereaction.org/2016/06/so-what-about-the-other-pregnant-honduran-woman-who-didnt-have-zika-2/  And while one pregnant Honduran woman vacationing in the US who tested positive for the virus and gave birth to a child with microcephaly made headline news, another Honduran woman who gave birth to a child with microcephaly and tested negative was barely mentioned.  Why this extreme bias?

https://jonrappoport.wordpress.com/2016/01/31/busted-25000-cases-of-microcephaly-in-the-us-per-year/  The US has 25,000 cases of microcephaly each year, but has nothing to do with Zika infection.  Mosquitos here in the states can’t even carry the virus.

http://www.reuters.com/article/us-health-zika-who-idUSKCN0V61JB

“No one has the $500 million on hand to take it (a vaccine) all the way to human trials. Somewhere along the course we hope to have big pockets join us,” Bogoch said.

And in the end, it’s all about vaccines.

As MSIDS patients we are infected with God knows what.  A literal hodgepodge of infections that testing can’t pick up.  Doctors don’t take us seriously, insurance won’t cover our treatment, and we have symptoms that make Zika look like a walk in the park.  

But, this fixation on rare tropical diseases such as Zika, West Nile, and others is bizarre when there are far worse pathogens debilitating and killing thousands of people.  Researchers, doctors, professionals – they don’t seem to want to touch MSIDS (multi systemic infectious disease syndrome – or Lyme with friends) with a ten-foot pole.

And, I think I know why.

Besides digging up some inconvenient historical facts about pathogens that have been tweaked in a lab somewhere for questionable purposes, there’s the vaccine issue.  Seems it’s always about vaccines these days.

http://www.nytimes.com/2002/02/28/business/sole-lyme-vaccine-is-pulled-off-market.html  Did you know that the LYMERIX vaccine which was pulled off the market due to “poor sales” caused 640 emergency room visits, 34 life threatening reactions, 77 hospitalizations, 198 disabilities, and 6 deaths?  In a vile cesspool of conflicts of interest are university patent holders, drug companies, and the FDA itself as another patent holder.  It generated 40 million dollars before it was yanked. (2008, Drymon)

http://www.yourlawyer.com/topics/overview/lymerix  One doctor stated that 21 patients developed severe arthritis after receiving the LYMERIX vaccine.

http://www.lymediseaseassociation.org/index.php/about-lyme/controversy/vaccine/261-lymerix-meeting

“Given that Dr. Marks lead the clinical trials for Lymerix’s competitor, the OspA vaccine produced and then abandoned by Aventis Pasteur, his conclusions mean a lot. “In my opinion,” he told FDA officials, “there is sufficient evidence that Lymerix is causally related to severe rheumatologic, neurologic, autoimmune, and other adverse events in some individuals. This evidence is such as to warrant a significantly heightened degree of warnings and possible limitations or removal from marketing of Lymerix.”

Since the public is now wary of the Lyme (borrelia) vaccine, they’ve changed their approach to focus on wildlife and pets, despite the fact that hamsters developed arthritic joints when infected with Bb (borrelia) or the Osp A vaccine! http://www.lymenet.de/literatur/12tbdconference/day1/day1.htm#OspA%20Induces%20Lyme%20Arthritis%20in%20Hamsters

It is convenient that these poor creatures can’t complain or sue drug producers and that all these products and animal vaccines will bring in a tsunami of money that so far hasn’t found a gold standard diagnostic test or created any benefit to MSIDS patients in any way, shape, or form.  Infection rates climb higher and higher while the CDC and IDSA sit idly by.

So when you call your local pharmacy and have to listen to vaccine scare tactics for 10 minutes which tempt you to get that flu vaccine or any other vaccine being pushed on you, please read up on the facts first and be informed.  It’s your body and you are already in a war with a pathogen invasion.  Don’t let anyone bully you into injecting something into your body that has every potential of making your health worse.

For more information read:

https://madisonarealymesupportgroup.wordpress.com/2015/06/19/a-word-on-vaccines/

https://madisonarealymesupportgroup.wordpress.com/2015/07/15/vaccines-continued/

While the world has elevated Zika to rock star status, there is a gigantic white elephant still standing in the room.

Health Policy Recap

Recap of the Evidence Based Health Policy Project held at the Wisconsin Capital yesterday:

Dr. Osorio, Associate Professor and Researcher, Department of Pathobiological Sciences, UW Madison spoke on Zika. If you are unfamiliar with this virus, please read: https://madisonarealymesupportgroup.wordpress.com/2016/02/05/zika-sexually-transmitted/  The most important take aways from his slide show was : 1)  80% of those infected with Zika don’t even know they have it.  2)  1 in 5 will have mild symptoms (fever, rash, joint pain, or conjunctivitis) lasting up to a week, and while those in Africa and South America are experiencing high infection rates, WI isn’t even on the radar (my words). One of the most important things he emphatically stated was that Zika caused the deaths of two babies due to two tissue samples that had Zika in them. (please hold this thought, I will deal with this later)

Next, Susan Paskewitz, Professor and Researcher, Medical Entomology Laboratory, UW Madison spoke primarily on West Nile Virus and Lyme Disease – with an emphasis on ticks and mosquitos. They have found some West Nile in mosquitos in WI but that the Northern mosquitos can not even carry Zika. She also stated that in regards to Lyme (borrelia), the two notorious carriers are the Dog tick (wood tick) and the deer tick (black legged tick), and that there is between 30,000 and 40,000 reported cases of Lyme (borrelia) in Wisconsin. She also stated that Wisconsin is a hot spot for Anaplasma with over 500 cases. She affirmed that ticks in WI are everywhere and on the move and that due to this, the disease has expanded as well.  There is a nifty website where you can check out great information on ticks here: labs.russell.wisc.edu/wisconsin-ticks/.

After the slide shows they gave time for questions.

These are the things I spoke about:

*Since the EBHPP’s purpose and goals are to give timely, high quality information for evidence based decision making to increase UW research and teaching in topical issues of state public policy, I asked if it wasn’t perhaps more beneficial to discuss and act on something that Wisconsinites can get in their backyard, bedroom, and can spread congenitally?

*In regards to Zika I pointed out the statistics mentioned above as well as the fact that results of 2 tissue samples showing Zika is NOT evidence that the virus caused microcephaly that that we have viruses all over us, some good, some bad, but that doesn’t mean we are experiencing symptoms or active infection. Correlation is simply not the same as causality. There needs to be in depth studies on thousands of babies – those with and those without microcephaly, with pregnant women enrolled prospectively being monitored throughout the pregnancy with conclusive laboratory evidence.

*I also proposed two events that happened in the past year that more probably could have caused this microcephaly: 1) Brazil’s National Vaccine Schedule with DTap for Pregnant women to be given in the 27th week, 36th week, and up to 20 days prior to the expected date of birth – regardless of the lack of safety or effectiveness of Boostrix being established in pregnant women and that the Brazilian government has been vaccinating perhaps hundreds of thousands of pregnant women.

Published on Mar 29, 2016 Published on Mar 29, 2016 (15 min)
NVIC’s Barbara Loe Fisher reviews the medical literature that reveals that pertussis vaccines are not effectively preventing pertussis infection. To learn more continue to watch this commentary or read the fully referenced version at www.NVIC.org.  Join NVIC’s Advocacy Portal to protect vaccine choice at www.NVICadvocacy.org.

2) A report published by the Physicians in the Crop-Sprayed Villages of Argentina that discounts the theory that the increase in microcephaly is due to Zika and that a chemical known as pyriproxyfen (C20 H19 NO3), a pyridine-based pesticide to eradicate mosquitoes has been applied by the State on drinking water used by the affected population for 18 months. Then I reminded them of our own experience of using DDT which caused birth defects and even deaths. Both of these events were about the length of the gestational period – just in time to see microcephaly. (Zika has been around for over 40 years and never caused problems before)

http://www.thevaccinereaction.org/2016/05/new-york-aerial-sprays-altosid-and-vectobac-pesticides-to-combat-zika/ Yet, despite Médicos de Pueblos Fumigados arguing that an insect growth regulator used in Brazil might actually be the reason for the microcephaly, the New York City Department of Health and Mental Hygiene is releasing similar growth regulators, Altosid and VectoBac, in pellet form from low-flying helicopters in Brooklyn, Queens, Staten Island, and The Bronx.

*I also spent considerable time discussing the plight of Lyme patients. That we are co-infected with numerous pathogens which make our cases far more complex than most realize. I spoke of borrelia, alone, and that it is pleomorphic with three shapes it can change into at will and that proper treatment needs to address this complexity and that 21 days of doxycycline, the current CDC standard of care is like throwing sand into the ocean. I spoke of 3 generations of Wisconsinites living under the same roof – all infected with MSIDS (multi systemic infectious disease syndrome). I explained that the myth that Lyme (borrelia) only causes a little joint pain and fatigue needs to be dispelled and that there is significant cognitive and psychological impairment with some suffering with severe anxiety, rage, confusion, depression, and memory loss.

115_pandemic316x316

http://lymestats.org

Let’s stop talking about exotic tropical diseases and focus on what’s keeping Wisconsinites sick!


Powassan Virus

http://www.cmaj.ca/content/161/11/1419.short  The Powassan Virus was discovered in Powassan, Ontario in 1958 when a 5-year-old boy died of severe encephalitis.

https://www.youtube.com/watch?v=4gKNa6JBeH8  A brief explanation by Dr. Michael Smith.  (approx. 1 min)

http://wwwnc.cdc.gov/eid/article/18/10/12-0621_article   POW is a single-stranded RNA virus in the genus Flavivirus of the Flaviviridae family. There is substantial serologic cross-reaction with other flaviviruses (dengue, St. Louis encephalitis, yellow fever, Japanese B encephalitis, West Nile virus). RNA viruses generally have high mutation rates. Both prototypic (POWV) and deer tick virus (DTV) genotypes exist and are cousins to the tick-borne encephalitis virus causing significant illness in Europe. All sequenced strains in Minnesota are of the DTV genotype.

https://www.dhs.wisconsin.gov/tickborne/powa-april-2010-wmj.pdf  Presence of POW-lineage viruses has been well documented in at least 38 mammal species including small and medium sized wild animals (rodents, woodchucks, skunks) and domestic animals (dogs, cats), with several species of ticks proven to be vectors at this time. Human infection with Powassan Virus has been documented in North America and Russia.

Selection bias in identifying the infection may exist, diminishing the reported incidence to only patients with severe disease.

http://www.cdc.gov/mmwr/preview/mmwrhtml/mm5035a4.htm   Because of the lack of awareness and the need for specialized laboratory tests to confirm diagnosis, the frequency of POW encephalitis may be greater than previously suspected. POW encephalitis should be included in the differential diagnosis of all encephalitis cases occurring in the northern United States, especially the Northeast. Laboratory tests for POW virus infection are not commercially available but can be requested through state public health laboratories for testing at CDC; however, Coppe Laboratories, right here in Waukesha, Wisconsin, has a direct and indirect test for Powassan virus. It requires a simple blood draw.   http://wisconsinwoodlands.org/study-of-wisconsin-ticks/  In this article Coppe Lab collected more than 2,000 ticks and found borrelia (the causative agent in Lyme Disease) in more than half as well as a high number of POW/deer tick viruses in ticks of hyper-endemic regions of NW Wisconsin, and that ticks carrying disease are in almost every county in WI.

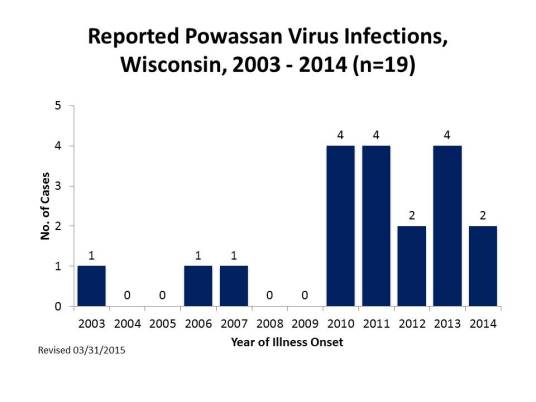
reported-powassan-virus-infections-2003-2014

Graph taken from:

https://www.dhs.wisconsin.gov/tickborne/powassan.htm

The virus is becoming more common in humans and appears to differ from Lyme Disease (borrelia) in that it is transmitted much more quickly (within minutes) and fatally (10-15% of cases), with 60% of patients who survive have permanent neurological dysfunction; however, please know that there is disagreement in the medical community on transmission times and much remains unclear. It is warned that only a single strain of POW has been used to determine vector competence or transmission time or viral amount to cause clinical illness. http://labs.russell.wisc.edu/wisconsin-ticks/powassan-virus/

https://wwwnc.cdc.gov/eid/article/23/8/16-1971_article  A study in Marshfield, WI showed that when 95 patients were tested for suspected tick-borne disease, 66% showed evidence of current or prior Lyme infection.  Of those patients, 17% had serologic evidence of acute POWV infection, demonstrating that POWV may affect more patients than we know.

The biggest challenge in addressing the Powassan infection will be distinguishing it from Lyme disease. The similarity of their etiology and symptomatology is extraordinary. If symptoms exacerbate rapidly, then that may be the critical sign that a Powassan virus is present.  

http://naturalsociety.com/powassan-virus-ticks-now-carrying-virus-worse-than-lyme-disease/  The Powassan virus attacks the nervous system and can infect the brain causing inflammation (encephalitis). It can also affect the lining of the brain (meningitis). Symptoms vary widely from none to death. http://wwwnc.cdc.gov/eid/article/18/10/12-0621_article  Patients with POW infection typically exhibit encephalitis after an incubation period of 1–4 weeks. Fever and headache are common.  Mental status changes, cerebellar symptoms (trouble with motor control, attention, and language), and weakness or paralysis in half of the body (reported in 50% of cases) are also common and may be severe. Results of CSF testing and brain imaging are generally consistent with viral encephalitis. Reverse transcription PCR of CSF, serologic testing of CSF, and serologic testing of serum are the preferred diagnostic tests, but they are not widely available. Pathogenesis is due to lymphocytic infiltration of perivascular neuronal tissue with a predilection for gray matter, including thalamus, midbrain, and cerebellum. Other symptoms include but are not limited to:  fever, headache, vomiting, weakness, and memory loss.

http://www.caryinstitute.org/newsroom/more-tickborne-diseases-other-lyme-maybe-just-don-t-go-outside  In this case a high school student was mildly ill for several weeks with a cough, but then collapsed and died.

http://wwwnc.cdc.gov/eid/article/18/10/12-0621_article
Case Report:  On May 30, 2011 a 67-year-old woman from Aitkin, Minnesota checked into the Abbott Northwestern Hospital in Minneapolis, complaining of dizziness, high fever, chills, nausea and malaise, as well as intermittent confusion with slurred speech.  As an avid gardener and hiker, the woman had been exposed to a number of vectors endemic to her area, such as deer ticks and mosquitos. She also had a long history of medical issues, including colon cancer, hypertension, cutaneous lupus, and a remote cerebral aneurysm, which was treated surgically.  Although the patient was alert upon arrival at the medical facility, by the next day her condition severely deteriorated. Within hours she became unresponsive. Over night her breathing stopped completely and she required intubation. The patient remained in her comatose state for nearly two weeks before the medical ventilator was removed and she died. It was not until after the patient’s death that serological testing was able to identify Powassan Virus (POWV) as the disease agent.

https://www.lymedisease.org/lyme-sci-powassan-update/  Powassan Virus put North Carolina Senator Kay Hagan into a 43-day coma, and while recovering she has difficulty speaking and is still unable to walk.

Arbovirus Infection MnLA Jan 2016-3  Very informative slide presentation by Dr. David Baewer, Chief Medical Officer, Coppe Laboratories, Waukesha, Wisconsin.

For an excellent article on how viruses work:
http://science.howstuffworks.com/life/cellular-microscopic/virus-human.htm

Please discuss all treatment options with your health care professional

Antibiotics are not effective against viruses, and no effective anti-viral drugs have been discovered for POW, hence there is no specific treatment; however, there is much that can be done to improve the immune system, thereby, lessoning the effects of the virus, as well as taking medications to reduce brain swelling, respiratory support, and IV fluids. 

http://health-truth.com/our-program/health-articles/chronic-fatigue-syndrome/how-to-conquer-the-viral-bacterial-syndrome/  According to Michael Biamonte, C.C.D., the immune system uses nutrients from food to manufacture substances that attack and kill viruses. Viruses help bacteria by invading the cells in an area, and if the immune system is too weak, bacteria begin to swarm the damaged cells invaded by the virus. As the virus begins to die having gone through its life cycle, the bacteria then start a secondary infection. For an MSIDS (multi systemic infectious disease syndrome) patient, they might be fighting borrelia (Lyme), Babesia, Bartonella, and many more pathogens, on top of viruses. This makes their disease much more complex.

27_sugar316x316Graphic from Lymestats.org

Biomonte says to avoid sugar as it reduces the number of white bloods cells which fight off infection. He states that garlic is the most effective food against all infections as well as Echinacea, Zinc, water-soluble vitamin A, protein (stimulates the adrenal and thyroid), and eggs (contain large quantities of lecithin).

http://science.howstuffworks.com/life/cellular-microscopic/light-virus.htm  Interestingly, a study done at Arizona State and Johns Hopkins shows strong, quick blasts of purple light from a low power laser can kill viruses by vibrating and damaging their outer shells, but unlike other treatments doesn’t cause mutatations leading to viral resistance. Blood UV radiation, similarly to the laser, also kills viruses by breaking down their cell walls.

Anti-virals:

Green Tea
Licorice (glycyrrhizin)
Pau D-Arco
Olive Leaf
Elderberry
Zinc
Garlic
Echinacea
St. John’s Wort
Coconut oil
Eucalyptus oil
Vitamin C

Monolaurin

More on Powassan:  https://madisonarealymesupportgroup.com/2017/06/28/powassan-can-kill/

https://madisonarealymesupportgroup.com/2017/05/05/powassan-another-reason-to-avoid-ticks/

https://madisonarealymesupportgroup.com/2017/04/20/first-case-of-powassan-in-connecticut-in-a-five-month-old-baby/

https://madisonarealymesupportgroup.com/2017/05/18/powassan-and-bb-infection-in-wisconsin-and-u-s-tick-populations/