Archive for the ‘Lyme’ Category

Corona Virus & Lyme Disease – Drs. Bock & Rawls

 Approx. 5 Min.

March 2, 2020,

Dr. Bock

The Corona Virus & Lyme Disease

Information on the Corona Virus and ways to protect yourself as a Lyme patient or if you have a compromised immune system. In the next few days we will be putting out an immune system boosting vitamin and supplement regiment with suggestions to help better protect yourself from viral infections.

http://  Approx. 15 Min.

March 4, 2020

Dr. Rawls

The coronavirus or COVID-19 has gained a foothold in the United States, and misinformation about the illness is rampant. Dr. Bill Rawls explains who’s really at risk, plus how to protect yourself and the best ways boost your immune system. (Talks about various herbs)

For more:  https://madisonarealymesupportgroup.com/2020/03/09/coronavirus-lyme/

https://madisonarealymesupportgroup.com/2020/02/28/coronavirus-how-bad-can-it-get-includes-treatments-disulfiram-is-one/

https://madisonarealymesupportgroup.com/2020/02/04/novel-coronavirus-the-latest-pandemic-scare-which-professor-states-is-a-biowarfare-weapon/


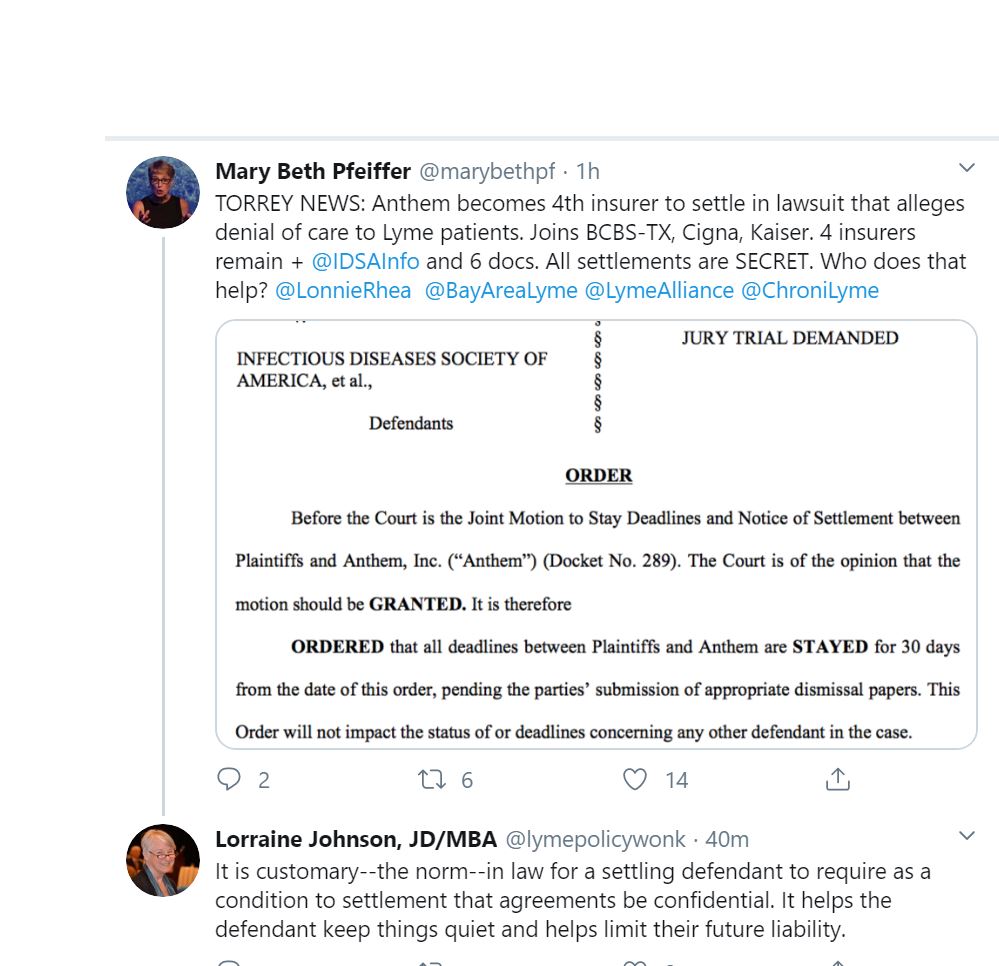
Anthem – 4th Insurance Company Settles in Lyme Lawsuit

https://www.lymedisease.org/torrey-anthem-settles-lyme/

Fourth insurance company settles in Lyme patient lawsuit

**Comment**
Keeping things quiet is the norm for the IDSA in its handling of Lyme/MSIDS.  I can only imagine the stress this has caused all the patients who are involved.

The Long-Term Persistence of Borrelia burgdorferi Antigens & DNA in the Tissues of Lyme Disease Patient

https://www.mdpi.com/2079-6382/8/4/183

The Long-Term Persistence of Borrelia burgdorferi Antigens and DNA in the Tissues of a Patient with Lyme Disease

*Author to whom correspondence should be addressed.
Antibiotics 2019, 8(4), 183; https://doi.org/10.3390/antibiotics8040183
Received: 22 August 2019 / Revised: 6 October 2019 / Accepted: 9 October 2019 / Published: 11 October 2019
(This article belongs to the Special Issue Antibiotics Resistance of Borrelia)
Whether Borrelia burgdorferi, the causative agent of Lyme disease, can persist for long periods in the human body has been a controversial question. The objective of this study was to see if we could find B. burgdorferi in a Lyme disease patient after a long clinical course and after long-term antibiotic treatment. Therefore, we investigated the potential presence of B. burgdorferi antigens and DNA in human autopsy tissues from a well-documented serum-, PCR-, and culture-positive Lyme disease patient, a 53-year-old female from northern Westchester County in the lower Hudson Valley Region of New York State, who had received extensive antibiotic treatments during extensive antibiotic treatments over the course of her 16-year-long illness. We also asked what form the organism might take, with special interest in the recently found antibiotic-resistant aggregate form, biofilm. We also examined the host tissues for the presence of inflammatory markers such as CD3+ T lymphocytes. Autopsy tissue sections of the brain, heart, kidney, and liver were analyzed by histological and immunohistochemical methods (IHC), confocal microscopy, fluorescent in situ hybridization (FISH), polymerase chain reaction (PCR), and whole-genome sequencing (WGS)/metagenomics.
We found significant pathological changes, including borrelial spirochetal clusters, in all of the organs using IHC combined with confocal microscopy.
The aggregates contained a well-established biofilm marker, alginate, on their surfaces, suggesting they are true biofilm.
We found:
  • B. burgdorferi DNA by FISH, polymerase chain reaction (PCR), and an independent verification by WGS/metagenomics, which resulted in the
  • detection of B. burgdorferi sensu stricto specific DNA sequences
  • IHC analyses showed significant numbers of infiltrating CD3+ T lymphocytes present next to B. burgdorferi biofilms
In summary, we provide several lines of evidence that suggest that B. burgdorferi can persist in the human body, not only in the spirochetal but also in the antibiotic-resistant biofilm form, even after long-term antibiotic treatment. The presence of infiltrating lymphocytes in the vicinity of B. burgdorferi biofilms suggests that the organism in biofilm form might trigger chronic inflammation. View Full-Text
__________________
**Comment**
When will there be enough evidence for mainstream medicine?

Coronavirus & Lyme

https://www.treatlyme.net/guide/coronavirus-lyme

Coronavirus (Covid-19) & Lyme Image

published 3/4/20

By Dr. Marty Ross

About Coronavirus (Covid-19) and Lyme

Many people with and without Lyme are fearful of Coronavirus also called Covid-19. In my Seattle Lyme practice, I am answering questions about what one should do to protect themselves and to boost their immune systems. Many wonder if immune dysregulation, caused by Lyme, increases their chances of acquiring the virus, having a severe case, or even death. (See link for article)

_________________

For more:  https://madisonarealymesupportgroup.com/2020/02/22/how-to-protect-yourself-your-family-from-infections/

https://madisonarealymesupportgroup.com/2020/02/28/coronavirus-how-bad-can-it-get-includes-treatments-disulfiram-is-one/

https://madisonarealymesupportgroup.com/2020/02/13/washington-doctors-successfully-treat-coronavirus/


Study Shows Lyme Patients Treated With Immune Suppressants Have Frequent Comorbidities, Late Stage Symptoms, & Treatment Failure

https://danielcameronmd.com/is-suppressing-immune-system-harmful-to-lyme-patients/

IS SUPPRESSING IMMUNE SYSTEM HARMFUL TO LYME PATIENTS?

Lyme disease, treatment

There have only been a few published reports detailing the outcome of treatment on Lyme disease patients who are immunocompromised. Now, a study by Maraspin and colleagues¹ evaluates the impact of tumour necrosis factor-alpha (TNF-α) inhibitors, medications that suppress the immune system, on Lyme disease patients.

The authors compared 16 individuals receiving TNF-α inhibitors with 32 healthy controls. The individuals had confirmed Lyme disease with an erythema migrans rash manifestation. The patients received immune-suppressing medications, which included adalimumab, infliximab, etanercept, golimumab. These were often combined with other immunosuppressant drugs for rheumatic (13 patients) or inflammatory bowel (3 patients) disease.

Investigators found that, when compared to controls, patients receiving immunosuppressants had:

  1. frequent comorbidities other than immune-mediated diseases (62.5% vs. 25%)
  2. symptoms/signs of disseminated Lyme borreliosis (18.8% vs. 0%)
  3. treatment failure (25% vs. 0%.)

In fact, 4 out of 16 (25%) Lyme disease patients treated with immunosuppression therapy failed treatment. Three of these four patients required retreatment. One of them was quite ill.

“The immunocompromised patients were also more likely to fail treatment than patients who were not immunocompromised,” writes Maraspin.

The fourth patient, a 44-year-old man, remained well until his 6-month follow-up visit. But, “7 months after beginning antibiotic treatment he developed severe arthralgia, fatigue and back pain,” writes Maraspin in the Journal of Clinical Medicine.

A specialist was consulted but could not confirm whether the man had a relapse of rheumatoid arthritis. He remained ill for the next 5 months. And tests revealed his IgG antibody to VlsE borrelial antigens rose from 542.1 to 1462.0 AU/mL.

His symptoms improved following re-treatment with the antibiotic, ceftriaxone.
The authors recommended regular follow-up visits to carefully monitor immunocompromised Lyme patients.
References:
  1. Bransfield RC, Friedman KJ, Differentiating Psychosomatic, Somatopsychic, Multisystem Illnesses and Medical Uncertainty. Healthcare 2019, 7(4), 114.

__________________

**Comment**

I would argue that ALL Lyme/MSIDS patients are immune suppressed even if they are not taking immune suppressing drugs, which means the outcome would be similar.  This issue desperately needs to be addressed as mainstream medicine and research continues to approach this as a singular pathogen illness when recent research shows 65% of TBD patients produce immune responses to various microbes:  https://madisonarealymesupportgroup.com/2018/10/30/study-shows-lyme-msids-patients-infected-with-many-pathogens-and-explains-why-we-are-so-sick/

Here’s a study shows patients with EM who were receiving rituximab (an immune suppressant) for underlying disease show more borrelia isolated in the blood and that their cases are more often disseminated than in immunocompetent patients : https://madisonarealymesupportgroup.com/2019/08/06/em-course-outcome-in-patients-treated-with-rituximab/

And here we see ticks have immunosuppressive proteins in their saliva:  https://madisonarealymesupportgroup.com/2019/08/14/what-tick-saliva-does-to-the-human-body/

The exact cocktail of a tick’s saliva proteins changes every few hours, Ribeiro says. The thousands of proteins in its saliva are highly redundant in function, and the tick cycles through them as a way of circumventing a host’s immune system. Immune systems take time to recognize and react to a foreign tick protein, and this strategy simply doesn’t give a host’s cells a chance to do that. Suppose, Ribeiro says, “Monday a tick starts feeding on you and injecting the saliva in you.” By Friday, when your body can mount a proper immune response against those first proteins, “the tick has already changed the repertoire.”

https://madisonarealymesupportgroup.com/2019/12/15/immunosuppressive-proteins-found-in-tick-saliva-in-every-life-stage/

Taken together, these results suggest that Ip-sL1 and Ip-sL2 confer immunosuppressive functions and appear to be involved in the transmission of pathogens by suppressing host immune responses, such as cytokine production and dendritic cell maturation.

In other words, there are immunosuppressants within tick saliva that makes it easier for transmission to occur.

It only follows that giving patients immunsuppressants (or those patients infected with numerous pathogens) will function similarly in the body – allowing for pathogen proliferation which will be demonstrated by more severe disease.